
Provider Application at a glance
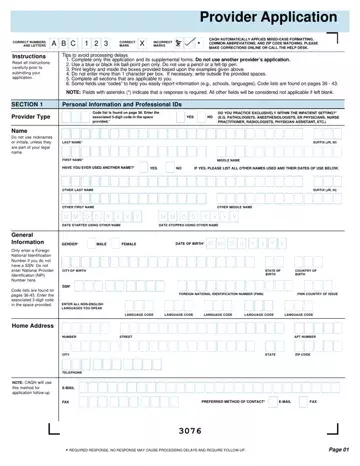
What it is: Provider Application. Read all instructions carefully prior to submitting your application.
A filled-in Provider Application example: a physician fills in the name
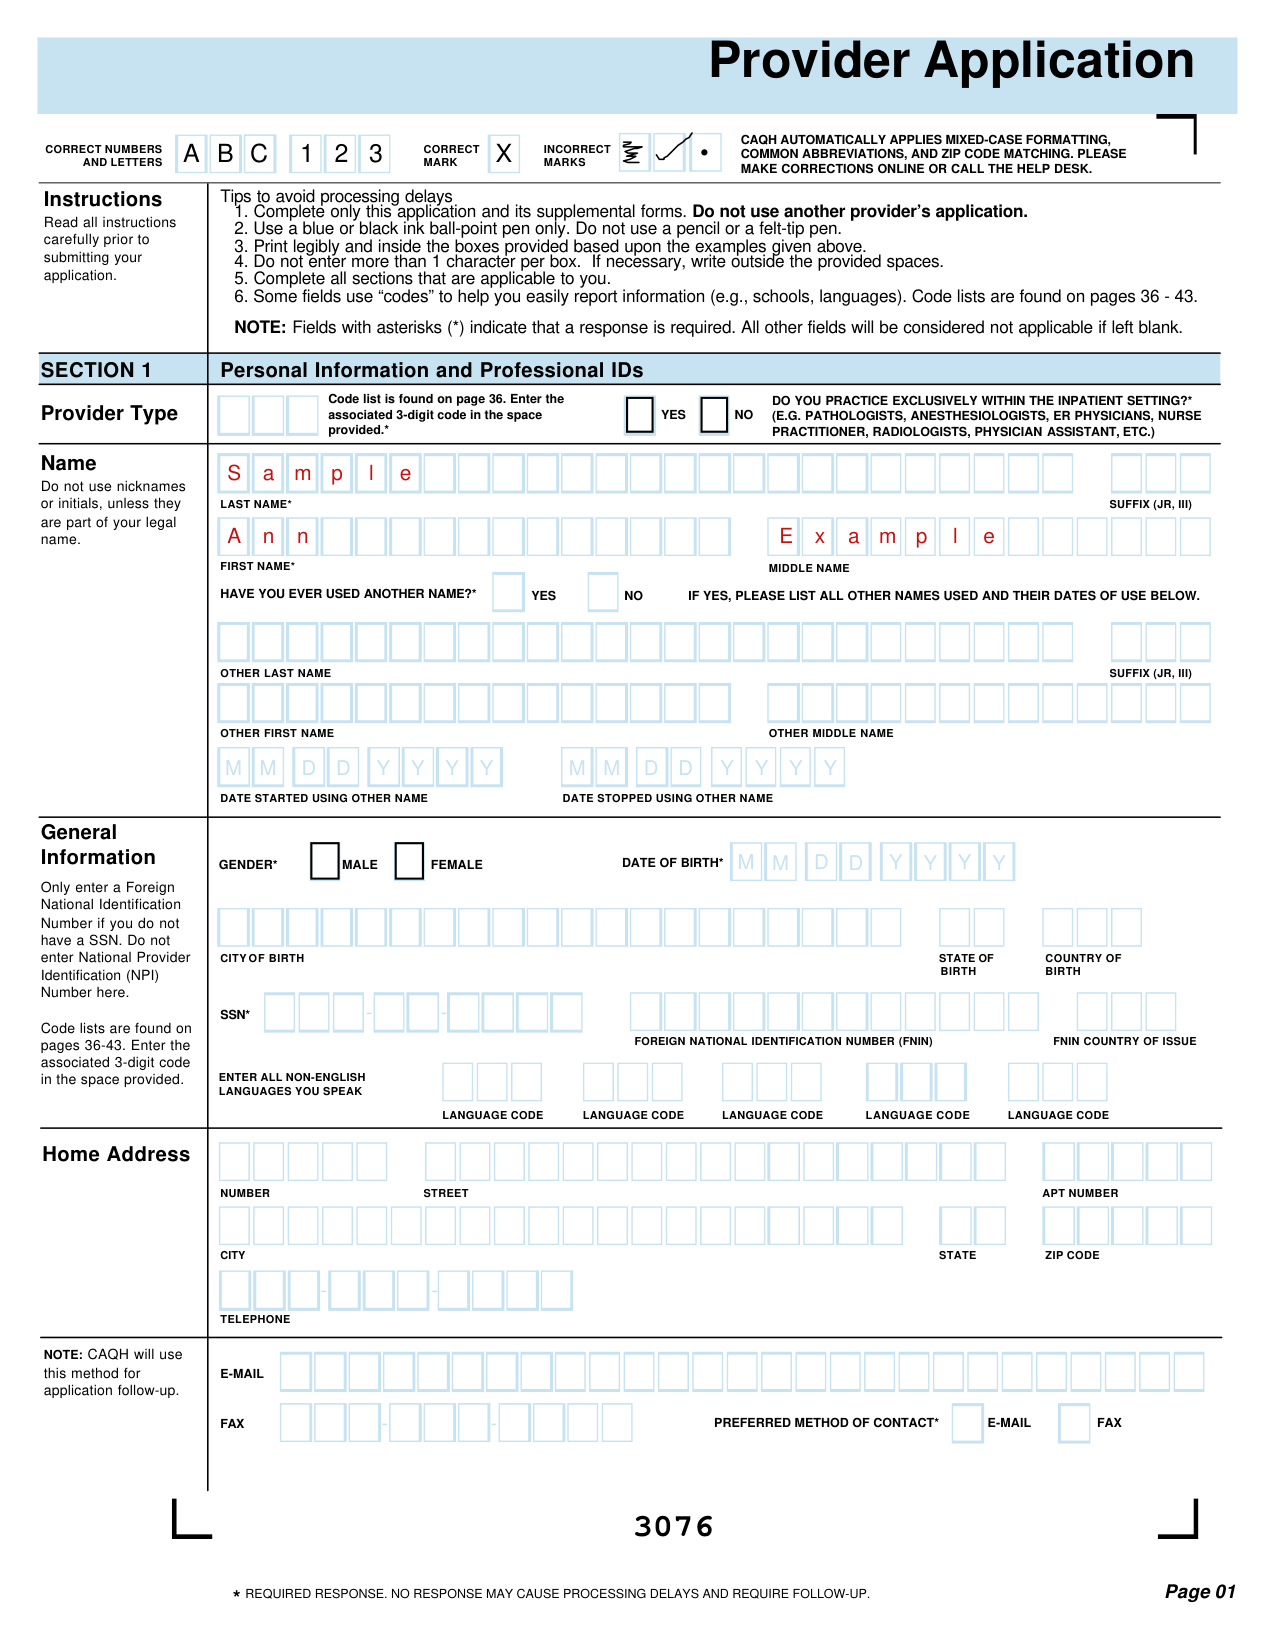
How to fill out Provider Application, box by box
Name
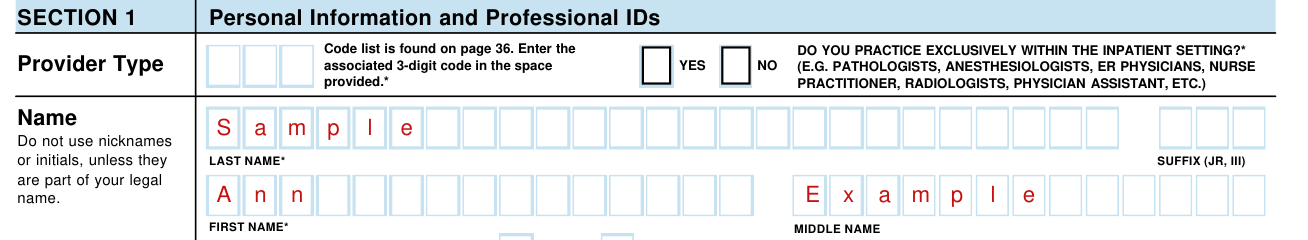
Do not use nicknames or initials, unless they are part of your legal name.
More rules for Provider Application
Complete only this application and its supplemental forms. Do not use another provider's application. Use a blue or black ink ball-point pen only. Do not use a pencil or a felt-tip pen.
Fields with asterisks (*) indicate that a response is required. All other fields will be considered not applicable if left blank.
Only enter a Foreign National Identification Number if you do not have a SSN. Do not enter National Provider Identification (NPI) Number here.
Code list is found on page 36. Enter the associated 3-digit code in the space provided.
CAQH will use this method for application follow-up.
Include all state licenses, DEA Registration and State Controlled Dangerous Substance (CDS) certification numbers.
Non-licensed professionals should enter certification/ registration number in the space provided for license number.
If you have additional Professional IDs to report, use the Professional IDs Supplemental Form on page 19.
Include a chronological work history for the past 10 years.
You are required to provide exactly 3 references. Your application will not be complete without this information.
For any “Yes” response, provide an explanation on the Supplemental Disclosure Question Explanation Form on page 34.
If you are an Allied Health Provider and you do not believe a question is applicable to you, you should answer the question “NO”.
Corrections to the application are permitted at any time prior to a determination of Participation by the Entity, and must be submitted online or in writing, and must be dated and signed by me (may be a written or an electronic signature).
Any material misstatement or omission in the application may constitute grounds for withdrawal of the application from consideration; denial or revocation of Participation; and/or immediate suspension or termination of Participation.
Use the Hospital Privileges (Current) Supplemental Form to continue listing hospitals where you currently have privileges.
Use the Work History Supplemental Form to continue listing work history.
Use the Disclosure Questions Supplemental Form to report any “Yes” response to one or more of the Disclosure Questions in Section 8.
Common questions about Provider Application
Is there a deadline?
I will notify the Entity and/or its Agent(s) within 10 days of any material changes to the information (including any changes/challenges to licenses, DEA, insurance, malpractice claims, NPDB/HIPDB reports, discipline, criminal convictions, etc.) I have provided in my application or authorized to be released pursuant to the credentialing process.
What am I certifying when I sign?
By signing you certify that all information provided by you in your application is current, true, correct, accurate and complete to the best of your knowledge and belief, and is furnished in good faith.
Sources
[1] Provider Application, CAQH (the Official source link on this page).
