


Form DOH CHRC 103 at a glance
What it is: DOH CHRC 103 is the NYS Department of Health request for criminal history record check.
Who signs: Signature of Agency Authorized Person: Date. If you secured his/her fingerprints, enter First Name, Last Name, Title and Date Fingerprinted, and sign on the Signature line.
A filled-in Form DOH CHRC 103 example: a home care agency requests a check
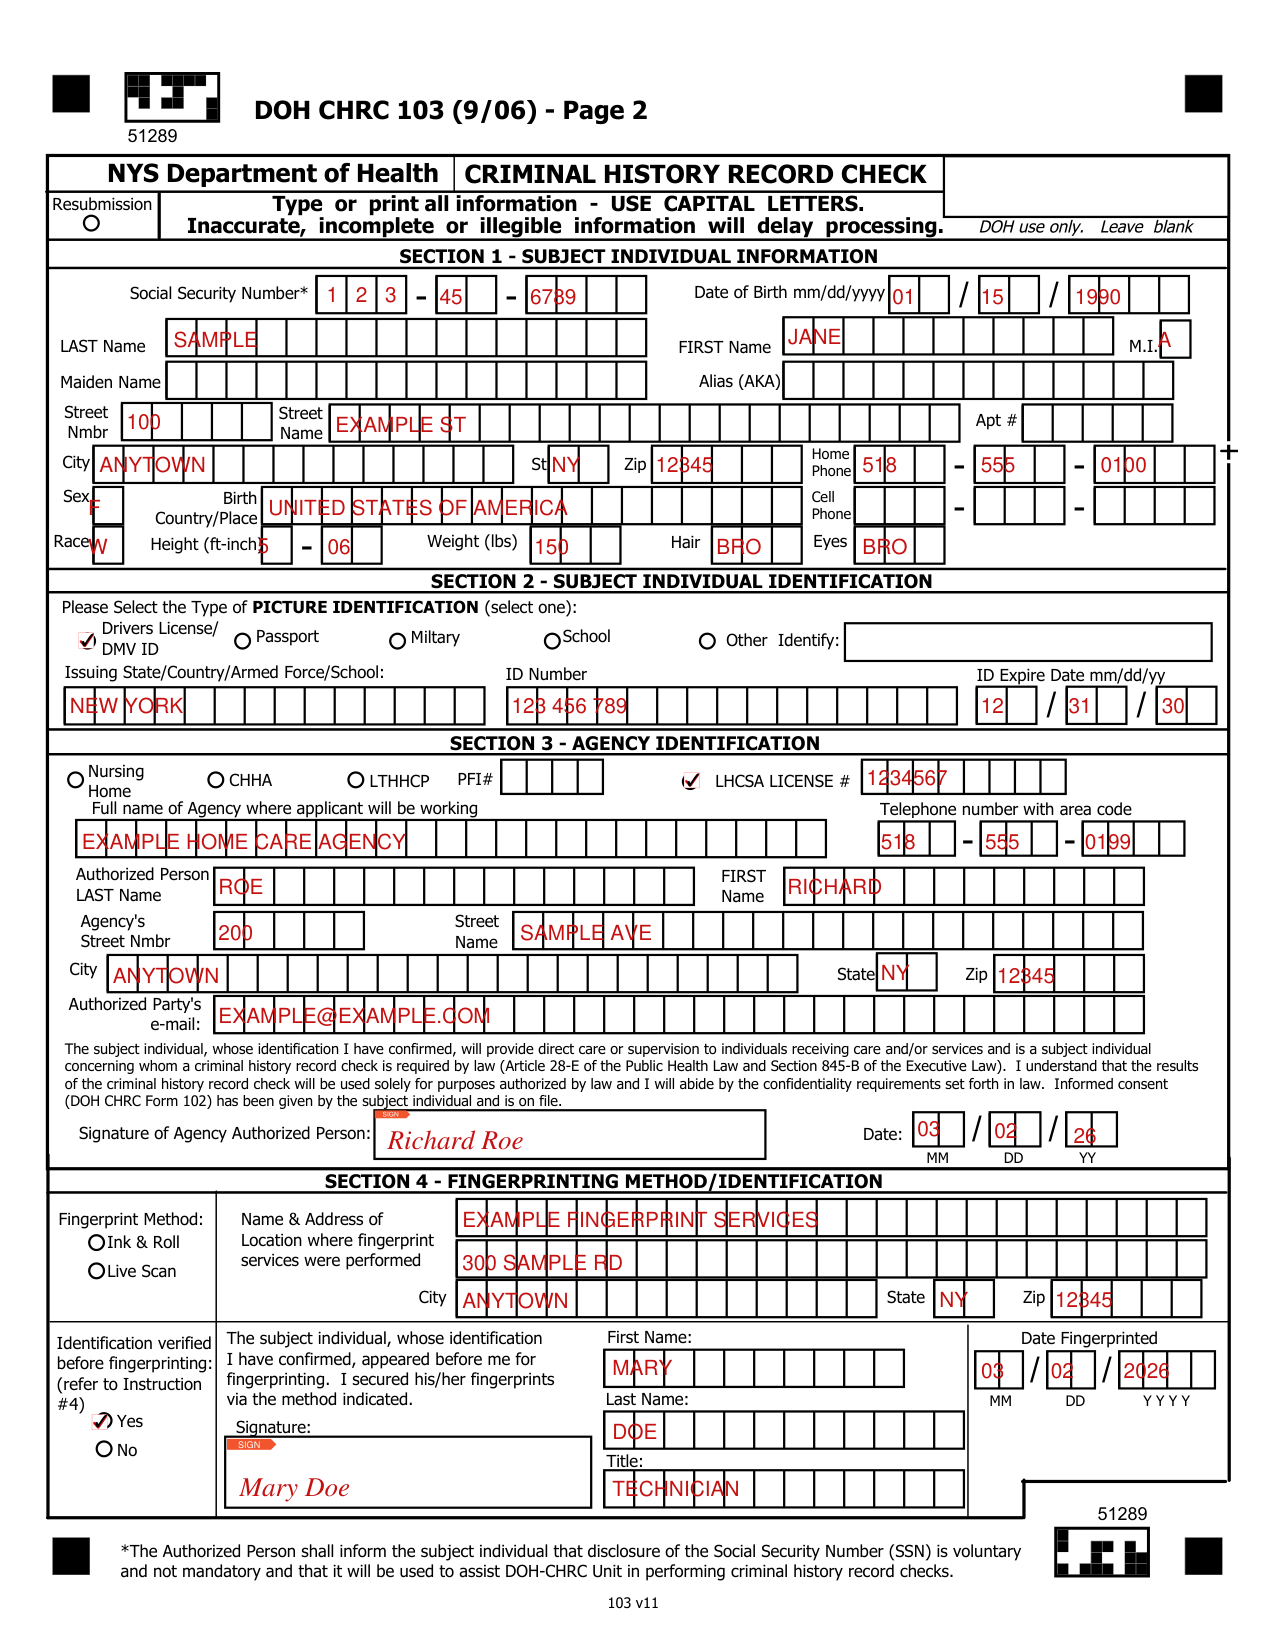
How to fill out Form DOH CHRC 103, box by box
Resubmission, Social Security Number and Date of Birth

Type or print all information - USE CAPITAL LETTERS. Inaccurate, incomplete or illegible information will delay processing.
The Authorized Person shall inform the subject individual that disclosure of the Social Security Number (SSN) is voluntary and not mandatory and that it will be used to assist DOH-CHRC Unit in performing criminal history record checks.
Resubmission.
Date of Birth mm/dd/yyyy.
Name and Alias (AKA)
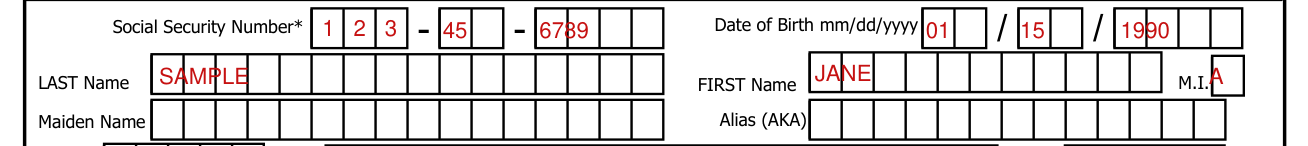
LAST Name, FIRST Name, Maiden Name and Alias (AKA).
Street, City and Phone
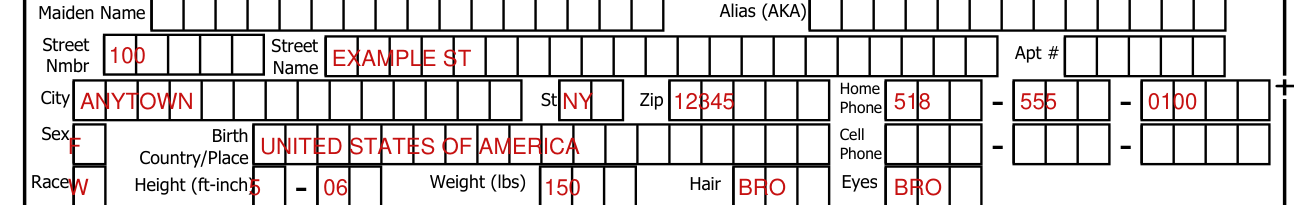
Street Nmbr, Street Name, Apt #, City, St, Zip and Home Phone.
Cell Phone.
Sex, Race, Birth Country/Place, Height, Weight, Hair and Eye
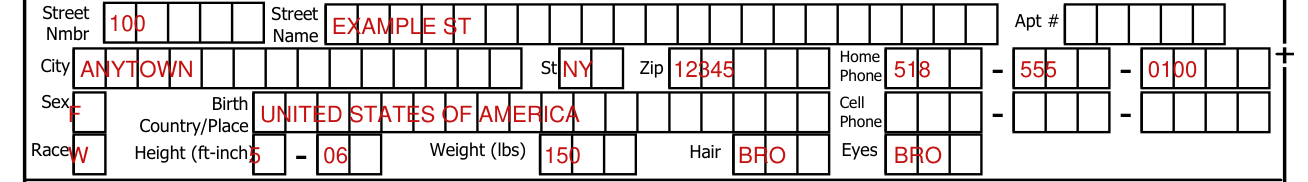
SEX FIELD M - Male F - Female RACE FIELD A - Chinese, Japanese, Filipino, Korean, Polynesian, Indian, Indonesian, Asian Indian, Samoan or any other Pacific Islander B - African black racial groups I - American Indian, Eskimo, or Alaskan native U - Of indeterminable race W - Caucasian, Mexican, Puerto Rican, Cuban, Central/South American or other Spanish origin BIRTH COUNTRY/PLACE FIELD Enter United States of America for those of American birth Enter Country of Birth for those not of American birth HEIGHT FIELD To be completed as a three (3) character value. If reported in feet and inches, the first (leftmost) digit is used to show feet with the two rightmost digits are used to show the inches between 00 and 11. If reported in inches, the leftmost character is "N" followed by two digits. If height in unknown, 000 is entered. The allowable range is 400 to 711. Heights shorter than 4 ft. will be recorded as 400 and taller than 7 ft. 11 in. will be recorded as 711. WEIGHT FIELD In this field, the subject applicant's weight in pounds is entered (000-499). If weight is unknown, 000 is entered. All weight in excess of 499 pounds will be recorded as 499 lbs. HAIR FIELD - COLOR CODES BAL - Bald BLK - Black BLN - Blonde or Strawberry BLU - Blue BRO - Brown GRN - Green GRY - Gray or Partially Gray ONG - Orange PNK - Pink PLE - Purple RED - Red or Auburn SDY - Sandy WHI - White XXX - Unknown
EYE FIELD - COLOR CODES: BLK - Black, BLU - Blue, BRO - Brown, GRY - Gray, GRN - Green, HAZ - Hazel, MAR - Maroon, MUL - Multicolored, PNK - Pink, XXX - Unknown.
Section 2 - Picture Identification
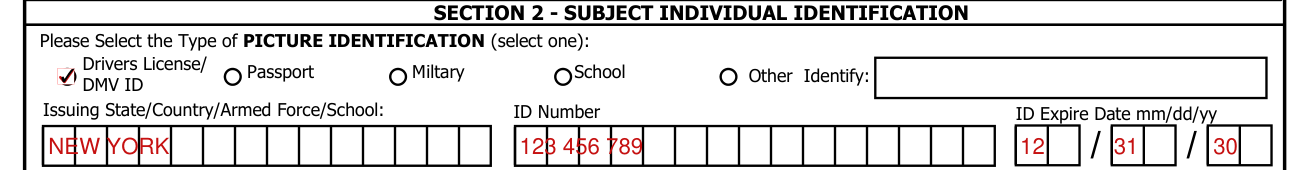
Please Select the Type of PICTURE IDENTIFICATION (select one): Drivers License/ DMV ID, Passport, Miltary, School or Other Identify.
Issuing State/Country/Armed Force/School, ID Number and ID Expire Date mm/dd/yy.
Section 3 - Agency Identification
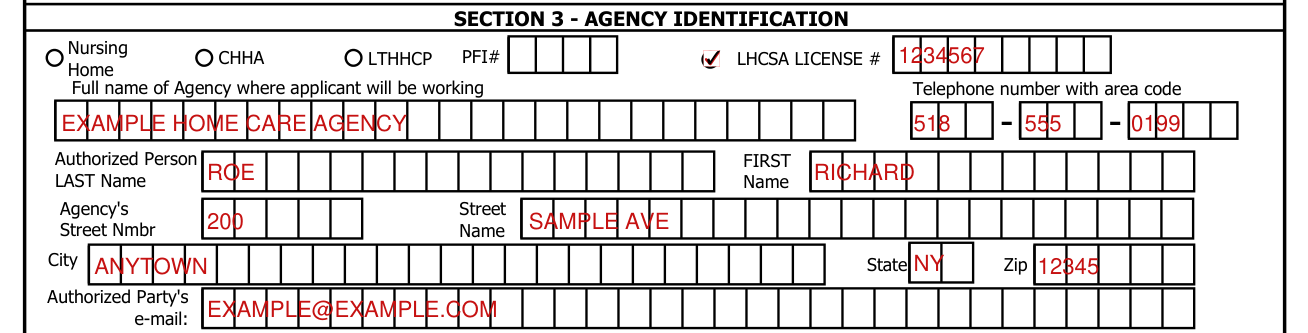
SECTION 3 - AGENCY IDENTIFICATION: Nursing Home, CHHA, LTHHCP, LHCSA LICENSE # and PFI#.
Full name of Agency where applicant will be working and Telephone number with area code.
Authorized Person LAST Name, FIRST Name, Agency's Street Nmbr, Street Name, City, State, Zip and Authorized Party's e-mail.
Signature of Agency Authorized Person

The subject individual, whose identification I have confirmed, will provide direct care or supervision to individuals receiving care and/or services and is a subject individual concerning whom a criminal history record check is required by law (Article 28-E of the Public Health Law and Section 845-B of the Executive Law).
I understand that the results of the criminal history record check will be used solely for purposes authorized by law and I will abide by the confidentiality requirements set forth in law.
Informed consent (DOH CHRC Form 102) has been given by the subject individual and is on file.
Signature of Agency Authorized Person: Date.
Section 4 - Fingerprinting Method/Identification
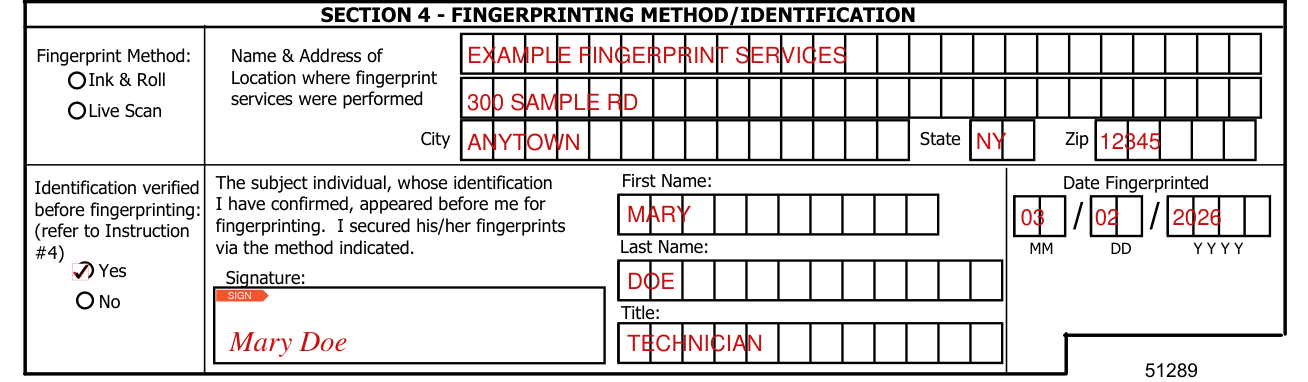
SECTION 4 - FINGERPRINTING METHOD/IDENTIFICATION: Fingerprint Method is Ink & Roll or Live Scan.
Name & Address of Location where fingerprint services were performed: City, State and Zip.
Identification verified before fingerprinting: (refer to Instruction #4) Yes.
The subject individual, whose identification I have confirmed, appeared before me for fingerprinting. I secured his/her fingerprints via the method indicated.
If you secured his/her fingerprints, enter First Name, Last Name, Title and Date Fingerprinted, and sign on the Signature line.
Completing and forwarding the form
Sources
[1] Form DOH CHRC 103 (9/06), Request for Criminal History Record Check, NYS Department of Health (the Official source link on this page).