
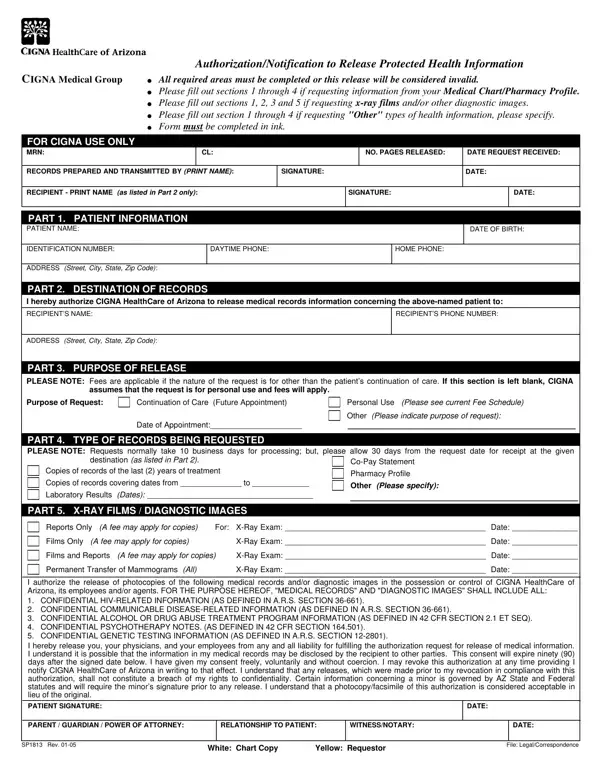

Cigna Form SP1813 at a glance
What it is: Form SP1813 is the Authorization notification to release protected health information.
Who signs: Sign on the Signature of Patient/Guardian/Personal Representative line and enter the Date.
Authorize Cigna Healthcare of Arizona, Inc. dba Evernorth Care Group (the group), previously known as Cigna Medical Group, its employees and/or agents to release your protected health information (PHI) to the persons or entities specified on this form and in the form/manner described under FORMAT / MANNER OF RELEASE. This authorization is voluntary and made to confirm your directions. Once the information is disclosed, it may no longer be protected by federal privacy regulations and may be re-disclosed by the recipient to other parties. Print your responses in ink and complete all required fields.
A filled-in Cigna Form SP1813 example: a patient sends records to her doctor

How to fill out Cigna Form SP1813, box by box
Verification

For ID verification purposes, enter the Patient Name, Date of Birth, Address and the Phone number where you can be reached.
Destination of records

Information will only be disclosed to the person/entity noted. Enter the Recipient's Name, Address, Recipient's Phone Number and Recipient's FAX Number.
Purpose of release

Under PURPOSE OF RELEASE, check Continuation of Care and enter the Date of Future Appointment, check At the request of individual, or check Other.
Description of information to be released
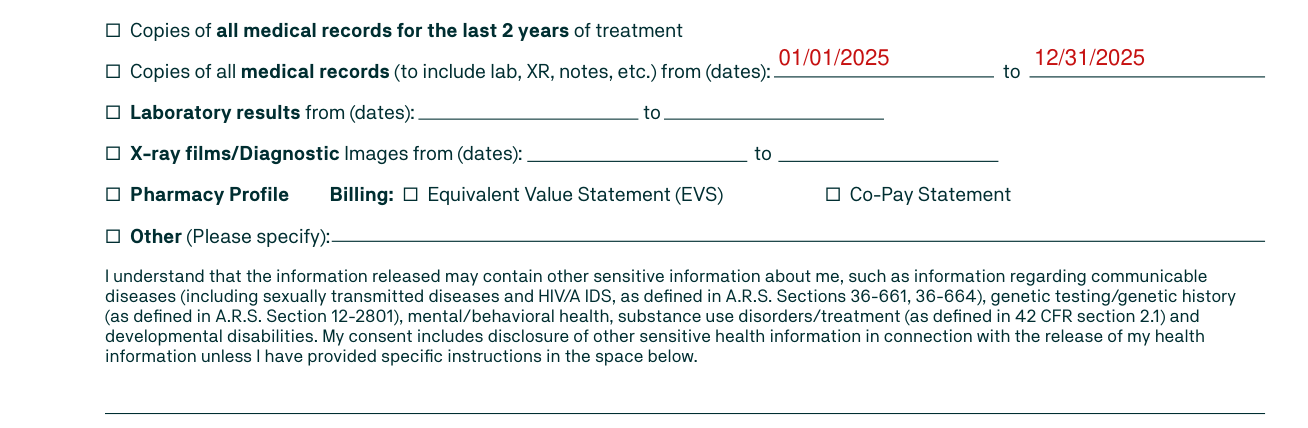
Under DESCRIPTION OF INFORMATION TO BE RELEASED, check Copies of all medical records for the last 2 years of treatment, or check Copies of all medical records (to include lab, XR, notes, etc.) from (dates): to.
Check Laboratory results from (dates): to, or X-ray films/Diagnostic Images from (dates): to, and enter the dates.
Check Pharmacy Profile Billing: Equivalent Value Statement (EVS) or Co-Pay Statement, or check Other (Please specify):.
The information released may contain other sensitive information, such as information regarding communicable diseases (including sexually transmitted diseases and HIV/A IDS, as defined in A.R.S. Sections 36-661, 36-664), genetic testing/genetic history (as defined in A.R.S. Section 12-2801), mental/behavioral health, substance use disorders/treatment (as defined in 42 CFR section 2.1) and developmental disabilities. The consent includes disclosure of other sensitive health information in connection with the release of the health information unless you have provided specific instructions in the Specific Instructions space.
Psychotherapy records

PSYCHOTHERAPY RECORDS (Optional): to include Confidential Psychotherapy Notes (as defined in 45 CFR Section 164.501), for example notes of private counseling sessions, check Copies of therapy records from (dates): to.
Format / manner of release
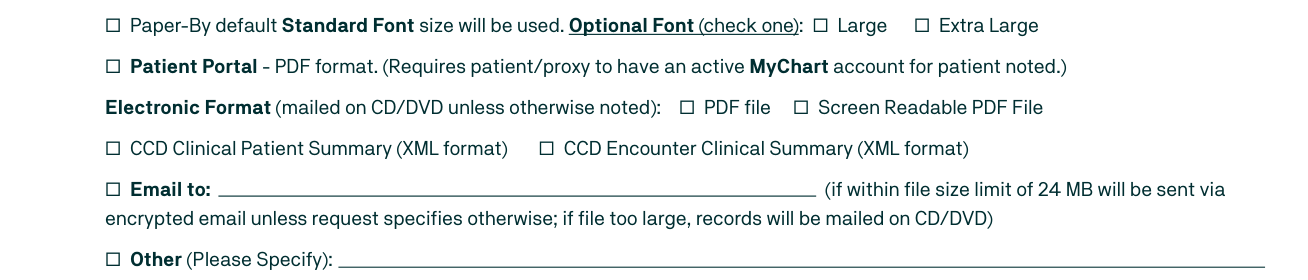
Under FORMAT / MANNER OF RELEASE, check Paper (by default Standard Font size will be used), or check one Optional Font: Large or Extra Large.
Check Patient Portal - PDF format. This requires the patient/proxy to have an active MyChart account for the patient noted.
Under Electronic Format (mailed on CD/DVD unless otherwise noted), check PDF file, Screen Readable PDF File, CCD Clinical Patient Summary (XML format) or CCD Encounter Clinical Summary (XML format).
Check Email to: if within file size limit of 24 MB the records will be sent via encrypted email unless the request specifies otherwise; if file too large, records will be mailed on CD/DVD.
Check Other (Please Specify):.
Signatures

Under SIGNATURES, enter the Print Name.
Enter the Relationship if not signed by the Patient (or description of authority to act for Patient).
Note that if not already provided, the group will require verification of the authority of a Personal Representative before this request will be considered complete including furnishing a copy of a valid healthcare power or attorney, Personal Representative Form or other relevant documents.
EXPIRATION: This consent will expire 1 year after the signed date under SIGNATURES.
If this request is made by a Parent/Guardian

If this request is made by a Parent/Guardian, complete the following: enter the minor's years of age (Patient is a minor years of age). The minor signs on the Minor's signature line and enters the Date.
If minor patient is 12 years or older, the group will require authorization from the minor prior to release of sensitive information or a valid Personal Representative form completed by the minor for parent/guardian on file; otherwise, records will be reviewed and redacted.
Certain information concerning a minor is governed by Arizona State and Federal law and will require the minor patient's signature prior to any release.
Witnesses

Telephonic/Verbal: Form ID verified, reviewed in full and documented per patient/representative's request. This requires sign-off by 2 Evernorth Care Group employees who witnessed the authorization.
Each witness enters the Witness (Print name), signs on the Witness signature line and enters the Date.
The 2nd Witness prints the name, signs and dates in the same way.
More rules for Cigna Form SP1813
If the information on this form is not fully completed, the group will return the form to you and this request will not be considered until the group receives all required information.
You may not be entitled to receive all of your PHI, including information such as psychotherapy notes (as defined in 45 CFR 164.501) or information compiled in reasonable anticipation of, or use in, a civil, criminal or administrative action or proceeding.
You release Evernorth Care Group, its physicians and employees from any and all liability for fulfilling this authorization request for the release of your medical information. You have given your consent freely, voluntarily and without coercion.
You may revoke this authorization at any time provided that you notify the group in writing to that effect. Any releases made prior to your revocation and in compliance with this authorization shall not constitute a breach of your rights to confidentiality.
A photocopy/fax of this authorization is considered acceptable in lieu of the original.
Sources
[1] Evernorth Care Group Authorization notification to release protected health information, Form SP1813 (rev. 06/2024) (the Official source link on this page).