

Form CMS-1490S at a glance
What it is: The Patient's Request for Medical Payment is the form that you complete when you submit your own claim to Medicare.
Where and when to file: Send only the completed form to your Medicare Administrative Contractor. Include a copy of the itemized bill and any supporting documents. Make a copy of your claim submission for your records and allow at least 60 days for Medicare to receive and process your request.
For Part B Services, in most situations your physician, other practitioner or supplier will submit your claim to Medicare; if they do not, you can submit a claim.
For Durable Medical Equipment, Prosthetics, Orthotics and Supplies, in most situations your supplier of DMEPOS will submit your claim to Medicare; if they do not, you can submit a claim for an item or services furnished by your supplier.
Physicians and other suppliers, such as clinical laboratories, imaging service suppliers, and durable medical equipment suppliers are required by law to submit a claim for Medicare covered services furnished to you, the Medicare beneficiary, within one year of the date of service.
What to bring and attach to Form CMS-1490S
Attach all supporting documentation to the form including an itemized bill with the following information: Date of service, Place of service, Description of illness or injury, Description of each surgical or medical service or supply furnished, Charge for each service, The doctor's or supplier's name and address, The provider or supplier's National Provider Identifier (NPI) If known.
You must attach an itemized bill in order for Medicare to process this claim.
If the itemized bill is from: A Clinical laboratory for ordered tests, An independent diagnostic imaging center for ordered imaging procedures, A supplier of Durable Medical Equipment, Prosthetics, Orthotics and Supplies (DMEPOS) for ordered DMEPOS, the ordering & referring providers legal name MUST be included on the itemized bill. Please also include the ordering & referring providers National Provider Identifier (NPI) if known.
Attach a copy of your primary insurer's Explanation of Benefits notice if you are requesting Medicare Secondary payment.
Shipboard services please include a copy of the ship's itinerary.
A filled-in Form CMS-1490S example: a patient files her own claim

How to fill out Form CMS-1490S, box by box
Your reason for submitting this claim

Your reason for submitting this claim, check one box only: The provider or supplier refused to file a claim for Medicare Covered Services, the provider or supplier is unable to file a claim for the Medicare Covered Services, or the provider or supplier is not enrolled with Medicare.
Type of Patient's Request

Type of Patient's Request, check one box only: Influenza/Pneumococcal Vaccination, Part B (includes physician, laboratory, imaging services), Foreign Travel (including Canada and Mexico) and/or Shipboard Services, or Durable Medical Equipment, Prosthetics, Orthotics and Supplies.
Patient information
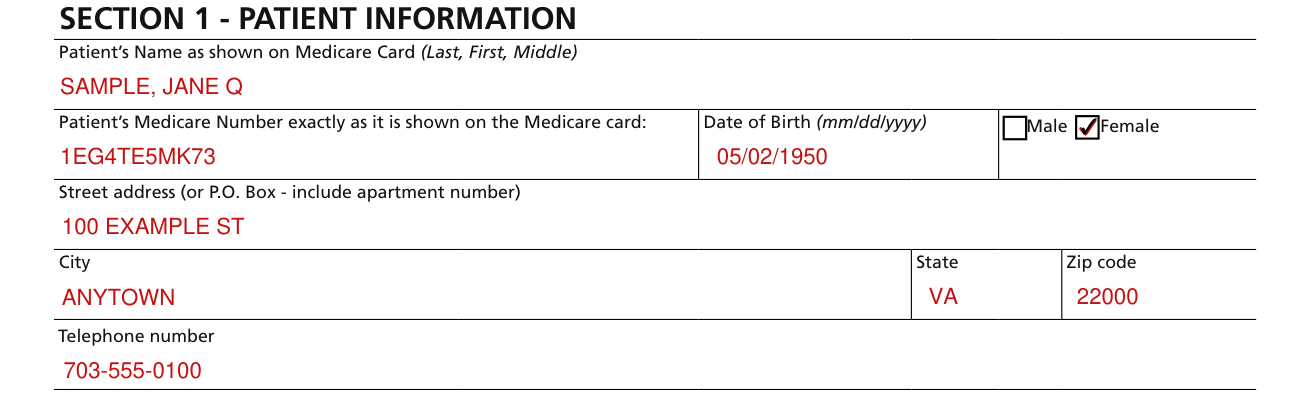
Print your name as shown on your Medicare card (Last Name, First Name, Middle Name). Print your Medicare Number exactly as it is shown on the Medicare card. Print your date of birth (mm/dd/yyyy).
Check the appropriate box for the patient's sex. Furnish your mailing address and include your telephone number.
Describe the illness or injury

For all claims including Influenza and Pneumococcal Vaccinations, describe the illness or injury for which you received treatment.
Was the condition related to

Was the condition related to: Employment, Auto Accident, Treatment for chronic dialysis or kidney transplant, Other Accident? Check the appropriate boxes.
If you are being treated for a work related injury be sure to check the appropriate box in Section 2 titled 'Condition Related to'.
Health insurance other than Medicare
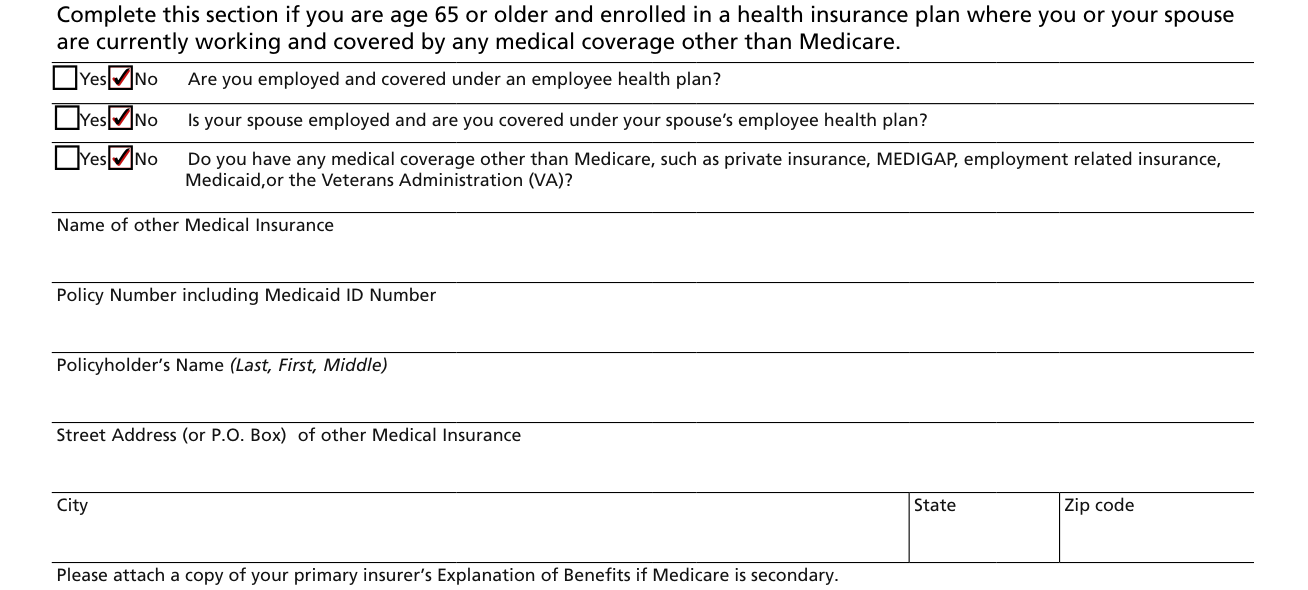
Complete this section if you are age 65 or older and enrolled in a health insurance plan where you or your spouse are currently working and covered by any medical coverage other than Medicare.
Yes or No: Are you employed and covered under an employee health plan? Yes or No: Is your spouse employed and are you covered under your spouse's employee health plan? Yes or No: Do you have any medical coverage other than Medicare, such as private insurance, MEDIGAP, employment related insurance, Medicaid, or the Veterans Administration (VA)?
Name of other Medical Insurance, Policy Number including Medicaid ID Number, Policyholder's Name (Last, First, Middle), Street Address (or P.O. Box) of other Medical Insurance, City, State, Zip code.
Signature

Section 4 - SIGNATURE: Sign your name and date the form. If the Medicare beneficiary is not able to sign his/her name, follow the instructions on the form.
If you cannot sign your name
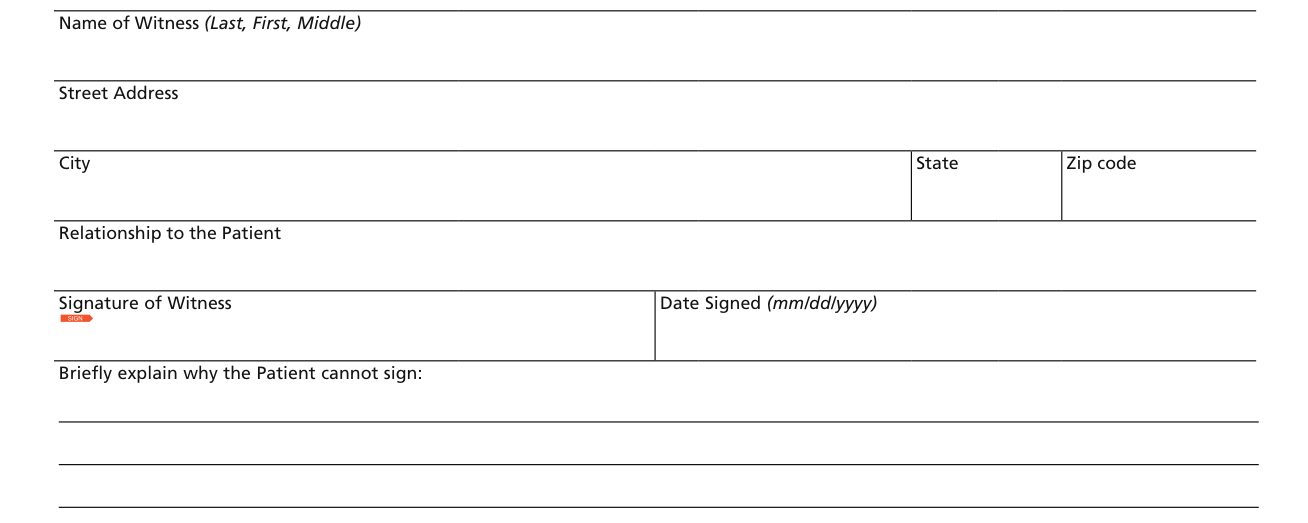
If you cannot sign your name, mark an (X) on the signature line. Have a witness sign his/her name next to the “X” and complete the witness section.
If signing this form on behalf of a Medicare patient, on the ‘Signature of Patient' line, indicate the patient's name followed by “By” and sign your name. Provide your name, address, and relationship to the patient with a brief explanation why the patient cannot sign.
More rules for Form CMS-1490S
If the claim form has incomplete or invalid information, the Medicare contractor will return the claim along with a letter to you clearly stating what information is missing or invalid.
Many times a bill will show the names of several doctors or suppliers. It is very important the provider who treated you be identified. Simply circle his/her name on the bill.
Mark out any services on the itemized bill(s) you are attaching for which you have already filed a Medicare claim.
If your situation is different
Foreign Travel (including Canada and Mexico)
Medicare law prohibits payment for health care services furnished outside the United States (U.S.) except in certain limited circumstances.
Influenza/Pneumococcal Vaccination
For Influenza/Pneumococcal Vaccination: Annual Part B deductible and coinsurance amounts do not apply. Medicare does not pay for the hepatitis B vaccines.
If the Patient is deceased
If the Patient is deceased, please contact your Social Security office for instructions on how to file a claim.
Common questions about Form CMS-1490S
Where do I file it?
Send the completed form and supporting documentation to your Medicare contractor. Reference the Medicare Administrative Contractor Address table for the correct address to mail your claim form. If you still do not know the address of your Medicare contractor, call 1-800-MEDICARE (1-800-633-4227). TTY users should call 1-877-486-2048.
Is there a penalty?
Anyone who misrepresents or falsifies essential information requested by this form may upon conviction be subject to fine and imprisonment under Federal law.
What am I certifying when I sign?
“I declare under penalty of perjury that I have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of my knowledge.”
When is this form not the right one?
Medicare will not process a beneficiary request for payment for diabetic test strips, Part B drugs, or for items paid for under the DMEPOS Competitive Bidding program.
Sources
[1] Form CMS-1490S (version 01/18), Patient's Request for Medical Payment, Centers for Medicare & Medicaid Services (the Official source link on this page).
