

Form CMS-485 at a glance
What it is: Form CMS-485 (12-14), OMB No. 0938-0357, is the Home Health Certification and Plan of Care; the primary use of this information is to process and pay Medicare benefits to or on behalf of eligible individuals.
Who signs: Box 27 is the Attending Physician's Signature and Date Signed.
A filled-in Form CMS-485 example: a nurse completes a plan of care

How to fill out Form CMS-485, box by box
Patient's HI Claim No., Start Of Care Date and Certification Period

Enter the Patient's HI Claim No. in box 1, the Start Of Care Date in box 2 and the Certification Period From and To in box 3 (Form Approved OMB No. 0938-0357).
Enter the Medical Record No. in box 4 and the Provider No. in box 5.
Patient's Name and Address and Provider's Name, Address and Telephone Number
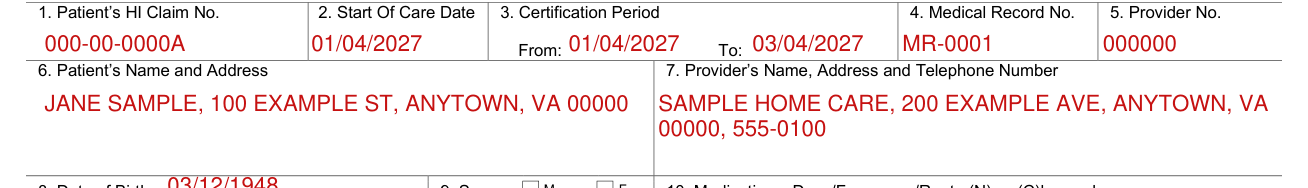
Enter the Patient's Name and Address in box 6.
Enter the Provider's Name, Address and Telephone Number in box 7.
Date of Birth, Sex and Medications
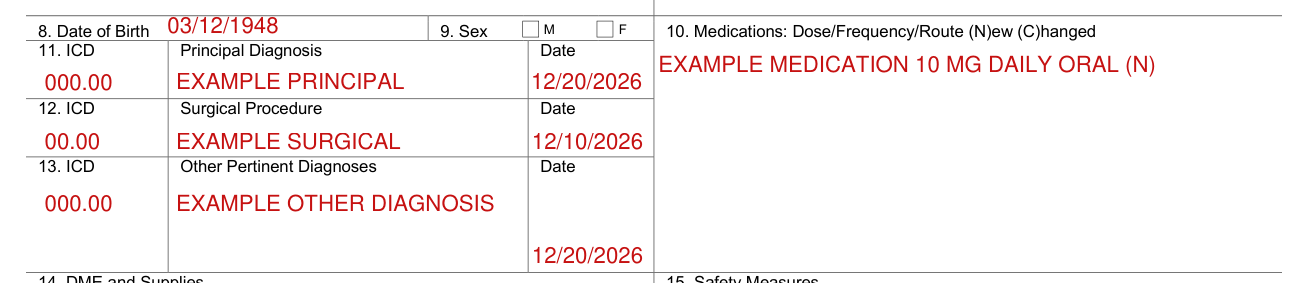
Enter the Date of Birth in box 8 and the Sex, M or F, in box 9.
Box 10, Medications, is for Dose/Frequency/Route, with (N)ew or (C)hanged.
ICD Principal Diagnosis, Surgical Procedure and Other Pertinent Diagnoses
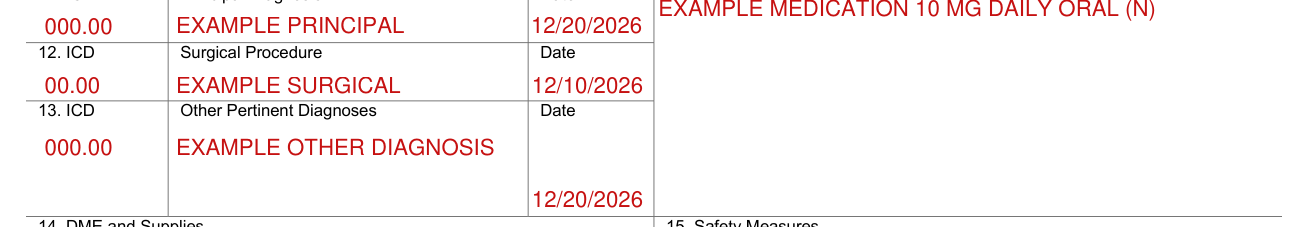
Box 11 is the ICD Principal Diagnosis, with its Date.
Box 12 is the ICD Surgical Procedure, with its Date.
Box 13 is the ICD Other Pertinent Diagnoses, with its Date.
DME and Supplies, Safety Measures, Nutritional Req. and Allergies

Box 14 is DME and Supplies.
Box 15 is Safety Measures.
Box 16 is Nutritional Req., box 17 is Allergies, box 18.A is Functional Limitations and box 18.B is Activities Permitted.
Functional Limitations, Activities Permitted, Mental Status and Prognosis
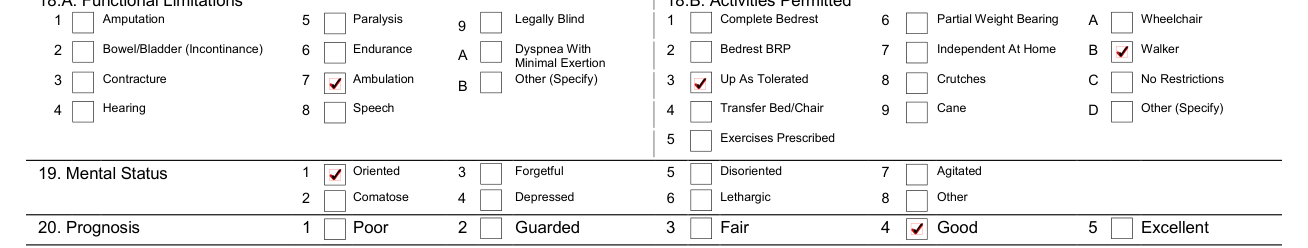
Box 18.A Functional Limitations: 1 Amputation, 2 Bowel/Bladder (Incontinance), 3 Contracture, 4 Hearing, 5 Paralysis, 6 Endurance, 7 Ambulation, 8 Speech, 9 Legally Blind, A Dyspnea With Minimal Exertion and B Other (Specify).
Box 18.B Activities Permitted: 1 Complete Bedrest, 2 Bedrest BRP, 3 Up As Tolerated, 4 Transfer Bed/Chair, 5 Exercises Prescribed, 6 Partial Weight Bearing, 7 Independent At Home, 8 Crutches, 9 Cane, A Wheelchair, B Walker, C No Restrictions and D Other (Specify).
Box 19 Mental Status: 1 Oriented, 2 Comatose, 3 Forgetful, 4 Depressed, 5 Disoriented, 6 Lethargic, 7 Agitated and 8 Other.
Box 20 Prognosis: 1 Poor, 2 Guarded, 3 Fair, 4 Good and 5 Excellent.
Orders for Discipline and Treatments and Goals

Enter the Orders for Discipline and Treatments (Specify Amount/Frequency/Duration) in box 21 and the Goals/Rehabilitation Potential/Discharge Plans in box 22.
Signatures, Physician and Date of HHA Received Signed POT

Box 23 is the Nurse's Signature and Date of Verbal SOC Where Applicable.
Enter the Physician's Name and Address in box 24.
Enter the Date of HHA Received Signed POT in box 25.
By signing you certify that this patient is confined to his/her home and needs intermittent skilled nursing care, physical therapy and/or speech therapy or continues to need occupational therapy, and the Attending Physician's Signature and Date Signed go in box 27.
Box 27 is the Attending Physician's Signature and Date Signed.
More rules for Form CMS-485
The time required to complete this information collection is estimated to average 15 minutes per response, including the time to review instructions, search existing data resources, gather the data needed, and complete and review the information collection.
Common questions about Form CMS-485
What is a 485 form in home health?
Form CMS-485 (12-14), OMB No. 0938-0357, is the Home Health Certification and Plan of Care; the primary use of this information is to process and pay Medicare benefits to or on behalf of eligible individuals. Furnishing the information on this form, including the SSN, is voluntary, but failure to do so may result in disapproval of the request for payment of Medicare benefits.
Is there a penalty?
Anyone who misrepresents, falsifies, or conceals essential information required for payment of Federal funds may be subject to fine, imprisonment, or civil penalty under applicable Federal laws.
Sources
[1] Form CMS-485 (12-14), Home Health Certification and Plan of Care, Centers for Medicare & Medicaid Services (the Official source link on this page).
