


Form CMS-588 at a glance
What it is: Form CMS-588, the ELECTRONIC FUNDS TRANSFER (EFT) AUTHORIZATION AGREEMENT, is for the purpose of authorizing electronic funds transfers.
Who signs: The EFT authorization form must be signed and dated by the same Authorized Representative or a Delegated Official named on the CMS-855 Medicare enrollment application which the Medicare contractor has on file.
Per 42 CFR 424.510(e)(1), providers and suppliers are required to receive electronic funds transfer (EFT) at the time of enrollment, revalidation, change of Medicare contractors or submission of an enrollment change request; and (2) submit the CMS-588 form to receive Medicare payment via electronic funds transfer.
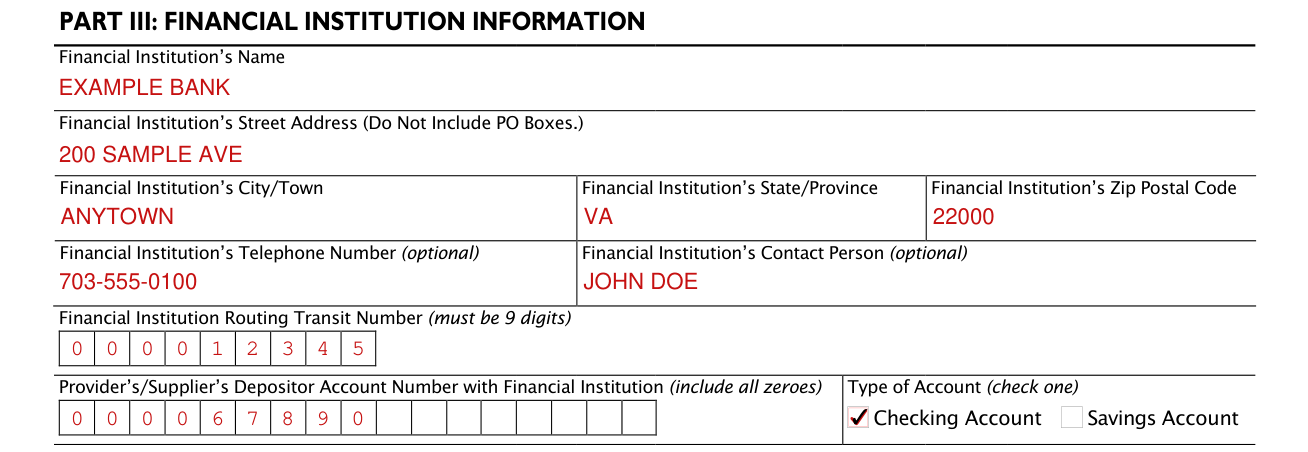
A filled-in Form CMS-588 example: a physician enrolls for direct deposit

How to fill out Form CMS-588, box by box
Reason for Submission

Indicate your reason for completing this form by checking the appropriate box: New EFT enrollment or change to your EFT enrollment account information.
If you are authorizing EFT payments to the home office of a chain organization of which you are a member, you must attach a letter authorizing the contractor to make payment due the provider of service to the account maintained by the home office of the chain organization. The letter must be signed by an authorized official of the provider of service and an authorized official of the chain home office.
NOTE: If you have had either a change of ownership or change of practice location, you must submit a change of information (using the Medicare enrollment application) to the Medicare contractor that services your geographical area(s) prior to or accompanying this EFT authorization agreement submission.
Account holder information
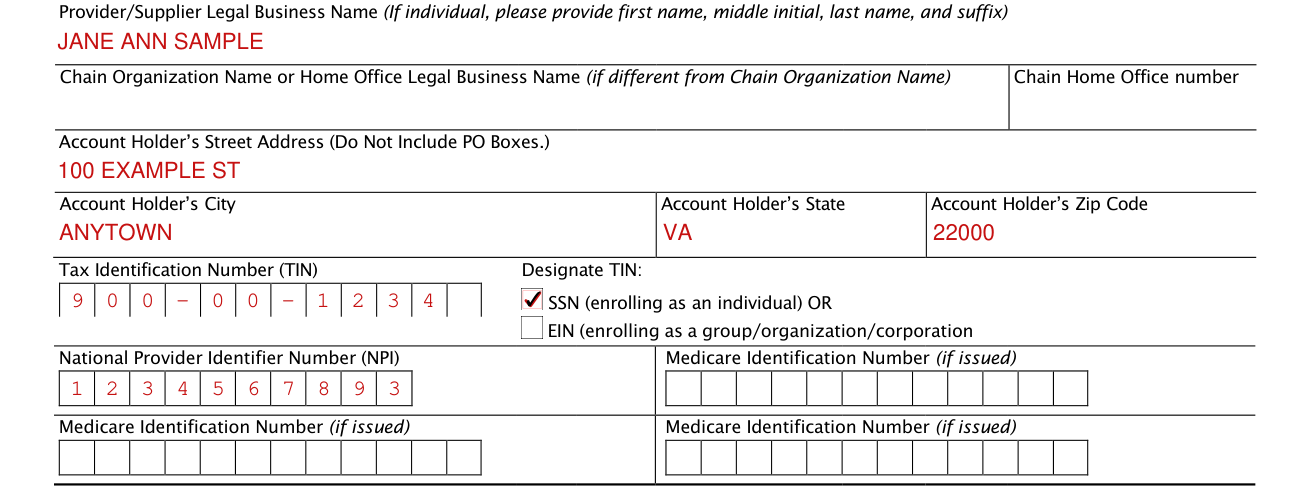
Enter the provider's/supplier's legal business name or the name of the physician or individual practitioner, as reported to the Internal Revenue Service (IRS). The account to which EFT payments made must bear the name of the physician or individual practitioner, or the legal business name of the person or entity enrolled with Medicare.
NOTE: Providers/suppliers must report the legal business name provided on the IRS CP-575 form.
Enter the Chain Home Office (CHO) legal business name. A CHO is an entity that provides centralized management and administrative services to the providers or suppliers under common ownership and common control, such as centralized accounting, purchasing, personnel services, management direction and control, and other similar services.
Enter the account holder's street address. NOTE: Do Not Include PO Boxes.
Enter the account holder's city, state, and zip code.
Enter the tax identification number as reported to the IRS. If the business is a group, organization or corporation, provide the Federal employer identification number. If enrolling as an individual provide your Social Security Number.
Enter the 10 digit NPI number. The NPI is required to process this form.
A provider/supplier may only have one EFT account per enrollment.
If issued, enter the Medicare identification number assigned by a Medicare Administrative Contractor (MAC). If you are not enrolled in Medicare, leave this field blank. If more than one Medicare identification number is attached to this NPI, include the Medicare identification numbers on this form. NOTE: Institutional providers enter only ONE Medicare Identification Number (if issued).
Financial institution information
Please include a confirmation of account information on bank letterhead or a voided check. When submitting the documentation, it should contain the name on the account, electronic routing transit number, account number and type.
If submitting bank letterhead, the bank officer's name and signature is also required.
NOTE: Supporting bank documents must be in the provider's/supplier's/entity's legal business name only.
NOTE: Starter checks are not acceptable for EFT confirmations.
Enter your Financial Institution's name (this is the name of the bank or qualifying depository that will receive the funds).
NOTE: The Financial Institution's name must be the Legal Business Name on the account, electronic routing transit number and type.
NOTE: The account name to which EFT payments will be paid is to the name submitted on Part II of this form.
Enter the financial institution's street address. NOTE: Do Not Include PO Boxes.
Enter the financial institution's city or town, state or province, and zip/postal code.
Enter the bank or financial institutional telephone number and contact person's name.
Enter the bank or financial institutional nine-digit routing number, including applicable leading zeros.
Enter the provider's/supplier's account number with the financial institution, including applicable leading zeros. Select the account type.
Contact person
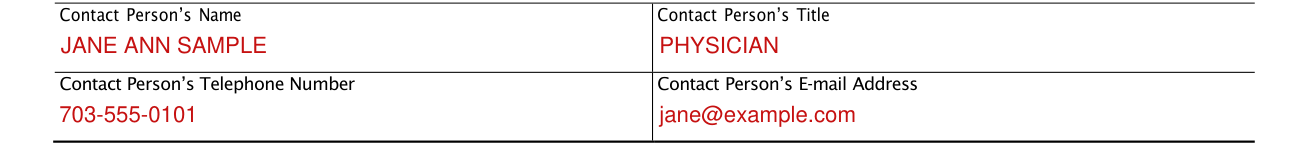
Enter the name and title of a contact person who can answer questions about the information submitted on this CMS-588 form.
Enter the contact person's telephone number. Enter the contact person's e-mail address.
Authorization

Authorized/Delegated Official Signature (Note: Must be signed and dated to process.)
By your signature on this form you are certifying that the account is drawn in the Name of the Physician or Individual Practitioner, or the Legal Business Name of the person or entity.
Include a telephone number where the Authorized Representative or Delegated Official can be contacted.
You must notify CMS regarding any changes in the account in sufficient time to allow the contractor and the Financial Institution to act on the changes.
If my Financial Institution information changes, I agree to submit to CMS an updated EFT Authorization Agreement.
More rules for Form CMS-588
All EFT requests are subject to a pre-certification period in which all accounts are verified by the qualifying financial institution before any Medicare direct deposits are made.
PLEASE NOTE: In accordance with section 1104 of the Affordable Care Act, enrollment of electronic fund transfer (EFT) is for electronic fund transfer authorization only. EFT enrollment does not constitute enrollment as a provider or supplier in the Medicare program.
An EFT authorization form must be submitted for each Medicare contractor to whom you submit claims for Medicare payment.
Common questions about Form CMS-588
Where do I file it?
Upload this form to PECOS or mail this form to the Medicare contractor that services your geographical area.
When is this form not the right one?
Physicians and individual practitioners who have granted a Medicare-enrolled provider or supplier the right to receive payments for all of their services, is not required to complete this form.
Sources
[1] Form CMS-588 (Rev: 11/2023), Electronic Funds Transfer (EFT) Authorization Agreement, Centers for Medicare & Medicaid Services (the Official source link on this page).