

DH-MQA 5022 at a glance
What it is: DH-MQA 5022 is the Certified Nursing Assistant Licensure by Endorsement Application of the Board of Nursing.
Who signs: I, the undersigned, state that I am the person referred to in this application for licensure in the state of Florida.
What to bring and attach to DH-MQA 5022
Take the Board of Nursing Electronic Fingerprinting form with you to the Livescan service provider. Check the service provider's requirements to see if you need to bring any additional items.
A filled-in DH-MQA 5022 example: a CNA licensed in Ohio applies by endorsement
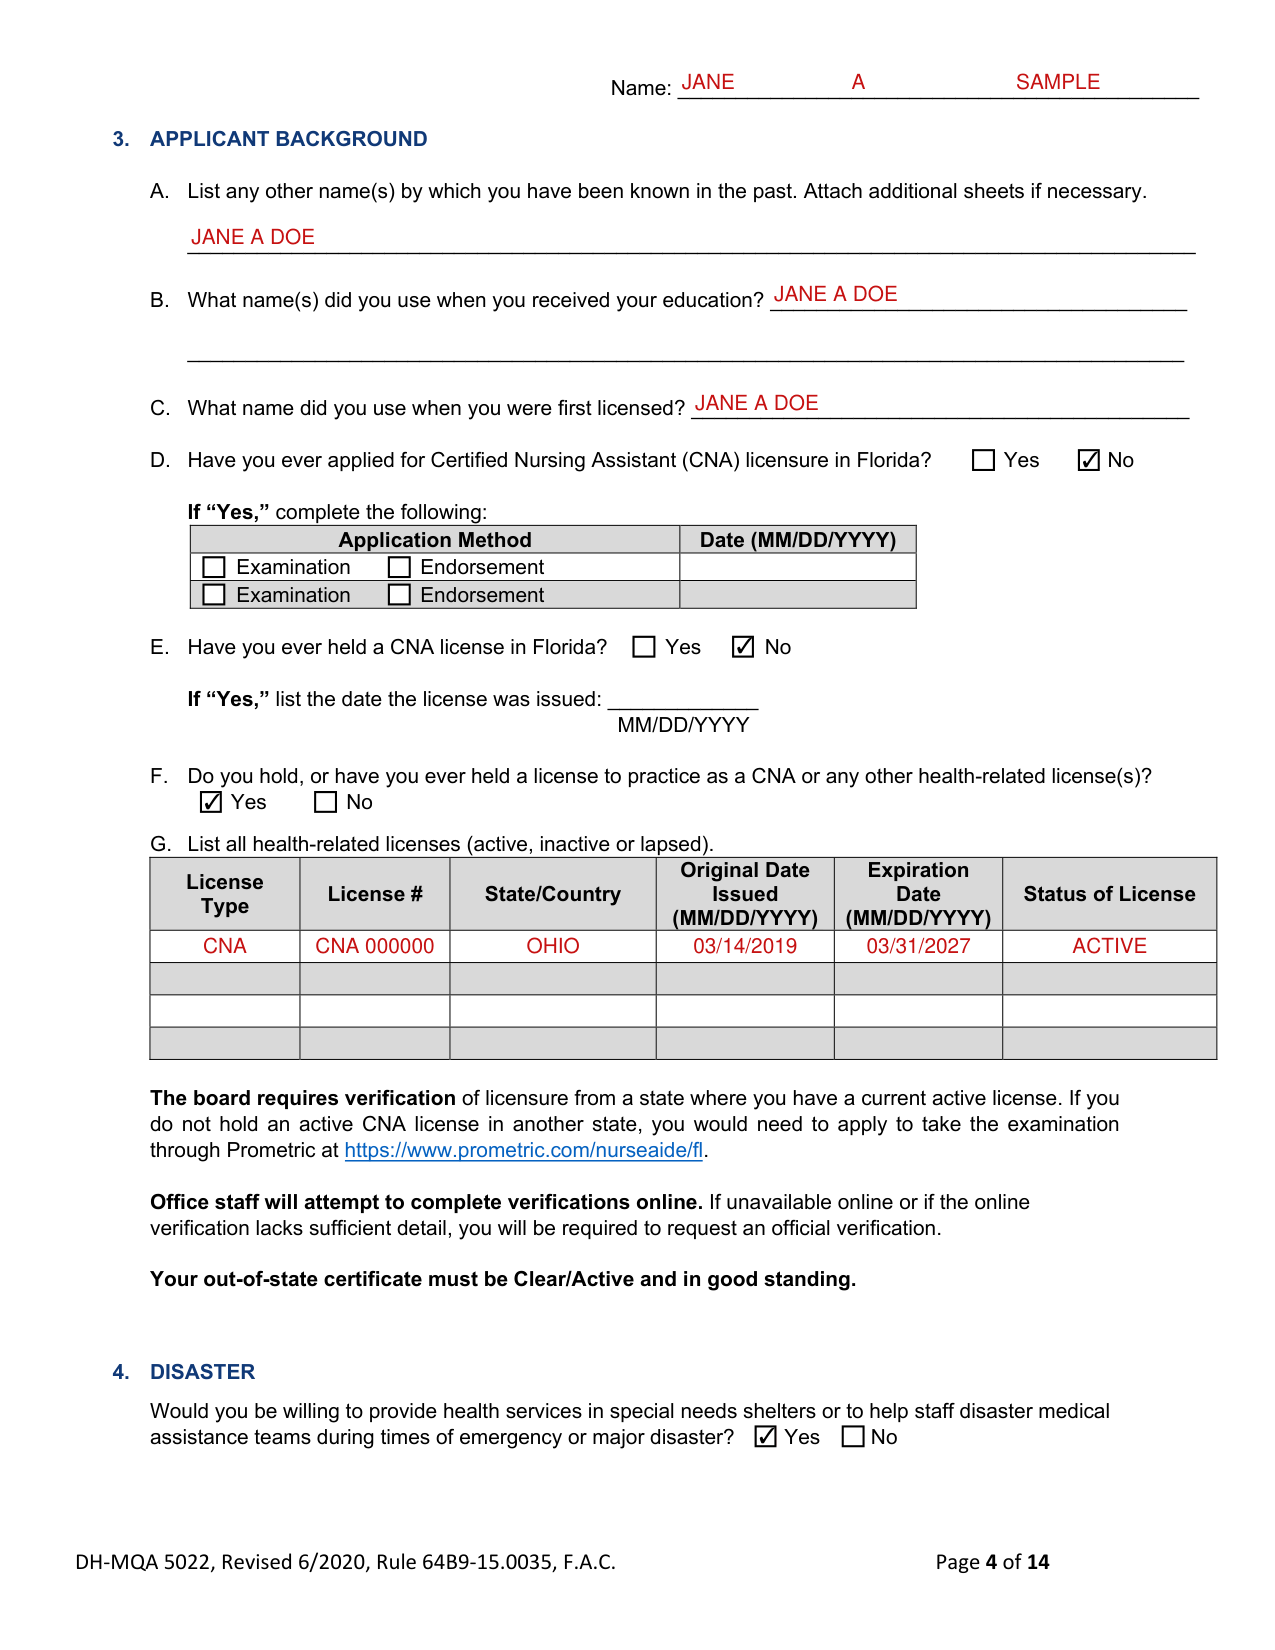
How to fill out DH-MQA 5022, box by box
Personal information
Enter the Name as Last/Surname, First and Middle, the Date of Birth as MM/DD/YYYY, and the mailing address as Street/P.O. Box, Apt. No., City, State, ZIP and Country. Input the Home/Cell Telephone and the Work/Cell Telephone without dashes. Physical Location is required if mailing address is a P.O. Box.
Email Notification
To be notified of the status of your application by email check the “Yes” box and fill in your email address on the line provided.
If you do not want your email address released in response to a public records request, do not provide an email address or send electronic mail to the office. Instead contact the office by phone or in writing.
Names you have been known by

List any other name(s) by which you have been known in the past. Attach additional sheets if necessary.
B: What name(s) did you use when you received your education?
C: What name did you use when you were first licensed?
Applications and license in Florida (D and E)
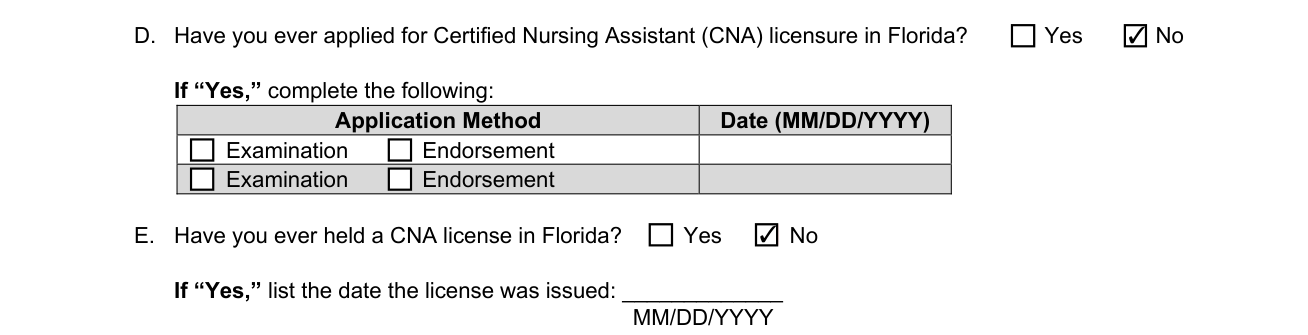
Mark Yes or No to D: have you ever applied for Certified Nursing Assistant (CNA) licensure in Florida?
If “Yes” to D, complete the following: Application Method, Examination or Endorsement, and Date (MM/DD/YYYY).
Mark Yes or No to E: have you ever held a CNA license in Florida?
If “Yes” to E, list the date the license was issued: MM/DD/YYYY.
Health-related licenses (F and G)
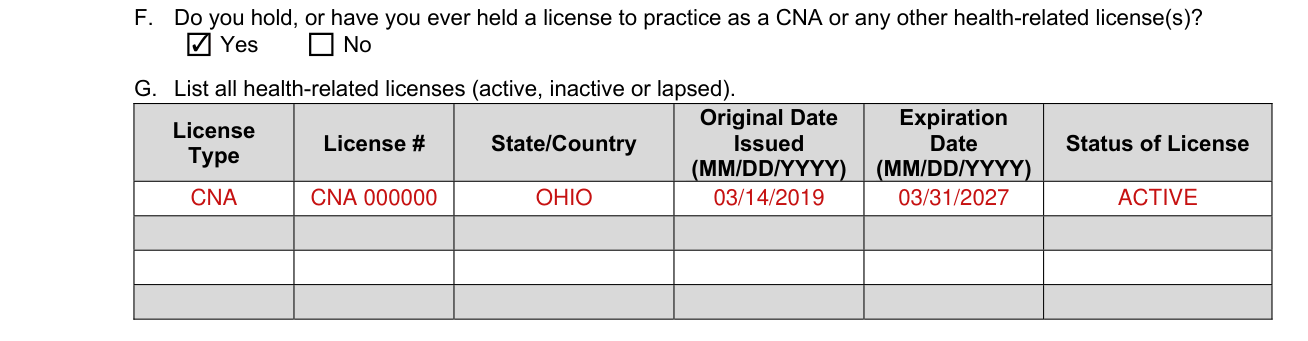
Mark Yes or No to F: do you hold, or have you ever held a license to practice as a CNA or any other health-related license(s)?
For G, list all health-related licenses (active, inactive or lapsed).
For each license enter the License Type, License #, State/Country, Original Date Issued (MM/DD/YYYY), Expiration Date (MM/DD/YYYY) and Status of License.
Your out-of-state certificate must be Clear/Active and in good standing.
If you do not hold an active CNA license in another state, you would need to apply to take the examination through Prometric at https://www.prometric.com/nurseaide/fl.
Disaster

Mark Yes or No: would you be willing to provide health services in special needs shelters or to help staff disaster medical assistance teams during times of emergency or major disaster?
Health history
If a “Yes” response was provided to any of the questions in this section, provide the following documents directly to the board office: A letter from a Licensed Health Care Practitioner, who is qualified by skill and training to address the condition identified, which explains the impact the condition may have on the ability to practice the profession with reasonable skill and safety.
The letter must specify that the applicant is safe to practice the profession without restrictions or specifically indicate the restrictions that are necessary.
Documentation provided must be dated within one year of the application date.
A written self-explanation, identifying the medical condition(s) or occurrence(s); and current status.
A: During the last two years, have you been treated for or had a recurrence of a diagnosed physical or mental disorder that impaired or would impair your ability to practice? Yes No
C: During the last five years, have you been treated for or had a recurrence of a diagnosed substance-related (alcohol or drug) disorder that impaired or would impair your ability to practice? Yes No
Discipline history
If you responded “Yes” to questions in this section, you must provide a written self-explanation, describing in detail the circumstances surrounding the disciplinary action.
A copy of the Administrative Complaint and Final Order.
Three current (written in the last year) professional Letters of Recommendation.
A: Have you ever been denied or is there now any proceeding to deny your application for any health care license to practice in Florida or any other state, jurisdiction, or country? Yes No
B: Have you ever had any disciplinary action taken against your license to practice any health care related profession by the licensing authority in Florida or in any other state, jurisdiction, or country? Yes No
C: Have you ever surrendered a license to practice any health care related profession in Florida or any other state, jurisdiction, or country while any such disciplinary charges were pending against you? Yes No
If you responded “Yes” to questions in this section, complete Name of Agency, State, Action Date (MM/DD/YYYY), Final Action and Under Appeal?
Criminal history
If you responded “Yes,” you must provide a Self-Explanation, describing in detail the circumstances surrounding each offense; including date, city and state, charges and final results.
Final Dispositions and Arrest Records for all offenses.
Completion of Sentence Documents. The report must include the start date, end date, and that the conditions were met.
Three current (written within the last year) professional Letters of Recommendation.
A: Have you ever been convicted of, or entered a plea of guilty, nolo contendere, or no contest to any crime in any jurisdiction other than a minor traffic offense? You must include all misdemeanors and felonies, even if adjudication was withheld.
Reckless driving, driving while license suspended or revoked (DWSLR), driving under the influence (DUI) or driving while impaired (DWI) are not minor traffic offenses for purposes of this question.
B: Have you ever had any records sealed pursuant to s. 943.059, F.S., or other state's applicable statute? Yes No
C: Have you ever been adjudicated delinquent? Yes No
If you responded “Yes” in this section, complete Offense, Jurisdiction, Date (MM/DD/YYYY), Final Disposition and Under Appeal?
Criminal and Medicaid/Medicare fraud questions
1: Have you been convicted of, or entered a plea of guilty or nolo contendere, regardless of adjudication, to a felony under chapter (ch.) 409, F.S., ch. 817, F.S., ch. 893, F.S. or a similar felony offense(s) in another state or jurisdiction? Yes No
2: Have you been convicted of, or entered a plea of guilty or nolo contendere to, regardless of adjudication, to a felony under 21 U.S.C. ss. 801-970 or 42 U.S.C. ss. 1395-1396? Yes No
Question 5 and the documents
5: Are you currently listed on the United States Department of Health and Human Services' Office of the Inspector General's List of Excluded Individuals and Entities (LEIE)? Yes No
If you responded “Yes” to any of the questions in this section, you must provide a written explanation for each question including the county and state of each termination or conviction, date of each termination or conviction, and copies of supporting documentation.
Supporting documentation including court dispositions or agency orders where applicable.
Documentation for sections 5 and 6 (Health history and Discipline history) must be sent to the board office at MQA.Nursing@flhealth.gov or mailed to: Board of Nursing 4052 Bald Cypress Way Bin C-02 Tallahassee, FL 32399-3252.
Documentation for section 7 and 8 (Criminal history, and Criminal and Medicaid/Medicare fraud questions) must be sent to the Background Screening Unit at MQA.BackgroundScreen@flhealth.gov or mailed to: Background Screening Unit Florida Department of Health 4052 Bald Cypress Way, Bin BSU-01 Tallahassee, FL 32399.
Livescan privacy statement and fingerprinting
I have been provided and read the statement from the Florida Department of Law Enforcement regarding the sharing, retention, privacy and right to challenge incorrect criminal history records and the “Privacy Statement” document from the Federal Bureau of Investigation (Found in the forms following this application).
The board will not receive your Livescan results if you do not confirm the statement by checking the box.
Electronic Fingerprinting: (Required for ALL applicants) All applicants, including out-of-state applicants, are required to submit their fingerprints electronically.
The board cannot accept hard fingerprint cards or results.
Applicant signature
Sign at Applicant Signature and enter the Date as MM/DD/YYYY. You may print this application and sign it or sign digitally.
I recognize that providing false information may result in disciplinary action against my license or criminal penalties pursuant to s. 456.067, 775.083, F.S.
Section 456.013(1)(a), F.S., provides that an incomplete application shall expire one year after the initial filing with the department.
More rules for DH-MQA 5022
Requests to withdraw must be made in writing.
The request must be received prior to the board considering licensure.
Sources
[1] DH-MQA 5022 (Revised 6/2020), Certified Nursing Assistant Licensure by Endorsement Application, Board of Nursing (the Official source link on this page).
