


Model COBRA Continuation Coverage Election Notice at a glance
What it is: The Model COBRA Continuation Coverage Election Notice is the Department of Labor's model Consolidated Omnibus Budget Reconciliation Act of 1985 (COBRA) election notice that a Plan may use.
Where and when to file: Send the completed Election Form to the Name and Address the Plan Administrator must fill in.
For use by single-employer group health plans.
To use this model election notice properly, the Plan Administrator must fill in the blanks with the appropriate plan information.
Federal law requires that most group health plans (including this Plan) give employees and their families the opportunity to continue their health care coverage through COBRA continuation coverage when there's a “qualifying event” that would result in a loss of coverage under an employer's plan.
A filled-in Model COBRA Continuation Coverage Election Notice example: an employee elects for himself

How to fill out Model COBRA Continuation Coverage Election Notice, box by box
Date of notice and the qualified beneficiaries

The Plan Administrator must enter the date of notice and, after Dear, identify the qualified beneficiary(ies), by name or status.
Why am I getting this notice?

The Plan Administrator must fill in the date your coverage under the Plan will end and check the appropriate box: End of employment, Reduction in hours of employment, Death of employee, Divorce or legal separation, Entitlement to Medicare, or Loss of dependent child status.
Who are the qualified beneficiaries?

The Plan Administrator checks the category or categories that apply. Each person (“qualified beneficiary”) in a category checked can elect COBRA continuation coverage. The categories are: Employee or former employee, Spouse or former spouse, Dependent child(ren) covered under the Plan on the day before the event that caused the loss of coverage, and Child who is losing coverage under the Plan because he or she is no longer a dependent under the Plan.
Completed Election Form and its due date
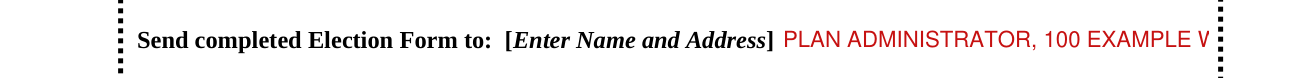
Under federal law, you have 60 days after the date of this notice to decide whether you want to elect COBRA continuation coverage under the Plan.
This Election Form must be completed and returned by mail, or by the other means of submission and due date the Plan Administrator describes. If mailed, it must be post-marked no later than the date the Plan Administrator must fill in.
If you don't submit a completed Election Form by the due date shown, you'll lose your right to elect COBRA continuation coverage.
If you reject COBRA continuation coverage before the due date, you may change your mind as long as you submit a completed Election Form before the due date. However, if you change your mind after first rejecting COBRA continuation coverage, your COBRA continuation coverage will begin on the date you submit the completed Election Form.
Who elects COBRA continuation coverage
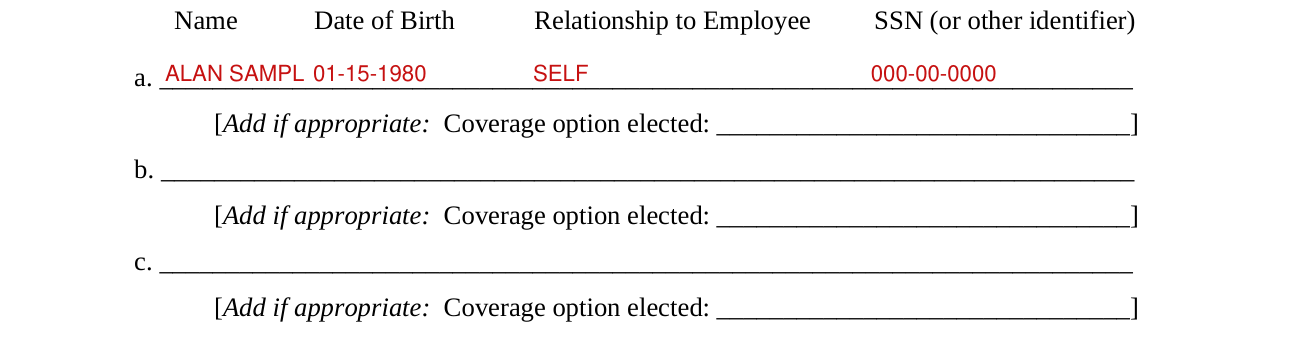
On lines a, b and c, enter the Name, Date of Birth, Relationship to Employee and SSN (or other identifier).
If the Plan lists coverage options, enter the Coverage option elected.
Signature, date and print name

Sign on the Signature line and enter the Date, then enter your Print Name, the Relationship to the individual(s) listed on lines a, b and c, your Print Address and your Telephone number.
Your first payment and all periodic payments should be sent to

The Plan Administrator must fill in the appropriate payment address to which your first payment and all periodic payments for continuation coverage should be sent.
More rules for Model COBRA Continuation Coverage Election Notice
The use of the model notices isn't required.
Plans do not need to include this instruction page with the model election notice.
If you have questions about the information in this notice, your rights to coverage, or if you want a copy of your summary plan description, contact the party responsible for COBRA administration for the Plan, with telephone number and address.
If your situation is different
If I elect COBRA continuation coverage, when will my coverage begin and how long will the coverage last?
The Plan Administrator must enter the date COBRA continuation coverage will begin and the date it can last until. If appropriate, the Plan may list the available coverage options you may elect.
Continuation coverage may end before the date noted in certain circumstances, like failure to pay premiums, fraud, or the individual becomes covered under another group health plan.
Can I extend the length of COBRA continuation coverage?
If you elect continuation coverage, you may be able to extend the length of continuation coverage if a qualified beneficiary is disabled, or if a second qualifying event occurs.
COBRA continuation coverage will cost
The Plan Administrator must fill in the amount each qualified beneficiary will be required to pay for each option per month of coverage and any other permitted coverage periods.
If you choose to elect continuation coverage, you don't have to send any payment with the Election Form.
When considering your options for health coverage, you may want to think about premiums: Your previous plan can charge up to 102% of total plan premiums for COBRA coverage.
When can I enroll in Marketplace coverage?
You always have 60 days from the time you lose your job-based coverage to enroll in the Marketplace. After 60 days your special enrollment period will end and you may not be able to enroll, so you should take action right away.
If you sign up for Marketplace coverage instead of COBRA continuation coverage, you cannot switch to COBRA continuation coverage once your election period ends.
Can I enroll in another group health plan?
You may be eligible to enroll in coverage under another group health plan (like a spouse's plan), if you request enrollment within 30 days of the loss of coverage.
Can I enroll in Medicare instead of COBRA continuation coverage after my group health plan coverage ends?
In general, if you don't enroll in Medicare Part A or B when you are first eligible because you are still employed, after the initial enrollment period for Medicare Part A or B, you have an 8-month special enrollment period 1 to sign up, beginning on the earlier of the month after your employment ends or the month after group health plan coverage based on current employment ends. If you don't enroll in Medicare Part B and elect COBRA continuation coverage instead, you may have to pay a Part B late enrollment penalty and you may have a gap in coverage if you decide you want Part B after that. If you elect COBRA continuation coverage and then enroll in Medicare Part A or B before the COBRA continuation coverage ends, the Plan may terminate your continuation coverage. However, if Medicare Part A or B is effective on or before the date of the COBRA election, COBRA coverage may not be discontinued on account of Medicare entitlement, even if you enroll in the other part of Medicare after the date of the election of COBRA coverage.
Important Information About Payment
You must make your first payment for continuation coverage no later than 45 days after the date of your election (this is the date the Election Notice is postmarked). If you don't make your first payment in full no later than 45 days after the date of your election, you'll lose all continuation coverage rights under the Plan.
You'll be given a grace period of 30 days after the first day of the coverage period, or a longer period if the Plan permits, to make each periodic payment. If you don't make a periodic payment before the end of the grace period for that coverage period, you'll lose all rights to continuation coverage under the Plan.
Sources
[1] Model COBRA Continuation Coverage Election Notice, U.S. Department of Labor, Employee Benefits Security Administration (the Official source link on this page).