
How to Fill Out Maryland Continuation Election Form

Maryland Continuation Election Form at a glance

What it is: Maryland Continuation Election Form: I wish to continue coverage under the Employee Benefit Plan, and this election is subject to the Plan.

What to bring and attach to Maryland Continuation Election Form

If YES, please attach a new application.

A filled-in Maryland Continuation Election Form example: a former employee elects health coverage

Maryland Continuation Election Form example filled out, example: a former employee elects health coverage
Jane Sample fills in the Maryland Continuation Election Form. Her employment ended, so she ticks Termination of Employment and picks Health for herself alone, and she leaves the part For Employer to complete empty. The picture leaves the YES and NO choice at the top unmarked, and none of its entries is real.

How to fill out Maryland Continuation Election Form, box by box

Effective date and first payment
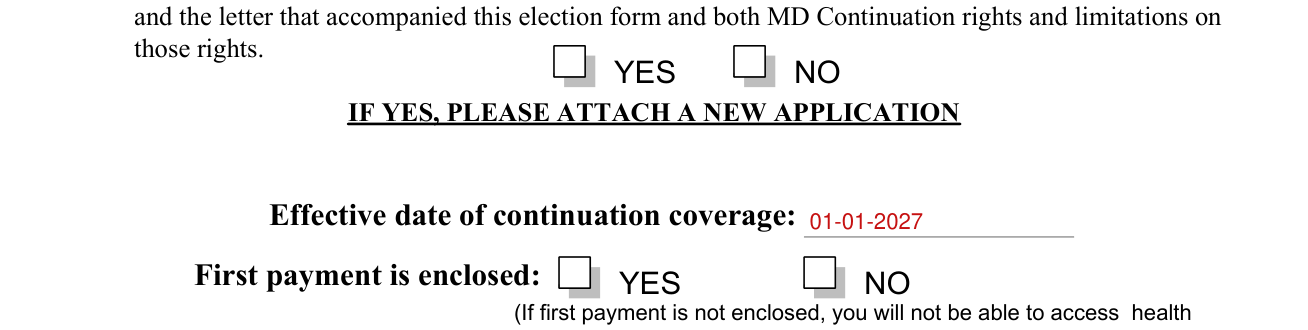
Maryland Continuation Election Form example filled out, effective date and first payment

Enter the Effective date of continuation coverage.

First payment is enclosed: If payment is not enclosed, you will not be able to access health care coverage until payment is received.

Qualifying Event
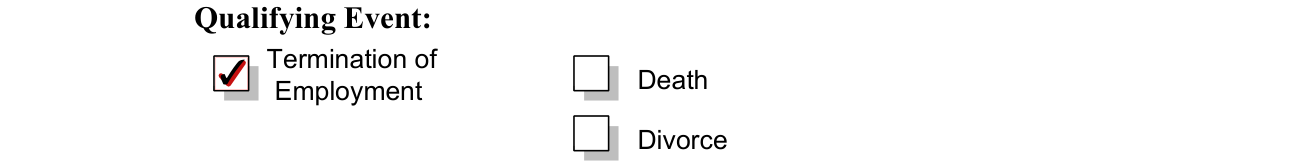
Maryland Continuation Election Form example filled out, qualifying Event

Qualifying Event: Death, Termination of Employment or Divorce.

Type of Insurance Selected

Maryland Continuation Election Form example filled out, type of Insurance Selected

Type of Insurance Selected: Health, Dental or Vision; you may not add lines of Insurance until Open Enrollment.

Type of Coverage Selected
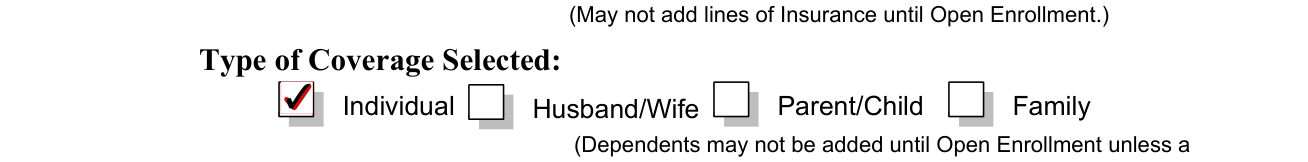
Maryland Continuation Election Form example filled out, type of Coverage Selected

Type of Coverage Selected: Individual, Husband/Wife, Parent/Child or Family; dependents may not be added until Open Enrollment unless a change in family status occurs.

Signature, Print Name and Social Security Number
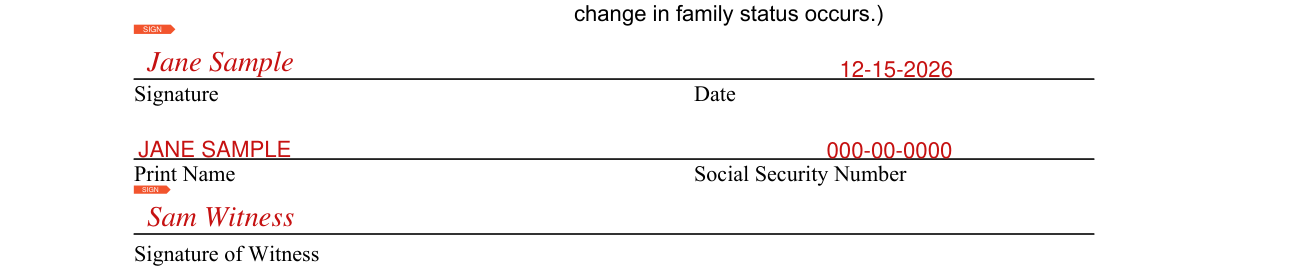
Maryland Continuation Election Form example filled out, signature, Print Name and Social Security Number

Sign, then enter the Date, your Print Name and your Social Security Number.

Have a witness sign on the Signature of Witness line.

For Employer to complete

Maryland Continuation Election Form example filled out, for Employer to complete

For Employer to complete: the Continuation coverage end date.

For Employer to complete: Bill to Company or Bill to Qualified Beneficiary, Billing address, City, State and Zip.

More rules for Maryland Continuation Election Form

I wish to continue coverage under the Employee Benefit Plan: YES or NO. If YES, please attach a new application.

Sources

[1] Maryland Continuation Election Form (the Official source link on this page).

Maryland Continuation Election Form PDF Details

In Maryland, individuals facing certain life events that result in the loss of employment-related health benefits have the option to continue their coverage through a process known as the Maryland Continuation Election. This crucial form serves as a lifeline, allowing employees and their families to maintain health, dental, and vision insurance during transitions. By completing the Maryland Continination Election Form, an individual signifies their intention to keep their coverage active under the specific plan provided by their employer. It's a declaration that necessitates a detailed understanding of one's rights and responsibilities, underscored by the requirement to have thoroughly reviewed the Maryland Continuation Coverage Notice and any accompanying documentation. The form encompasses several key decisions, including the type of insurance and coverage selected, which is especially important since changes, such as adding new lines of insurance or dependents, are restricted to periods of open enrollment or qualified family status changes. Aside from marking a choice to proceed with continuation coverage, the form captures essential details such as the effective date, whether the first payment has been made (a prerequisite for activating coverage), and the nature of the qualifying event leading to the loss of coverage, such as termination of employment, death, or divorce. All these elements are critical, not just for the individual electing to continue their benefits but also for employers who play a role in facilitating this continuation and need to be informed about billing directives. The process embodies a structured method to ensure that individuals do not find themselves without necessary health benefits during significant life changes, making understanding and correctly completing the Maryland Continuation Election Form paramount.

QuestionAnswer
Form NameMaryland Continuation Election Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesget the es 935 maryland form, maryland es 935, maryland es 935 unemployment, es 935 md