

Form 18 at a glance
What it is: Form 18, the North Carolina Industrial Commission Notice of Accident to Employer and Claim of Employee, Representative, or Dependent, gives notice that an employee sustained an injury or contracted an occupational disease.
Who signs: The employee, attorney, representative, or dependent signs.
Where and when to file: This form must be filed with the Industrial Commission within two years of the date of injury or occupational disease or your claim may be barred.
A Form 18 establishes a legal claim of injury on your behalf if filed within two years of the date of injury or occupational disease, and gives the required written notice to the employer if a copy is submitted to the employer within 30 days of the injury.
A filled-in Form 18 example: an employee reports a cut to the right hand

How to fill out Form 18, box by box
IC File #, Emp. Code # and Carrier Code #

You do not need to fill in the spaces on the upper right corner of the Form 18.
If you know that your employer has already filed a report of injury (Form 19) and you know what your I.C. (Industrial Commission) File Number is, you may write the number in the "I.C. File No." space.
If you do not already have an I.C. File Number, the Industrial Commission will assign one upon receipt of the Form 18.
The other two spaces, "Emp. Code No." and "Carrier Code No.", are for internal use only.
The I.C. File # is the unique identifier for this injury; it will be provided by return letter and is to be referenced in all future correspondence.
Employee's Name, Address and Social Security Number
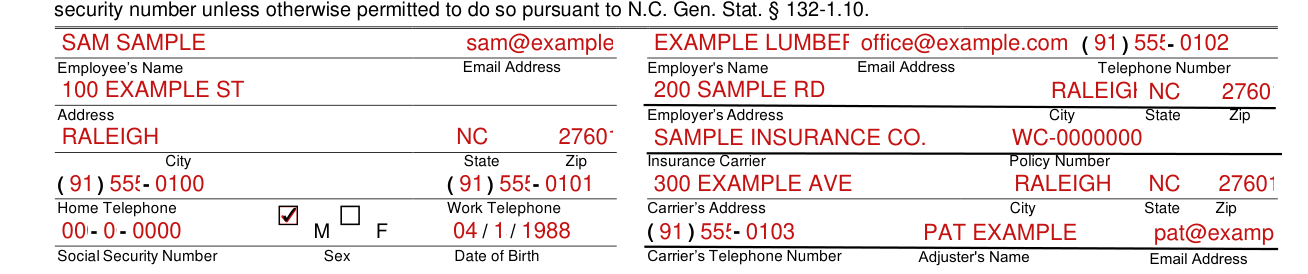
Enter the Employee's Name, Email Address, Address, City, State and Zip, then the Home Telephone and the Work Telephone.
Enter the Social Security Number, mark M or F for Sex and enter the Date of Birth.
The disclosure of a social security number by an individual to the Industrial Commission is voluntary.
The purpose of requesting your social security number on this form is for the Industrial Commission to verify the correct employer with the North Carolina Department of Commerce, Division of Employment Security and to identify workers' compensation insurance coverage.
Social security numbers are confidential and exempt from public disclosure by the Industrial Commission, which may not share your social security number unless otherwise permitted to do so pursuant to N.C. Gen. Stat. § 132-1.10.
Employer's Name and Insurance Carrier
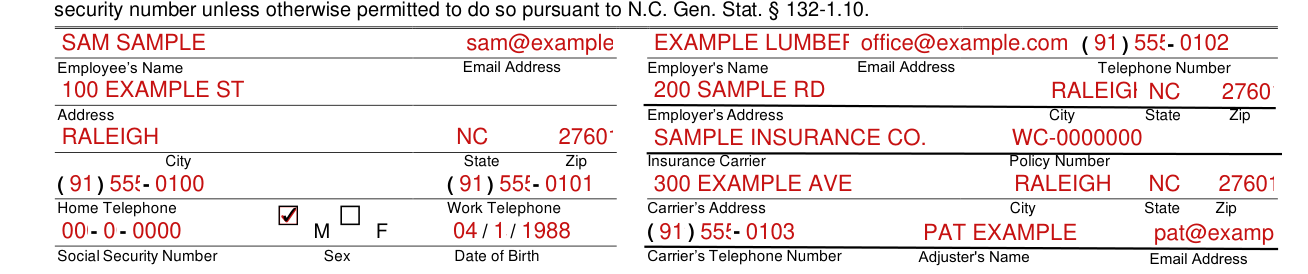
Enter the Employer's Name, Email Address, Telephone Number and Employer's Address with City, State and Zip.
Enter the Insurance Carrier, the Policy Number, the Carrier's Address with City, State and Zip, the Carrier's Telephone Number, the Adjuster's Name and the Email Address.
If you do not know who the employer's insurance carrier is you may either ask your employer for the information, call the Industrial Commission's Claims Administration Section at (800) 688-8349 then press "3" after the prompt, or simply leave the line blank.
The injury or occupational disease
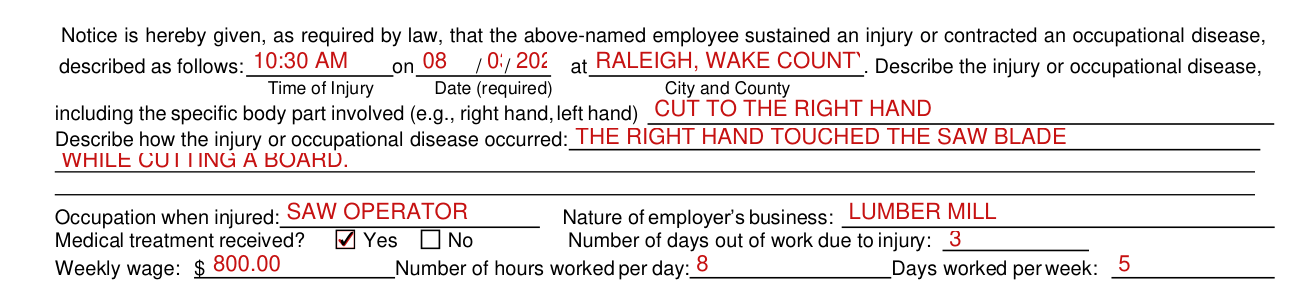
Enter the Time of Injury, the Date (required) and the City and County where the employee sustained an injury or contracted an occupational disease.
Describe the injury or occupational disease, including the specific body part involved (e.g., right hand, left hand).
Describe how the injury or occupational disease occurred.
Enter the Occupation when injured and the Nature of employer's business.
For Medical treatment received, check Yes or No.
Enter the Number of days out of work due to injury, the Weekly wage, the Number of hours worked per day and the Days worked per week.
When listing the number of days out of work, include partial as well as whole calendar days not worked; the days do not need to be consecutive.
Signature, Printed Name of Signer and Date Completed

Sign on the Signature line and check one: Employee, Attorney, Representative, or Dependent.
If the employee is unable to sign this form, another may sign for him.
Enter the Printed Name of Signer, E-mail Address, Telephone Number, Address, City, State, Zip Code and Date Completed.
More rules for Form 18
This form should also be used for occupational disease claims; however, for asbestosis, silicosis and byssinosis, Form 18B is to be used.
This form should be typed or printed by hand in black ink, if possible.
If your situation is different
Your employer files a Form 19 or is paying compensation
The employer is required by law to file a Form 19 if the employee misses more than one day of work due to the injury or if the medical bills exceed $4,000.00 (checked November 11, 2026).
Common mistake: The employer's filing of a Form 19 does not satisfy the employee's obligation to file a claim.
In order to ensure the employee's rights are protected, the employee must file a Form 18 even though the employer may be paying compensation or the Industrial Commission may have opened a file for the injury.
To whom should the Form 18 be sent?
The original Form 18 should be submitted to the Industrial Commission.
Employees e-mail the form to forms@ic.nc.gov or mail it to NCIC, Claims Section, 1235 Mail Service Center, Raleigh, North Carolina 27699-1235; attorneys file via EDFP at https://www.ic.nc.gov/docfiling.html.
The injured worker should keep one copy for his or her records and one copy should be submitted to the employer at the time of the injury.
What happens after I file the Form 18?
The Industrial Commission will mail an acknowledgement letter to you after your Form 18 is processed.
Processing time varies according to current workload.
The Industrial Commission will mail a copy of the acknowledgement letter to the employer or its workers' compensation insurance carrier asking them to contact you and inform you if compensation will be paid to you voluntarily.
Common questions about Form 18
What is form 18 for?
Form 18, the North Carolina Industrial Commission Notice of Accident to Employer and Claim of Employee, Representative, or Dependent, gives notice that an employee sustained an injury or contracted an occupational disease. The notice is sent to the employer in compliance with requirements of the North Carolina Workers' Compensation Act, in order that the medical services prescribed by the Act may be obtained; and, if disability extends beyond 7 days duration, or if death ensues, compensation may be paid according to law.
Is there a deadline?
The form must be filed with the Industrial Commission within two years of the date of injury or occupational disease or the claim may be barred, and notice shall be given to the employer immediately after the accident or as soon as practicable and within 30 days.
Sources
[1] Form 18 (07/2026), Notice of Accident to Employer and Claim of Employee, Representative, or Dependent, North Carolina Industrial Commission (the Official source link on this page).
