

OAAS-PF-10-014 at a glance
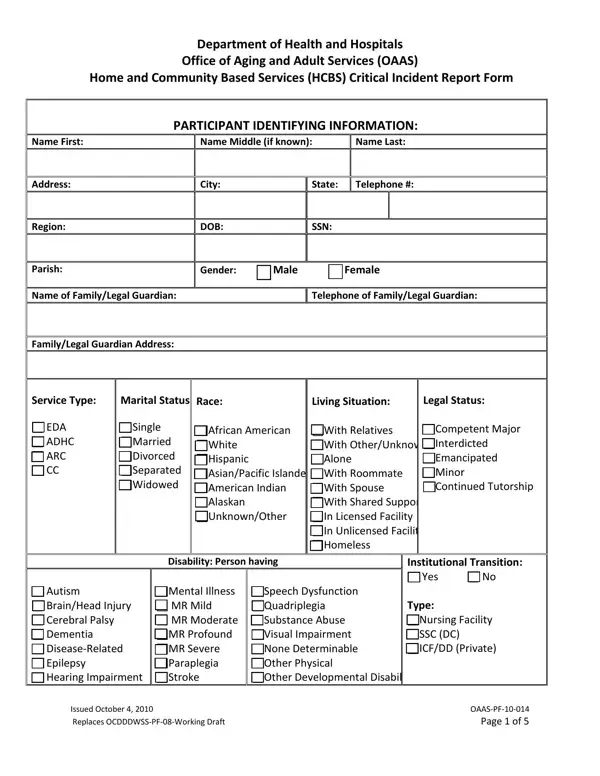
What it is: Home and Community Based Services (HCBS) Critical Incident Report Form of the Department of Health and Hospitals Office of Aging and Adult Services (OAAS), OAAS-PF-10-014.
Who signs: Use as many pages as necessary, numbering, dating and signing each page. Each additional page must be signed and dated.
A filled-in OAAS-PF-10-014 example: a direct service worker reports an incident

How to fill out OAAS-PF-10-014, box by box
PARTICIPANT IDENTIFYING INFORMATION
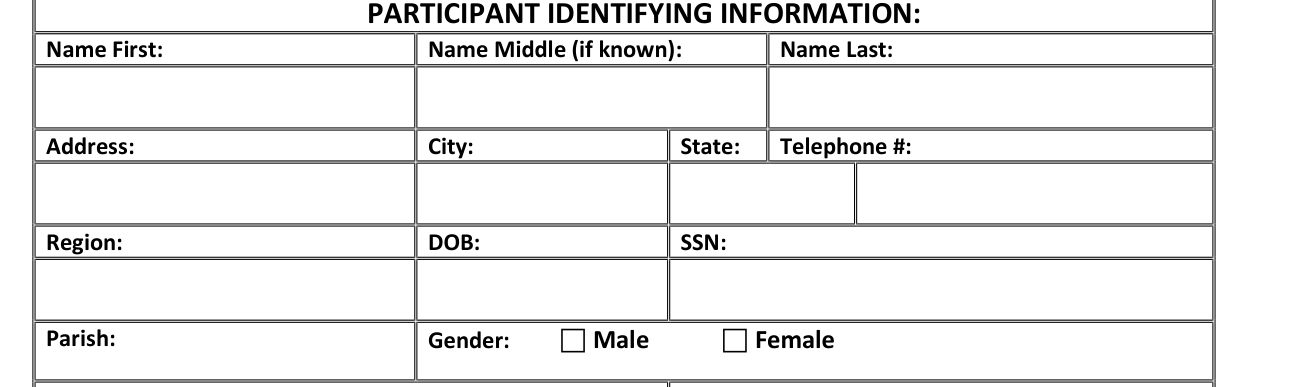
Under PARTICIPANT IDENTIFYING INFORMATION, enter Name First, Name Middle (if known) and Name Last.
Enter Address, City, State and Telephone #.
Enter Region, DOB and SSN.
Enter Parish. Gender: Male, Female.
Family/Legal Guardian

Enter Name of Family/Legal Guardian, Telephone of Family/Legal Guardian and Family/Legal Guardian Address.
Service Type, Marital Status, Race, Living Situation and Legal Status

Service Type: CCW, ADHC.
Marital Status: Single, Married, Divorced, Separated, Widowed.
Race: African American, White, Hispanic, Asian/Pacific Islander, American Indian, Alaskan, Unknown/Other.
Living Situation: With Relatives, With Other/Unknown, Alone, With Roommate, With Spouse, With Shared Support, In Licensed Facility, In Unlicensed Facility, Homeless.
Legal Status: Competent Major, Interdicted, Emancipated, Minor, Continued Tutorship.
Disability and Institutional Transition
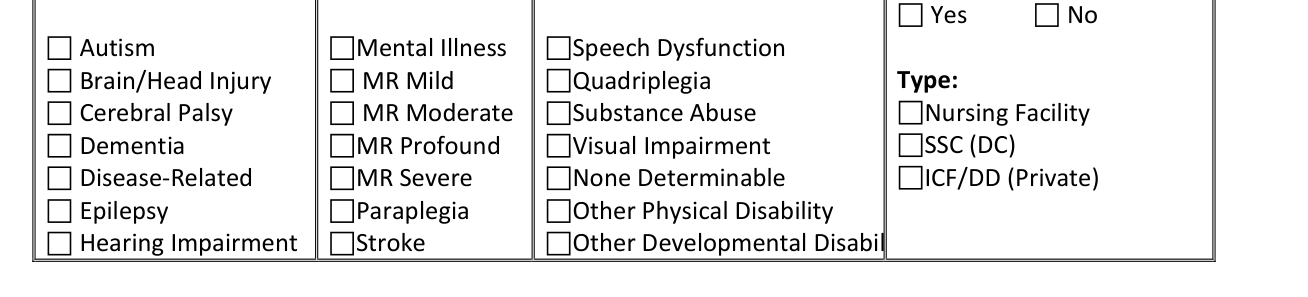
Disability: Person having Autism, Brain/Head Injury, Cerebral Palsy, Dementia, Disease-Related, Epilepsy, Hearing Impairment, Speech Dysfunction, Quadriplegia, Substance Abuse, Visual Impairment, None Determinable, Other Physical Disability, Other Developmental Disability, Mental Illness, MR Mild, MR Moderate, MR Profound, MR Severe, Paraplegia, Stroke.
Institutional Transition: Yes, No. Type: Nursing Facility, SSC (DC), ICF/DD (Private).
INCIDENT CATEGORIES
Common mistake: Incident categories: Check only those that apply.
All protective services allegations must be verbally reported.
If the Support Coordinator (SC) discovers/witnesses an Abuse, Neglect, Exploitation or Extortion incident involving a participant between the ages of 18-59, the SC should immediately verbally report the incident to APS.
If the SC discovers/witnesses an Abuse, Neglect, Exploitation or Extortion incident involving a participant between the ages of 18-59, the SC should complete the CIR and keep a copy for his/her record.
Common mistake: The SC shall not enter the information regarding APS Cases aged 18-59 into the Online Tracking Incident System. This only applies to APS cases aged 18-59, not APS cases aged 60 and over.
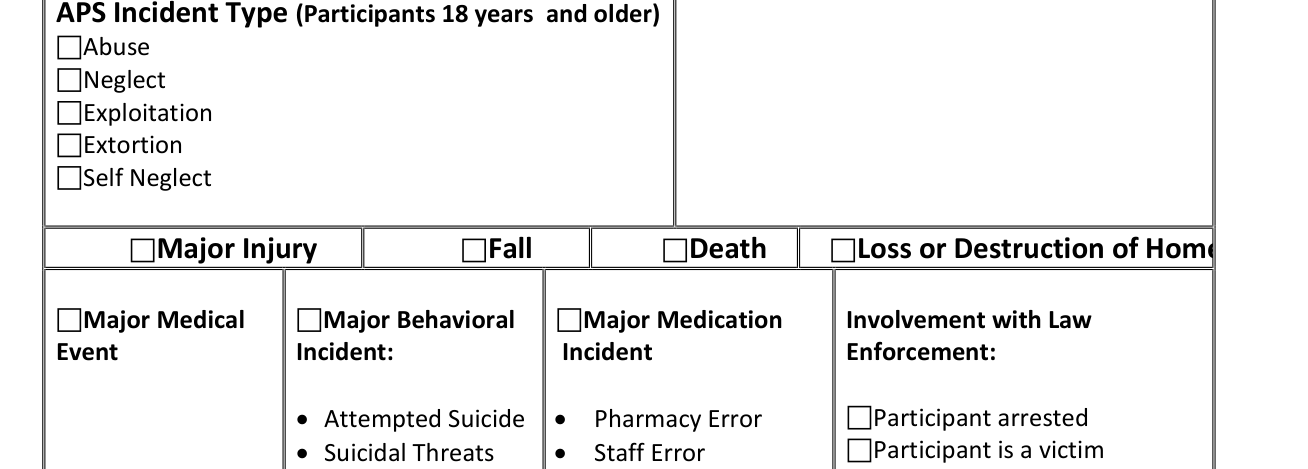
APS Incident Type (Participants 18 years and older): Abuse, Neglect, Exploitation, Extortion, Self Neglect.
Boxes: Major Injury, Fall, Death, Loss or Destruction of Home.
Box: Major Medical Event.
Major Behavioral Incident: Attempted Suicide, Suicidal Threats, Self-Endangerment, Elopement/Missing, Self-Injury, Offensive Sexual Behavior, Sexual Aggression, Physical Aggression.
Major Medication Incident: Pharmacy Error, Staff Error, Family Error, Participant Error.
Involvement with Law Enforcement: Participant arrested, Participant is a victim of a crime.
EVENT INFORMATION
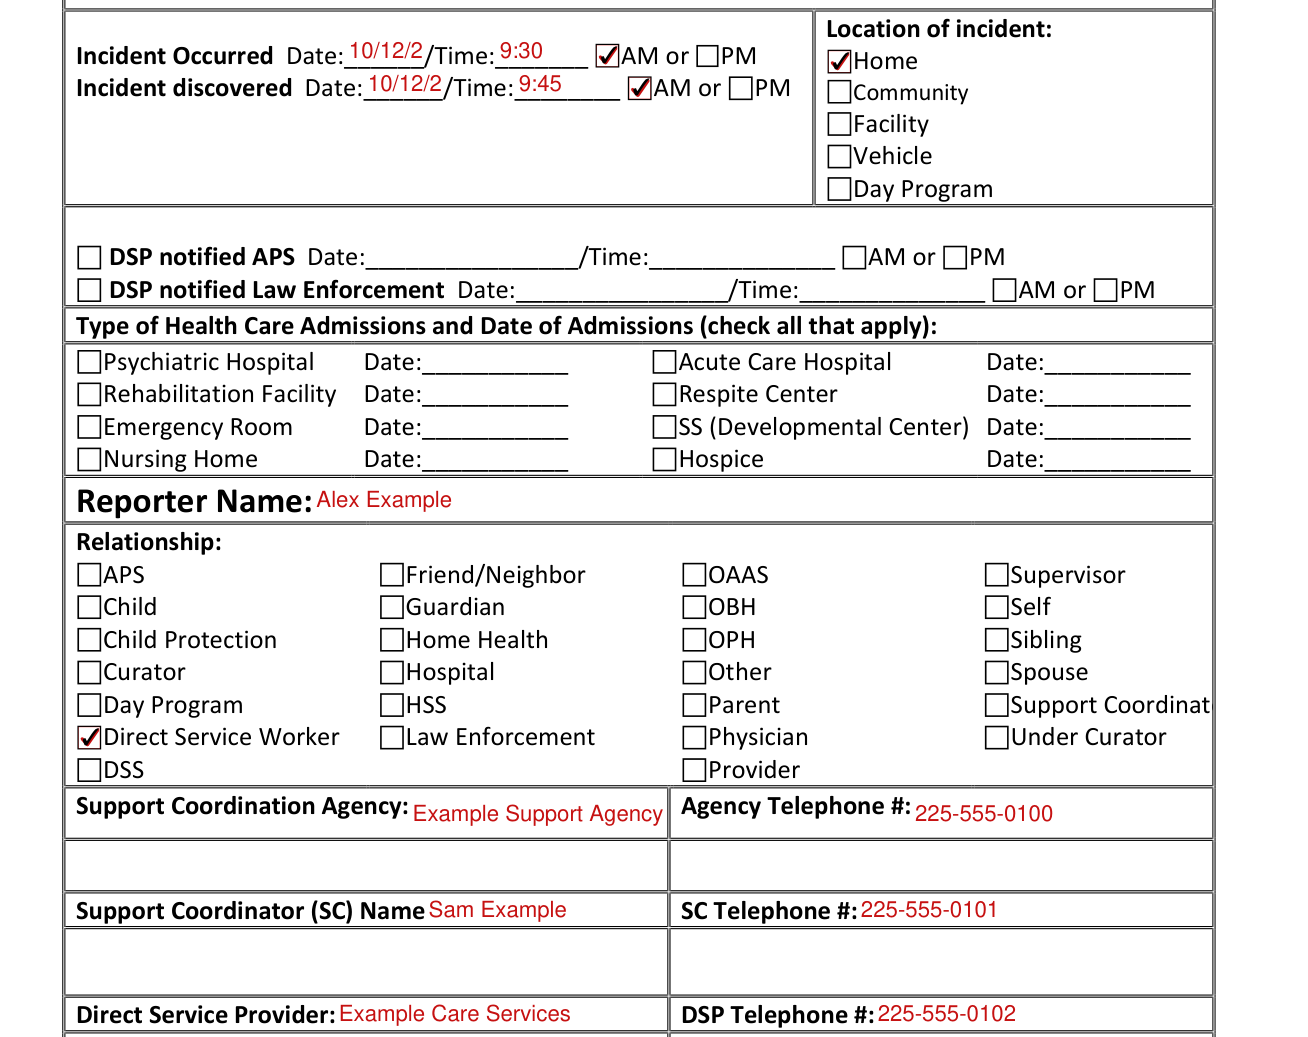
Enter Incident Occurred Date, Time and AM or PM, and Incident discovered Date, Time and AM or PM.
Location of incident: Home, Community, Facility, Vehicle, Day Program.
DSP notified APS: Date, Time, AM or PM. DSP notified Law Enforcement: Date, Time, AM or PM.
Type of Health Care Admissions and Date of Admissions (check all that apply): Psychiatric Hospital, Rehabilitation Facility, Emergency Room, Nursing Home, Acute Care Hospital, Respite Center, SS (Developmental Center), Hospice.
Enter Reporter Name. Relationship: APS, Child, Child Protection, Curator, Day Program, Direct Service Worker, DSS, Friend/Neighbor, Guardian, Home Health, Hospital, HSS, Law Enforcement, OAAS, OBH, OPH, Other, Parent, Physician, Provider, Supervisor, Self, Sibling, Spouse, Support Coordinator, Under Curator.
Enter Support Coordination Agency and Agency Telephone #, Support Coordinator (SC) Name and SC Telephone #, and Direct Service Provider and DSP Telephone #.
Critical Incident Description
Critical Incident Description: Enter all information regarding the incident (i.e., Who, What, When, Where, How, et cetera). Include all specifics and details related to the incident.
Include the name of the individual with the participant at the time of the incident (including relationship, address, telephone # and name of agency et cetera).
If Law Enforcement was notified, include the name of the agency, contact person, and address.
Use as many pages as necessary, numbering, dating and signing each page.
Enter Name of Direct Service Provider, Date reported to SC and Time, then Report completed by, Telephone #, Date and Region.
DSP Follow-Up
Use as many copies of this form as needed to complete your report.
Each additional page must be signed and dated.
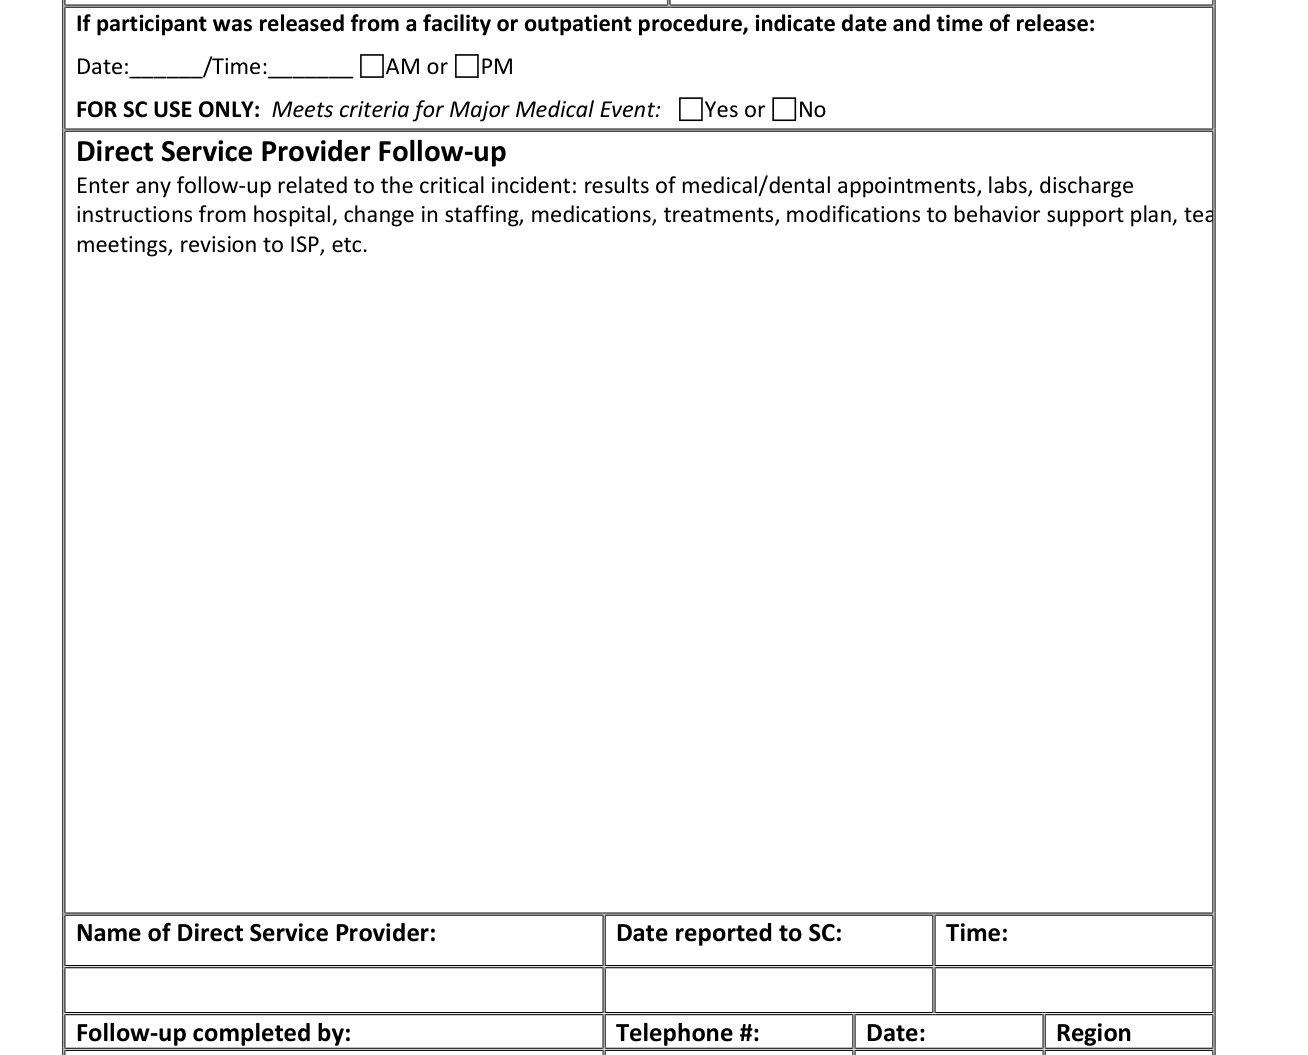
If participant was released from a facility or outpatient procedure, indicate date and time of release: Date, Time, AM or PM.
FOR SC USE ONLY: Meets criteria for Major Medical Event: Yes or No.
Direct Service Provider Follow-up: Enter any follow-up related to the critical incident: results of medical/dental appointments, labs, discharge instructions from hospital, change in staffing, medications, treatments, modifications to behavior support plan, tea meetings, revision to ISP, etc.
Enter Follow-up completed by, Telephone #, Date and Region.
More rules for OAAS-PF-10-014
Enter Participant Name and SSN.
Sources
[1] OAAS-PF-10-014, Home and Community Based Services (HCBS) Critical Incident Report Form, reissued September 2, 2014, Department of Health and Hospitals Office of Aging and Adult Services (OAAS) (the Official source link on this page).