

DA Form 5888-1 at a glance
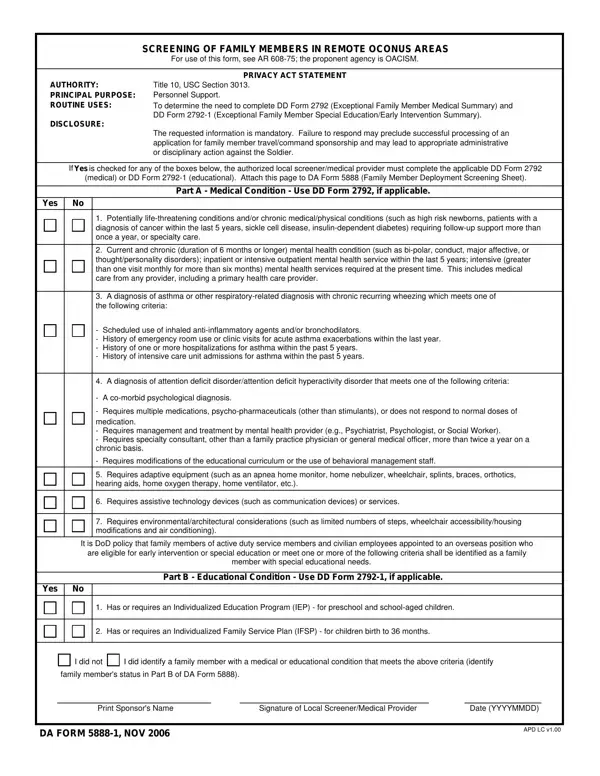
What it is: DA Form 5888-1 is the Screening of Family Members in Remote OCONUS Areas; for use of this form, AR 608-75.
Who signs: Print the Sponsor's Name, enter the Date (YYYYMMDD) and add the Signature of Local Screener/Medical Provider.
Attach DA Form 5888-1 to DA Form 5888 (Family Member Deployment Screening Sheet). If Yes is checked for any of the boxes in Part A or Part B, the authorized local screener/medical provider must complete the applicable DD Form 2792 (medical) or DD Form 2792-1 (educational).
A filled-in DA Form 5888-1 example: a screener marks asthma as the only Yes
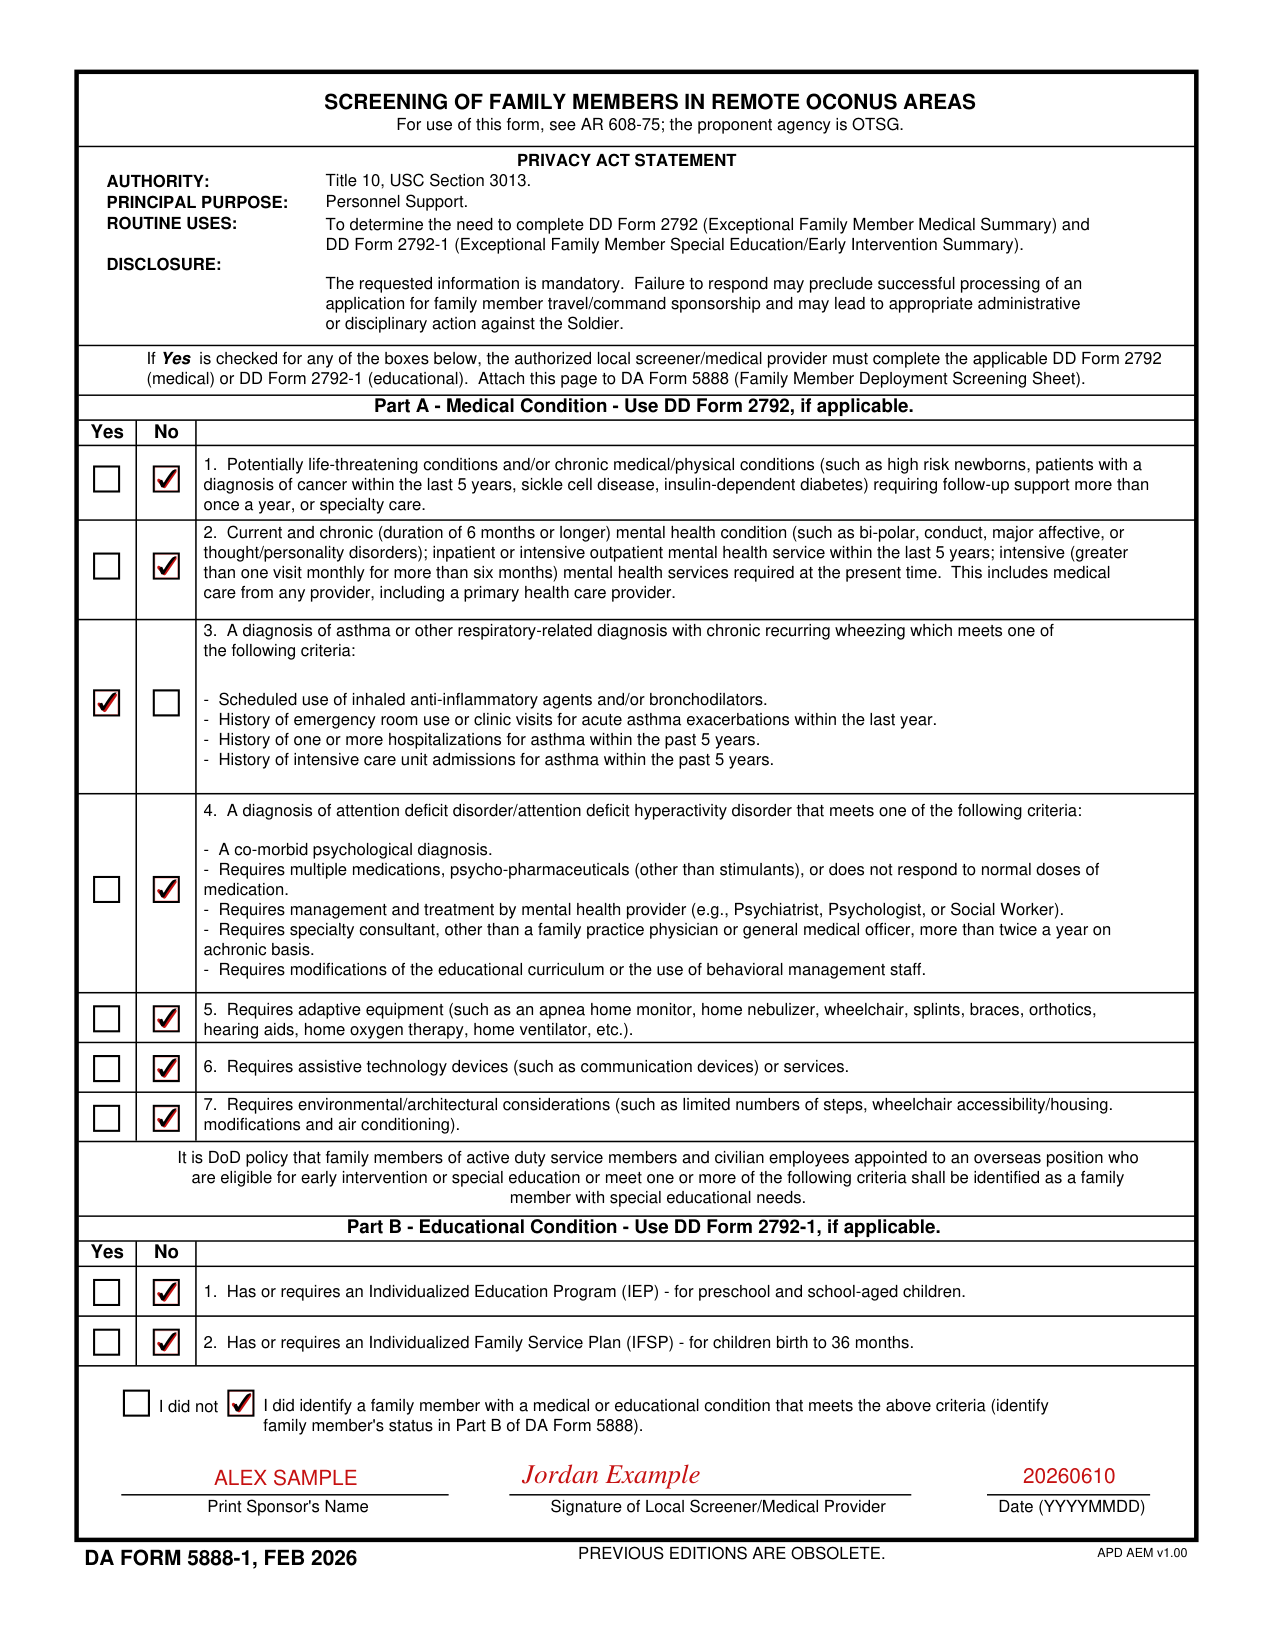
How to fill out DA Form 5888-1, box by box
Part A - Medical Condition: life-threatening, chronic and mental health conditions
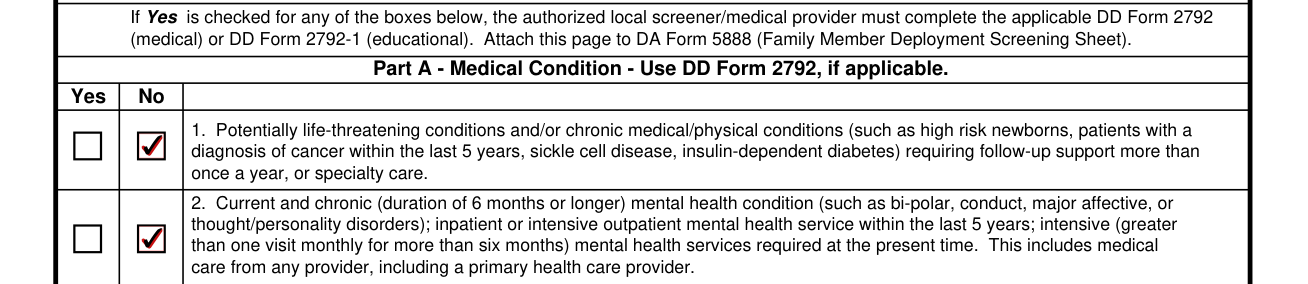
Part A - Medical Condition - Use DD Form 2792, if applicable. Check Yes or No.
Part A - 1. Potentially life-threatening conditions and/or chronic medical/physical conditions (such as high risk newborns, patients with a diagnosis of cancer within the last 5 years, sickle cell disease, insulin-dependent diabetes) requiring follow-up support more than once a year, or specialty care.
Part A - 2. Current and chronic (duration of 6 months or longer) mental health condition (such as bi-polar, conduct, major affective, or thought/personality disorders); inpatient or intensive outpatient mental health service within the last 5 years; intensive (greater than one visit monthly for more than six months) mental health services required at the present time. This includes medical care from any provider, including a primary health care provider.
Asthma or other respiratory-related diagnosis

Part A - 3. A diagnosis of asthma or other respiratory-related diagnosis with chronic recurring wheezing which meets one of the following criteria:
Scheduled use of inhaled anti-inflammatory agents and/or bronchodilators. History of emergency room use or clinic visits for acute asthma exacerbations within the last year. History of one or more hospitalizations for asthma within the past 5 years. History of intensive care unit admissions for asthma within the past 5 years.
Attention deficit disorder/attention deficit hyperactivity disorder

Part A - 4. A diagnosis of attention deficit disorder/attention deficit hyperactivity disorder that meets one of the following criteria:
A co-morbid psychological diagnosis. Requires multiple medications, psycho-pharmaceuticals (other than stimulants), or does not respond to normal doses of medication. Requires management and treatment by mental health provider (e.g., Psychiatrist, Psychologist, or Social Worker). Requires specialty consultant, other than a family practice physician or general medical officer, more than twice a year on a chronic basis. Requires modifications of the educational curriculum or the use of behavioral management staff.
Adaptive equipment, assistive technology and environmental considerations

Part A - 5. Requires adaptive equipment (such as an apnea home monitor, home nebulizer, wheelchair, splints, braces, orthotics, hearing aids, home oxygen therapy, home ventilator, etc.).
Part A - 6. Requires assistive technology devices (such as communication devices) or services.
Part A - 7. Requires environmental/architectural considerations (such as limited numbers of steps, wheelchair accessibility/housing modifications and air conditioning).
Part B - Educational Condition
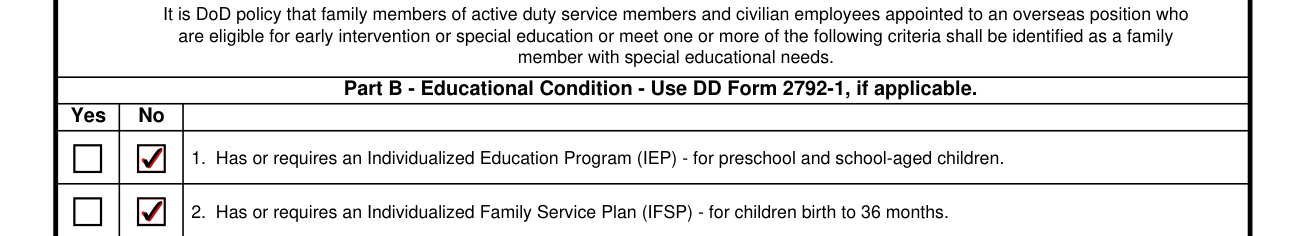
It is DoD policy that family members of active duty service members and civilian employees appointed to an overseas position who are eligible for early intervention or special education or meet one or more of the following criteria shall be identified as a family member with special educational needs.
Part B - Educational Condition - Use DD Form 2792-1, if applicable. Check Yes or No.
Part B - 1. Has or requires an Individualized Education Program (IEP) - for preschool and school-aged children.
Part B - 2. Has or requires an Individualized Family Service Plan (IFSP) - for children birth to 36 months.
I did not or I did identify a family member

Check I did not or I did identify a family member with a medical or educational condition that meets the criteria in Part A or Part B (identify family member's status in Part B of DA Form 5888).
Sponsor's name, date and signature of the local screener

Print the Sponsor's Name, enter the Date (YYYYMMDD) and add the Signature of Local Screener/Medical Provider.
More rules for DA Form 5888-1
The authority is Title 10, USC Section 3013, Personnel Support, and the routine uses are to determine the need to complete DD Form 2792 (Exceptional Family Member Medical Summary) and DD Form 2792-1 (Exceptional Family Member Special Education/Early Intervention Summary).
The requested information is mandatory. Failure to respond may preclude successful processing of an application for family member travel/command sponsorship and may lead to appropriate administrative or disciplinary action against the Soldier.
Sources
[1] DA Form 5888-1 (FEB 2026), Screening of Family Members in Remote OCONUS Areas, Department of the Army (the Official source link on this page).