

DD Form 137 at a glance
What it is: DD Form 137 is the Secondary Dependency Application.
Who signs: Sign at (1) SPONSOR(S) SIGNATURE and enter the DATE (YYYYMMDD) at (2).
To qualify as a secondary dependent, the claimed individual must be more than one-half (50%) 'in fact' dependent on the sponsor.
What to bring and attach to DD Form 137
Read information regarding supporting documentation to show dependency at the end of this form prior to completing.
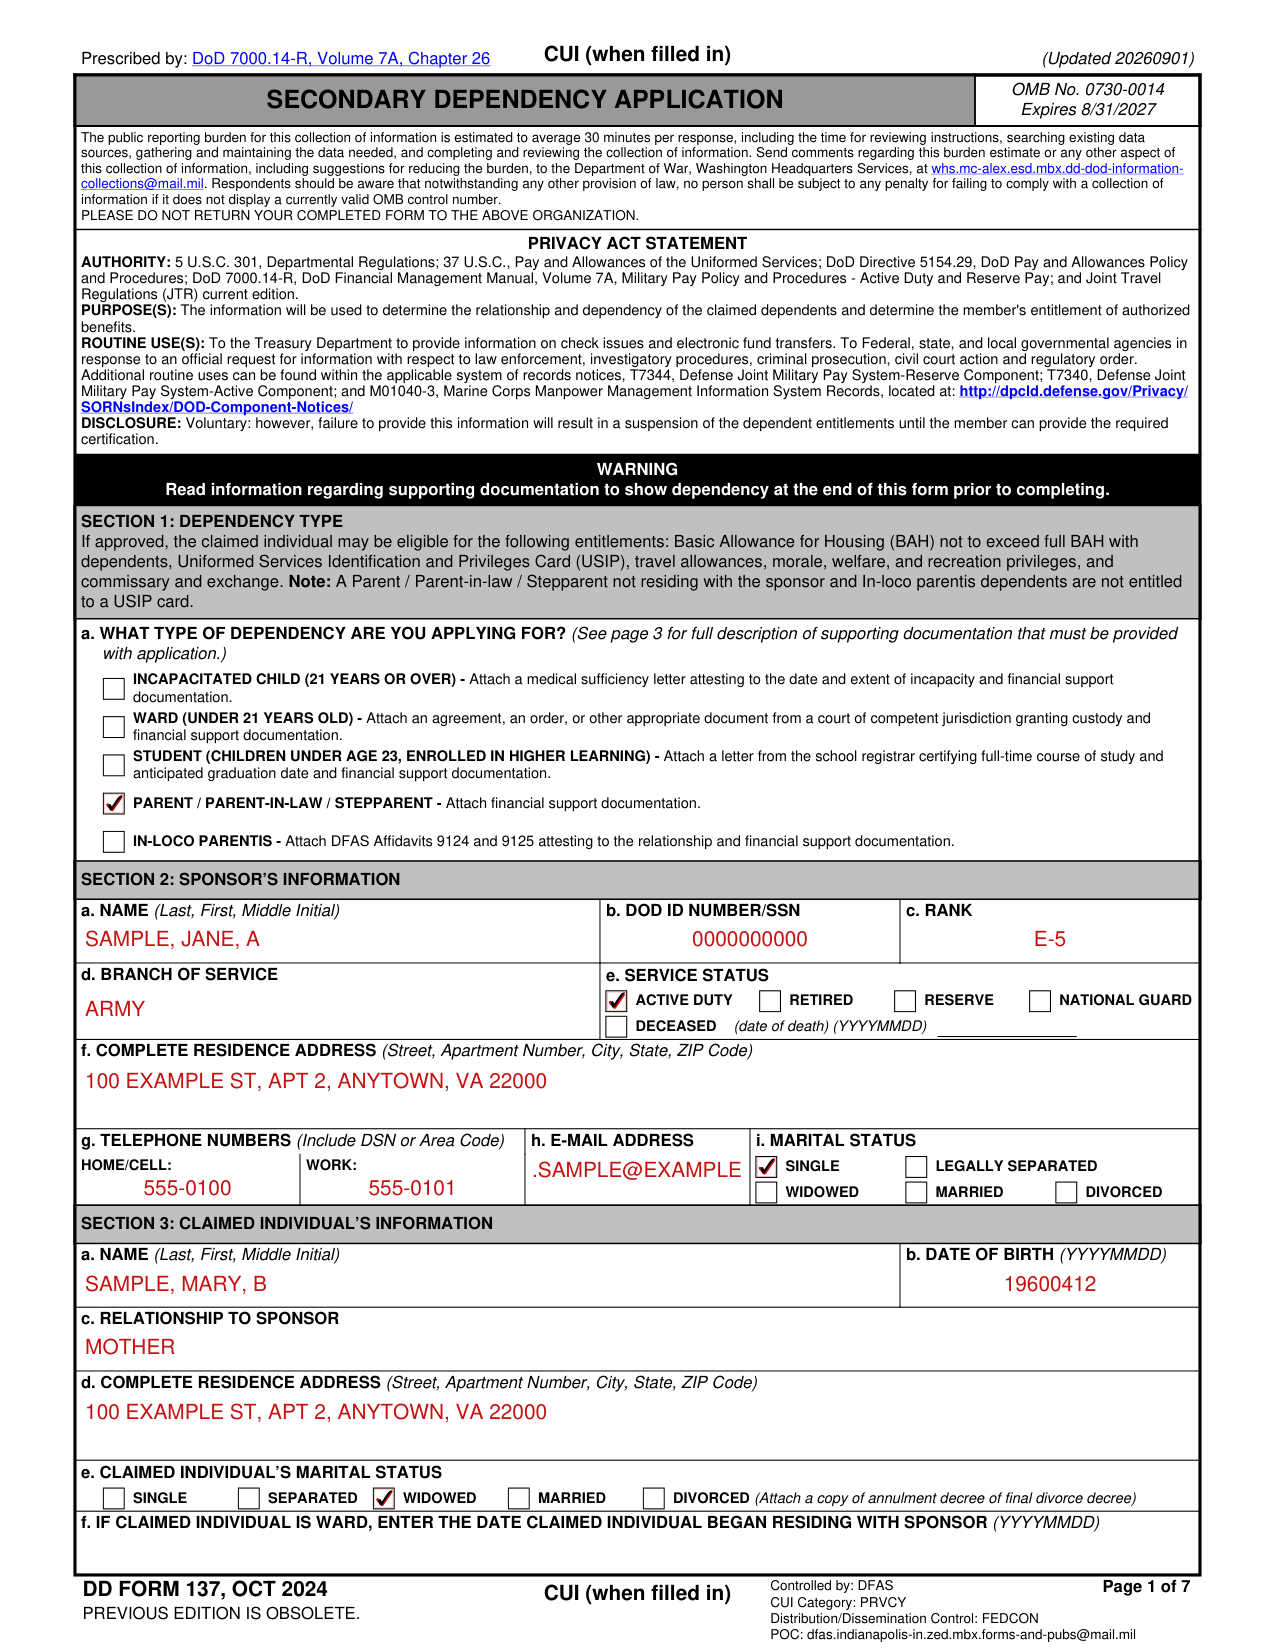
A filled-in DD Form 137 example: a sponsor claims her mother as a dependent
How to fill out DD Form 137, box by box
Section 1: Dependency type
Mark the type of dependency you are applying for; see page 3 for full description of supporting documentation that must be provided with application.
For INCAPACITATED CHILD (21 YEARS OR OVER), attach a medical sufficiency letter attesting to the date and extent of incapacity and financial support documentation. For WARD (UNDER 21 YEARS OLD), attach an agreement, an order, or other appropriate document from a court of competent jurisdiction granting custody and financial support documentation. For STUDENT (CHILDREN UNDER AGE 23, ENROLLED IN HIGHER LEARNING), attach a letter from the school registrar certifying full-time course of study and anticipated graduation date and financial support documentation.
For PARENT / PARENT-IN-LAW / STEPPARENT, attach financial support documentation.
For IN-LOCO PARENTIS, attach DFAS Affidavits 9124 and 9125 attesting to the relationship and financial support documentation.
SECTION 1: DEPENDENCY TYPE. If approved, the claimed individual may be eligible for Basic Allowance for Housing (BAH) not to exceed full BAH with dependents, Uniformed Services Identification and Privileges Card (USIP), travel allowances, morale, welfare, and recreation privileges, and commissary and exchange. Note: A Parent / Parent-in-law / Stepparent not residing with the sponsor and In-loco parentis dependents are not entitled to a USIP card.
Section 2: Sponsor's information
In SECTION 2: SPONSOR'S INFORMATION, enter the NAME (Last, First, Middle Initial), DOD ID NUMBER/SSN and RANK.
Enter the branch of service and mark the service status: active duty, retired, reserve, national guard or deceased (date of death) (YYYYMMDD).
Enter the COMPLETE RESIDENCE ADDRESS (Street, Apartment Number, City, State, ZIP Code).
Enter the TELEPHONE NUMBERS (Include DSN or Area Code): HOME/CELL and WORK.
Enter the E-MAIL ADDRESS and mark the MARITAL STATUS: SINGLE, LEGALLY SEPARATED, WIDOWED, MARRIED or DIVORCED.
Section 3: Claimed individual's information
In SECTION 3: CLAIMED INDIVIDUAL'S INFORMATION, enter the NAME (Last, First, Middle Initial) and DATE OF BIRTH (YYYYMMDD).
Enter the RELATIONSHIP TO SPONSOR and the COMPLETE RESIDENCE ADDRESS (Street, Apartment Number, City, State, ZIP Code).
Mark the CLAIMED INDIVIDUAL'S MARITAL STATUS: SINGLE, SEPARATED, WIDOWED, MARRIED or DIVORCED (Attach a copy of annulment decree of final divorce decree).
If claimed individual is ward, enter the date claimed individual began residing with sponsor (YYYYMMDD).
Section 3 g: Does any other person claim the individual
Does any other person(s) claim the individual for Basic Allowance for Housing, travel allowance, or Uniformed Services Identification and Privileges (USIP) card? Mark YES (list below) or NO (skip to SECTION 4).
If YES, list the NAME (Last, First, Middle Initial), DOD ID NUMBER and BRANCH OF SERVICE.
Section 4: School attendance
SECTION 4: If claimed individual has been enrolled in a full-time course of study in the past 12 months, furnish all of the following information and include proof of school registration with your application; if not, skip to SECTION 5.
Enter the NAME AND ADDRESS OF SCHOOL, the DATES ATTENDED (YYYYMMDD) FROM and TO, and the STUDENT MAILING ADDRESS.
Student may still qualify for a Uniformed Services Identification and Privileges Card (USIP) during school break if enrolled before school break and immediately after school break.
Section 5: Hospital or institution
SECTION 5: IF CLAIMED INDIVIDUAL RESIDES IN A HOSPITAL OR INSTITUTION. If claimed individual is in a hospital or institution, furnish all of the following information; if not, skip to SECTION 6.
Enter the ENTERED HOSPITAL/INSTITUTION date (YYYYMMDD) and the ANTICIPATED DATE OF DISCHARGE (YYYYMMDD).
Mark YES or NO to WILL CLAIMED INDIVIDUAL RETURN TO SPONSOR'S HOME AFTER DISCHARGE?; for NO, explain where claimed dependent will reside.
Section 6: Financial support requirement
Did you claim the individual named in 3A as a dependent on your most recent tax return? Mark YES or NO.
For YES, provide a copy of your prior year's tax return showing the claimed individual as a dependent.
If you do not want, or are unable to provide a copy of your tax returns, complete and return Worksheet for Determining Financial Support with your DD137 to demonstrate financial support of the claimed individual.
For NO, complete and return the Worksheet for Determining Financial Support with your DD137 to demonstrate financial support of the claimed individual.
Sections 7 and 8: Remarks and financial dependency
Write in SECTION 7: REMARKS if necessary; use back.
Sponsors must provide more than one-half (50%) of the claimed individual's support.
The claimed individual's income that is used for own support must also be considered in determining whether the Sponsor is providing more than one-half support.
You must prove financial dependency to qualify.
In SECTION 8: FINANCIAL DEPENDENCY, mark the certification: Under penalties of perjury, I certify claimed individual is to my knowledge my dependent as defined by this form.
Section 9: Signatures
Read the penalty provisions, sign and date the form. Whoever, in any matter within the jurisdiction of any department or agency of the United States, knowingly and willfully falsifies, conceals, or covers up by any trick, scheme, or device, a material fact, or makes any false, fictitious, or fraudulent statements or representations, or makes or uses any false writing or document knowing the same to contain any false, fictitious, or fraudulent statement or entry, shall be fined as provided in Title 18, or imprisoned not more than 5 years, or both (U.S. Code, title 18, section 1001).
The information provided in this form may be referred to the appropriate Military Service investigative agency.
I make the claim with full knowledge of the penalties involved for willfully making a false claim. (U.S. Code, title 18, section 287, formerly section 80, provides a penalty: imprisonment for not more than five years and subject to a fine in the amount provided in this title.)
Under SPONSOR/CLAIMED INDIVIDUAL'S REPRESENTATIVE, print name(s); you will immediately notify the service concerned of any change in claimed dependent's financial circumstances, marital status, physical custody, or change in dependency upon the sponsor as shown in this form.
Sign at (1) SPONSOR(S) SIGNATURE and enter the DATE (YYYYMMDD) at (2).
Worksheet for Determining Financial Support
Read the instructions at the end of this form in their entirety prior to completing; under PERSONAL INFORMATION enter the SPONSOR NAME (Last, First, Middle Initial), DOD ID NUMBER/SSN, CLAIMED INDIVIDUAL'S NAME (Last, First, Middle Initial) and DATE (YYYYMMDD).
Line 1: Enter the total funds belonging to the person you supported, including income received (taxable and nontaxable) and amounts borrowed during the year, plus the amount in savings and other accounts at the beginning of the year. Do not include funds provided by the state; include those amounts on line 23 instead.
Line 2: Enter the amount on line 1 that was used for the person's own support. Line 3: Enter the amount on line 1 that was used for other purposes. Line 4: Enter the total amount in the person's savings and other accounts at the end of the year. Line 5: Add lines 2 through 4. (This amount should equal line 1.)
Line 7: Enter the total food expenses.
Line 8: Enter the total amount of utilities (heat, electric, water, etc., not included in line 6a or 6b).
Line 9: Enter the total amount of home repairs (not included in line 6a or 6b).
Line 10: Enter the total of other household expenses.
Line 11: Add lines 6a through 10. These are the total household expenses.
Line 12: Enter total number of persons who lived in the household.
Line 13: Divide line 11 by line 12. This is the person's share of the household expenses.
Line 14: Enter person's total clothing expenses.
Line 15: Enter the person's total education expenses (not covered by scholarship or grants).
Line 16: Enter the person's medical, vision, and dental expenses not paid for or reimbursed by insurance or TRICARE.
Line 17: Enter the person's total travel and recreation expenses.
Line 18: Enter the total of the person's other expenses.
Line 19: Add lines 13 through 18. This is the total cost of the person's support for the year.
Line 20: Multiply line 19 by 50% (0.50).
Line 22: Is line 21 more than line 20?
Line 24: Add lines 21 and 23.
Line 25: Subtract line 24 from line 19. This is the amount you provided for the person's support.
Line 26: Is line 25 more than line 20?
If your situation is different
A parent is claimed
Parent: The individual named in section 3a is dependent on the member sponsor for over one-half of his/ her support, and for USIP Benefits only: the individual named in section 3a resides (lives with) with member sponsor. If person does not meet these criteria, they are not eligible for secondary dependency status. A member/sponsor may claim a parent as dependent for housing and travel allowance purposes even if parent is not residing with the member/sponsor.
You will need to send more than one document. Send the prior year's tax return or the Worksheet for Determining Financial Support and Member's birth certificate or other official documents of birth, letter from an authorized adoption agency, letter from the authorized placement agency, or applicable court document that verify relationship to the member if not previously enrolled in DEERS, and Parent's Marriage Certificate.
Sources
[1] DD Form 137 (OCT 2024), Secondary Dependency Application, Washington Headquarters Services (the Official source link on this page).
