
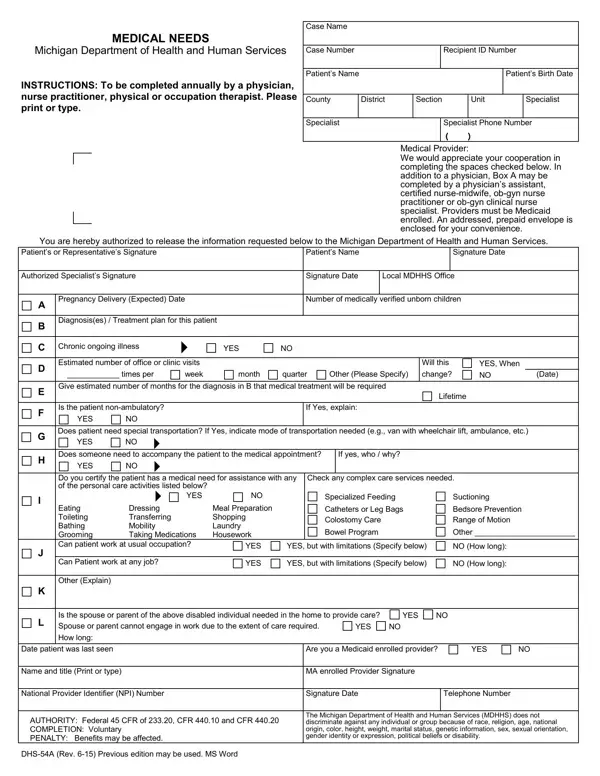

Form DHS-54A at a glance
What it is: DHS-54A, Medical Needs, is a Michigan Department of Health and Human Services form to be completed annually by a physician, nurse practitioner, physical or occupation therapist.
Who signs: The MA enrolled Provider Signature line is signed by the provider.
In addition to a physician, Box A may be completed by a physician's assistant, certified nurse-midwife, ob-gyn nurse practitioner or ob-gyn clinical nurse specialist.
Providers must be Medicaid enrolled.
A filled-in Form DHS-54A example: a physician records a chronic illness
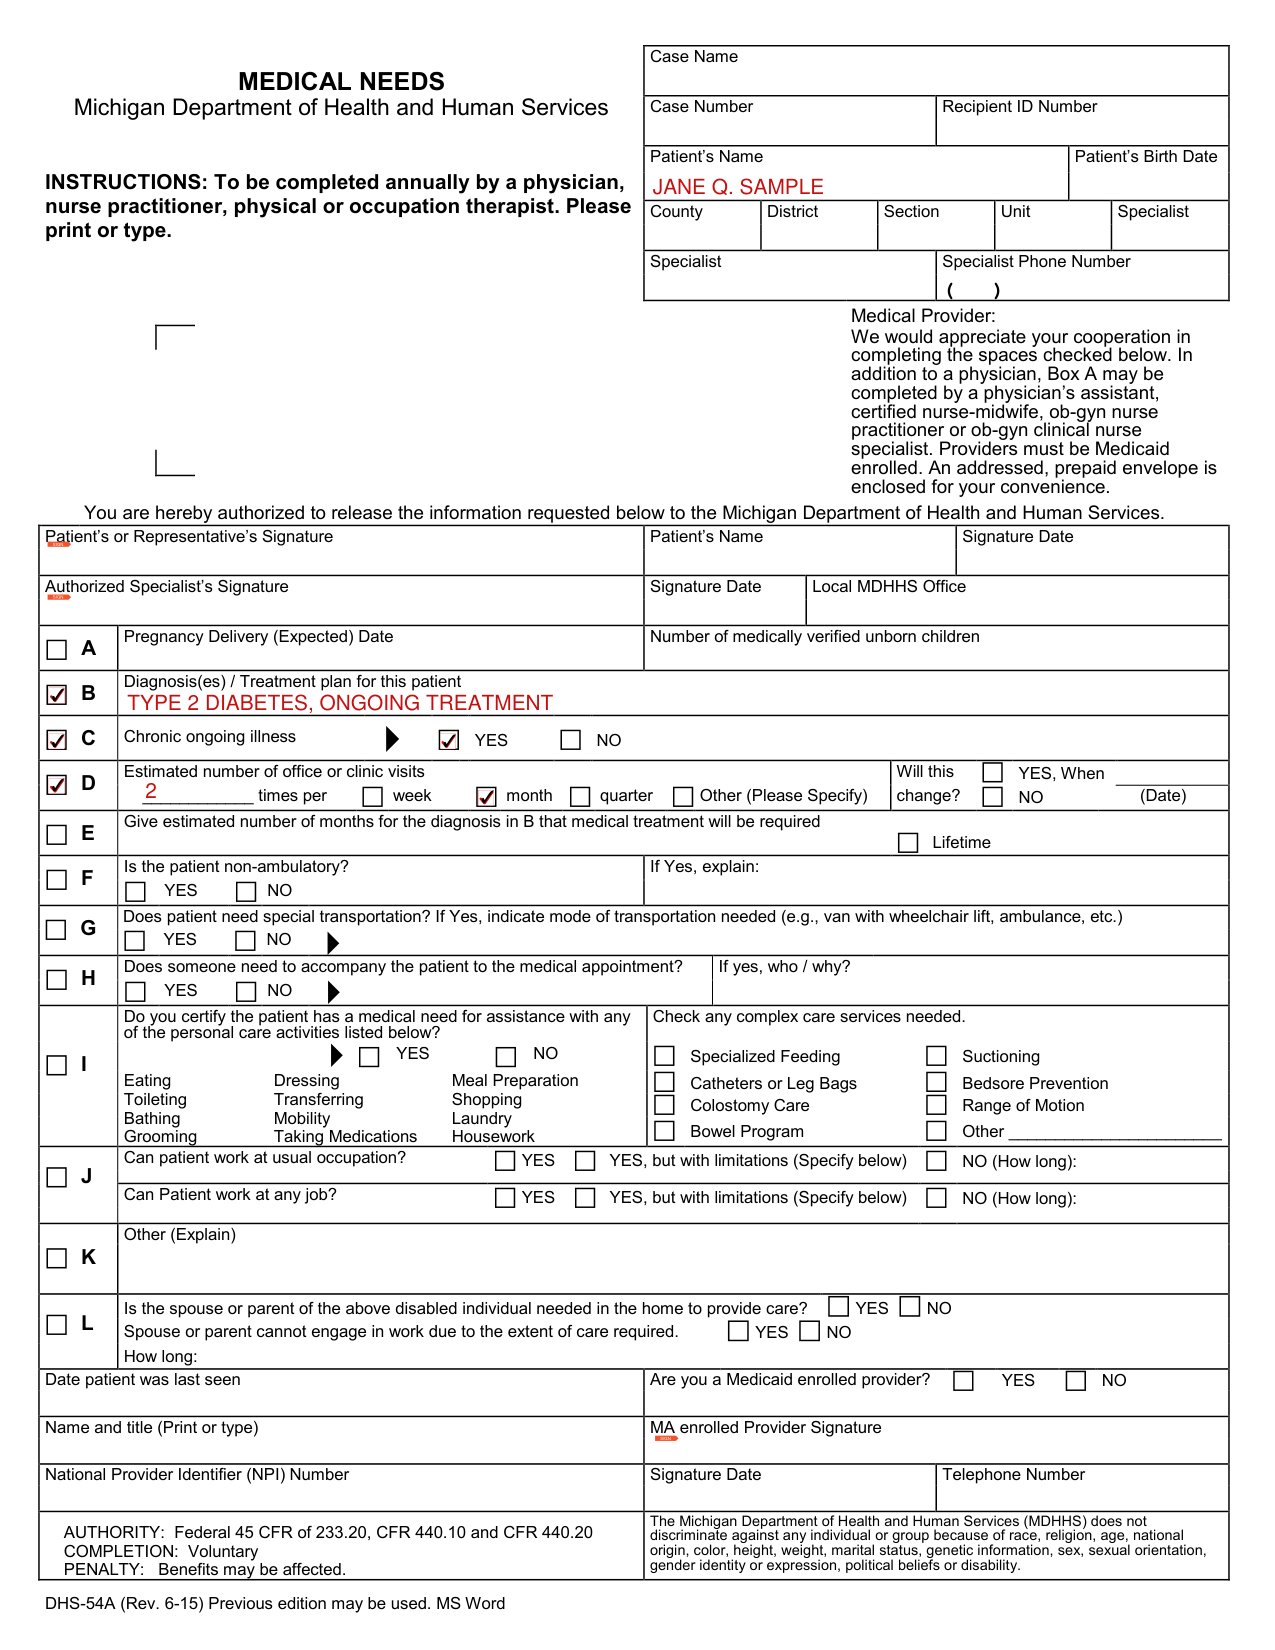
How to fill out Form DHS-54A, box by box
Case Name, Case Number, Recipient ID Number, Patient's Name and Patient's Birth Date
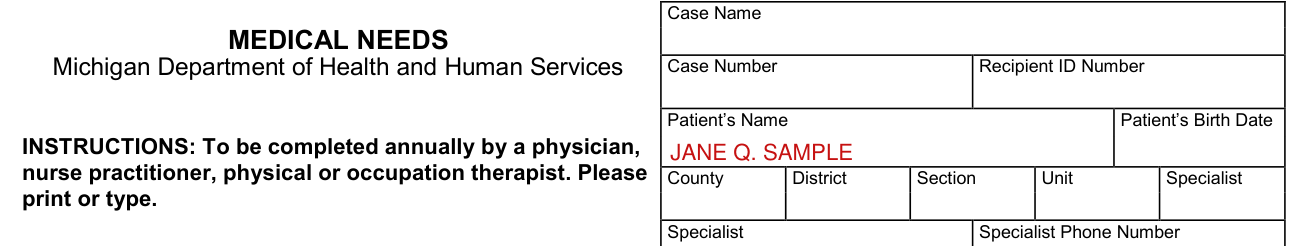
Fill in the Case Name, Case Number, Recipient ID Number, Patient's Name and Patient's Birth Date.
County, District, Section, Unit and Specialist

Fill in the County, District, Section, Unit, Specialist and Specialist Phone Number.
Signatures for release of information
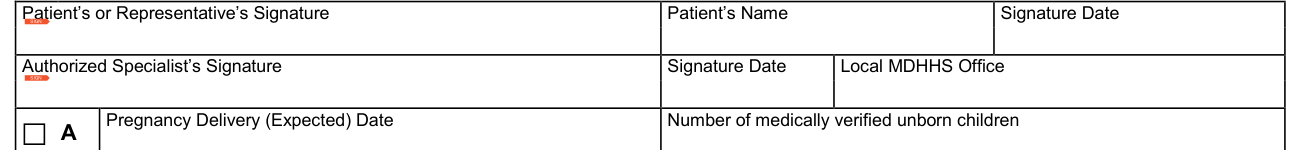
You are hereby authorized to release the information requested to the Michigan Department of Health and Human Services.
The Patient's or Representative's Signature line, with the Patient's Name and Signature Date, is for the patient or representative; the Authorized Specialist's Signature line, with the Signature Date and Local MDHHS Office, is for the specialist.
A Pregnancy Delivery (Expected) Date

In Box A, enter the Pregnancy Delivery (Expected) Date and the Number of medically verified unborn children.
B Diagnosis(es) / Treatment plan

In Box B, enter the Diagnosis(es) / Treatment plan for this patient.
C Chronic ongoing illness

In Box C, mark YES or NO for Chronic ongoing illness.
D Estimated number of office or clinic visits
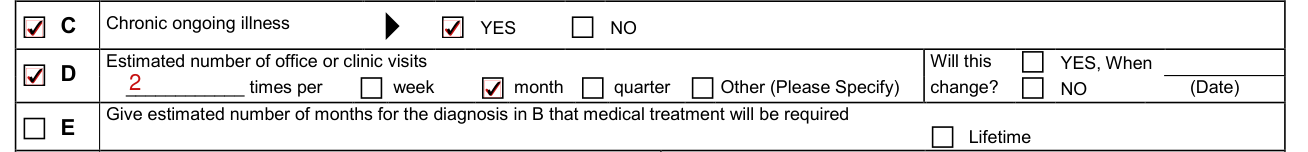
In Box D, enter the Estimated number of office or clinic visits as ____________ times per week, month, quarter or Other (Please Specify). For Will this change?, mark YES, When (Date) or NO.
E Estimated number of months of treatment

In Box E, give the estimated number of months for the diagnosis in B that medical treatment will be required, or mark Lifetime.
F Is the patient non-ambulatory?

In Box F, mark YES or NO for Is the patient non-ambulatory? If Yes, explain.
G Does patient need special transportation?

In Box G, mark YES or NO for Does patient need special transportation? If Yes, indicate mode of transportation needed (e.g., van with wheelchair lift, ambulance, etc.).
H Does someone need to accompany the patient?

In Box H, mark YES or NO for Does someone need to accompany the patient to the medical appointment? If yes, who / why?
I Personal care activities and complex care services

In Box I, mark YES or NO for Do you certify the patient has a medical need for assistance with any of the personal care activities listed?
After YES or NO, check any of the personal care activities with a medical need for assistance: Eating, Dressing, Meal Preparation, Toileting, Transferring, Shopping, Bathing, Mobility, Laundry, Grooming, Taking Medications and Housework.
Check any complex care services needed: Specialized Feeding, Suctioning, Catheters or Leg Bags, Bedsore Prevention, Colostomy Care, Range of Motion, Bowel Program or Other.
J Can patient work?

In Box J, for Can patient work at usual occupation? and for Can Patient work at any job?, mark YES, YES, but with limitations (Specify) or NO (How long):.
K Other (Explain)

Explain the Other in Box K.
L Spouse or parent needed in the home

In Box L, mark YES or NO for Is the spouse or parent of the disabled individual needed in the home to provide care?
For Spouse or parent cannot engage in work due to the extent of care required, mark YES or NO and enter How long.
Provider name, signature and Medicaid enrollment
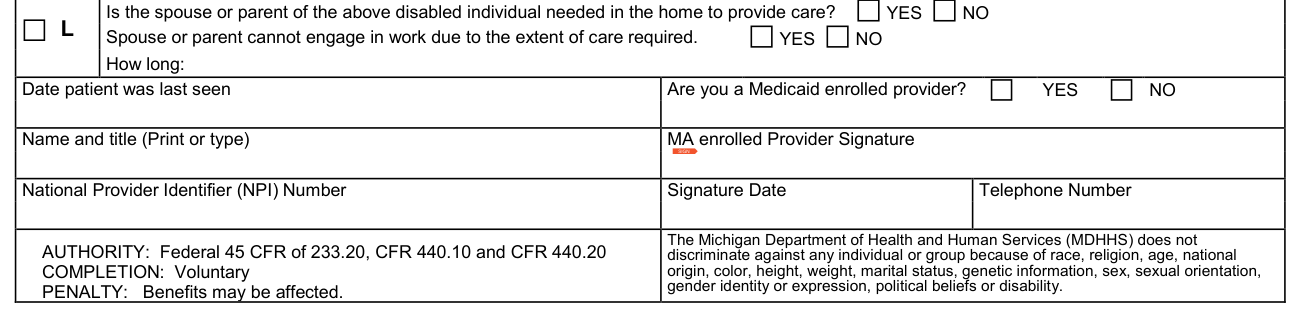
Enter the Date patient was last seen.
Mark YES or NO for Are you a Medicaid enrolled provider?
Enter the Name and title (Print or type) and the National Provider Identifier (NPI) Number, Signature Date and Telephone Number.
More rules for Form DHS-54A
Complete the spaces that are checked.
An addressed, prepaid envelope is enclosed for your convenience.
Common questions about Form DHS-54A
Is there a penalty?
COMPLETION: Voluntary, PENALTY: Benefits may be affected, with AUTHORITY: Federal 45 CFR of 233.20, CFR 440.10 and CFR 440.20.
Sources
[1] Form DHS-54A (Rev. 6-15), Medical Needs, Michigan Department of Health and Human Services (the Official source link on this page).