

Form DMAS-225 at a glance
What it is: The Medicaid LTSS Communication Form DMAS-225 allows the local Department of Social Services (LDSS), Managed Care Organizations (MCOs), nursing facilities, waiver services providers and PACE programs to exchange information.
Where and when to file: For individuals in a NF, send the original to the MCO (CCC Plus) or the NF (FFS only).
The form is initiated by either the LDSS, MCO for individuals in a managed care plan, or the provider of care.
The MCO or provider must use the form to document admission date, request Medicaid eligibility status, and notify the LDSS of changes in the individual's circumstances, discharge or death.
The form exchanges information regarding: the Medicaid eligibility status of an individual; a change in the individual's level of care; admission or discharge of an individual to an institution, HCBS, or Hospice, or to report the death of an individual; other information known to the provider that might cause a change in the eligibility status or patient pay amounts.
What to bring and attach to Form DMAS-225
A copy of the DMAS-96 must be attached to this form when the individual is first admitted to care.
A filled-in Form DMAS-225 example: a nursing facility reports a new admission
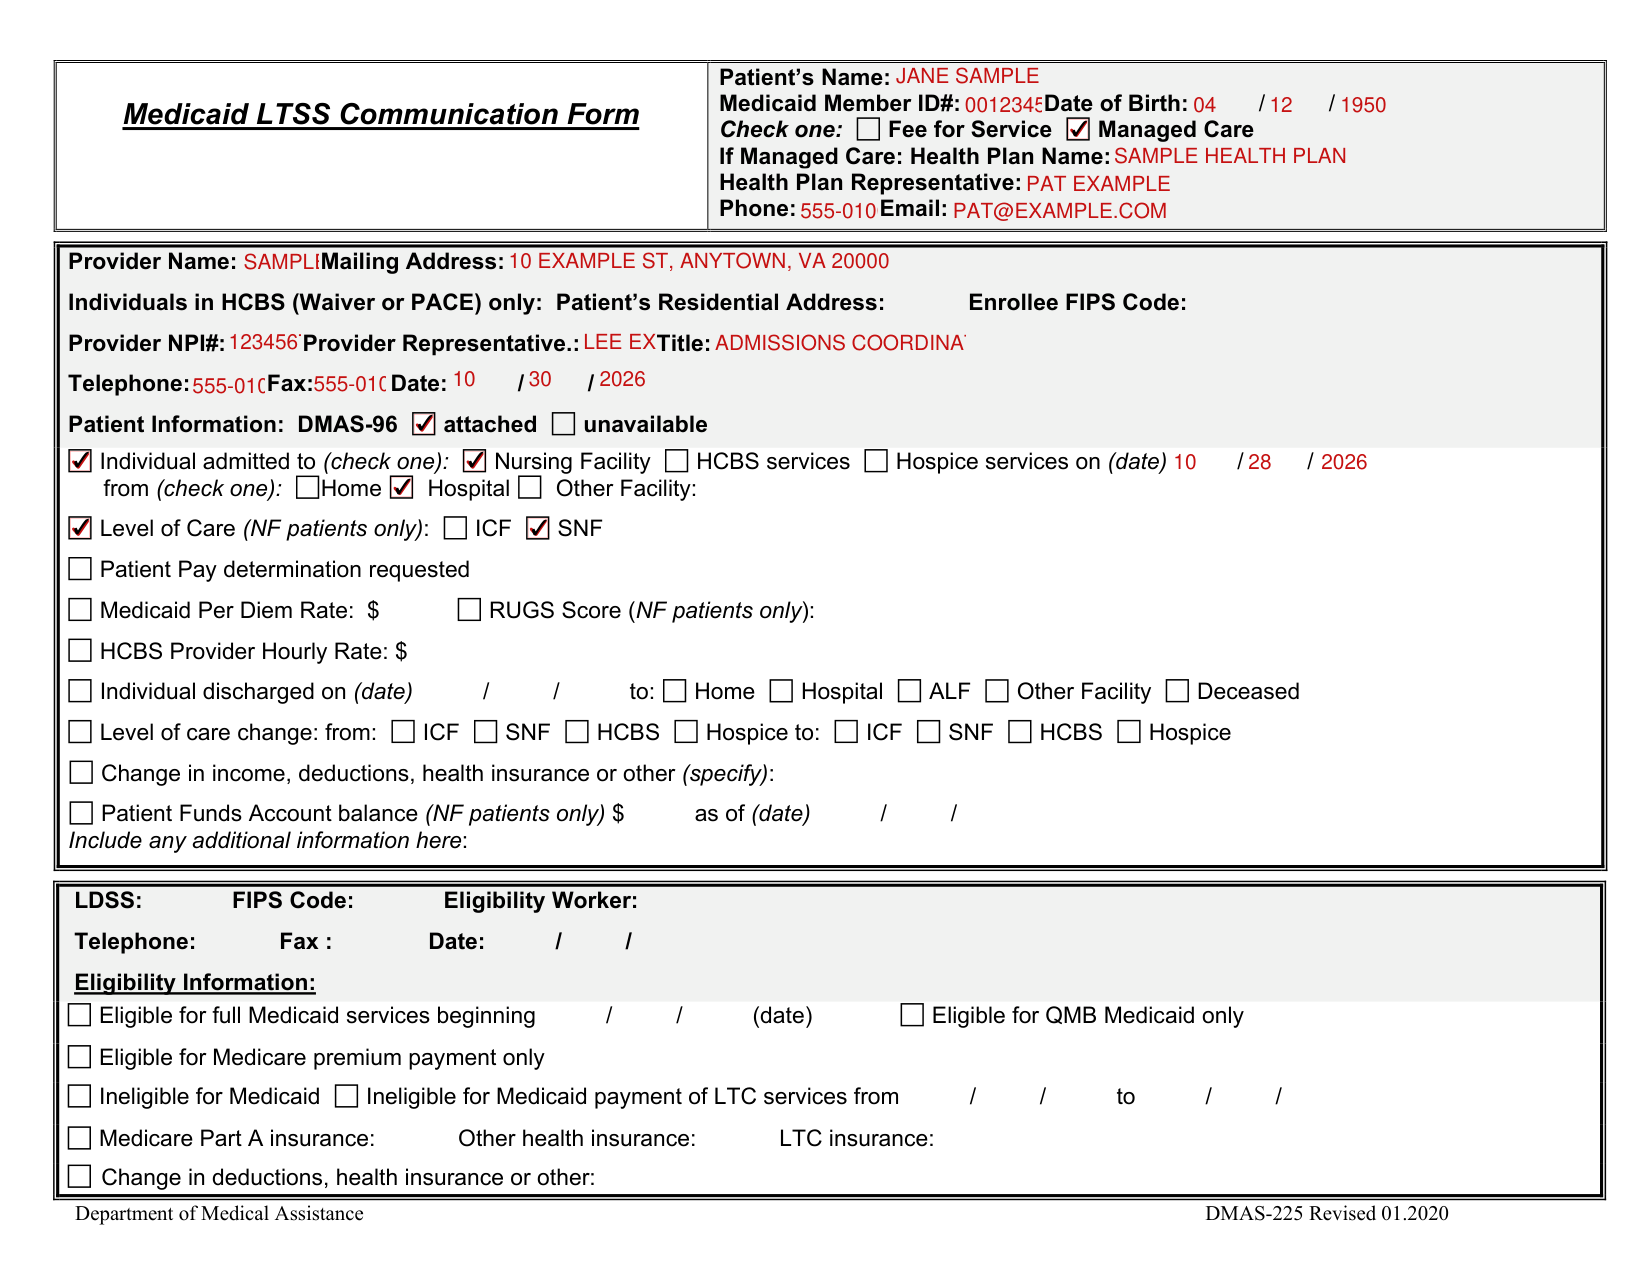
How to fill out Form DMAS-225, box by box
Individual's name, date of birth and Medicaid identification number

At the top of the form, enter the Individual's name, date of birth, and Medicaid identification number, if known.
Check one: Fee for Service or Managed Care

Check one: Fee for Service or Managed Care. If Managed Care: enter the Health Plan Name, Health Plan Representative, Phone and Email.
Provider Name, Mailing Address and Provider Representative

Complete either the Provider/Contractor or LDSS section as appropriate. In either section, complete all data elements of the gray section, then check the appropriate boxes and complete all data elements in the white section as appropriate to the individual's circumstances.
Enter the Provider Name, Mailing Address, Provider NPI#, Provider Representative, Title, Telephone, Fax and Date.
Individuals in HCBS (Waiver or PACE) only: Patient's Residential Address and Enrollee FIPS Code

Individuals in HCBS (Waiver or PACE) only: Patient's Residential Address and Enrollee FIPS Code.
CCC Plus Care Coordinators and waiver services providers (FFS) must advise the LDSS of the individual's residential address when different from the address from which this form originates and provide the individual FIPS code.
DMAS-96 attached or unavailable

Under Patient Information, check DMAS-96 attached or unavailable.
Individual admitted to (check one)

Individual admitted to (check one): Nursing Facility, HCBS services or Hospice services on (date), from (check one): Home, Hospital or Other Facility.
Level of Care (NF patients only)

Level of Care (NF patients only): ICF or SNF.
Patient Pay determination requested
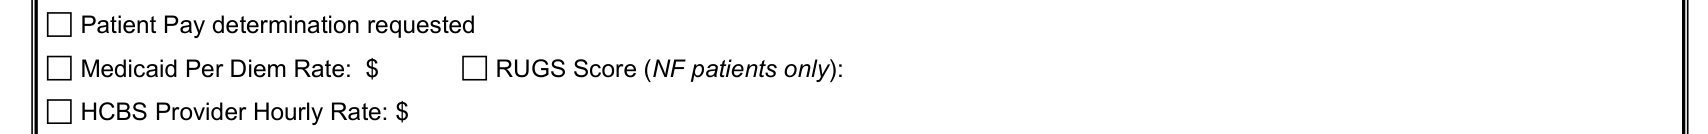
Check Patient Pay determination requested, then Medicaid Per Diem Rate, RUGS Score (NF patients only) or HCBS Provider Hourly Rate.
Providers should ensure that the individual understands that they may have a patient pay, which is the amount of their income that must be paid to the provider every month for the cost of long-term care services they receive.
Individual discharged on (date)

Individual discharged on (date) to: Home, Hospital, ALF, Other Facility or Deceased.
Level of care change
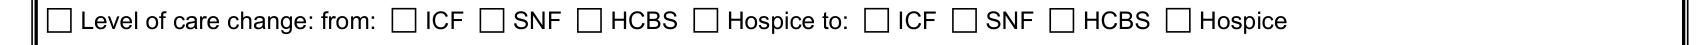
Level of care change: from ICF, SNF, HCBS or Hospice to ICF, SNF, HCBS or Hospice.
Change in income, deductions, health insurance or other (specify)

Check Change in income, deductions, health insurance or other and specify it. For NF patients only, enter the Patient Funds Account balance as of the date and include any additional information here.
LDSS, FIPS Code and Eligibility Worker
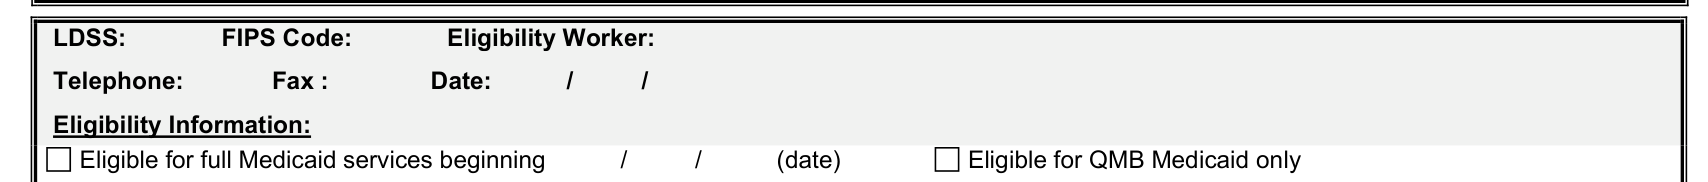
Enter LDSS, FIPS Code, Eligibility Worker, Telephone, Fax and Date.
Do not provide the source of an individual's income.
Eligibility Information

Under Eligibility Information, check Eligible for full Medicaid services beginning (date), Eligible for QMB Medicaid only or Eligible for Medicare premium payment only.
Ineligible for Medicaid

Check Ineligible for Medicaid, or Ineligible for Medicaid payment of LTC services from / / to / /.
Medicare Part A insurance, Other health insurance and LTC insurance

Enter Medicare Part A insurance, Other health insurance and LTC insurance. Check Change in deductions, health insurance or other and enter it.
More rules for Form DMAS-225
Number of copies: original and one copy for individuals in a NF; original and two copies for individuals in HCBS.
Place a copy of this form in the eligibility case file.
If your situation is different
Where to send the original
For individuals in HCBS waiver services, send the original to the following individuals: MCO Care Coordinator (for individuals in a CCC Plus MCO or other managed Medicaid plans); DMAS Case Manager (for FFS individuals with CCC Plus Waiver Tech Assisted services), DMAS, Division of Aging and Disability Services, 600 E. Broad St., Richmond, VA 23219; Service Facilitator (for FFS individuals in the CCC Plus Waiver with consumer-directed services); Personal Care Provider (for FFS patients with CCC Plus Waiver personal care services and other services); Case Manager at the Community Service Board for the Community Living and Building Independence Waivers; Support Coordinator (Case Manager) at DBHDS for the Family and Individual Supports Waiver.
For individuals in Hospice, including those in a NF or who also receive waiver services, send the original to the MCO (CCC Plus) or to the Hospice provider (FFS).
For individuals in PACE, send the original to the PACE provider.
The individual's circumstances change
A new form must be prepared by the LDSS whenever there is any change in the individual's circumstances that results in a change in eligibility status or information needs to be given to the MCO or provider.
The individual is ineligible for Medicaid payment of long-term care
If the individual is ineligible for Medicaid payment of long-term care due to imposition of a penalty period, send a copy of this form to Eligibility & Enrollment Services Division, DMAS, 600 E. Broad St., Suite 1300, Richmond, Va. 23219.
Common questions about Form DMAS-225
When is this form not the right one?
The form DMAS-225 is to be used only for individuals approved for or receiving long-term services and supports (LTSS): nursing facility (NF) care, home and community based services (HCBS waiver services or PACE) or Hospice.
Sources
[1] Medicaid LTSS Communication Form DMAS-225 (Revised 01.2020), Department of Medical Assistance Services (the Official source link on this page).
