

Form DMA-5199 at a glance
What it is: The Medicaid Renewal Request for Information Notice is the form you must complete to be considered for Medicaid or N.C. Health Choice.
Who signs: In Section 4, the Beneficiary/Authorized Representative signs: the person who completed the form or their legal representative.
In order to be considered for Medicaid or N.C. Health Choice, you must complete this form; the information will be used to verify that you and your family still qualify.
In addition to helping yourself, you can use this form to apply for health insurance coverage for other family members in your house.
A filled-in Form DMA-5199 example: a mother renews Medicaid for herself and her son

How to fill out Form DMA-5199, box by box
Section 1, tell us about yourself

In Section 1, mark Yes or No for Do you expect to file a tax return? and for Are you a dependent on someone else's tax return?; if yes, write who.
Section 2, Person 1
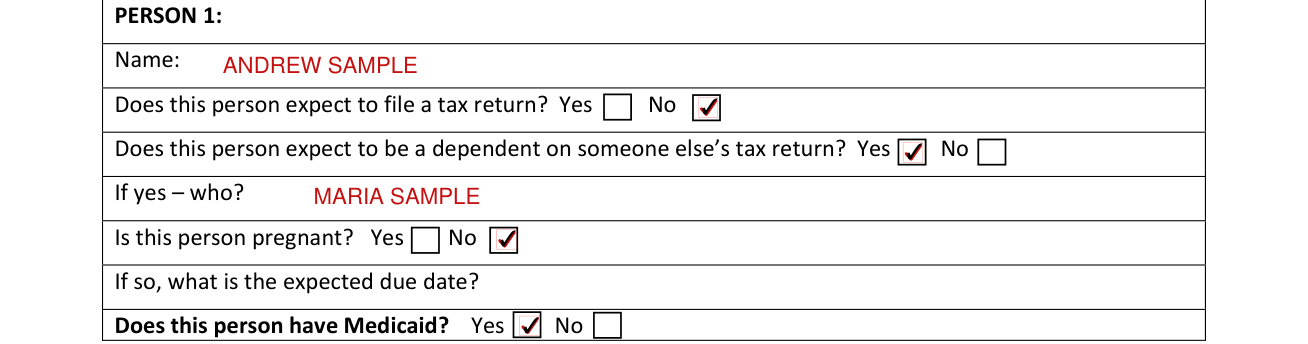
For Person 1, write the Name; mark Yes or No for Does this person expect to file a tax return?, Does this person expect to be a dependent on someone else's tax return? and Is this person pregnant?; if yes, write who; if so, write the expected due date; then mark Yes or No for Does this person have Medicaid?
If this person does not have Medicaid, complete Attachment A to apply for Medicaid.
Section 2, Persons 2 to 4
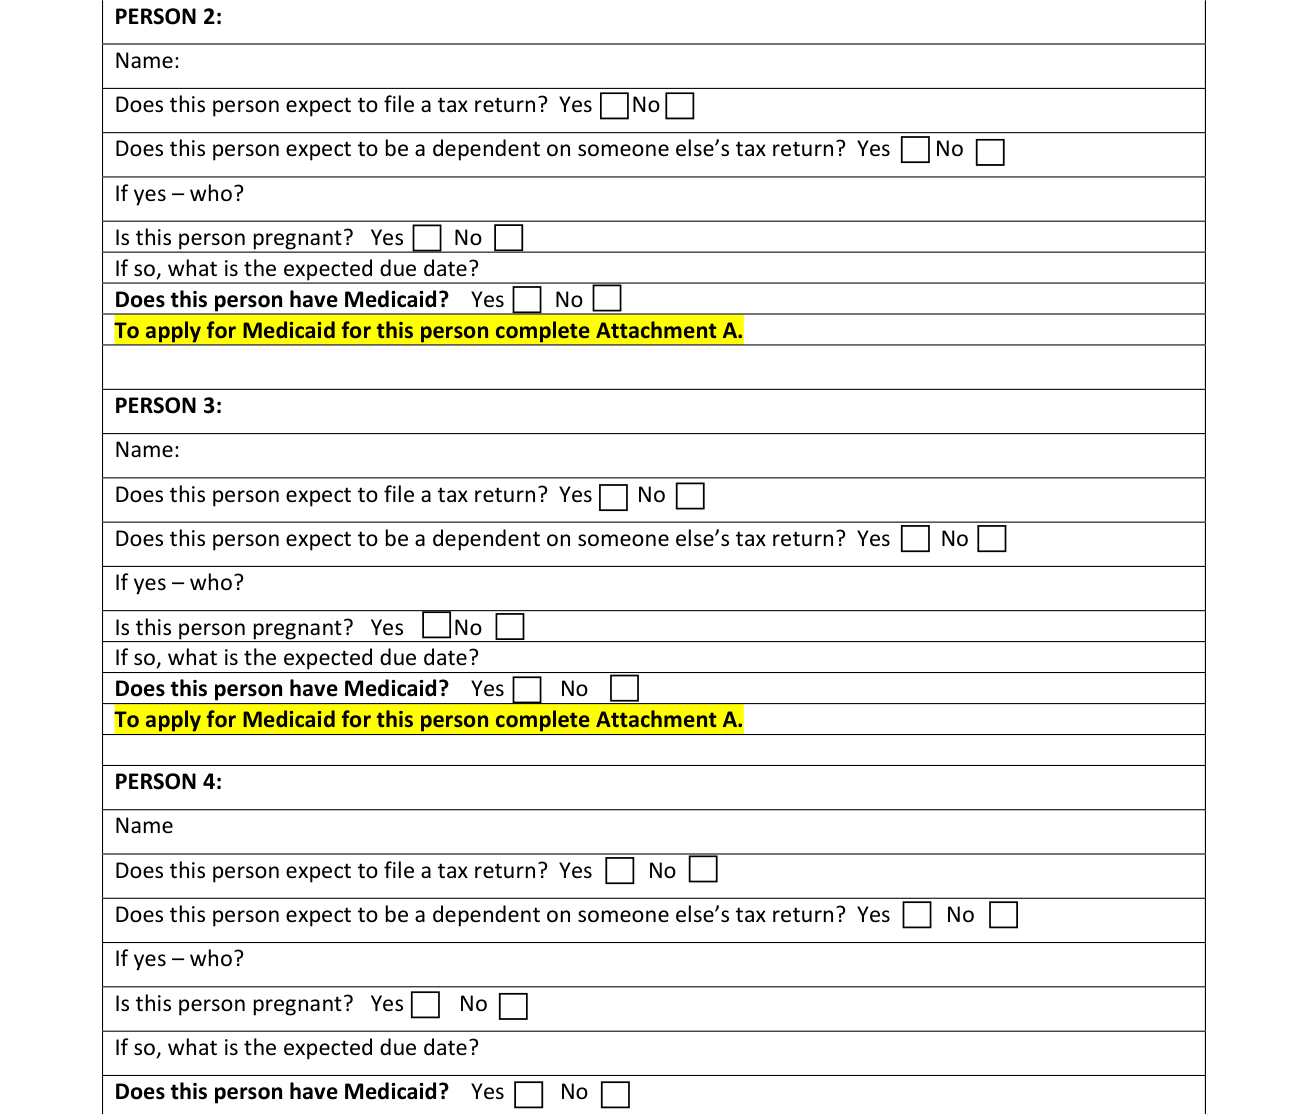
For PERSON 2, PERSON 3 and PERSON 4, write the Name and mark Yes or No for Does this person expect to file a tax return?, Does this person expect to be a dependent on someone else's tax return?, Is this person pregnant? and Does this person have Medicaid?; if yes, write who; if so, write the expected due date.
To apply for Medicaid for this person complete Attachment A.
Section 3, tell us more about the people listed
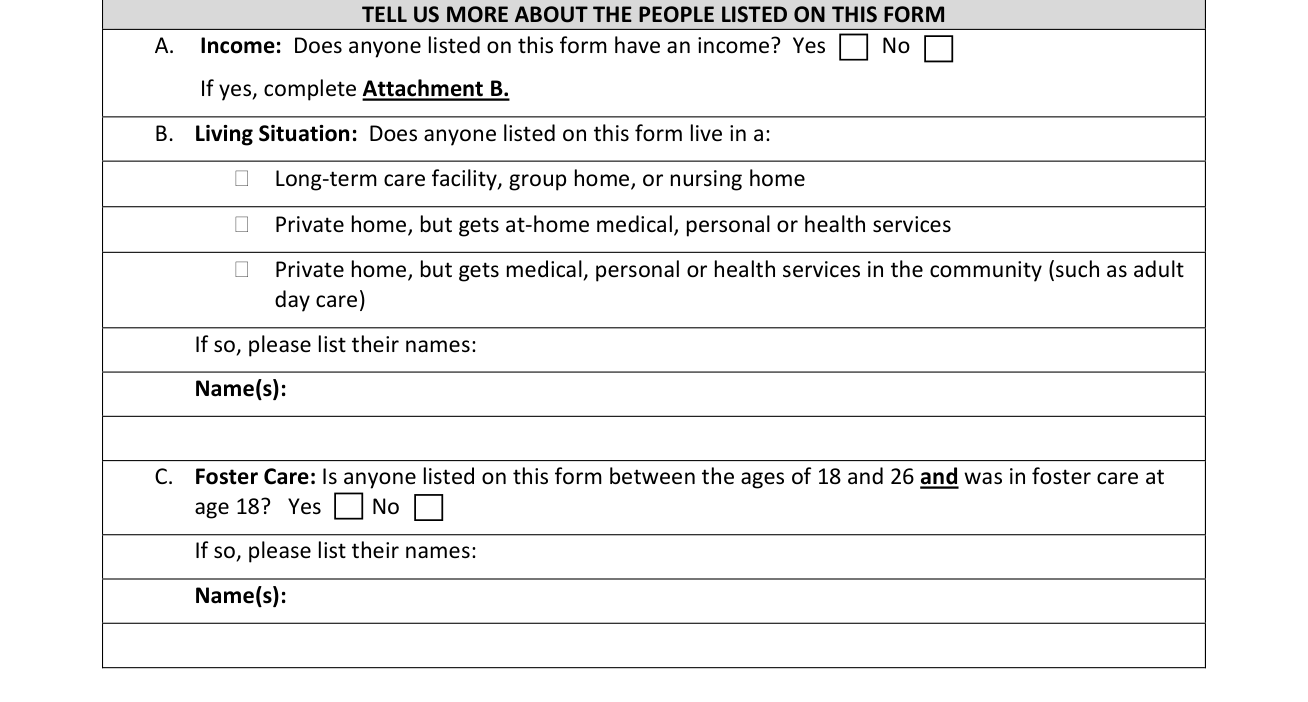
In SECTION 3, A. Income, mark Yes or No for Does anyone listed on this form have an income?; if yes, complete Attachment B.
In B. Living Situation, mark each box that applies to anyone listed on this form: a long-term care facility, group home, or nursing home; a private home, but gets at-home medical, personal or health services; or a private home, but gets medical, personal or health services in the community (such as adult day care). If so, list their names.
In C. Foster Care, mark Yes or No for Is anyone listed on this form between the ages of 18 and 26 and was in foster care at age 18?; if so, list their names.
Section 4, signature

Write the Date.
Attachment A, Person 1
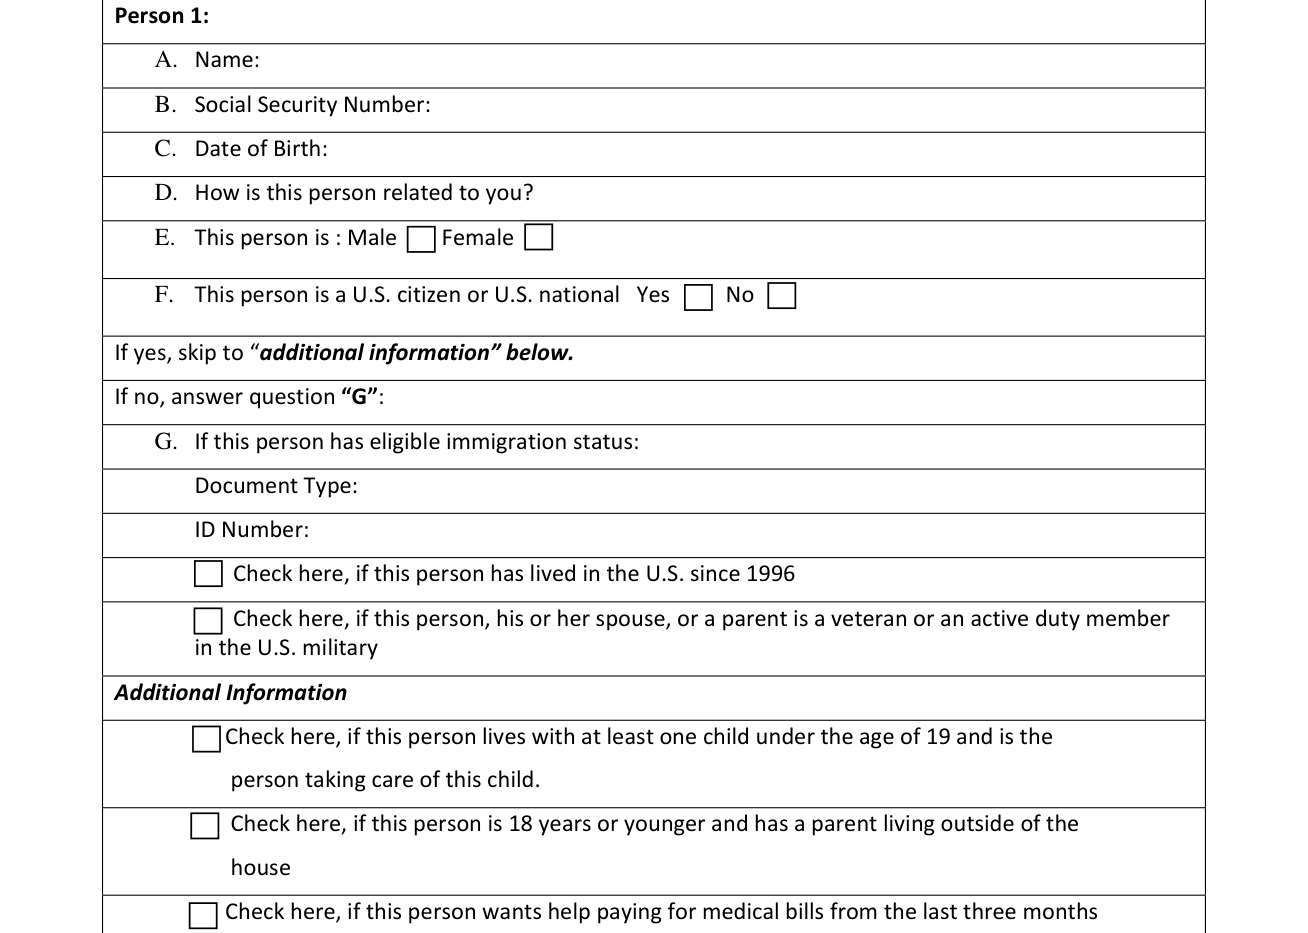
Attachment A is to apply for Medicaid for anyone listed in Section 2. For Person 1, write A. Name, B. Social Security Number, C. Date of Birth and D. how this person is related to you.
For E, mark Male or Female for This person is.
For F, mark Yes or No for This person is a U.S. citizen or U.S. national; if yes, skip to additional information, and if no, answer question G.
For G, if this person has eligible immigration status, write the Document Type and the ID Number, and check here if this person has lived in the U.S. since 1996 or if this person, his or her spouse, or a parent is a veteran or an active duty member in the U.S. military.
Under Additional Information, check here if this person lives with at least one child under the age of 19 and is the person taking care of this child; if this person is 18 years or younger and has a parent living outside of the house; or if this person wants help paying for medical bills from the last three months.
Attachment A, Person 2
For Person 2, write A. Name, B. Social Security Number, C. Date of Birth and D. how this person is related to you. Mark E. Male or Female and F. Yes or No for U.S. citizen or U.S. national. If yes, skip to Additional Information. If no, answer question G, with the Document Type and ID Number, and check here if this person has lived in the U.S. since 1996 or if this person, his or her spouse, or a parent is a veteran or an active duty member in the U.S. military.
For Person 2, under Additional Information, check here if this person lives with at least one child under the age of 19 and is the person taking care of this child. Check here if this person is 18 years or younger and has a parent living outside of the house. Check here if this person wants help paying for medical bills from the last three months.
Attachment B, income
In Attachment B, INCOME, write for each income the Person Receiving Income, Income Type, Amount Before Taxes, How Often Received and Start Date.
Include income from: Jobs, Foreign Income, Self-Employment, Investment Income or Interest, Alimony, Farming or Fishing Income, Unemployment, Rental or Royal Income, Social Security Benefits, Capital Gains, Retirement / Pension, Scholarship, Title Alien Sponsor Lump Sum Amount, American Indian / Alaskan Native Income.
Do not include Child Support, Workers Compensation, Supplemental Security Income (SSI) or Veterans Administration (VA) Benefits.
For C. Loss of Income, mark Yes or No for Was anyone listed on this form receiving income in the last 12 months but no longer is?; if yes, write who, when and what type.
D. Expenses
For D. Expenses, mark Yes or No for Is there anyone in the family deducting expenses from their taxes?; if yes, complete Expenses (Deductions) with the Person Paying Deduction, Deduction Type, Amount, How Often and Start Date.
Health Insurance and Voter Registration
For E. Health Insurance, mark Yes or No for Does anyone listed on this form have other health insurance besides Medicaid and N.C. Health Choice?; if so, complete Health Insurance with the Person Covered, Policy Holder, Policy Number, Insurance Company, Type of Coverage and Start Date.
If you are not registered to vote where you live now, mark yes or no for would you like to apply to register to vote here today; if you want to register to vote, you can complete a voter registration form at http://www.ncsbe.gov/.
More rules for Form DMA-5199
Contact the County DSS if you have any questions about filling out this form.
If more space is needed, please attach a separate sheet.
If more space is needed to report changes, attach a separate sheet.
Common questions about Form DMA-5199
Is there a deadline?
This form must be sent in by the date on the line (30 days from the Date on the form) or you may lose your N.C. Medicaid or N.C. Health Choice.
Where do I file it?
You can complete the form in person at the County DSS Office (street address), by phone, or by mail at the County DSS Office (mailing address).
Is there a penalty?
You may be subject to penalties under federal law if you provide untrue information.
What am I certifying when I sign?
In SECTION 4, by signing you are signing this renewal form under penalty of perjury, which means you have provided true answers to all the questions to the best of your knowledge.
Sources
[1] Form DMA-5199 (3/30/16), Medicaid Renewal Request for Information Notice, North Carolina Department of Health and Human Services (the Official source link on this page).
