


Form DOH-4231 at a glance
What it is: Form DOH-4231 is the New York State Department of Health Bureau of Emergency Medical Services and Trauma Systems EMT-Paramedic Recertification Continuing Education Recertification Program form.
Who signs: The applicant signs the Applicant's Printed Name, Signature and Date lines. The Medical Director, the Sponsoring Agency Contact / Coordinator, the CIC and the Skill Training Officer also sign.
A filled-in Form DOH-4231 example: an EMT-Paramedic fills out the applicant lines
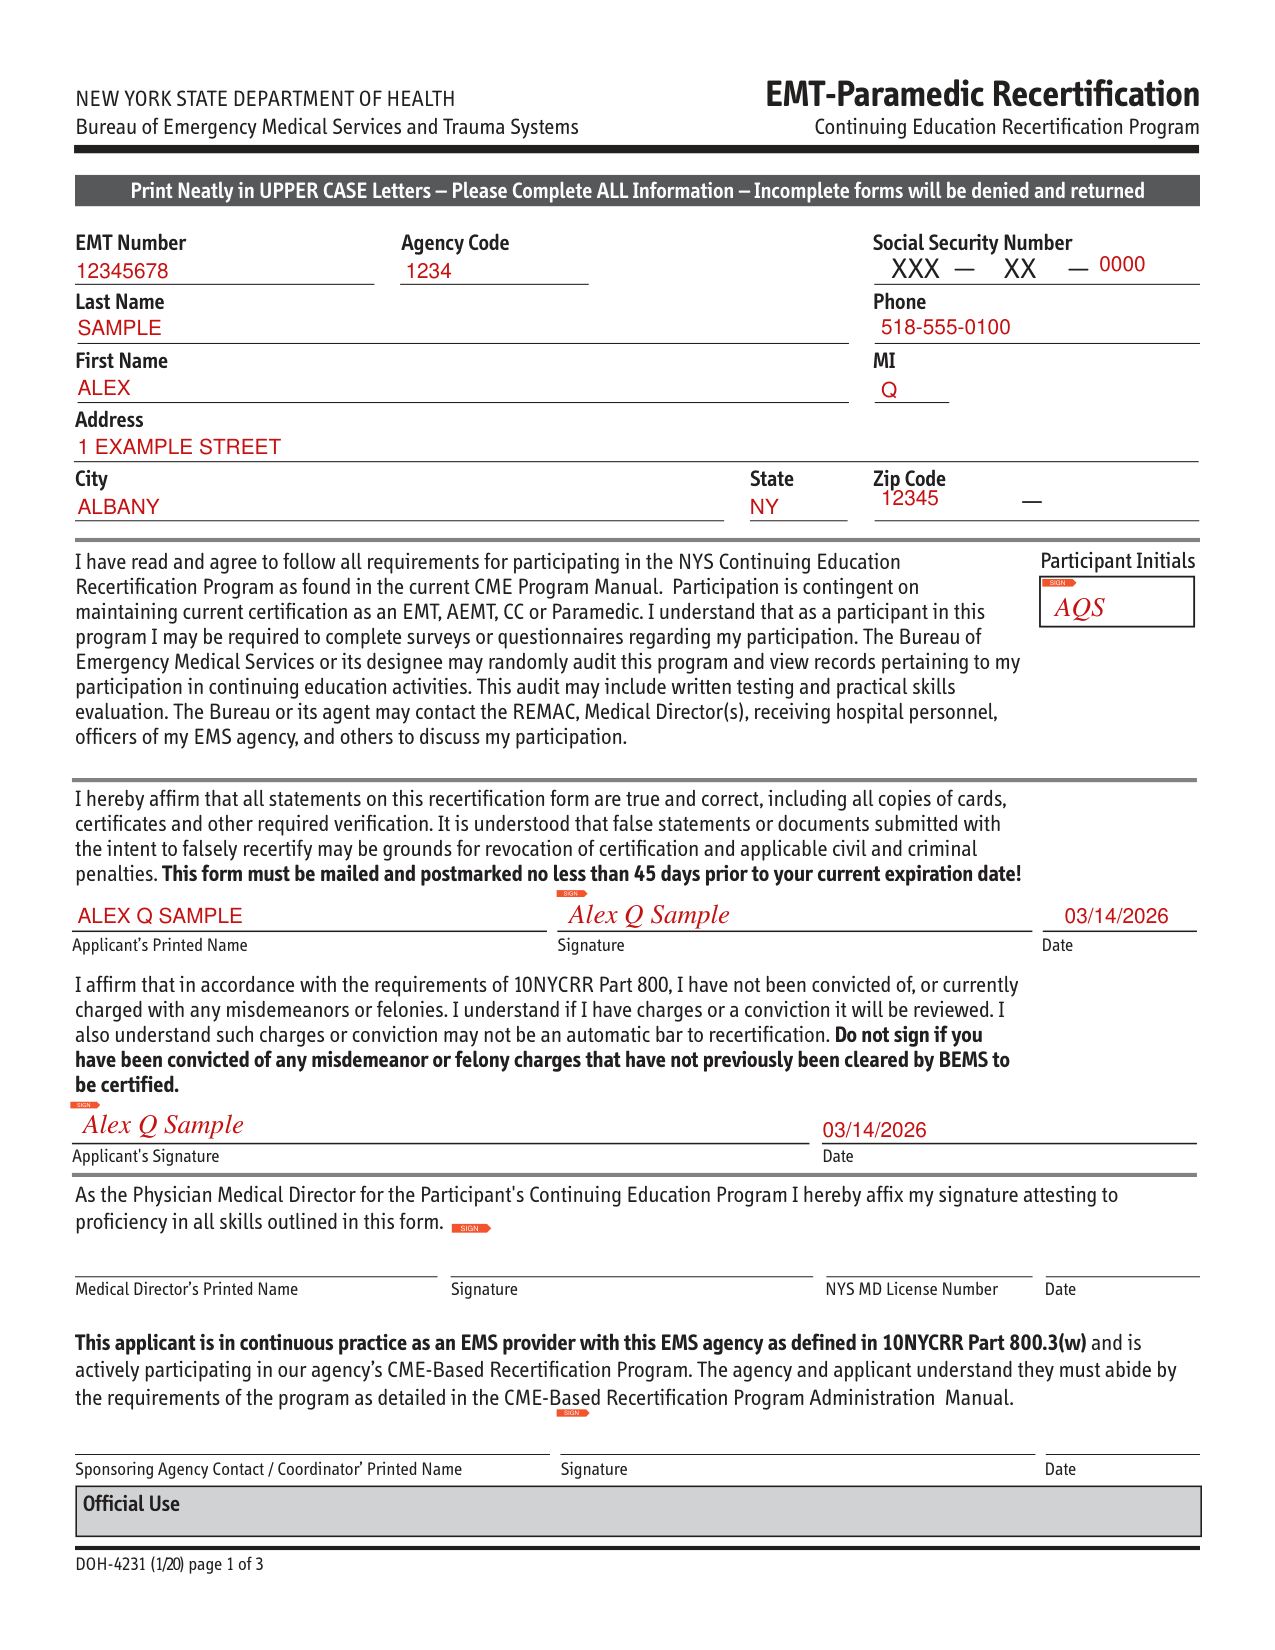
How to fill out Form DOH-4231, box by box
EMT Number, Social Security Number and Agency Code
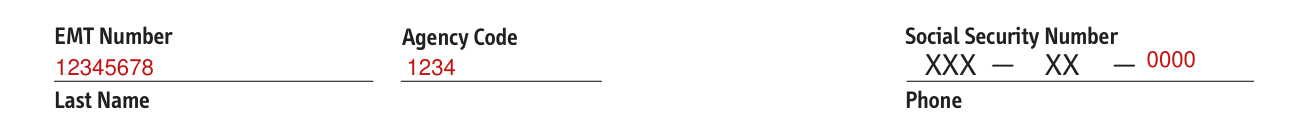
Print neatly in UPPER CASE letters. Please complete ALL information. Incomplete forms will be denied and returned.
Enter your EMT Number, Social Security Number and Agency Code.
Last Name, First Name, Address and Phone

Enter your Last Name, Phone, First Name, MI, Address, City, State and Zip Code.
Participant Initials

Write your Participant Initials to agree to follow all requirements for participating in the NYS Continuing Education Recertification Program as found in the current CME Program Manual. Participation is contingent on maintaining current certification as an EMT, AEMT, CC or Paramedic. As a participant you may be required to complete surveys or questionnaires regarding your participation. The Bureau of Emergency Medical Services or its designee may randomly audit this program and view records pertaining to your participation in continuing education activities. This audit may include written testing and practical skills evaluation. The Bureau or its agent may contact the REMAC, Medical Director(s), receiving hospital personnel, officers of your EMS agency, and others to discuss your participation.
Applicant's Printed Name, Signature and Date

This form must be mailed and postmarked no less than 45 days prior to your current expiration date.
The applicant signs the Applicant's Printed Name, Signature and Date lines.
You affirm that all statements on this recertification form are true and correct, including all copies of cards, certificates and other required verification. False statements or documents submitted with the intent to falsely recertify may be grounds for revocation of certification and applicable civil and criminal penalties.
Applicant's Signature and Date

Write the Applicant's Signature and the Date to affirm that in accordance with the requirements of 10NYCRR Part 800, you have not been convicted of, or currently charged with any misdemeanors or felonies. If you have charges or a conviction it will be reviewed. Such charges or conviction may not be an automatic bar to recertification. Do not sign if you have been convicted of any misdemeanor or felony charges that have not previously been cleared by BEMS to be certified.
Medical Director's Printed Name, Signature and NYS MD License Number

The Physician Medical Director affixes a signature attesting to proficiency in all skills outlined in this form, and writes the Medical Director's Printed Name, NYS MD License Number and Date.
Sponsoring Agency Contact / Coordinator's Printed Name, Signature and Date

The Sponsoring Agency Contact / Coordinator writes the Printed Name, Signature and Date to say this applicant is in continuous practice as an EMS provider with this EMS agency as defined in 10NYCRR Part 800.3(w) and is actively participating in the agency's CME-Based Recertification Program. The agency and applicant understand they must abide by the requirements of the program as detailed in the CME-Based Recertification Program Administration Manual.
EMT-Paramedic Refresher Training, 35 Hours
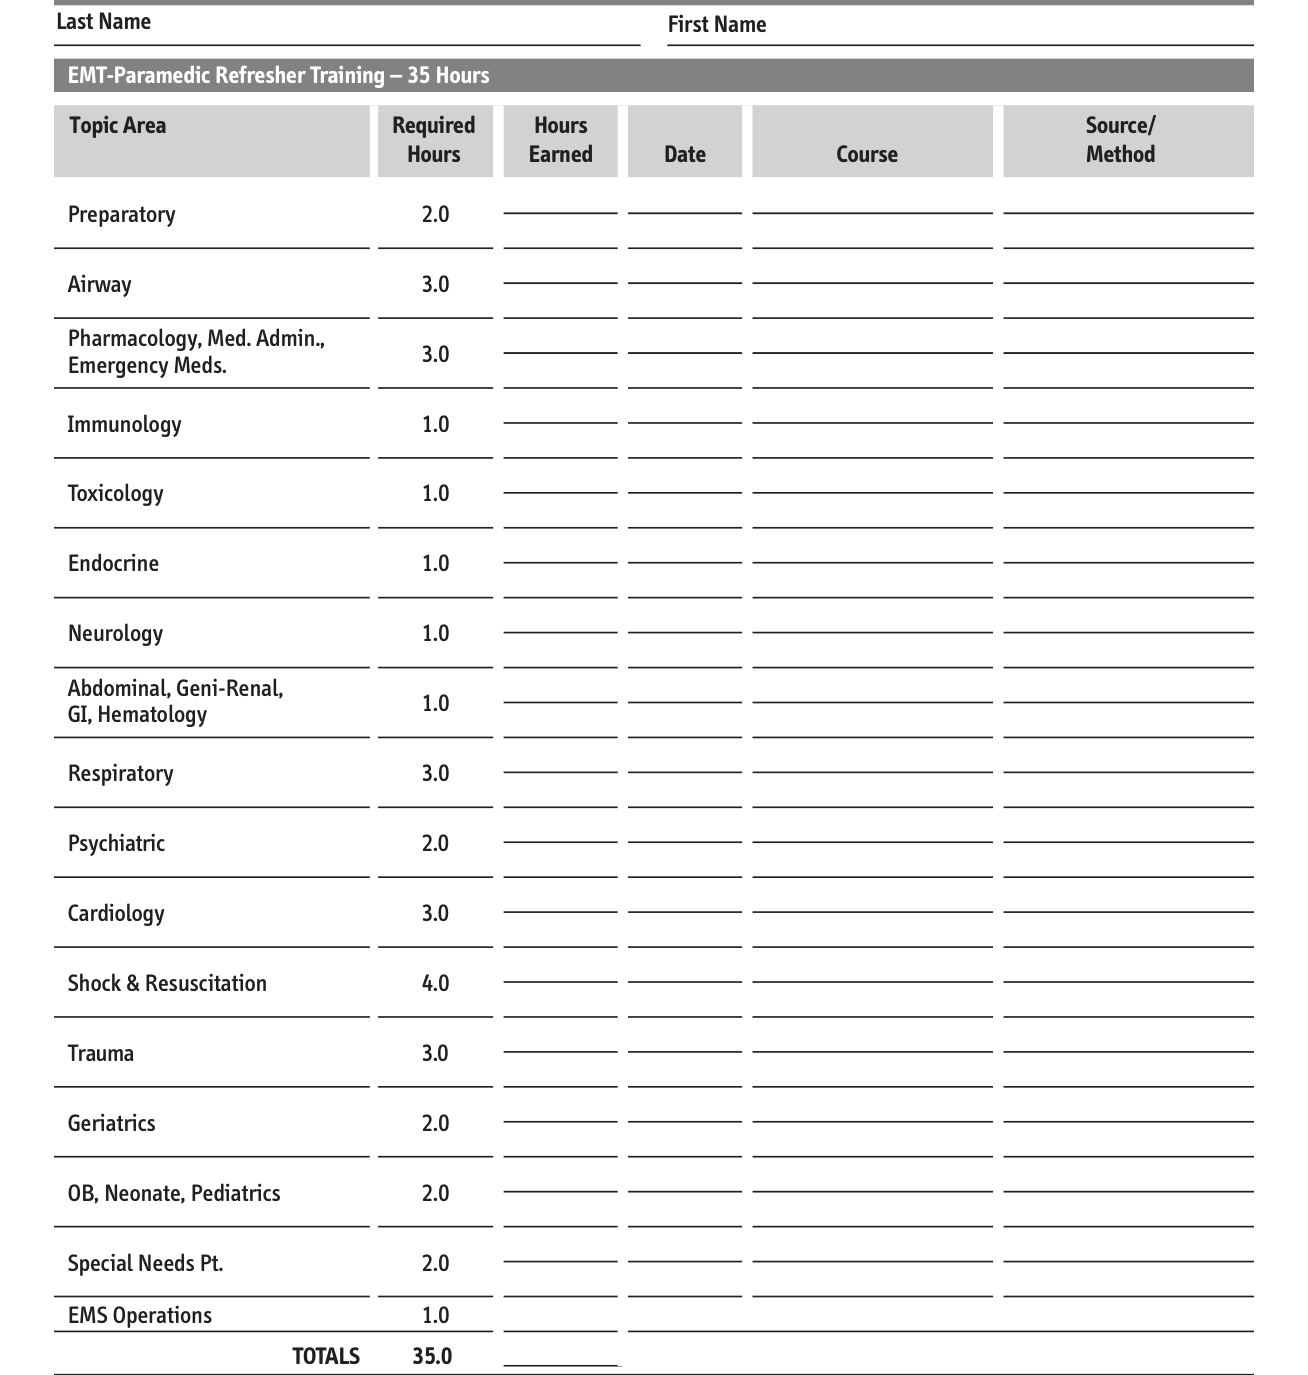
For the EMT-Paramedic Refresher Training, 35 Hours, enter Hours Earned, Date, Course and Source/ Method for each Topic Area.
Required Hours by Topic Area: Preparatory 2.0, Airway 3.0, Pharmacology, Med. Admin., Emergency Meds. 3.0, Immunology 1.0, Toxicology 1.0, Endocrine 1.0, Neurology 1.0, Abdominal, Geni-Renal, GI, Hematology 1.0, Respiratory 3.0, Psychiatric 2.0, Cardiology 3.0, Shock & Resuscitation 4.0, Trauma 3.0, Geriatrics 2.0, OB, Neonate, Pediatrics 2.0, Special Needs Pt. 2.0, EMS Operations 1.0, TOTALS 35.0.
CIC Signature, CIC Print Name and CIC Number
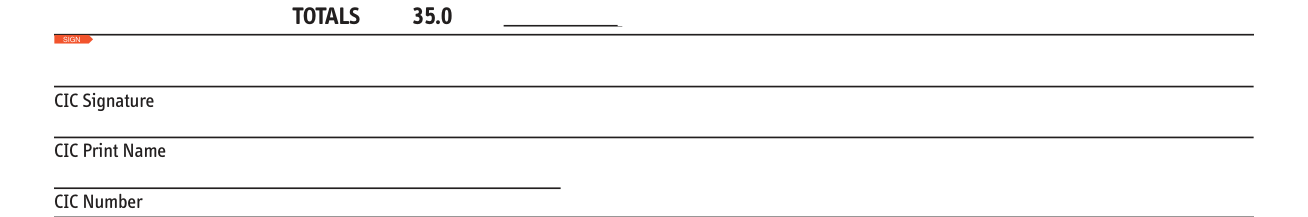
The CIC writes the CIC Signature, CIC Print Name and CIC Number.
Mandatory Topics, 5 hours
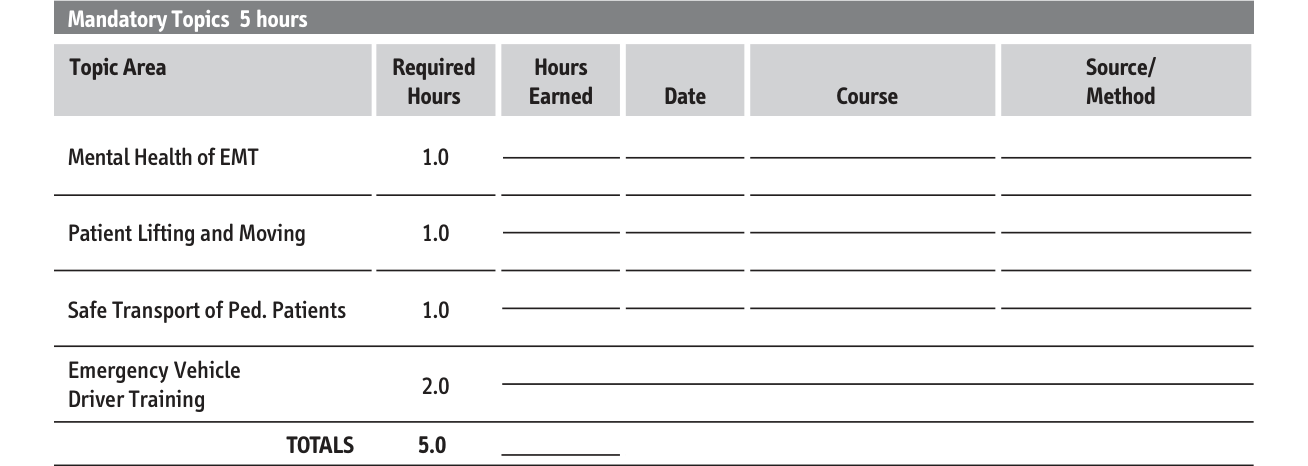
For Mandatory Topics 5 hours, enter Hours Earned, Date, Course and Source/ Method for Mental Health of EMT 1.0, Patient Lifting and Moving 1.0, Safe Transport of Ped. Patients 1.0 and Emergency Vehicle Driver Training 2.0, with TOTALS 5.0.
Additional 20 Hours of Continuing Education
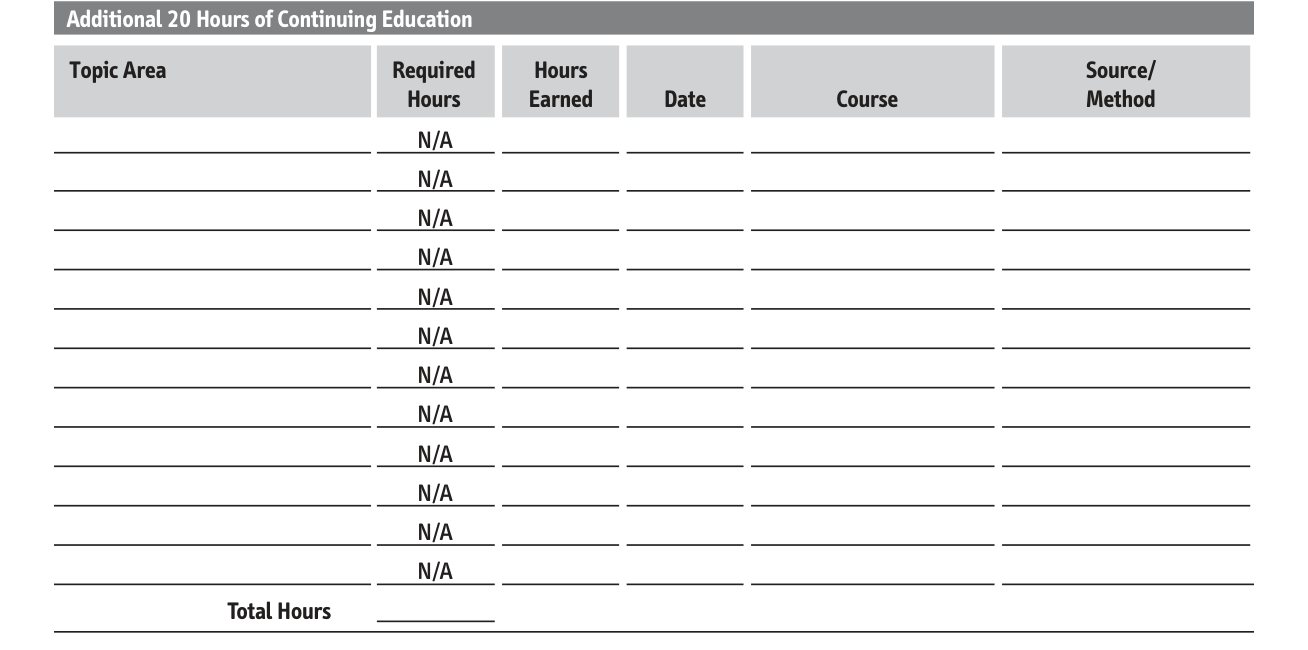
For Additional 20 Hours of Continuing Education, enter Topic Area, Hours Earned, Date, Course and Source/ Method, and the Total Hours.
CPR, ACLS and PALS, Skill Competency Verification
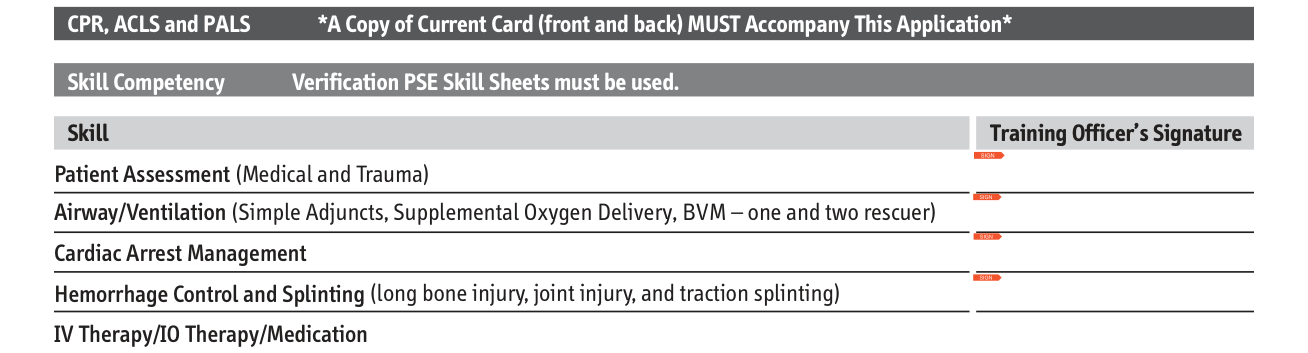
A Copy of Current Card (front and back) for CPR, ACLS and PALS MUST Accompany This Application.
For Skill Competency Verification, PSE Skill Sheets must be used.
Skill Training Officer's Signature: Patient Assessment (Medical and Trauma), Airway/Ventilation (Simple Adjuncts, Supplemental Oxygen Delivery, BVM - one and two rescuer), Cardiac Arrest Management, Hemorrhage Control and Splinting (long bone injury, joint injury, and traction splinting), IV Therapy/IO Therapy/Medication.
Sources
[1] Form DOH-4231 (1/20), EMT-Paramedic Recertification Continuing Education Recertification Program, New York State Department of Health (the Official source link on this page).