


Form DOH-2557 at a glance
What it is: Authorization for Release of Health Information and Confidential HIV-Related Information is a New York State Department of Health AIDS Institute form.
Who signs: The Signature and Date lines are for the subject of information or legally authorized representative.
A filled-in Form DOH-2557 example: a person releases her own health records

How to fill out Form DOH-2557, box by box
I consent to disclosure of (please check all that apply)

This form authorizes release of health information including HIV-related information. You may choose to release only your non-HIV health information, only your HIV-related information, or both.
Please check all that apply: My HIV-related information, My non-HIV health information, Both (non-HIV health and HIV-related information).
By checking the boxes and signing this form, health information and/or HIV-related information can be given to the people listed on page two (and on additional sheets if necessary) of the form, for the reason(s) listed. Upon your request, the facility or person disclosing your health information must provide you with a copy of this form.
Under New York State Law HIV-related information can only be given to people you allow to have it by signing a written release. This information may also be released to the following: health providers caring for you or your exposed child; health officials when required by law; insurers to permit payment; persons involved in foster care or adoption; official correctional, probation and parole staff; emergency or health care staff who are accidentally exposed to your blood; or by special court order. Under New York State law, anyone who illegally discloses HIV-related information may be punished by a fine of up to $5,000 and a jail term of up to one year (checked November 8, 2026). However, some re-disclosures of health and/or HIV-related information are not protected under federal law. For more information about HIV confidentiality, call the New York State Department of Health HIV Confidentiality Hotline at 1-800-962-5065; for more information regarding federal privacy protection, call the Office for Civil Rights at 1-800-368-1019. You may also contact the NYS Division of Human Rights at 1-888-392-3644.
This Authorization for Release of Health Information and Confidential HIV-Related Information form is HIPAA compliant. If releasing only non-HIV related health information, you may use this form or another HIPAA-compliant general health release form.
Name and address of facility/person disclosing HIV-related information

Enter the name and address of the facility/person disclosing HIV-related information.
Name of person whose information will be released

Enter the name of the person whose information will be released.
Name and address of person signing this form (if other than above)

Enter the name and address of the person signing this form, if other than the person whose information will be released.
If a person other than the person whose information will be released signs, enter the relationship to the person whose information will be released.
Describe information to be released and the reason for release

Describe the information to be released.
Enter the reason for release of information.
Time Period During Which Release of Information is Authorized

Enter the time period during which release of information is authorized: From and To.
Exceptions to the right to revoke consent, if any

Enter the exceptions to the right to revoke consent, if any.
Description of the consequences, if any, of failing to consent to disclosure

Describe the consequences, if any, of failing to consent to disclosure upon treatment, payment, enrollment, or eligibility for benefits (Note: Federal privacy regulations may restrict some consequences).
Sign below only to authorize all facilities/persons to share information

Sign the Signature and Date lines only if you wish to authorize all facilities/persons listed on pages 1 and 2 (and 3 if used) of this form to share information among and between themselves for the purpose of providing health care and services.
Name and address of facility/person to be given general health and/or HIV-related information
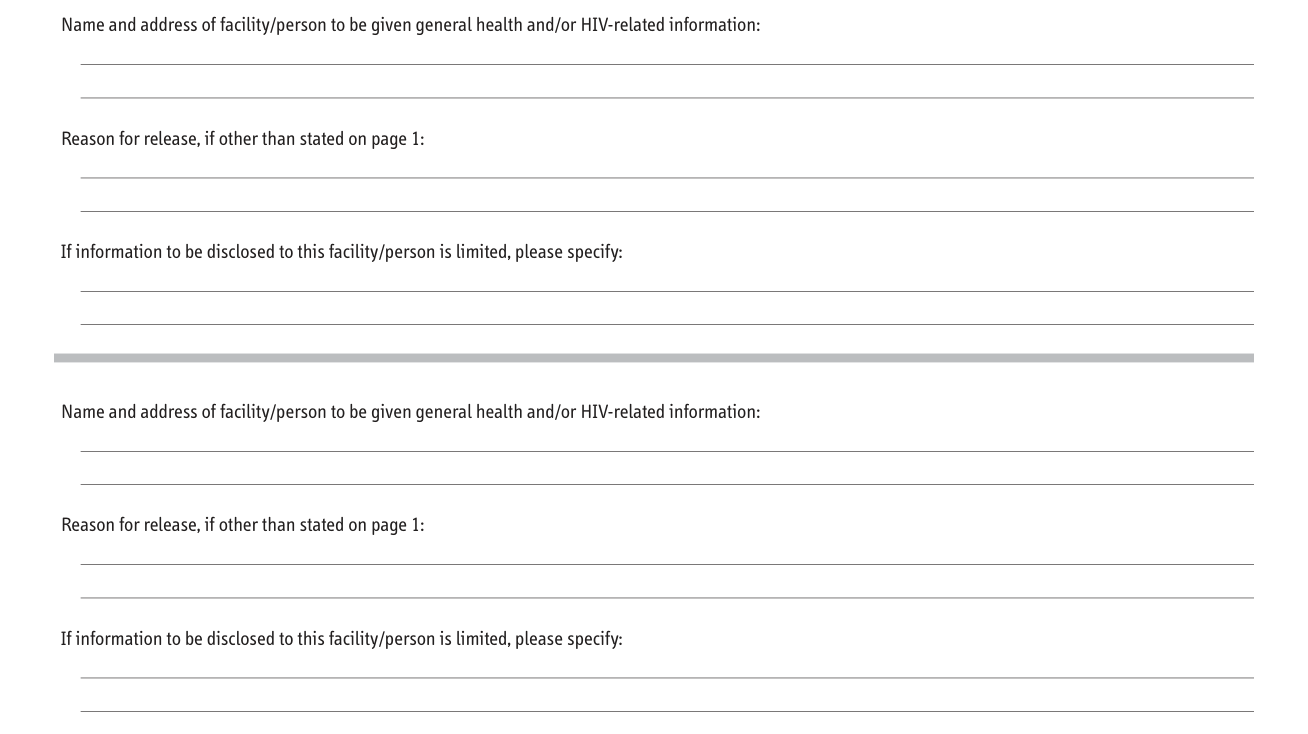
Complete information for each facility/person to be given general information and/or HIV-related information.
Enter the name and address of the facility/person to be given general health and/or HIV-related information.
Enter the reason for release, if other than stated on page 1.
If information to be disclosed to this facility/person is limited, please specify.
Attach additional sheets as necessary. It is recommended that blank lines be crossed out prior to signing.
Signature Date (Subject of Information or Legally Authorized Representative)

I authorize the facility/person noted on page one to release health and/or HIV-related information of the person named on page one to the organizations/persons listed.
I know that I do not have to allow release of my health and/or HIV-related information, and that I can change my mind at any time and revoke my authorization by writing the facility/person obtaining this release.
My questions about this form have been answered.
Sign the Signature and Date lines as the subject of information or legally authorized representative; if legal representative, indicate relationship to subject.
Enter the Print Name and the Client/Patient Number.
If any/all of this page is completed, please sign below

If any/all of page 3 is completed, sign the Signature and Date lines of page 3.
More rules for Form DOH-2557
The law protects you from HIV-related discrimination in housing, employment, health care and other services.
For more information, call the New York City Commission on Human Rights at (212) 306-7500 or the NYS Division of Human Rights at 1-888-392-3644.
Sources
[1] Form DOH-2557 (2/11), Authorization for Release of Health Information and Confidential HIV-Related Information, New York State Department of Health AIDS Institute (the Official source link on this page).