


Form DOH-5032 at a glance
What it is: DOH-5032 is the New York State Department of Health Authorization for Release of Health Information (Including Alcohol/Drug Treatment and Mental Health Information) and Confidential HIV/AIDS-related Information.
Who signs: The SIGNATURE OF PATIENT OR REPRESENTATIVE AUTHORIZED BY LAW signs the form.
A filled-in Form DOH-5032 example: a patient releases all her health information
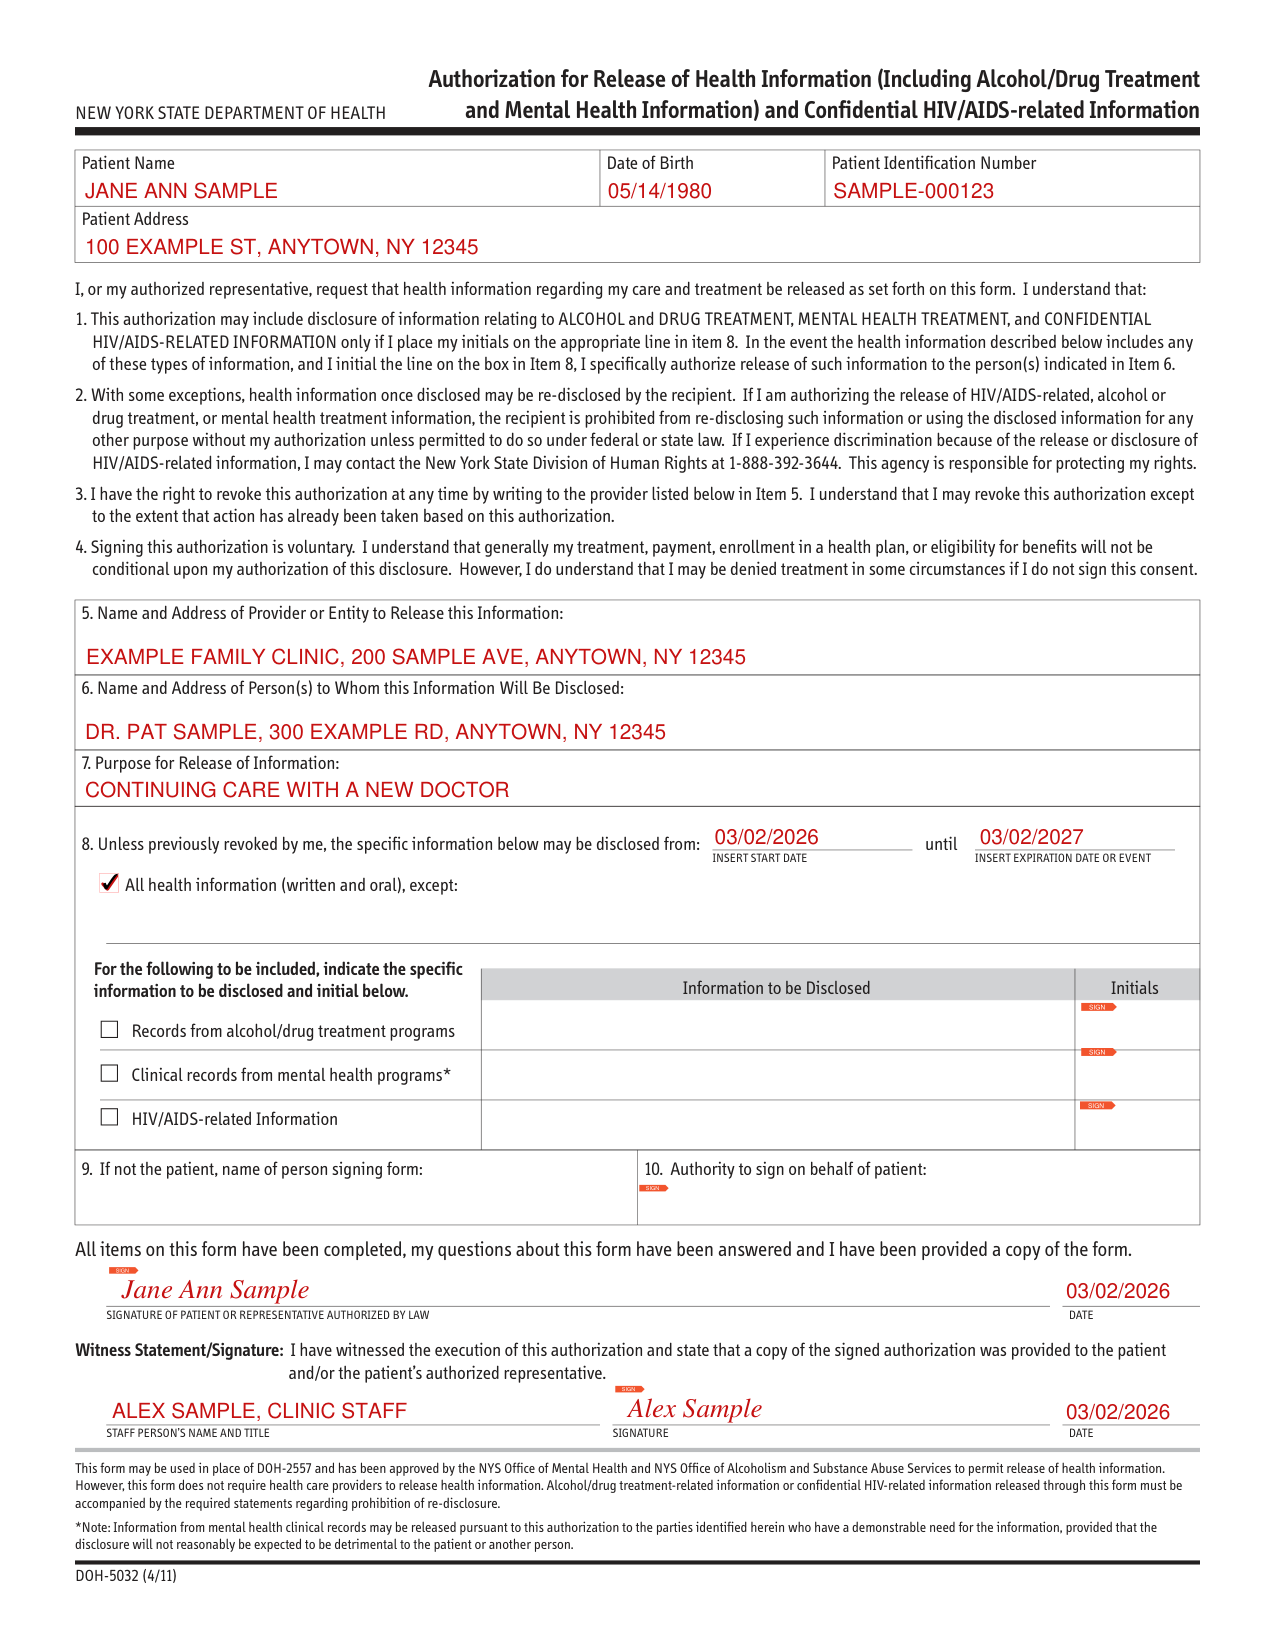
How to fill out Form DOH-5032, box by box
Patient Name, Date of Birth, Patient Identification Number and Patient Address
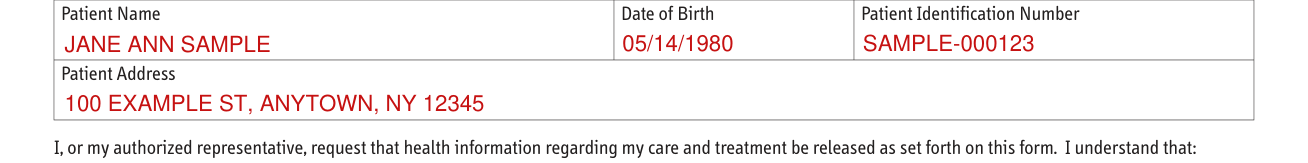
Enter the Patient Name, Date of Birth and Patient Identification Number.
Enter the Patient Address.
Provider or Entity, Person(s) to Whom this Information Will Be Disclosed and Purpose for Release of Information

Enter the Name and Address of Provider or Entity to Release this Information (5).
Enter the Name and Address of Person(s) to Whom this Information Will Be Disclosed (6).
Enter the Purpose for Release of Information (7).
Item 8: the information to be disclosed
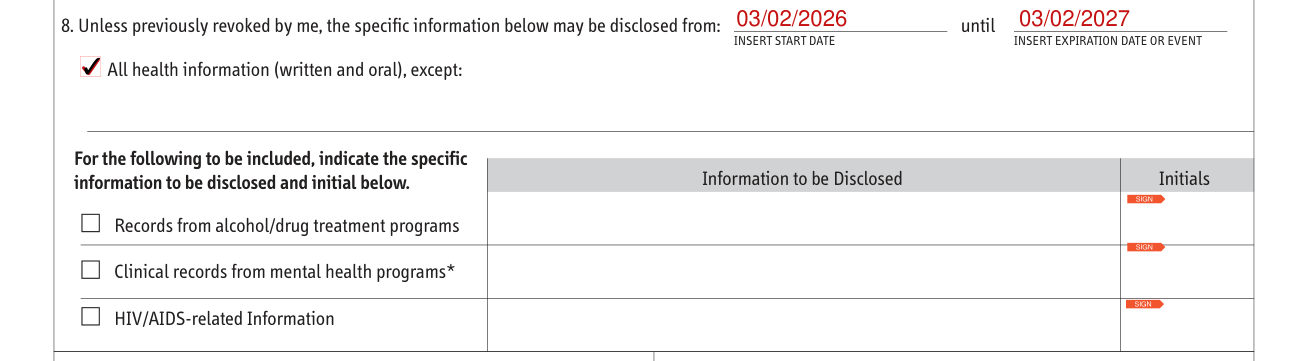
(8) Unless previously revoked, the specific information may be disclosed from the INSERT START DATE until the INSERT EXPIRATION DATE OR EVENT.
Check the box for All health information (written and oral), except.
Alcohol and drug treatment, mental health treatment, and confidential HIV/AIDS-related information may be disclosed only if you place your initials on the appropriate line in item 8. For the following to be included, indicate the specific information to be disclosed and initial it under Initials.
The lines are Records from alcohol/drug treatment programs, Clinical records from mental health programs and HIV/AIDS-related Information.
Information from mental health clinical records may be released pursuant to this authorization to the parties identified herein who have a demonstrable need for the information, provided that the disclosure will not reasonably be expected to be detrimental to the patient or another person.
If not the patient, name of person signing form and authority to sign on behalf of patient

If not the patient, enter the name of person signing form (9) and the Authority to sign on behalf of patient (10).
Signature of patient or representative authorized by law

Sign on the line for SIGNATURE OF PATIENT OR REPRESENTATIVE AUTHORIZED BY LAW and enter the DATE. All items on this form have been completed, your questions about this form have been answered and you have been provided a copy of the form.
Witness statement

Witness Statement/Signature: the witness has witnessed the execution of this authorization and states that a copy of the signed authorization was provided to the patient and/or the patient's authorized representative. The staff person enters the STAFF PERSON'S NAME AND TITLE, signs on the SIGNATURE line and enters the DATE.
More rules for Form DOH-5032
This form may be used in place of DOH-2557 and has been approved by the NYS Office of Mental Health and NYS Office of Alcoholism and Substance Abuse Services to permit release of health information. However, this form does not require health care providers to release health information. Alcohol/drug treatment-related information or confidential HIV-related information released through this form must be accompanied by the required statements regarding prohibition of re-disclosure.
You, or your authorized representative, request that health information regarding your care and treatment be released as set forth on this form.
You have the right to revoke this authorization at any time by writing to the provider listed below in Item 5, except to the extent that action has already been taken based on this authorization.
Signing this authorization is voluntary. Generally, treatment, payment, enrollment in a health plan, or eligibility for benefits will not be conditional upon authorization of this disclosure. However, you may be denied treatment in some circumstances if you do not sign this consent.
Sources
[1] Form DOH-5032 (4/11), Authorization for Release of Health Information, New York State Department of Health (the Official source link on this page).