

ODM 00202 Employee Call-Off Sheet at a glance
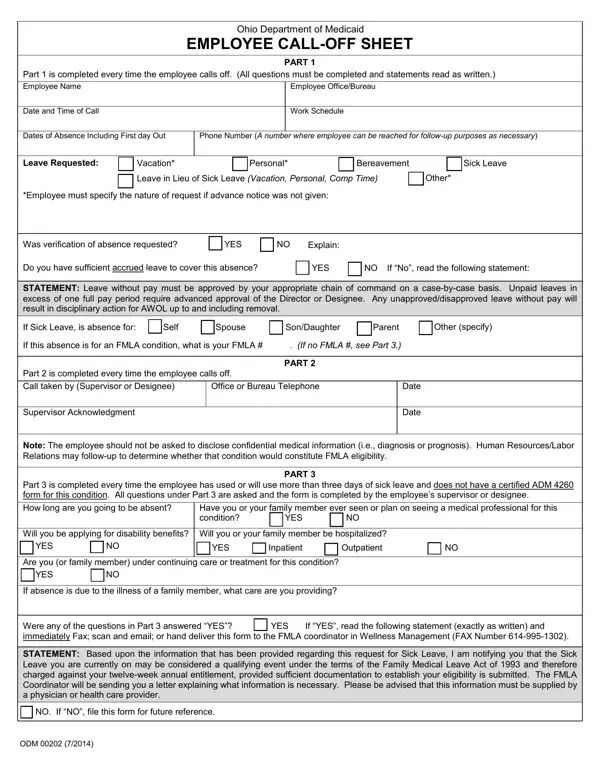
What it is: Ohio Department of Medicaid Employee Call-Off Sheet: Part 1 is completed every time the employee calls off.
Where and when to file: Were any of the questions in Part 3 answered “YES”? If “YES”, read the following statement (exactly as written) and immediately Fax; scan and email; or hand deliver this form to the FMLA coordinator in Wellness Management (FAX Number 614-995-1302).
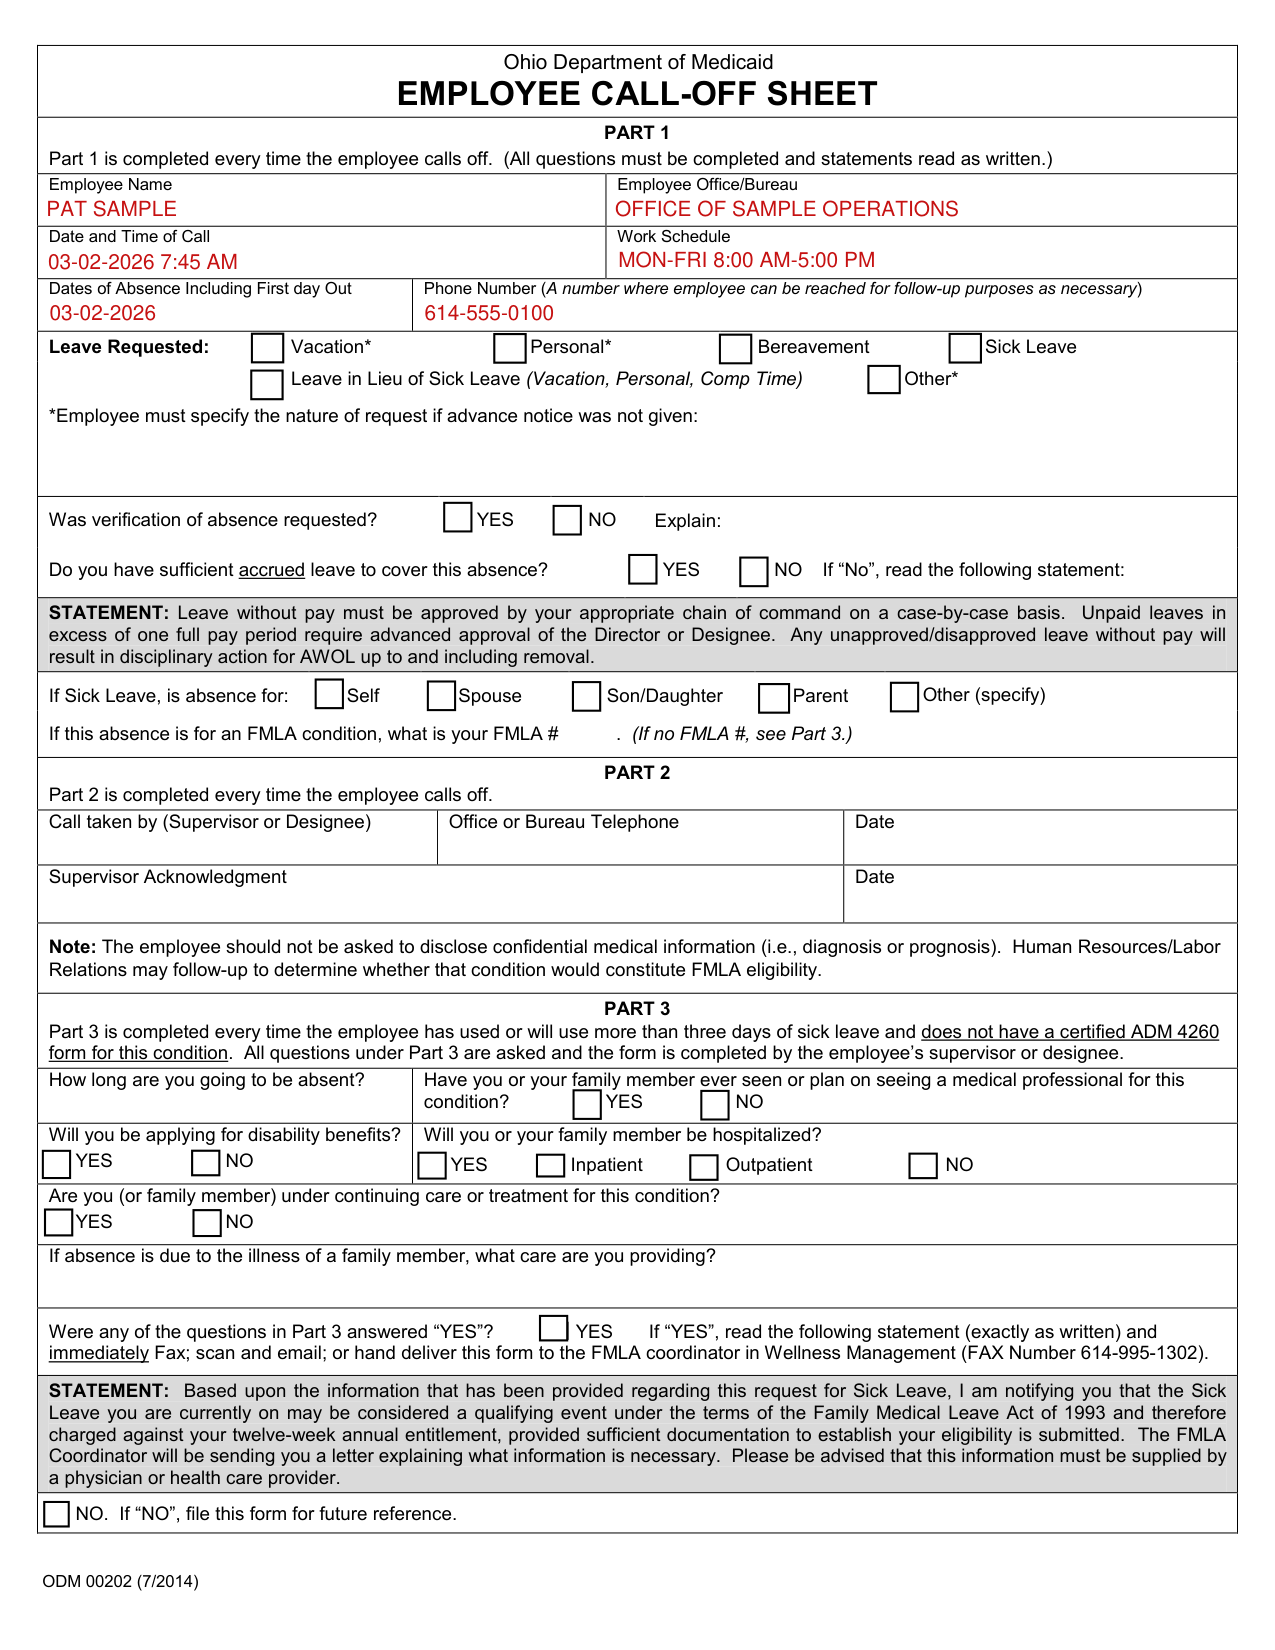
A filled-in ODM 00202 Employee Call-Off Sheet example: an employee calls off sick
How to fill out ODM 00202 Employee Call-Off Sheet, box by box
Part 1: employee, dates and phone

All questions must be completed and statements read as written.
Enter the Employee Name, Employee Office/Bureau, Date and Time of Call, Work Schedule and Dates of Absence Including First day Out, and a Phone Number (a number where employee can be reached for follow-up purposes as necessary).
Leave Requested

Leave Requested: Vacation*, Personal*, Bereavement, Sick Leave, Leave in Lieu of Sick Leave (Vacation, Personal, Comp Time) or Other*. For Vacation*, Personal* and Other*, *Employee must specify the nature of request if advance notice was not given.
Verification of absence and accrued leave

Was verification of absence requested? YES or NO. Explain.
Do you have sufficient accrued leave to cover this absence? YES or NO. If “No”, read the following statement.
Leave without pay must be approved by your appropriate chain of command on a case-by-case basis. Unpaid leaves in excess of one full pay period require advanced approval of the Director or Designee. Any unapproved/disapproved leave without pay will result in disciplinary action for AWOL up to and including removal.
If Sick Leave: whose absence and FMLA number

If Sick Leave, is absence for: Self, Spouse, Son/Daughter, Parent or Other (specify)?
If this absence is for an FMLA condition, what is your FMLA #? If no FMLA #, see Part 3.
Part 2: call taken by

Part 2 is completed every time the employee calls off. Call taken by (Supervisor or Designee).
Enter the Date, the Supervisor Acknowledgment and the Office or Bureau Telephone.
Note: The employee should not be asked to disclose confidential medical information (i.e., diagnosis or prognosis). Human Resources/Labor Relations may follow-up to determine whether that condition would constitute FMLA eligibility.
Part 3: more than three days of sick leave

Part 3 is completed every time the employee has used or will use more than three days of sick leave and does not have a certified ADM 4260 form for this condition. All questions under Part 3 are asked and the form is completed by the employee's supervisor or designee. How long are you going to be absent?
Ask: Have you or your family member ever seen or plan on seeing a medical professional for this condition? YES or NO. Will you be applying for disability benefits? YES or NO.
Will you or your family member be hospitalized? Mark YES with Inpatient or Outpatient, or NO.
Are you (or family member) under continuing care or treatment for this condition? YES or NO.
If absence is due to the illness of a family member, what care are you providing?
After Part 3: the statement and file
STATEMENT: Based upon the information that has been provided regarding this request for Sick Leave, I am notifying you that the Sick Leave you are currently on may be considered a qualifying event under the terms of the Family Medical Leave Act of 1993 and therefore charged against your twelve-week annual entitlement, provided sufficient documentation to establish your eligibility is submitted. The FMLA Coordinator will be sending you a letter explaining what information is necessary. Please be advised that this information must be supplied by a physician or health care provider.
If “NO”, file this form for future reference.
Sources
[1] Ohio Department of Medicaid Employee Call-Off Sheet, ODM 00202 (7/2014) (the Official source link on this page).