
Express Scripts Androgel PDF Details

The Express Scripts Androgel form represents a critical tool in the patient care process, functioning as a prior authorization form that meticulously outlines the necessity for thorough assessment before Androgel, a medication used primarily in the treatment of specific medical conditions, is dispensed. This form, emphasizing the importance of detailed patient and prescriber information, lays the groundwork for a systematic review based on Express Scripts' standard criteria, acknowledging, however, that not all patients' situations or health plans may align strictly with these standards. It includes fields for patient demographics, detailed prescriber credentials, diagnostic information, and a clear request for the specific medication and dosage, along with a record of any past medications or therapies that have been attempted. Given the nuances of individual health benefits plans, the form also prepares the submitter for the possible need for additional information to support the prior authorization process. Furthermore, the inclusion of contact details for urgent requests underscores the form’s role in facilitating timely access to necessary treatments. It also serves a dual function as a safeguard for personal health information, underscoring the confidentiality and the critical nature of the data being handled. Despite its utility, the form also carries a reminder that it does not replace the professional medical judgment of the treating physician, who ultimately determines the appropriateness of the medication for the patient. In essence, the Express Scripts Androgel prior authorization form is a fundamental component in the intersection of healthcare management, patient care, and regulatory compliance, requiring accurate, comprehensive information to ensure that patients receive the medications they need while adhering to the constraints of their health plan’s coverage.

QuestionAnswer
Form NameExpress Scripts Androgel
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesexpress scripts tier exception, express scripts medicare tier exception form, expressscript, express scripts tier exception form

How to Fill Out Prior Authorization Form General Request Form

Prior Authorization Form General Request Form at a glance

What it is: The Prior Authorization Form General Request Form is based on Express Scripts standard criteria and may not be applicable to all patients.

Who signs: Under SIGN, enter the Prescriber Signature and the Date.

A filled-in Prior Authorization Form General Request Form example: a prescriber requests a prior authorization

Prior Authorization Form General Request Form example filled out, example: a prescriber requests a prior authorization
A prescriber's office fills out the Prior Authorization Form for one patient. Dr. Ann Sample requests 30 units for a 30 days supply, and one line is enough for Other Medications, so the later lines stay empty. The picture shows the filled form, and none of its entries is real.

How to fill out Prior Authorization Form General Request Form, box by box

Patient Information

Prior Authorization Form General Request Form example filled out, patient Information

Under Patient Information, enter the Patient First Name and the Patient Last Name.

Enter the Patient ID# and the Patient DOB.

Enter the Patient Phone #.

Prescriber Information

Prior Authorization Form General Request Form example filled out, prescriber Information

Under Prescriber Information, enter the Prescriber Name and the Prescriber DEA/NPI (required).

Enter the Prescriber Phone # and the Prescriber Fax #.

Enter the Prescriber Address, the State and the Zip Code.

Diagnosis, the drug requested and Other Medications tried
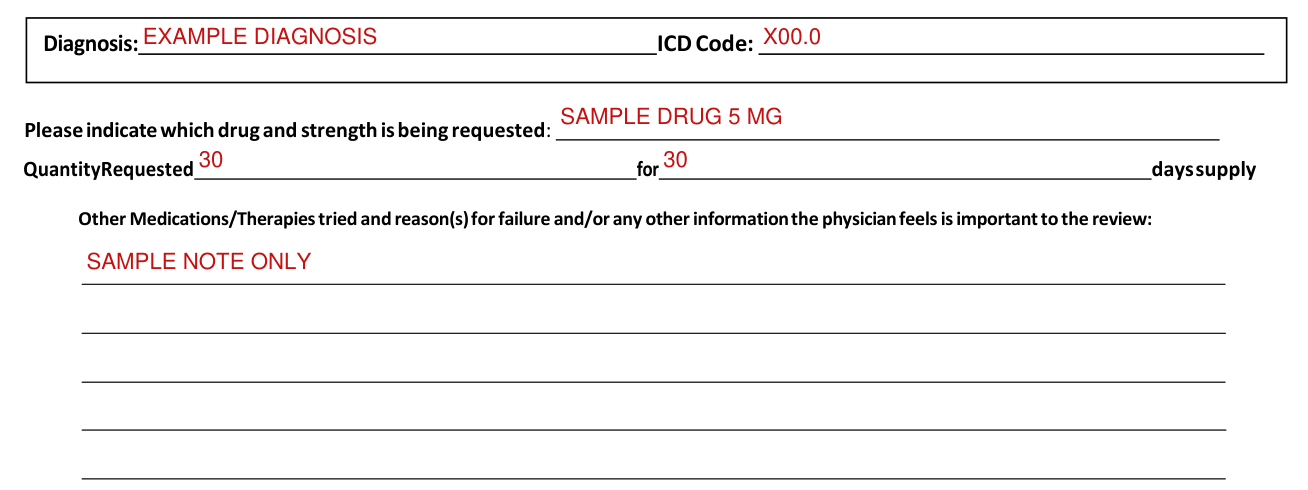
Prior Authorization Form General Request Form example filled out, diagnosis, the drug requested and Other Medications tried

Enter the Diagnosis and the ICD Code.

Please indicate which drug and strength is being requested.

Enter the QuantityRequested and the days supply.

Enter the Other Medications/Therapies tried and reason(s) for failure and/or any other information the physician feels is important to the review.

SIGN
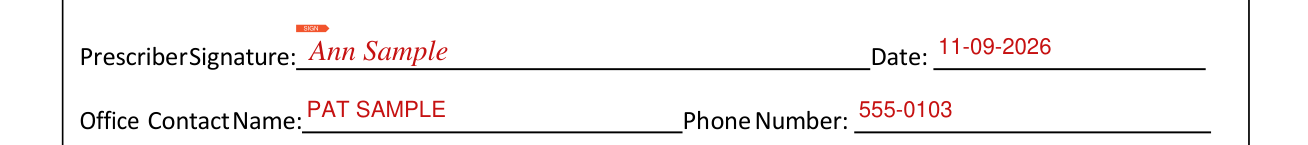
Prior Authorization Form General Request Form example filled out, sIGN

Under SIGN, enter the Prescriber Signature and the Date.

Enter the Office Contact Name and the Phone Number.

More rules for Prior Authorization Form General Request Form

Based upon each patient's prescription plan, additional questions may be required to complete the prior authorization process. If you have any questions about the process or required information, please contact the prior authorization team at the number listed on the top of this form.

Common questions about Prior Authorization Form General Request Form

Where do I file it?

Fax completed form to 1-877-251-5896. If this is an URGENT request, please call 1-800-417-8164.

Sources

[1] Prior Authorization Form General Request Form, Express Scripts (the Official source link on this page).

Please rate Express Scripts Androgel

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .