

Form 3 at a glance
What it is: The Virginia Workers' Compensation Act requires employers to report all workplace injuries and occupational diseases to the Commission under Va. Code § 65.2-900.
Who signs: The SUBMITTER (Required) signs under Signature, with PRINT, DATE and PHONE NUMBER.
A filled-in Form 3 example: an employer reports a worker's injury
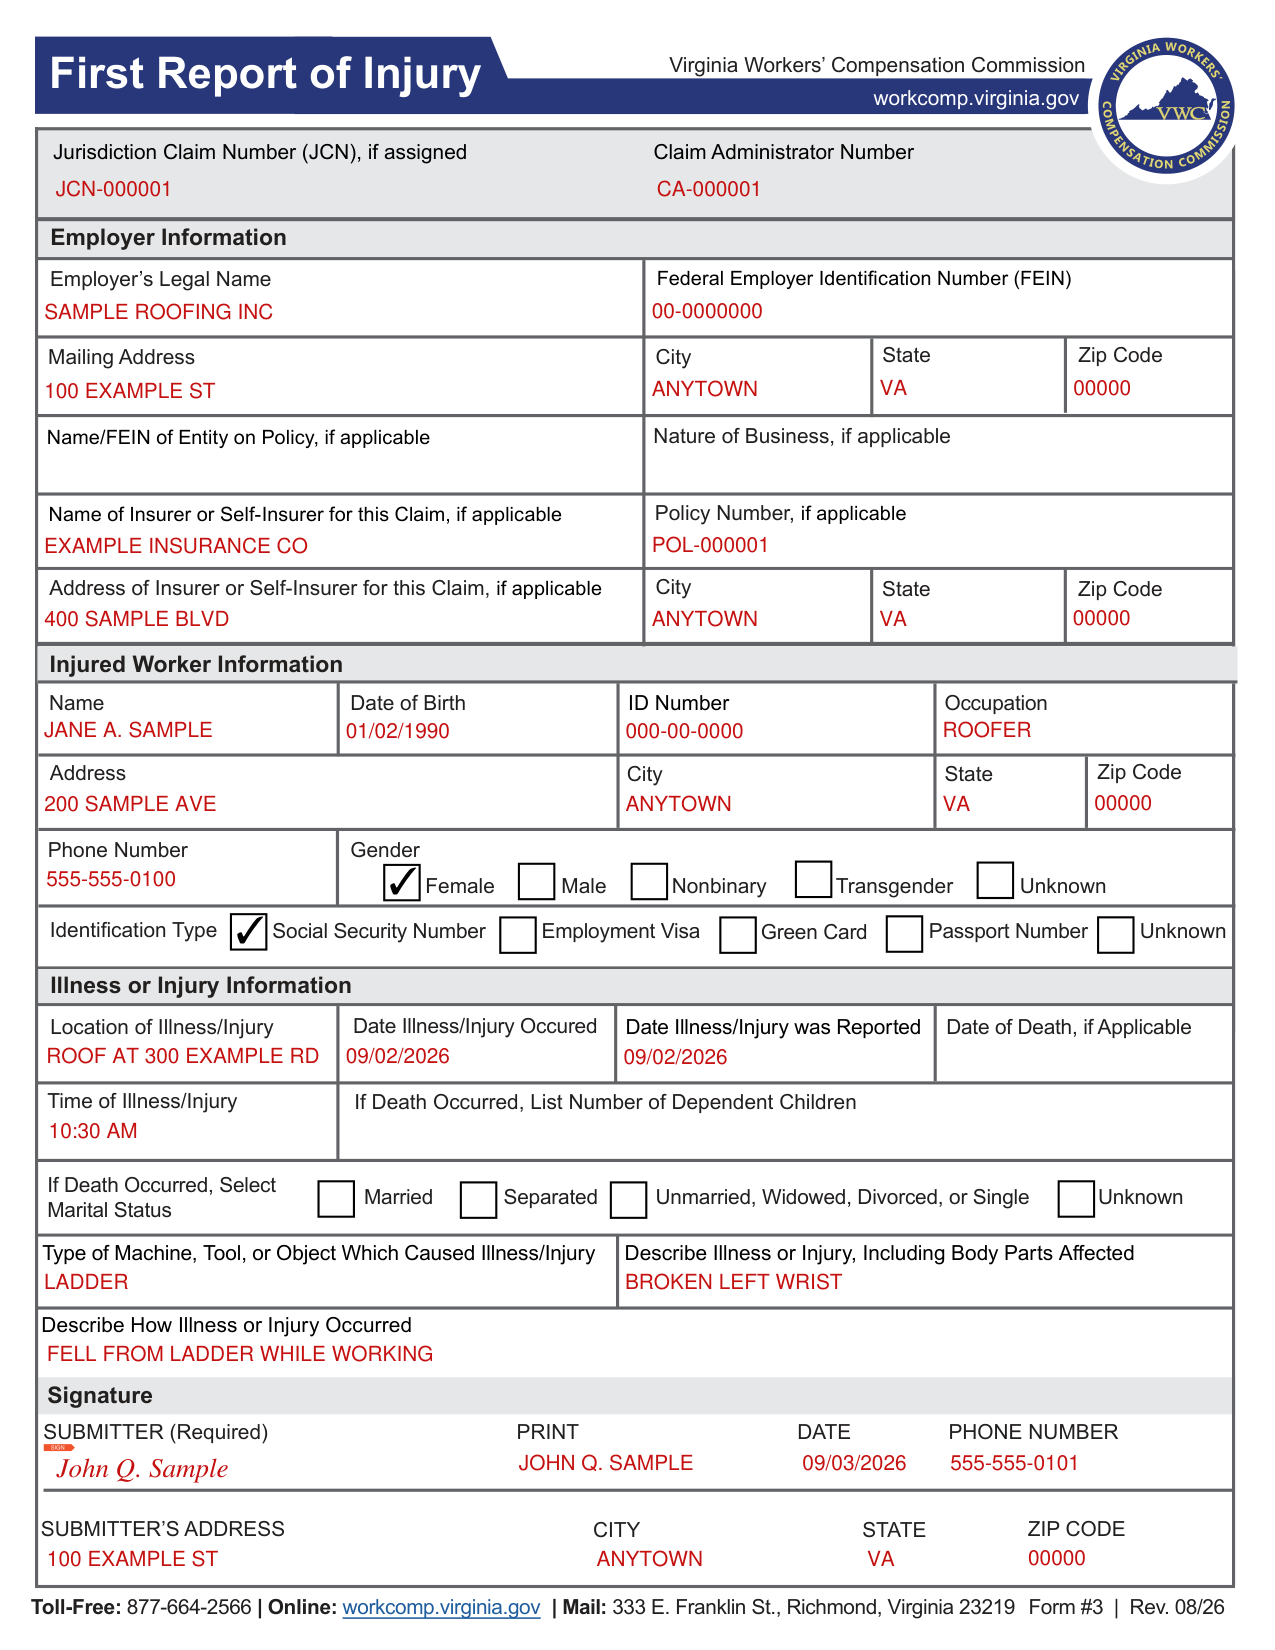
How to fill out Form 3, box by box
Jurisdiction Claim Number (JCN), if assigned

Enter the Jurisdiction Claim Number (JCN), if assigned, and the Claim Administrator Number.
Employer Information
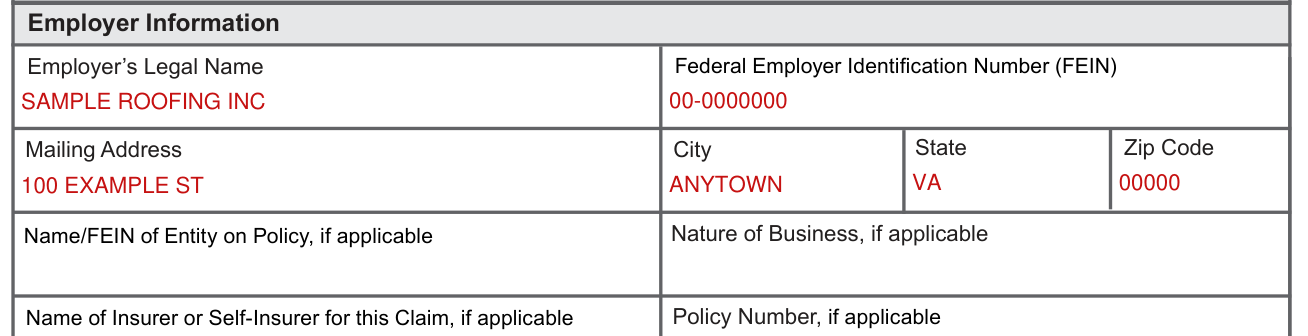
Under Employer Information, enter the Federal Employer Identification Number (FEIN), the Employer's Legal Name, and the Mailing Address, City, State and Zip Code.
Enter the Name/FEIN of Entity on Policy, if applicable, and the Nature of Business, if applicable.
Name of Insurer or Self-Insurer for this Claim
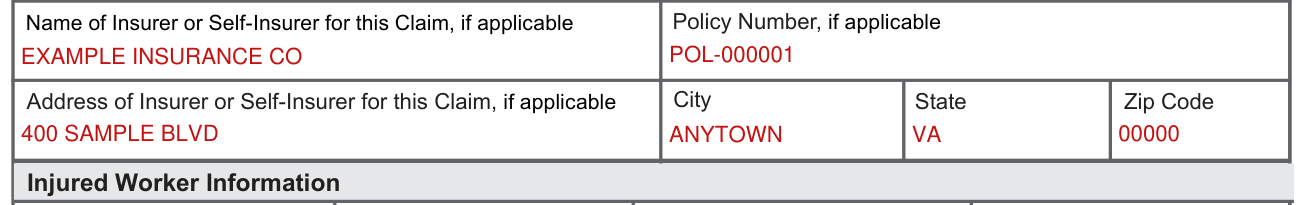
Enter the Name of Insurer or Self-Insurer for this Claim, if applicable, the Policy Number, if applicable, and the Address of Insurer or Self-Insurer for this Claim, if applicable, with City, State and Zip Code.
Injured Worker Information
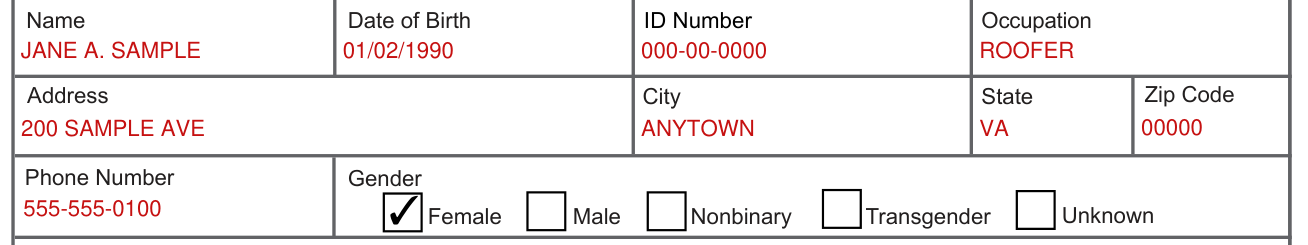
Under Injured Worker Information, enter the Name, ID Number, Date of Birth and Occupation.
Enter the Address, City, State, Zip Code and Phone Number.
Gender

Under Gender, mark Female, Male, Transgender, Nonbinary or Unknown.
Identification Type

Under Identification Type, mark Social Security Number, Employment Visa, Green Card, Passport Number or Unknown.
Illness or Injury Information
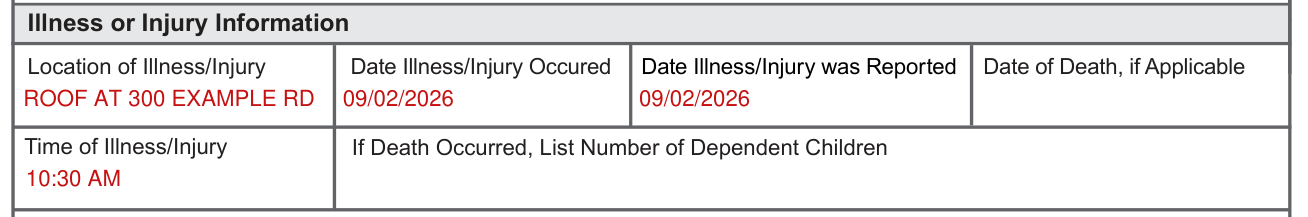
Under Illness or Injury Information, enter the Date Illness/Injury was Reported, the Location of Illness/Injury, the Date Illness/Injury Occured and the Time of Illness/Injury.
If Death Occurred
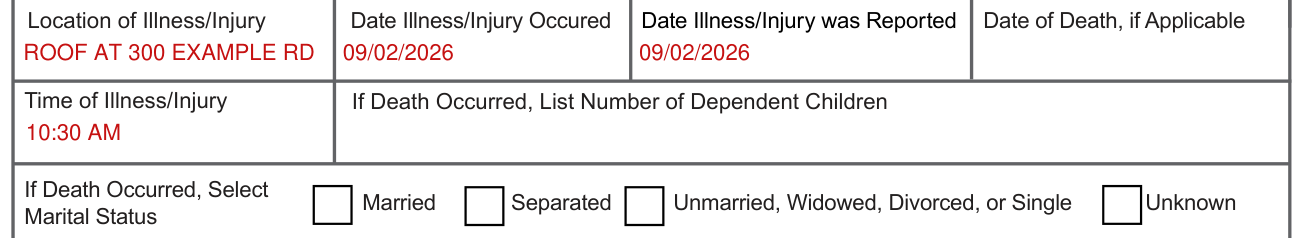
If Death Occurred, enter the Date of Death, if Applicable, and List Number of Dependent Children.
If Death Occurred, Select Marital Status: Unmarried, Widowed, Divorced, or Single, Married, Separated or Unknown.
Describe How Illness or Injury Occurred

Enter the Type of Machine, Tool, or Object Which Caused Illness/Injury, Describe Illness or Injury, Including Body Parts Affected, and Describe How Illness or Injury Occurred.
Signature
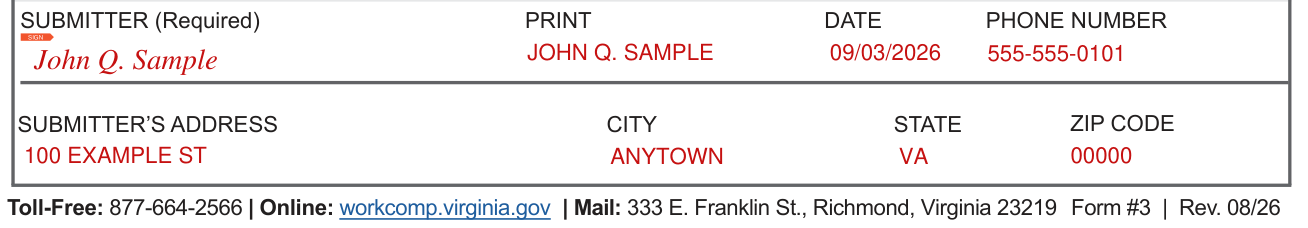
The SUBMITTER (Required) signs under Signature, with PRINT, DATE and PHONE NUMBER.
Enter the SUBMITTER'S ADDRESS, CITY, STATE and ZIP CODE.
More rules for Form 3
The form should be typed or legibly printed, signed, and dated by the preparer.
For other questions or assistance completing this form, please contact the Commission toll-free at 877- 664-2566.
If you are an uninsured employer and/ or are not represented by an attorney, you can contact the Ombudsman Department toll-free at 833-448-1681.
Common questions about Form 3
Who must file Form 3?
The employer is responsible for accurately completing all sections of this form when an employee is injured or is diagnosed with an occupational disease. Uninsured employers who do not have a claim administrator or insurance carrier and are unable to file electronically must submit the First Report of Injury form directly to the Virginia Workers' Compensation Commission.
Is Form 3 required by law?
The Virginia Workers' Compensation Act requires employers to report all workplace injuries and occupational diseases to the Commission under Va. Code § 65.2-900. In accordance with 16VAC30-91-20, all claims reports must be filed electronically with the Commission.
Where do I file it?
Send the original form to the claim administrator for the insurance company who provided insurance coverage on the date of the occurrence, if applicable. The claim administrator will report this information to the Commission if the employer has coverage. Otherwise, the employer should submit the First Report of Injury directly to the Virginia Workers' Compensation Commission. Mail: 333 E. Franklin St., Richmond, Virginia 23219.
Sources
[1] Form 3 (Rev. 08/26), First Report of Injury, Virginia Workers' Compensation Commission (the Official source link on this page).
