

Form 3613 at a glance
What it is: Form 3613 is the Home and Community Support Services Agency Provider Investigation Report for Home Health, Hospice and Personal Assistance Services Provider Use Only.
Where and when to file: Fax this report to (if 15 total pages or fewer): 877-438-5827. Email this report to: ciiprovider@hhs.texas.gov. Fax, Mail or Email One Time Only.
What to bring and attach to Form 3613
Attach all documents and pertinent information that might be needed for HHSC to complete the review of your investigation.
Attach documentation of any criminal history check searches, nurse aide registry searches and employee misconduct registry searches conducted to verify the employability of the alleged perpetrator.
Do not send printed copies of actual criminal history reports obtained from the Department of Public Safety (DPS) secure site.
A filled-in Form 3613 example: a home health agency reports an allegation
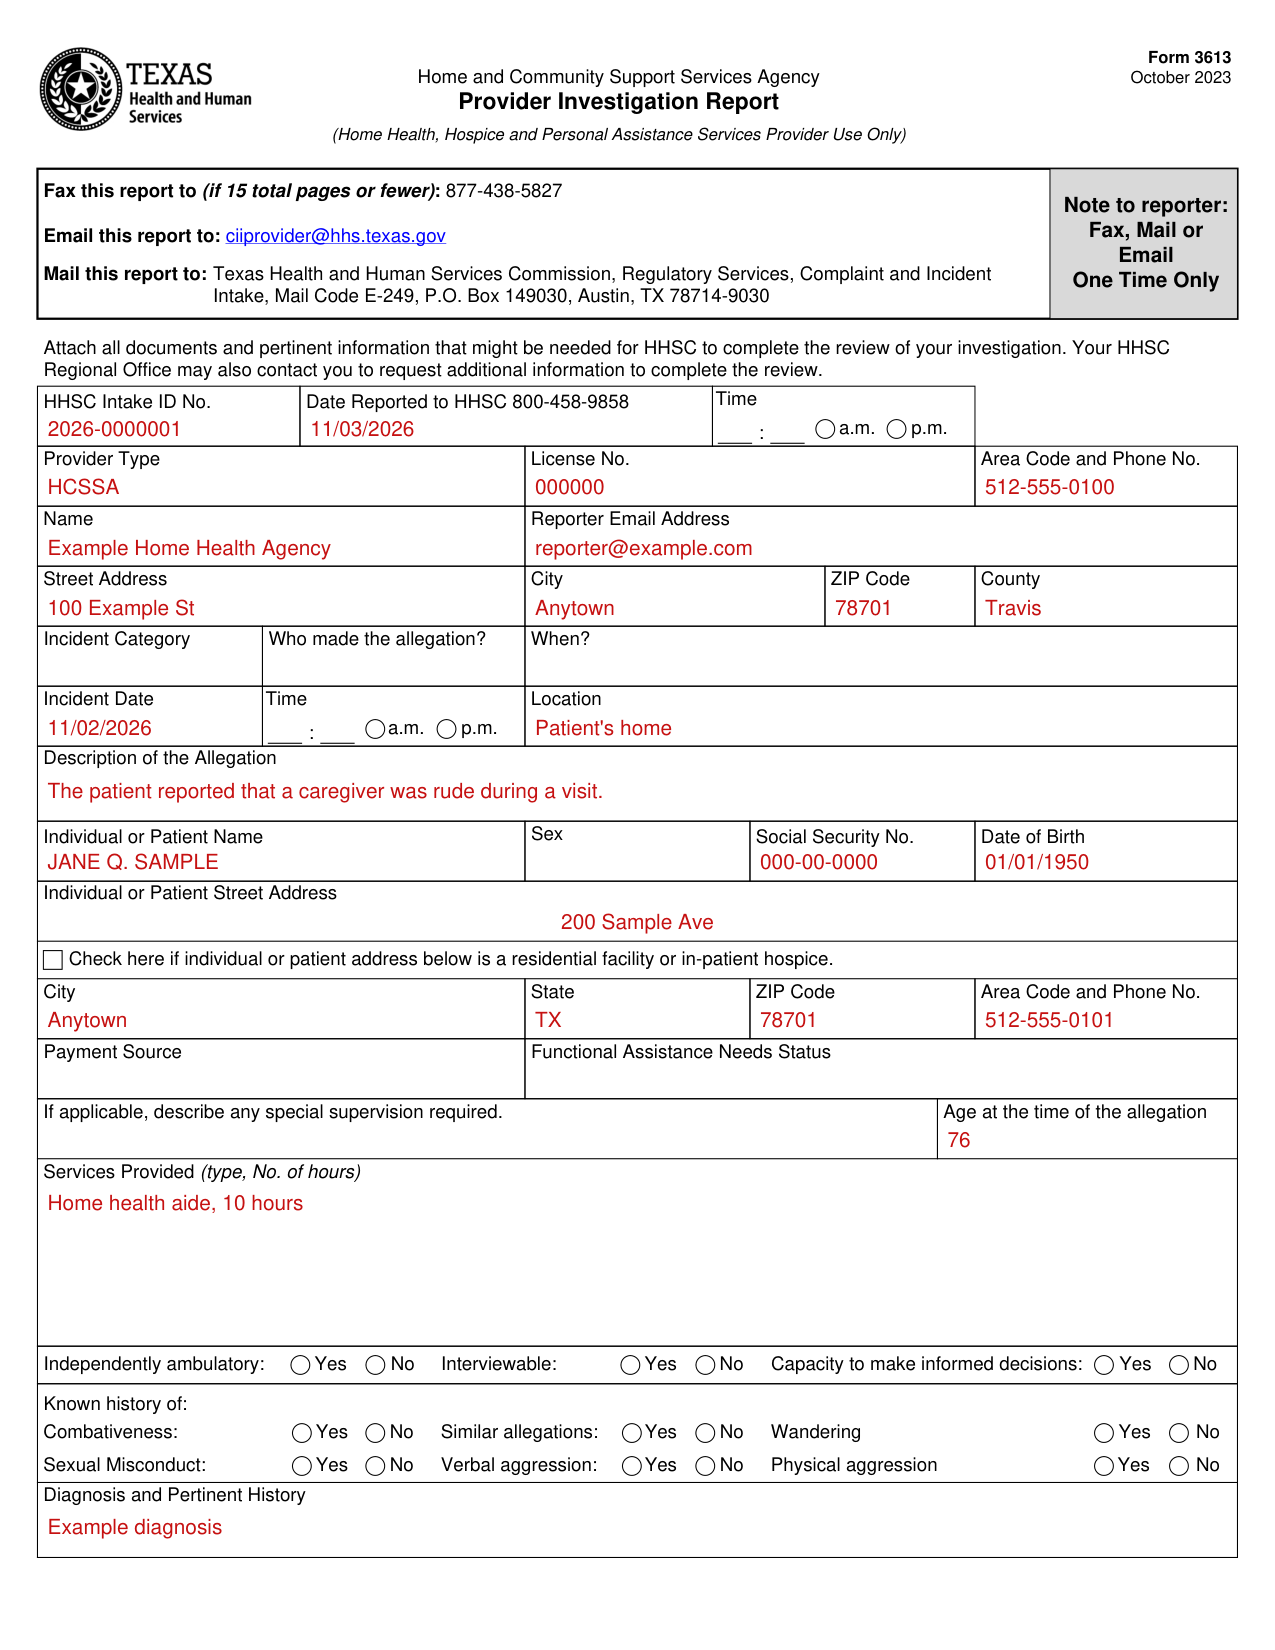
How to fill out Form 3613, box by box
HHSC Intake ID No. and Date Reported to HHSC

Enter the HHSC Intake ID No., Date Reported to HHSC and Time.
The provider

For the provider, enter the Provider Type, License No., Area Code and Phone No., Name, Reporter Email Address, Street Address, City, ZIP Code and County.
The allegation

For the allegation, enter the Incident Category, Who made the allegation?, When?, Incident Date, Time, Location and Description of the Allegation.
The individual or patient
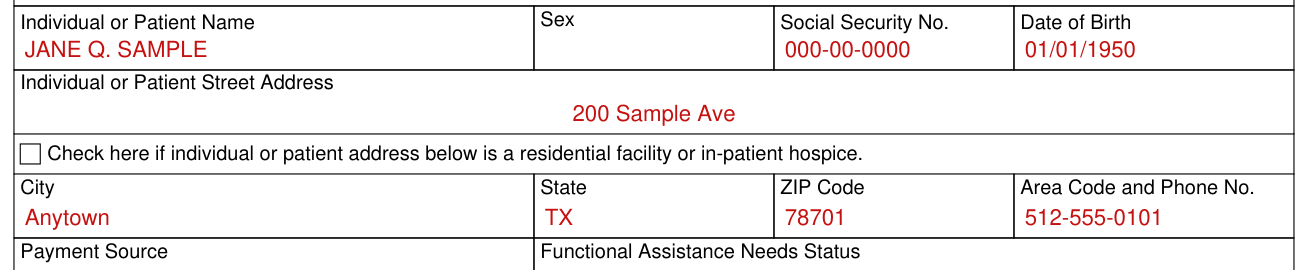
For the individual or patient, enter the Name, Sex, Social Security No., Date of Birth, Street Address, City, State, ZIP Code and Area Code and Phone No.
Check here if individual or patient address is a residential facility or in-patient hospice.
More rules for Form 3613
Enter the Age at the time of the allegation, Services Provided (type, No. of hours) and Diagnosis and Pertinent History.
Independently ambulatory, Interviewable and Capacity to make informed decisions: Yes No. Known history of Combativeness, Similar allegations, Wandering, Sexual Misconduct, Verbal aggression and Physical aggression: Yes No.
Attach additional sheets as necessary to the Investigation Summary.
Your HHSC Regional Office may also contact you to request additional information to complete the review.
Enter the No. of Pages, including cover.
If applicable, describe any special supervision required.
Common questions about Form 3613
Does it need a notary?
If the investigation reveals the presence of a witness, a statement attached is signed and notarized if possible: mark Yes or No.
Who signs it?
HHSC does not accept this report as complete until the reporter's signature, printed name, title and date have been entered.
Where do I file it?
Mail this report to: Texas Health and Human Services Commission, Regulatory Services, Complaint and Incident Intake, Mail Code E-249, P.O. Box 149030, Austin, TX 78714-9030.
Sources
[1] Form 3613 (10-2023), Home and Community Support Services Agency Provider Investigation Report, Texas Health and Human Services Commission (the Official source link on this page).