

Form F-60945 at a glance
What it is: F-60945 is the Adult Family Home Initial License Application of the Department of Health Services, Division of Quality Assurance, State of Wisconsin.
Where and when to file: Send the completed form with attachments listed to the Division of Quality Assurance (DQA) regional office assigned to the county in which the facility is located. Contact the appropriate regional office if you have questions about completion of this form.
Completion of this form is required by Chapter 50.033(2m), Wis. Stats., and DHS 88.03(2)(a), (b) and (4)(b), Wis. Admin. Code. Failure to complete this form accurately may result in licensure denial and/or delay in processing.
A filled-in Form F-60945 example: a new home applies for a license

How to fill out Form F-60945, box by box
Facility information
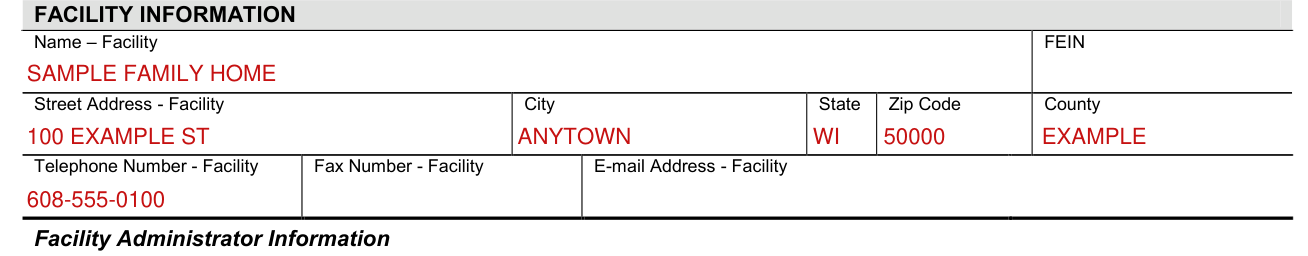
Under FACILITY INFORMATION, enter Name - Facility, FEIN, Street Address - Facility, City, State, Zip Code, County, Telephone Number - Facility, Fax Number - Facility and E-mail Address - Facility.
Resident information

Under RESIDENT INFORMATION, mark Total Resident Capacity: Three or Four.
Mark Yes or No: Does the Adult Family Home have a contract with a county agency or managed care organization to serve publicly funded individuals?
Mark All Female, All Male or Both.
More rules for Form F-60945
Under Facility Administrator Information, enter Name - Administrator, Birth Date - Administrator, Mailing Address - Administrator, City, State, Zip Code, Telephone Number - Administrator and E-mail Address - Administrator.
Under Designated Mail Recipient, provide contact information for the individual to whom mail from DHS/DQA is to be sent: Name - Designated Mail Recipient, Telephone Number, E-mail Address, Mailing Address, City, State and Zip Code.
Check the box indicating the primary client group(s) you are requesting to serve: AA - Advanced aged. ALZ - Irreversible dementia/Alzheimer's. DD - Developmentally disabled. MH - Emotionally disturbed / mental illness. ADA - Alcohol / drug dependent. PD - Physically disabled. PWC - Pregnant women who need counseling. CC - Correctional clients. TI - Terminally ill. TBI - Traumatic brain injury.
Under LICENSEE INFORMATION, check only one box: Governmental (City, County, State, Tribal), Proprietary (Individual, Partnership, Corporation, Limited Liability Co.) or Voluntary Non-Profit (Corporation, Church, Limited Liability Co.).
Enter Name - Licensee [Individual or Corporation (legal entity)], Birth Date - Licensee, Name - Owner or President, Mailing Address - Licensee, City, State, Zip Code and Telephone Number - Licensee.
Under MONTHLY OPERATING EXPENSES, enter All Salaries (i.e., licensee, caregivers, contract providers, etc.), Lease or Mortgage, All Other (food, supplies, utilities, insurance, taxes, etc.) and TOTAL Monthly Expenses.
Under NON RESIDENT INFORMATION, list the names of all persons, age 10 and older, who live in the facility and are not a resident, with Name (Last Name, First Name, MI), Relationship to Licensee and Date of Birth.
Under FIRE DEPARTMENT INFORMATION, enter the fire department's name, address, and telephone number. The Division of Quality Assurance will send a copy of the license to the local fire department.
Enter Name - Local Fire Department, Telephone Number (Do not enter 911.), Address (Street or PO Box), City, State and Zip Code.
The following items must be submitted with this application: program statement, resident grievance procedure. Floor plan (w/ room dimensions, exits, usage), background check. Verification of completion - AFH webcast, if a new provider, Assisted Living Facility Model Balance Sheet (F-62674A), fire evacuation plan, resident rights policy. Proof of vehicle and home owners / renters insurance, documentation of 60-day operating funds, admission / service agreement. License fee (non-refundable); check payable to: DQA. House rules and responsibilities.
The licensee is responsible for notifying the Division of Quality Assurance in writing of any change in the information provided on this application.
Mark YES or NO: Did you submit form F-82064 (BID) and form F-82069 (BID Appendix) to the Office of Caregiver Quality at the address listed: DHS / Division of Quality Assurance, Office of Caregiver Quality, P.O. Box 2969, Madison, WI 53701-2969?
Mark YES or NO: Does the licensee currently hold another type of license or certification?
List the days when residents are NOT in the facility. List the hours when residents are NOT in the facility.
The following information will be used to determine if the applicant meets the fit and qualified requirements under Chapter 50, Wis. Stats.
Has the licensee ever operated a residential facility, health care facility, or a day care program for adults or children in Wisconsin or in any other state? Mark Yes or No. If "yes," provide the name, address, and telephone number of the facility / program.
Was the facility / program licensed, certified, or otherwise regulated by any government or private agency? Mark Yes or No. If "yes," provide the name, address, and telephone number of that agency.
Has the licensee ever had a license, certification or governmental approval to operate a facility / program denied, revoked, suspended or not renewed? Mark Yes or No. If "yes," specify the type of license, certification, or approval affected; in which state the action occurred; which agency took the enforcement action; and the name, address, telephone number, and type of facility / program that was affected.
Under MONTHLY FEES, enter the minimum and maximum monthly fees charged for resident care. Include fees paid from all sources including government, private agencies, residents, and / or resident's family.
A current balance sheet must be submitted with this application. (See DQA form F-62674A, Assisted Living Facility Model Balance Sheet.)
Submit copies of financial documents verifying your ability to operate the facility for 60 days. This amount must be equal to or more than 2 times your monthly operating expenses.
If income from residents would not be adequate to pay your monthly operating expenses, you must have other sources of funds or income that may be used to continue the operation of the facility for at least a 60-day period. Check all other sources of income.
Under LICENSEE OWNERSHIP, mark what the licensee owns: Building, Land or Operation.
Provide specific directions to the facility from the closest major STATE highway.
Common questions about Form F-60945
Who signs it?
The licensee or designee signs under SIGNATURE (FULL) - Licensee or Designee, and enters Date Signed, Name - Licensee or Designee (Print or type.) and Title.
Are there fees?
The following items must be submitted with this application: License fee (Non-refundable); Check payable to: DQA.
Is there a penalty?
I understand, under penalty of law, that the information provided is truthful and accurate to the best of my knowledge. Knowingly providing false information or omitting information may result in a fine of up to $10,000 or imprisonment not to exceed 6 years, or both (Chapter 946.32, Wis. Stats.) (checked November 14, 2026).
Sources
[1] Form F-60945 (03/2013), Adult Family Home Initial License Application, Wisconsin Department of Health Services (the Official source link on this page).