


Form CA-7b at a glance
What it is: Form CA-7b is the U.S. Department of Labor Office of Workers' Compensation Programs Leave Buy Back (LBB) Worksheet/ Certification and Election.
Who signs: The Agency Official signs and dates, and advises the employee of the amount they owe to the agency. The claimant signs under III. Employee Claim (Signature of Claimant) and enters the Date Signed.
Page 3 Instructions, Form CA-7B Leave Buy Back Worksheet (June 2025): This form is intended to accompany Form CA-7, Claim for Compensation, when the employee is claiming leave buy back.
What to bring and attach to Form CA-7b
Complete the Form CA-7 for the dates claimed.
Where more than one continuous period of leave is claimed, complete Form CA-7a following the instructions for completing that form.
Medical documentation must be provided for all dates claimed.
Please submit a claim for a minimum of 10 hours unless no further claim is anticipated.
A filled-in Form CA-7b example: an employee elects leave buy back

How to fill out Form CA-7b, box by box
Employee Statement: name, file number, Social Security Number and period

Please carefully read instructions on pages 3 and 4 before filling out this form.
Enter A. Name of Employee: (Last, First, Middle), B. OWCP File Number and C. Social Security Number.
Under D. Period for Which Compensation is Claimed to Repurchase Leave, enter From and To.
I. Agency Estimate of FECA Entitlement, A. Weekly Base Payrate
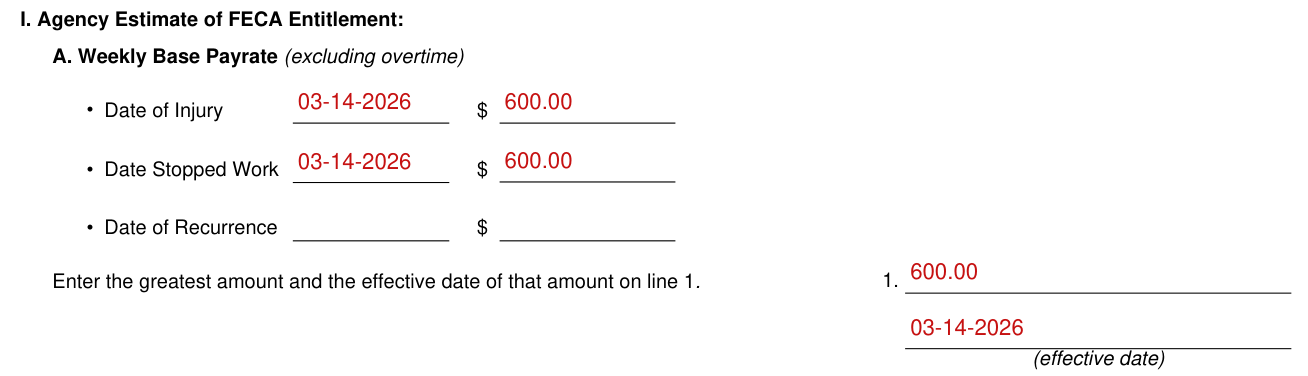
I. Agency Estimate of FECA Entitlement, A. Weekly Base Payrate (excluding overtime): Enter all three pay rate types and effective dates if applicable. Choose the greatest amount of the three and enter the amount and effective date in Line 1.
A recurrent pay rate should only be used if: (1) the employee stops work more than 6 months following their first return to regular, full time duty and (2) the loss of time is due to disability rather than medical examinations or treatment.
B. Additions to Base Pay
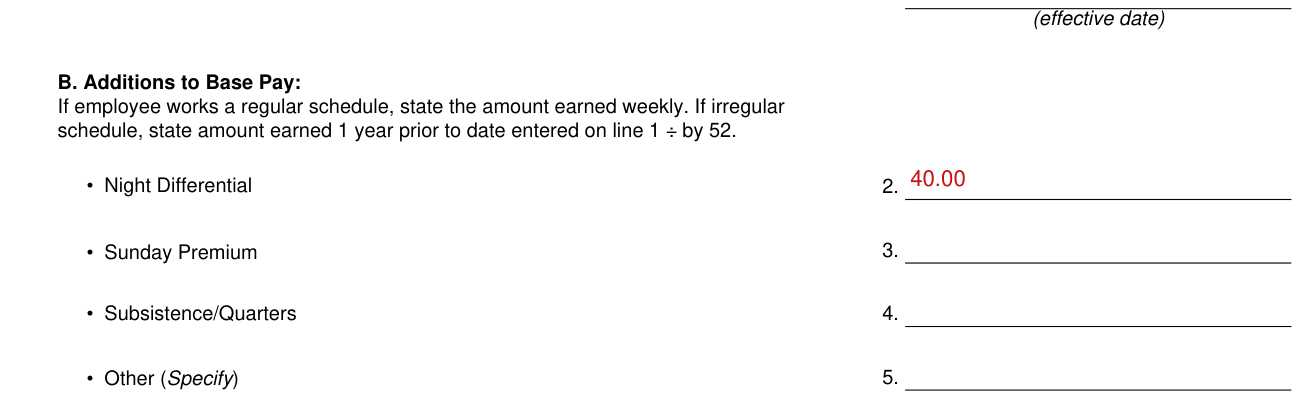
B. Additions to Base Pay: If employee works a regular schedule, state the amount earned weekly. If irregular schedule, state amount earned 1 year prior to date entered on line 1 ÷ by 52.
Please refer to Payrate Desk Aid for guidance on inclusions and exclusions. If in doubt, consult a Claims Examiner.
C. Total Weekly Payrate and D. Compensation Rate

C. Total Weekly Payrate (Add lines 1 through 5): enter the total in Line 6.
D. Compensation Rate (Circle either 2/3 or 3/4): circle the appropriate rate: 2/3 for employees without dependents; 3/4 with dependents.
Dependents include: spouse; children under 18 living with or supported by the employee; children under 23 in school fuil time; children over 18 incapable of self support; and parents wholly supported by the employee.
E. Total Hours Claimed and F. Total Hours Worked per Week

Item E: Enter the total hours claimed, from Form CA-7a.
Item F: Enter the total hours in the employee's normal work week.
G. Formula (for FECA Entitlement)
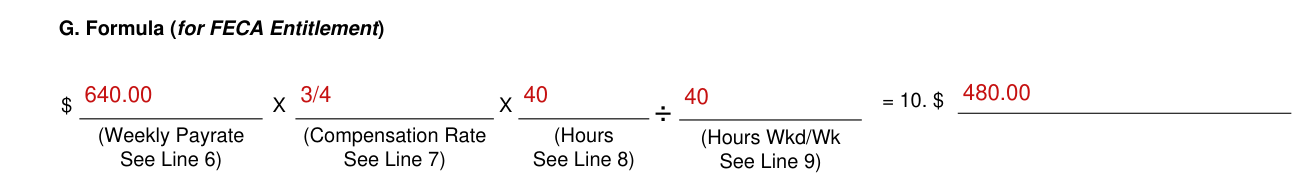
Item G: Formula for FECA Entitlement. Use this formula to calculate estimate of FECA entitlement and enter the result in Line 10.
II. Agency Certification

Agency Certification: Item H & I are self-explanatory. For Line J, subtract Line I from Line H.
"I hereby certify that the above is consistent with agency payroll records."
I further certify that if this claim is signed by the employee, the employee has made arrangements to pay the agency the balance between the total amount the agency requires to recredit leave and the amount of the FECA entitlement.
III. Employee Claim: K or L

K. I hereby elect not to repurchase the leave used at this time.
L. I hereby elect FECA compensation to repurchase leave used for medical care or disability resulting from my Job-related injury or condition.
If you choose to repurchase the leave, you will be required to pay to the agency the difference between the compensation due and the amount owed to the agency.
Employee Claim: If the employee elects not to repurchase the leave, retain the form in the agency files.
If the employee elects to repurchase the leave, submit all claim documents (CA-7, CA-7a & CA-7b) plus any medical documentation to OWCP for processing.
The claimant signs under III. Employee Claim (Signature of Claimant) and enters the Date Signed.
More rules for Form CA-7b
A claimant may not repurchase leave used during a period they were eligible for COP.
When disability does not exceed 14 days beyond the COP period, 3 day LWOP must be charged before compensation can be paid. If leave was used for this period, compensation can not be paid for the 3 days, but the claimant will have to pay back leave paid during the 3 days to repurchase the leave.
The employee's pay status must be changed to LWOP in order for compensation to be paid. Leave is not earned while in LWOP.
"If the total amount of FECA benefits estimated by the agency is not more than 10% above the amount determined by OWCP to be accurate, OWCP will process a payment for all hours supported by medical evidence."
"If the total amount of FECA benefits estimated by the agency is more than 10% above the correct amount, OWCP will not process the payment. Instead, the Office will offer you a new election with the correct amount of FECA benefits payable,"
Sources
[1] Form CA-7b (June 2025), Leave Buy Back (LBB) Worksheet/ Certification and Election, U.S. Department of Labor, Office of Workers' Compensation Programs (the Official source link on this page).