
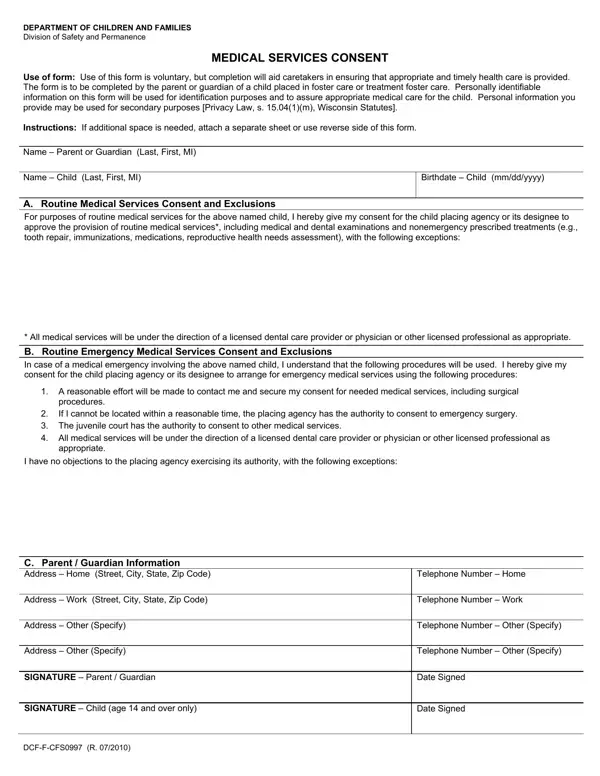
Form DCF-F-CFS0997-E at a glance
What it is: Medical Services Consent is a form of the DEPARTMENT OF CHILDREN AND FAMILIES, Division of Safety and Permanence.
Who signs: The parent or guardian signs on the line marked SIGNATURE - Parent / Guardian. Write the Date Signed (mm/dd/yyyy); the child signs under SIGNATURE - Child (age 14 and over only).
The blank Form DCF-F-CFS0997-E: print it and complete it by hand
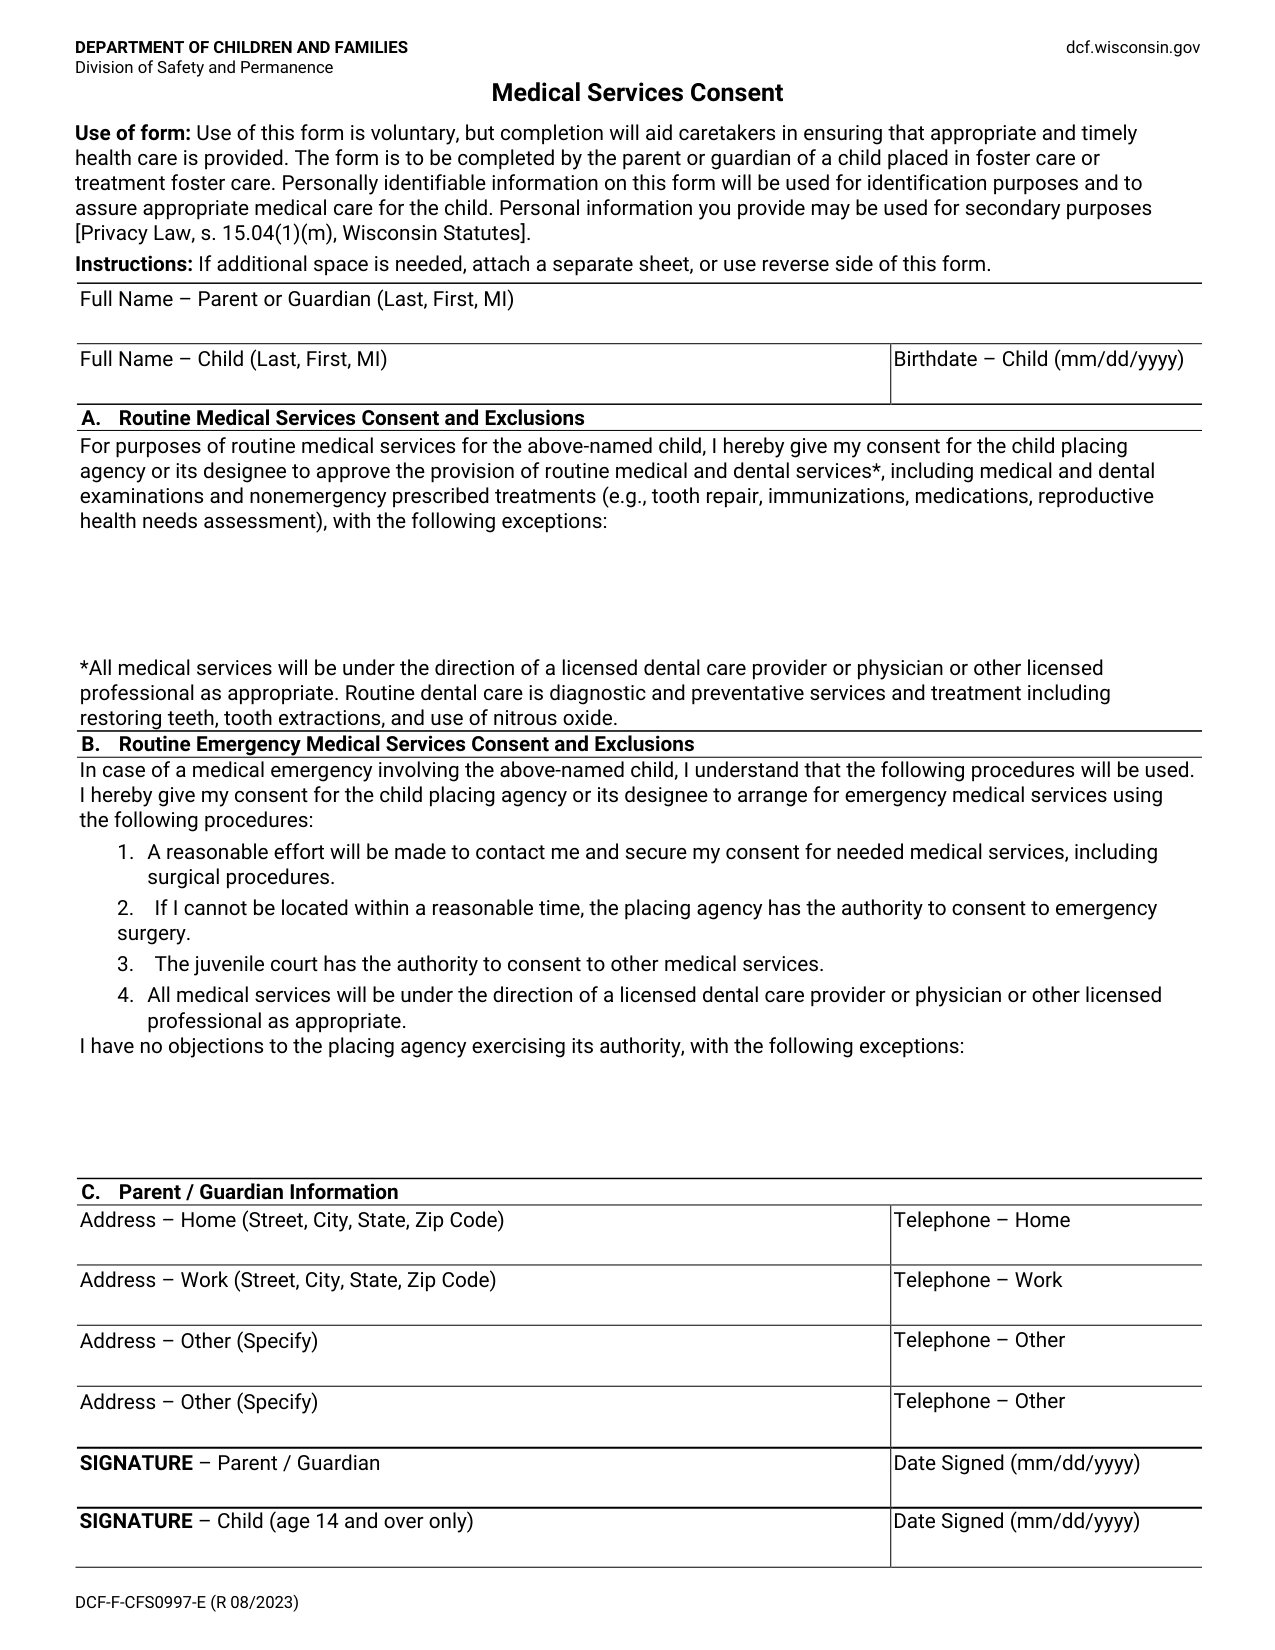
How to fill out Form DCF-F-CFS0997-E, box by box
The parent or guardian and the child
Enter the Full Name of the Parent or Guardian (Last, First, MI), the Full Name of the Child (Last, First, MI) and the child's Birthdate (mm/dd/yyyy).
A. Routine Medical Services Consent and Exclusions
In A. Routine Medical Services Consent and Exclusions, you give consent for the child placing agency or its designee to approve routine medical and dental services, including medical and dental examinations and nonemergency prescribed treatments, with the exceptions you list.
Routine dental care is diagnostic and preventative services and treatment including restoring teeth, tooth extractions, and use of nitrous oxide.
B. Routine Emergency Medical Services Consent and Exclusions
In B. Routine Emergency Medical Services Consent and Exclusions, you give consent for the child placing agency or its designee to arrange for emergency medical services using the following procedures.
1: a reasonable effort will be made to contact you and secure your consent for needed medical services, including surgical procedures.
2: if you cannot be located within a reasonable time, the placing agency has the authority to consent to emergency surgery.
3: the juvenile court has the authority to consent to other medical services.
4: all medical services will be under the direction of a licensed dental care provider or physician or other licensed professional as appropriate; you have no objections to the placing agency exercising its authority, with the exceptions you list.
C. Parent / Guardian Information
In C. Parent / Guardian Information, enter the Home address (Street, City, State, Zip Code) and the Home Telephone.
Enter the Work address (Street, City, State, Zip Code) and the Work Telephone.
The form prints two Address - Other (Specify) lines, each with its own Telephone - Other: for each Other address, specify it and write its Telephone - Other.
Signature
The parent or guardian signs on the line marked SIGNATURE - Parent / Guardian.
Write the Date Signed (mm/dd/yyyy); the child signs under SIGNATURE - Child (age 14 and over only).
More rules for Form DCF-F-CFS0997-E
If additional space is needed, attach a separate sheet, or use reverse side of this form.
Sources
[1] Form DCF-F-CFS0997-E (R 08/2023), Medical Services Consent, Wisconsin Department of Children and Families (the Official source link on this page).