


Form DL-121 at a glance
What it is: DL-121 is the Seizure Reporting Form of the Bureau of Driver Licensing, approved by the Medical Advisory Board 11/16/2012 for Medical Reporting.
Who signs: Sign the Health Care Provider's Signature line and enter the Date.
A filled-in Form DL-121 example: a doctor reports one seizure on page 1

How to fill out Form DL-121, box by box
Patient information

Complete the patient information in its entirety.
Enter the Driver's License No., Last Name(s), Jr. etc. and First Name, then the Height in Feet and Inches, Sex, Eye Color, Date of Birth by Month, Day and Year, Telephone Number and E-mail (if applicable).
Enter the Street Address, City, State and Zip Code; a P.O. Box number may be used in addition to the actual street address, but cannot be used as the only address.
Enter the Patient Name and Driver's License Number.
Treating the patient, seizure and EEG

1. How long have you been treating the patient?
2. Did the patient have a seizure? If yes, enter the date of the seizure.
3. Has the patient had more than one seizure?
4. Does the patient have an electrically diagnosed seizure disorder?
5. Has the patient had an EEG? If yes, enter the date of EEG.
Medication and loss of consciousness

6. Is the patient being treated with medication? If yes, enter the type and dosage and if the medication affects the patient's ability to safely operate a motor vehicle.
7. Other than a seizure disorder, does the patient have episode(s) of loss of consciousness or awareness that would interfere with the safe operation of a motor vehicle? If yes, please explain.
8. Does the patient have seizure(s) attributable to a prescribed change in or removal from medication? If yes, enter when the medication was changed/discontinued, the date of last seizure and if the original medication has been reintroduced.
Aura, sleep and the last 6 months
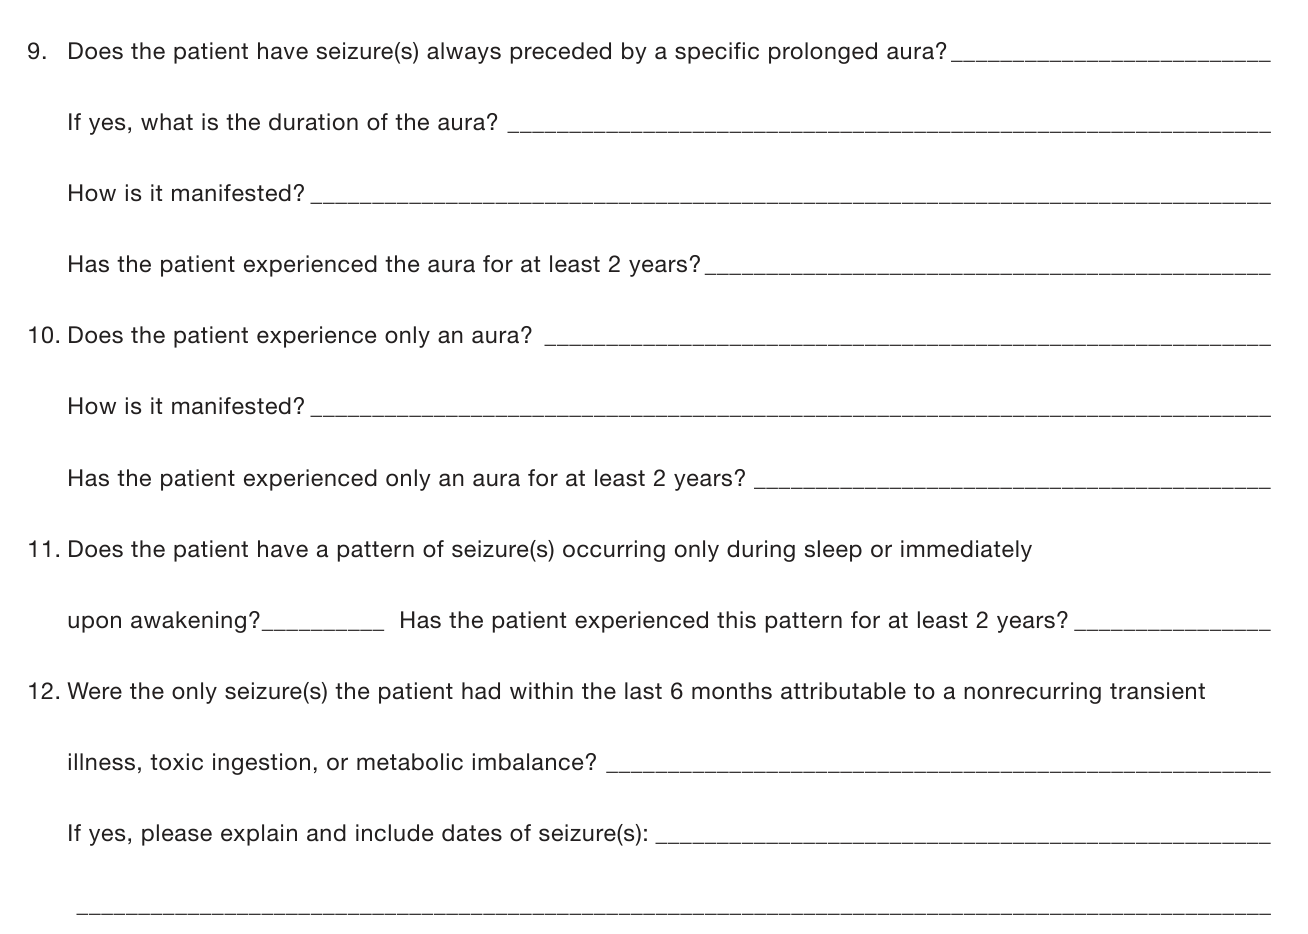
9. Does the patient have seizure(s) always preceded by a specific prolonged aura? If yes, enter the duration of the aura, how it is manifested and if the patient has experienced the aura for at least 2 years.
10. Does the patient experience only an aura? Enter how it is manifested and if the patient has experienced only an aura for at least 2 years.
11. Does the patient have a pattern of seizure(s) occurring only during sleep or immediately upon awakening? Enter if the patient has experienced this pattern for at least 2 years.
12. Were the only seizure(s) the patient had within the last 6 months attributable to a nonrecurring transient illness, toxic ingestion, or metabolic imbalance? If yes, please explain and include dates of seizure(s).
Health care provider information
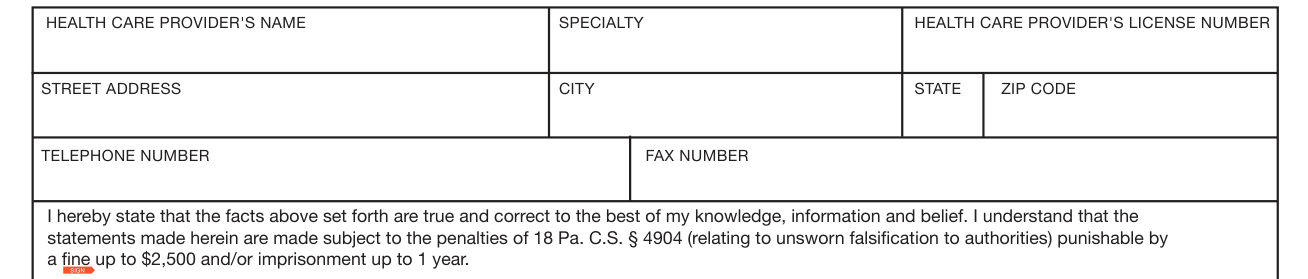
Under Health Care Provider Information, print or type the Health Care Provider's Name, Specialty, Health Care Provider's License Number, Street Address, City, State, Zip Code, Telephone Number and Fax Number.
Health Care Provider's Signature and Date

State that the facts set forth are true and correct to the best of your knowledge, information and belief.
Sign the Health Care Provider's Signature line and enter the Date.
The statements made are subject to the penalties of 18 Pa. C.S. § 4904, punishable by up to $2,500 and/or imprisonment up to 1 year (checked November 10, 2026).
More rules for Form DL-121
Type or print all information in blue or black ink.
Sources
[1] Seizure Reporting Form DL-121 (12-12) (the Official source link on this page).