

DOH-4328 at a glance
What it is: DOH-4328 (11/23) is the New York State Department of Health Medicare Savings Program Application.
Who signs: The applicant or a representative signs; if both spouses are applying, both must sign.
By completing and signing this form, you are applying for the Medicare Savings Program, and payment of your Medicare premium is a Medicaid benefit.
If you are married and living with your spouse, you must complete both the "Self" and "Spouse" questions on the application (even if the spouse is not applying for the MSP).
What to bring and attach to DOH-4328
Please review this list and submit the documents that you will need to provide in order for the Medicaid Program to determine if you are eligible for MSP.
A photocopy of the front and back of your Medicare card.
Proof of income: Paycheck stubs, letter from employer, income tax return, award letter for any unearned income such as social security or unemployment, or letter from renter, boarder or tenant.
Health insurance premiums that you pay other than Medicare: Letter from employer, premium statement, or pay stub.
Proof of date of birth: State driver's license, U.S. birth certificate, permanent resident card ("green card"), or NYS Benefit Identification Card.
Proof of residence: Lease/letter/rent receipt with your home address from your landlord, driver's license (if issued in the past 6 months), utility bill (gas, electric, phone, cable, fuel or water), government ID card with address, property tax records or mortgage statement, or postmarked envelope or postcard (cannot use if sent to a P.O. Box).
If you are not a U.S. citizen, you must provide documents indicating your current immigration status.
If there is an applying spouse, the spouse must also provide documentation.
A filled-in DOH-4328 example: an applicant for the Medicare Savings Program
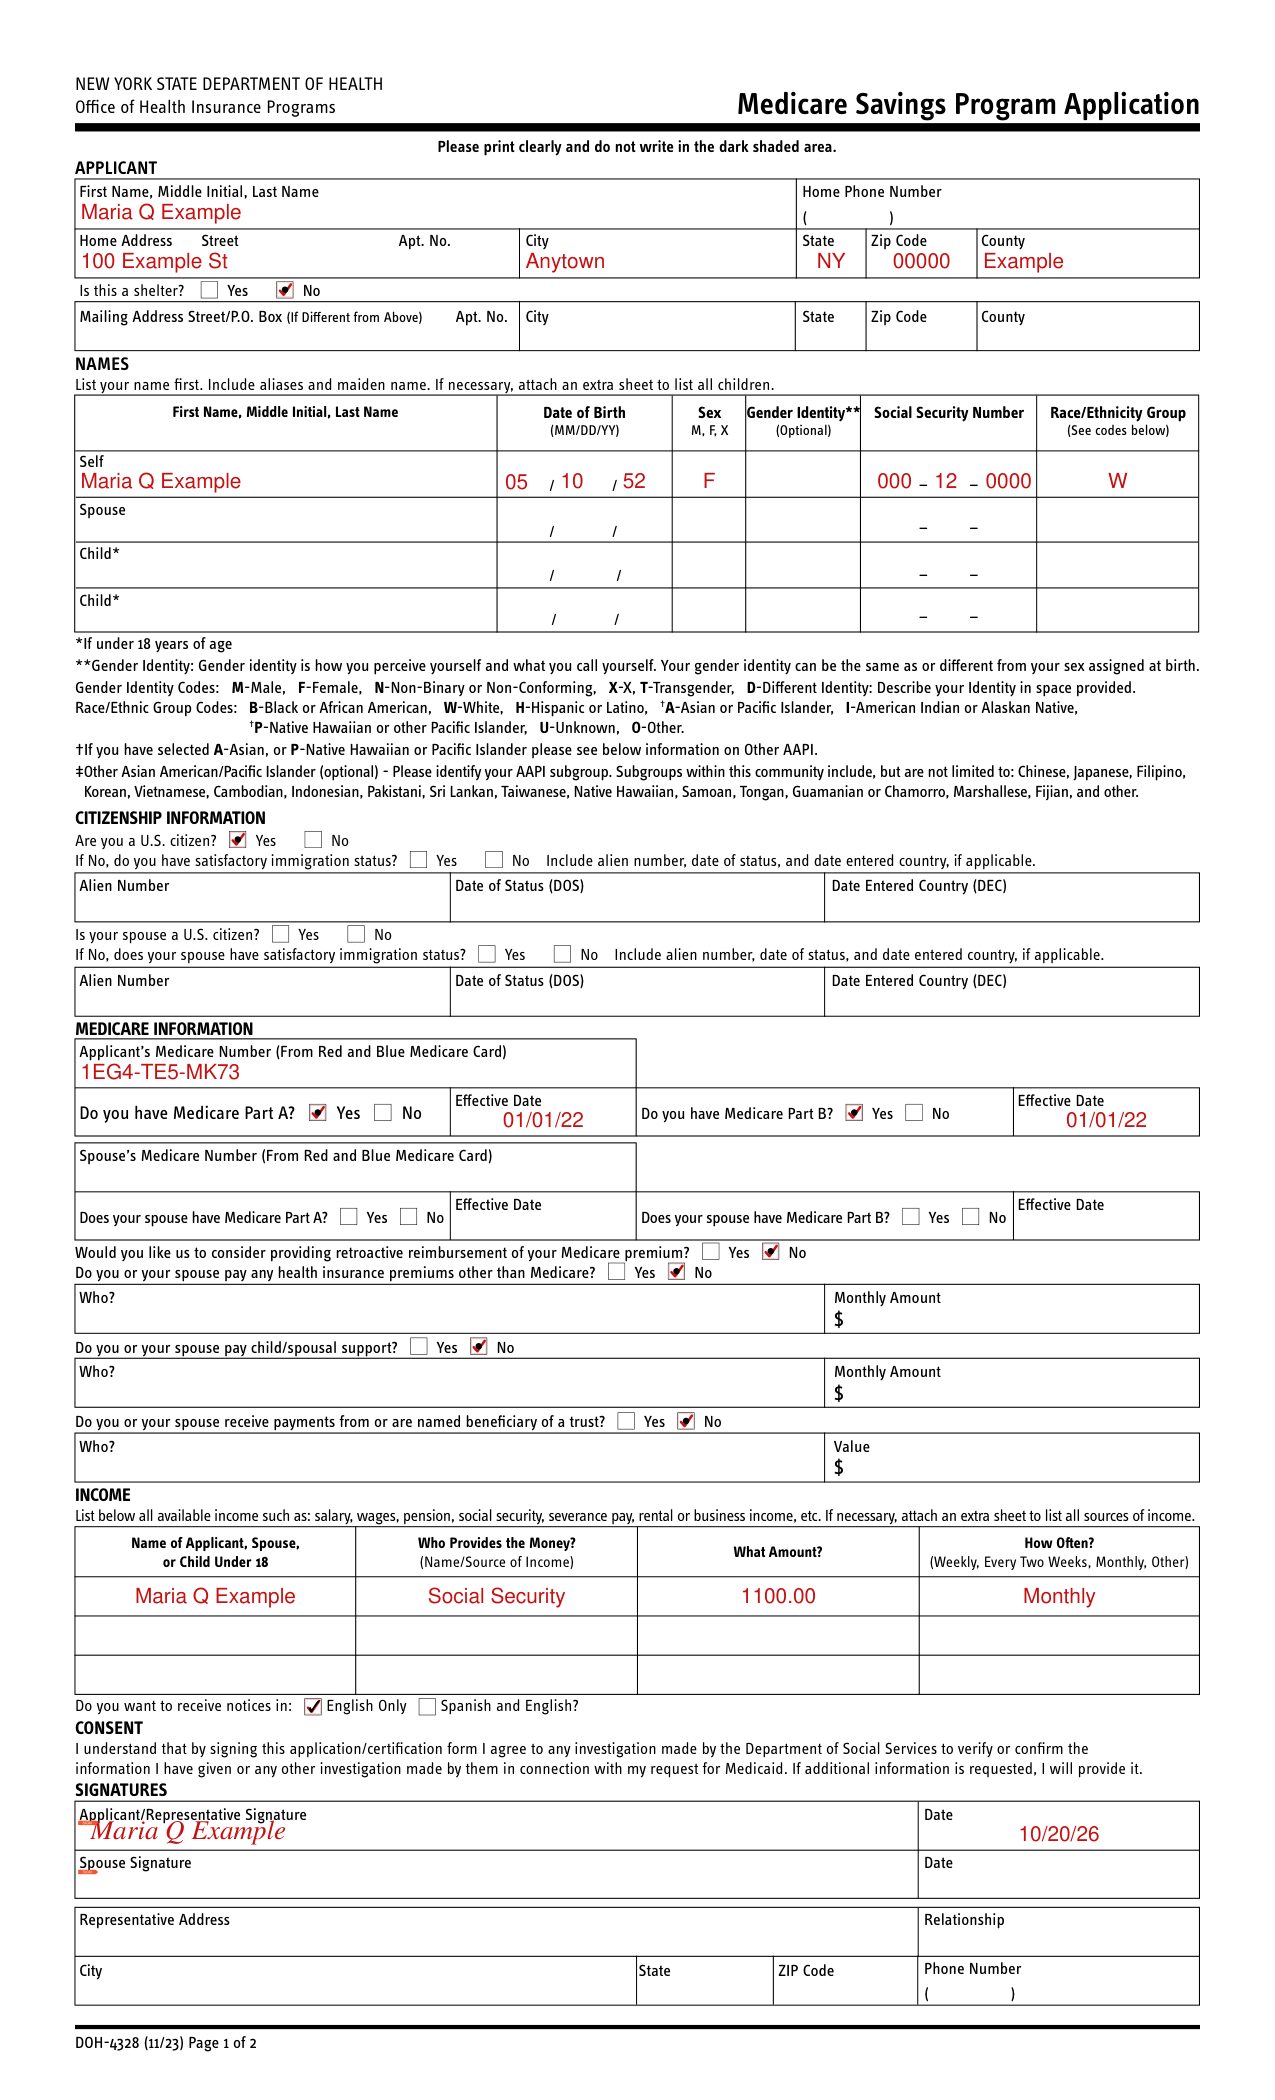
How to fill out DOH-4328, box by box
Home Address

Enter First Name, Middle Initial, Last Name, Home Phone Number, Home Address Street, Apt. No., City, State, Zip Code and County.
Mark Yes or No for Is this a shelter?
Names
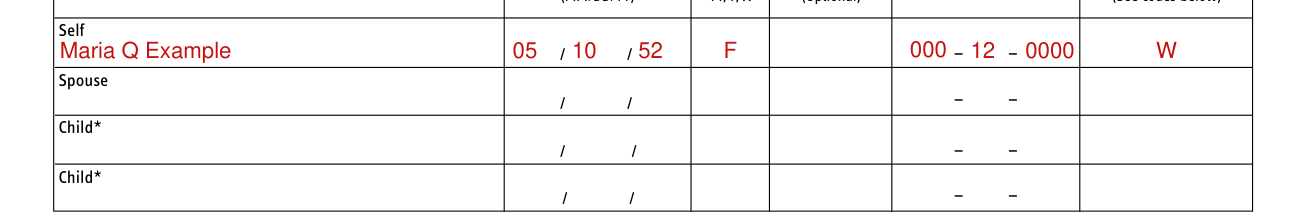
Under NAMES, list your name first. Include aliases and maiden name. If necessary, attach an extra sheet to list all children.
On each line, enter First Name, Middle Initial, Last Name, Date of Birth (MM/DD/YY), Sex M, F, X, Gender Identity (Optional), Social Security Number and Race/Ethnicity Group ("See codes below").
The lines are Self, Spouse and Child*.
Alien Number
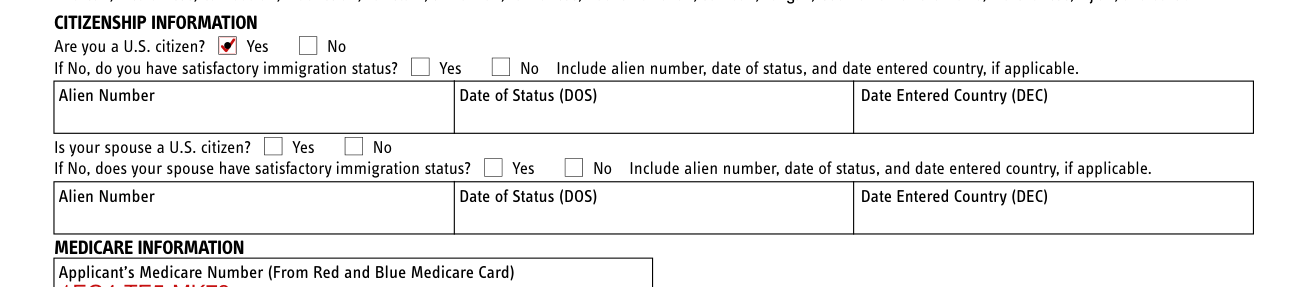
Under Citizenship Information, mark Yes or No for Are you a U.S. citizen? If No, do you have satisfactory immigration status? Mark Yes or No. Include your Alien Number, Date of Status (DOS) and Date Entered Country (DEC), if applicable.
Mark Yes or No for Is your spouse a U.S. citizen? If No, does your spouse have satisfactory immigration status? Mark Yes or No. Include alien number, date of status, and date entered country, if applicable.
Medicare information
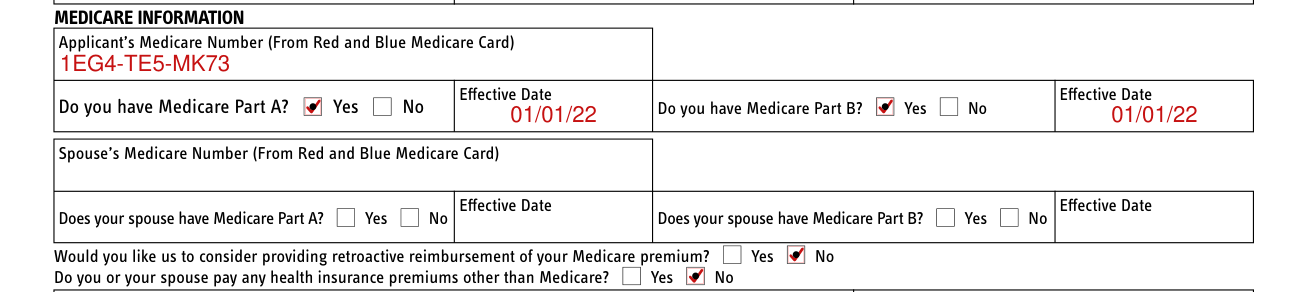
Under MEDICARE INFORMATION, enter the Applicant's Medicare Number (From Red and Blue Medicare Card). Mark Yes or No for Do you have Medicare Part A? and enter the Date. Mark Yes or No for Do you have Medicare Part B? and enter the Date.
Enter the Spouse's Medicare Number (From Red and Blue Medicare Card). Mark Yes or No for Does your spouse have Medicare Part A? and enter the Date. Mark Yes or No for Does your spouse have Medicare Part B? and enter the Date.
Premiums, support and trust
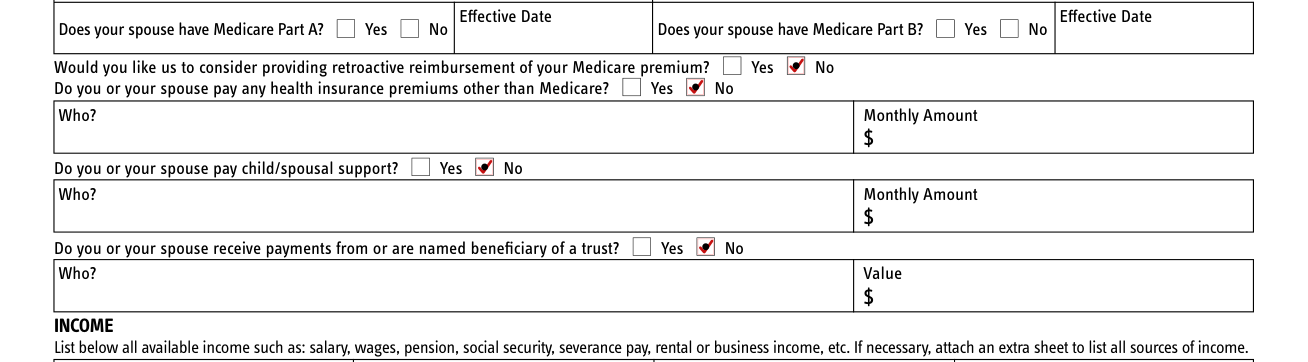
Mark Yes or No for providing retroactive reimbursement of your Medicare premium. If you are requesting retroactive reimbursement of your Medicare premiums, you must send proof of income for the previous three-months.
Mark Yes or No for Do you or your spouse pay any health insurance premiums other than Medicare? then enter Who? and Monthly Amount $.
Mark Yes or No for Do you or your spouse pay child/spousal support? then enter Who? and Monthly Amount $.
Mark Yes or No for Do you or your spouse receive payments from ... of a trust?, then enter Who? and Value $.
Income
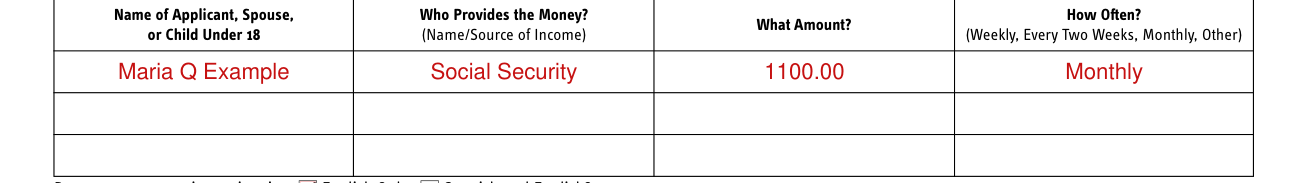
Under INCOME, list all available income such as: salary, wages, pension, social security, severance pay, rental or business income, etc. If necessary, attach an extra sheet to list all sources of income.
For each source, enter Name of Applicant, Spouse, or Child Under 18, Who Provides the Money? (Name/Source of Income), What Amount? and How? (Weekly, Every Two Weeks, Monthly, Other).
Notices, consent and signatures
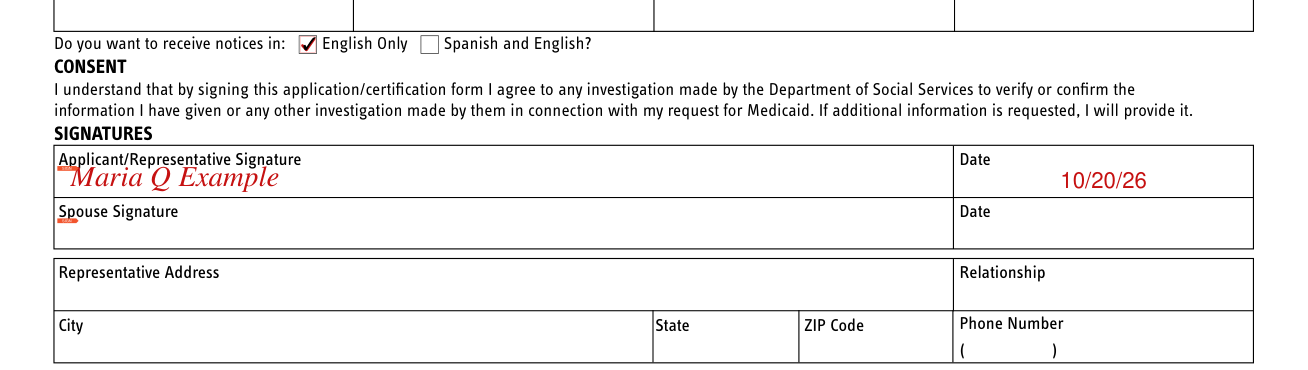
Mark English Only or Spanish and English for Do you want to receive notices in:
By signing this application you agree to any investigation made by the Department of Social Services to verify the information you have given or any other investigation made by them in connection with your request for Medicaid. If additional information is requested, you will provide it.
Under SIGNATURES, sign in Applicant/Representative Signature and enter the Date.
If both spouses are applying, both must sign the MSP application. The Spouse Signature has its own Date.
Enter the Representative Address, Relationship, City, State, ZIP Code and Phone Number.
In signing this application, you swear that the information you have given or will give to the Department of Social Services as a basis for Medicaid is correct.
You certify, under the penalty of perjury, by signing your name on this application, that you, and/or any person for whom you are signing is a U.S. citizen or national of the United States or has satisfactory immigration status.
Withdrawal

If after reading and completing this form, you decide that you DO NOT want to apply for the Medicare Savings Program, please sign your name on Applicant Signature and enter the Date, to consent to withdraw your application.
More rules for DOH-4328
Please type or print legibly, do not write in the dark shaded area, and be sure to answer all the questions.
If you are applying for the Medicare Savings Program, you must report your SSN.
You agree to immediately report any changes to the information on this application.
Federal and State laws provide for penalties if you do not tell the truth at any time when you are questioned about your eligibility, or cause someone else not to tell the truth regarding your application or your continuing eligibility.
Common questions about DOH-4328
Where do I file it?
Mail the application and required documentation to your local Department of Social Services (LDSS) or Human Resource Administration (HRA). The address in your county is at http://www.health.ny.gov/health_care/medicaid/ldss.htm.
Is there a penalty?
Federal and State laws provide for penalties if you do not tell the truth when you apply for Medicaid.
Sources
[1] DOH-4328 (11/23), Medicare Savings Program Application, New York State Department of Health (the Official source link on this page).
