

CCSP Application DCYF 14-417 at a glance
What it is: The CCSP Application, DCYF 14-417, is the Child Care Subsidy Programs application of the State of Washington Department of Children, Youth, and Families.
Where and when to file: The Child Care Subsidy Contact Center is at PO Box 11346, Tacoma, WA 98411-9903, toll free 844-626-8687, fax 877-309-9747.
What to bring and attach to CCSP Application DCYF 14-417
Complete a CCSP application even if you are in a WorkFirst activity or referred from Child Welfare.
Proof of the last three months of household income (such as pay stubs, child support, Social Security Income, Supplemental Security Income (SSI), and any other income received by someone in your family); include your employment schedule. You don't need to provide proof of income for cash assistance from the state (TANF).
Proof of any court or administrative ordered child support payments made in the last three months.
A filled-in CCSP Application DCYF 14-417 example: a single mother applies for child care subsidy
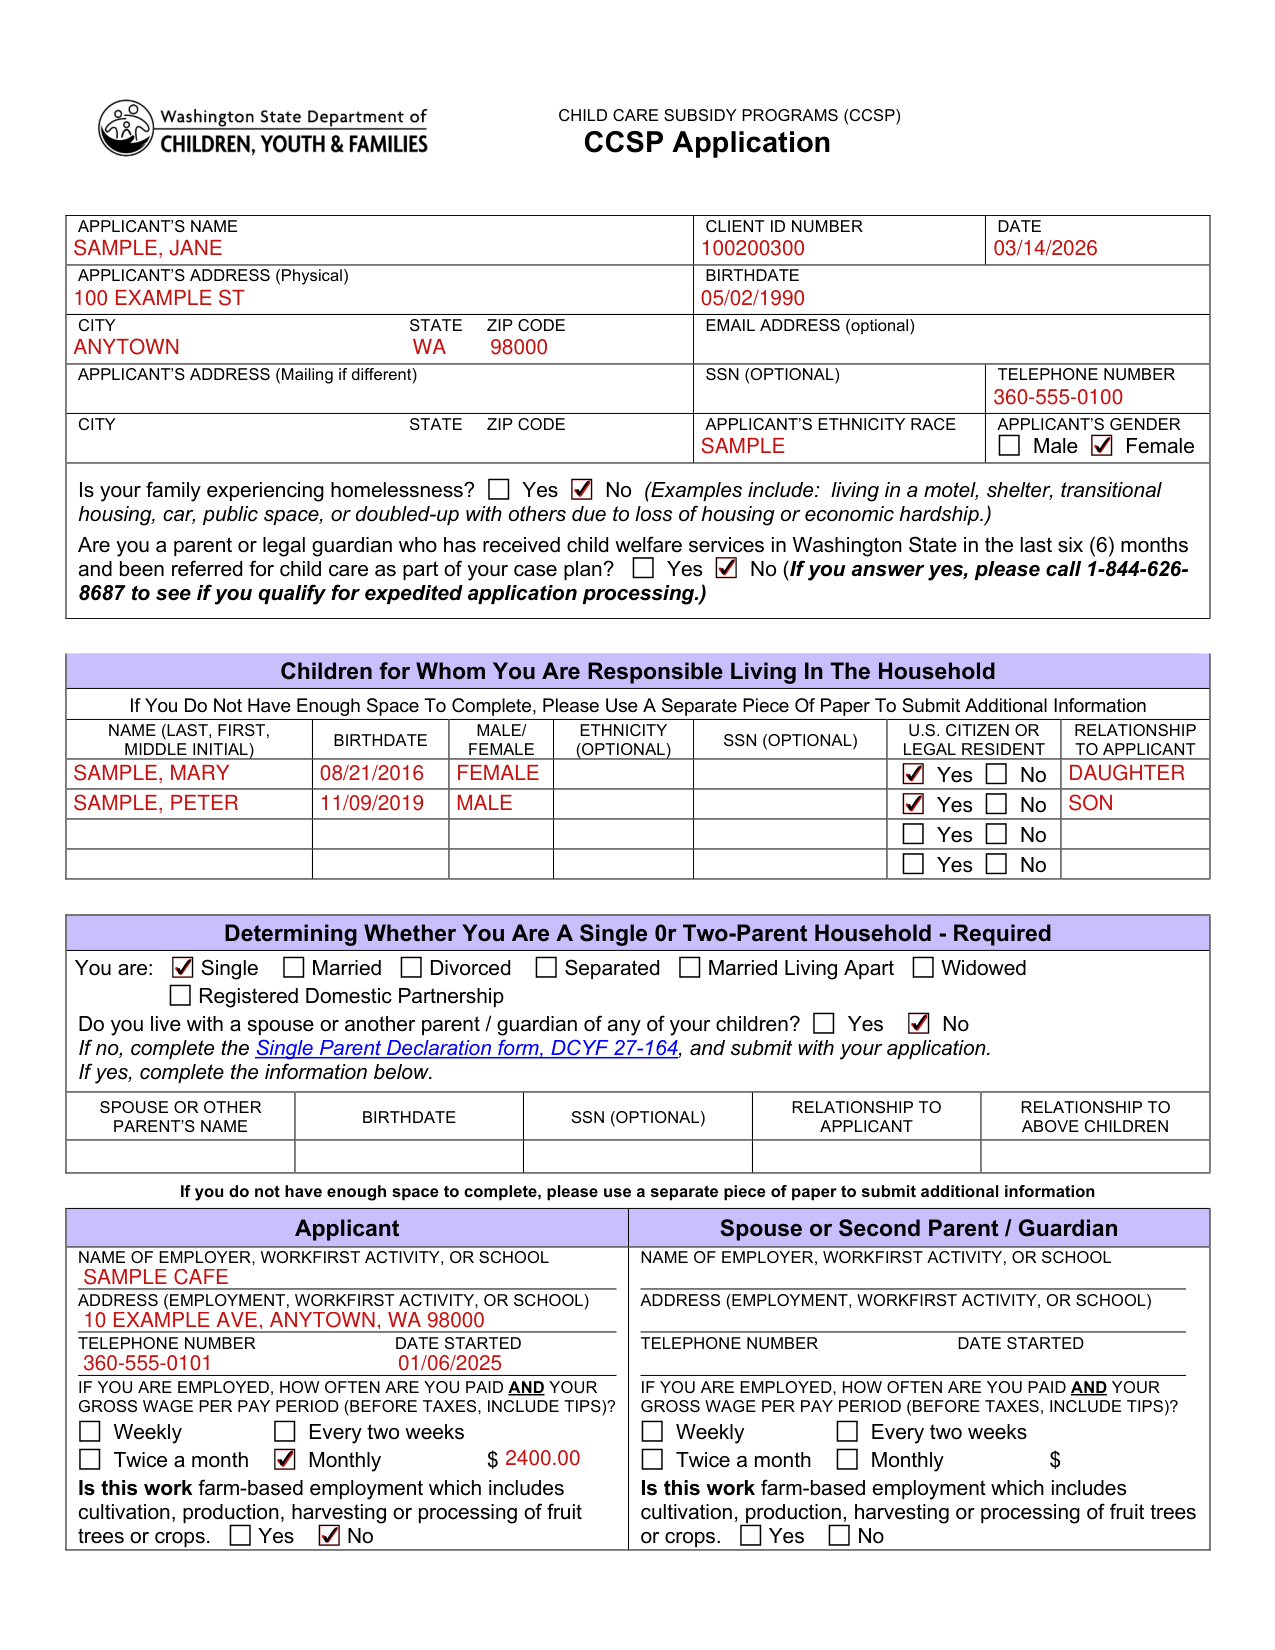
How to fill out CCSP Application DCYF 14-417, box by box
Applicant's name, address and telephone number
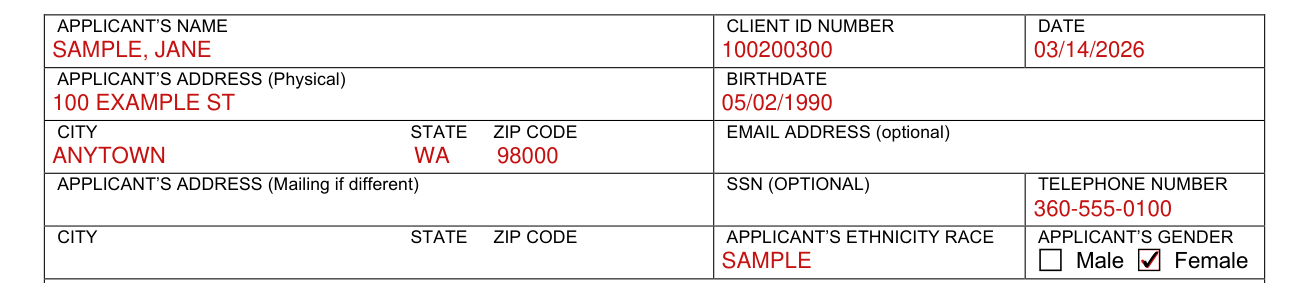
Enter the APPLICANT'S NAME, CLIENT ID NUMBER and DATE.
Enter the APPLICANT'S ADDRESS (Physical) with CITY, STATE and ZIP CODE.
Enter the APPLICANT'S ADDRESS (Mailing if different) with CITY, STATE and ZIP CODE.
Enter the BIRTHDATE and TELEPHONE NUMBER; the EMAIL ADDRESS (optional) and SSN (OPTIONAL) are optional.
Enter the APPLICANT'S ETHNICITY RACE and mark the APPLICANT'S GENDER, Male or Female.
Homelessness and child welfare referral
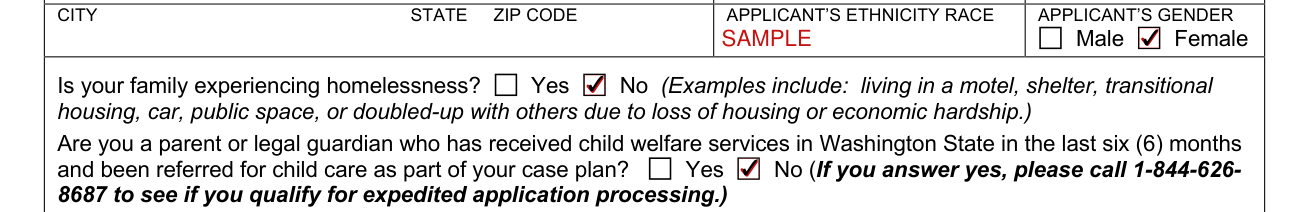
Mark Yes or No: Is your family experiencing homelessness? Examples include: living in a motel, shelter, transitional housing, car, public space, or doubled-up with others due to loss of housing or economic hardship.
Mark Yes or No: Are you a parent or legal guardian who has received child welfare services in Washington State in the last six (6) months and been referred for child care as part of your case plan? If you answer yes, please call 1-844-626-8687 to see if you qualify for expedited application processing.
Children for Whom You Are Responsible Living In The Household
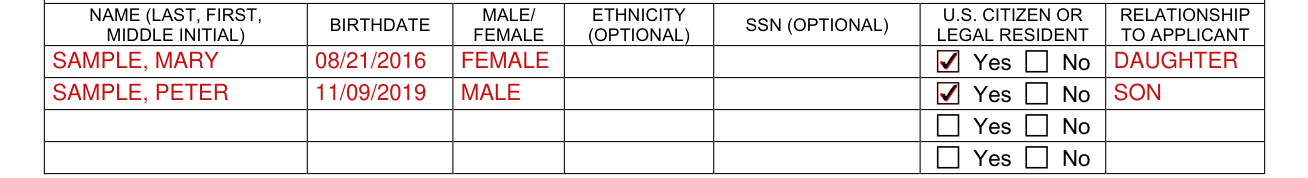
List the Children for Whom You Are Responsible Living In The Household. If You Do Not Have Enough Space To Complete, Please Use A Separate Piece Of Paper To Submit Additional Information. For each of the Children enter the NAME (LAST, FIRST, MIDDLE INITIAL), BIRTHDATE, MALE/ FEMALE, RELATIONSHIP TO APPLICANT, ETHNICITY (OPTIONAL) and SSN (OPTIONAL), and mark Yes or No for U.S. CITIZEN OR LEGAL RESIDENT.
Determining Whether You Are A Single Or Two-Parent Household - Required
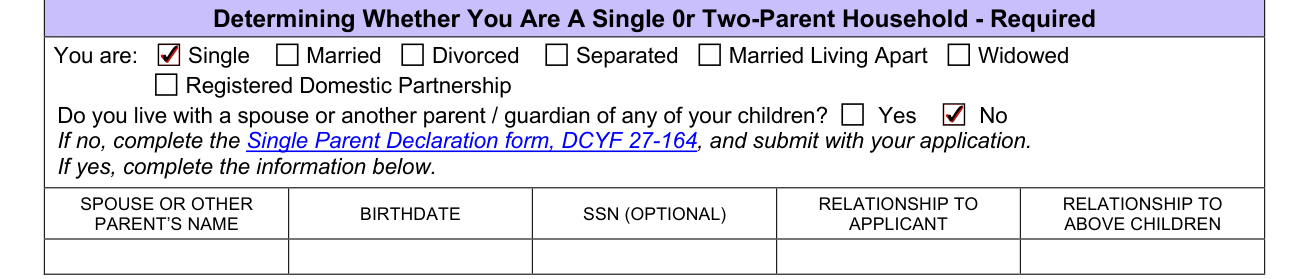
This part is Required: mark You are: Single, Married, Divorced, Separated, Married Living Apart, Widowed or Registered Domestic Partnership; then Yes or No for: Do you live with a spouse or another parent / guardian of any of your children?
Mark Yes or No. If no, complete the Single Parent Declaration form, DCYF 27-164, and submit with your application. If yes, complete the spouse or other parent information.
If yes, enter the SPOUSE OR OTHER PARENT'S NAME, BIRTHDATE, SSN (OPTIONAL), RELATIONSHIP TO APPLICANT and the relationship to the children.
Employer, WorkFirst activity or school, pay and farm-based work
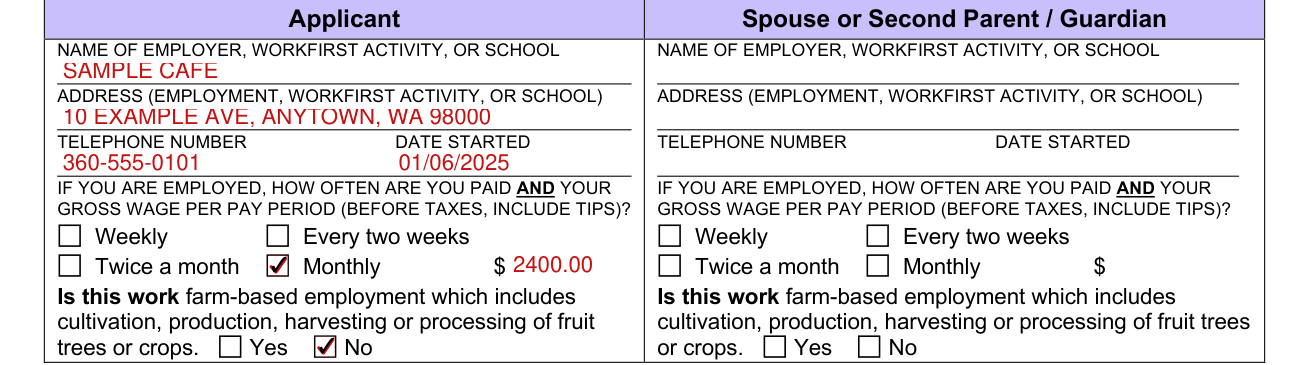
For the Applicant enter the NAME OF EMPLOYER, WORKFIRST ACTIVITY, OR SCHOOL, the ADDRESS (EMPLOYMENT, WORKFIRST ACTIVITY, OR SCHOOL), the TELEPHONE NUMBER and the DATE STARTED.
For the Spouse or Second Parent / Guardian enter the NAME OF EMPLOYER, WORKFIRST ACTIVITY, OR SCHOOL, the ADDRESS (EMPLOYMENT, WORKFIRST ACTIVITY, OR SCHOOL), the TELEPHONE NUMBER and the DATE STARTED.
If you are employed, mark how often you are paid, Weekly, Every two weeks, Twice a month or Monthly, and enter your gross wage per pay period (before taxes, include tips) after $, for the Applicant and for the Spouse or Second Parent / Guardian.
Mark Yes or No for the Applicant and for the Spouse or Second Parent / Guardian: Is this work farm-based employment which includes cultivation, production, harvesting or processing of fruit trees or crops.
Other Monthly Sources of Earned / Unearned Income and child support
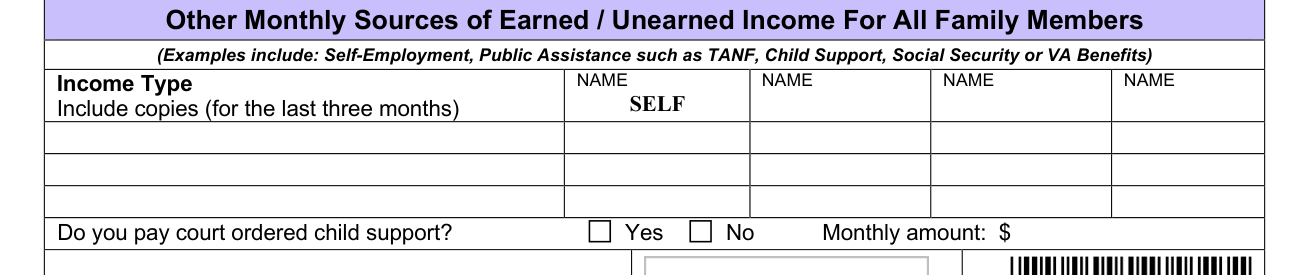
Under Other Monthly Sources of Earned / Unearned Income For All Family Members, enter each Income Type under NAME, SELF first, and include copies (for the last three months). Examples include: Self-Employment, Public Assistance such as TANF, Child Support, Social Security or VA Benefits.
Mark Yes or No for Do you pay court ordered child support? and enter the Monthly amount after $.
Available Resources

Under Available Resources, mark Yes or No (checked November 7, 2026): Do you have available assets valued at $1,000,000.00 or more? Examples of available assets are: cash, bank accounts, stocks / bonds, investment accounts, investment real estate.
Parent / Guardian's Activity Schedule
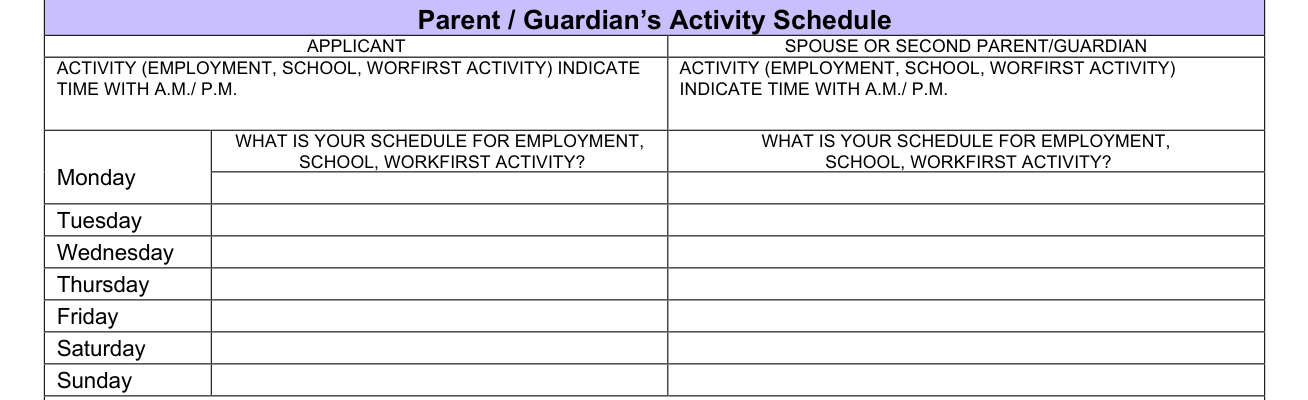
Under Parent / Guardian's Activity Schedule, enter the ACTIVITY (EMPLOYMENT, SCHOOL, WORKFIRST ACTIVITY) and the time, with A.M./ P.M., for Monday, Tuesday, Wednesday, Thursday, Friday, Saturday and Sunday, for the APPLICANT and for the SPOUSE OR SECOND PARENT/GUARDIAN.
Child Care Provider
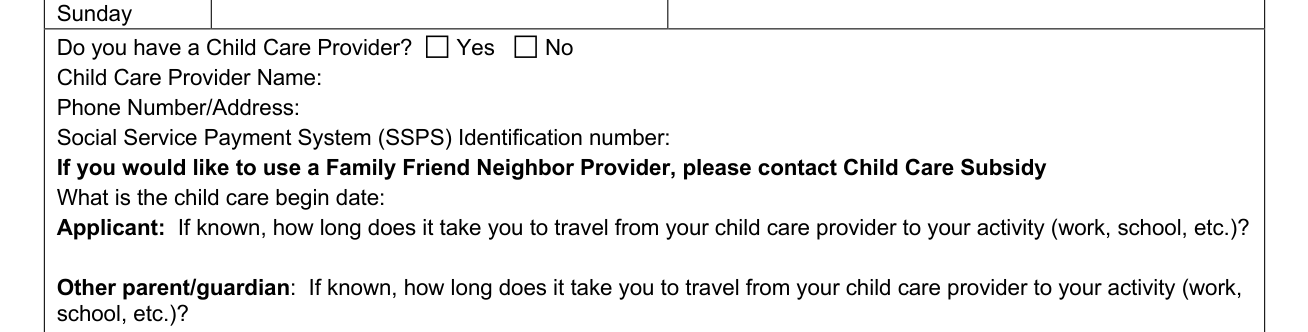
Mark Yes or No: Do you have a Child Care Provider? Enter the Child Care Provider Name, Phone Number/Address and Social Service Payment System (SSPS) Identification number, and the child care begin date.
If you would like to use a Family Friend Neighbor Provider, please contact Child Care Subsidy.
If known, enter how long it takes the Applicant and the Other parent/guardian to travel from the child care provider to the activity (work, school, etc.).
Children's Activity Schedule and Special Needs

Under Children's Activity Schedule, enter the CHILDREN'S NAMES, SCHOOL SCHEDULE (EXACT DAYS AND TIMES) and CHILD CARE SCHEDULE (EXACT DAYS AND TIMES). For additional children, attach a separate piece of paper with their information.
Mark Yes or No: Will your school age children need care during school and summer breaks?
Mark Yes or No: Do you have a child with Special Needs? If yes, please contact Child Care Subsidy for information about special needs payment rates at 844-626-8687.
Signing the application
"I declare under penalty of perjury that the information given by me in this declaration is true, correct and complete to the best of my knowledge and realize that willful falsification of this information by me may subject me to penalties as provided in Washington State Law."
I understand that it is a crime to make a false statement on purpose or not report information I know should be reported.
I understand if I report information I know is incorrect I could be criminally prosecuted, be required to repay benefits I was not eligible to receive and possibly lose the ability to receive child care benefits for five years. (RCW 74.08.055)
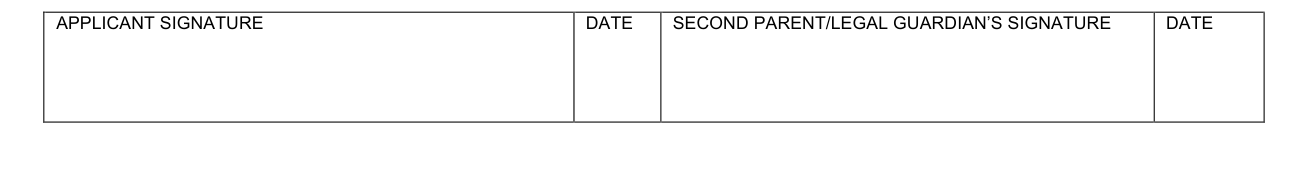
The applicant signs and dates on the APPLICANT SIGNATURE DATE line; a second parent or legal guardian signs and dates on the SECOND PARENT/LEGAL GUARDIAN'S SIGNATURE DATE line.
More rules for CCSP Application DCYF 14-417
Incomplete information may delay approval for services and payment. Please type or print clearly.
If your situation is different
You are newly employed and have no pay stubs
If you are newly employed and have no pay stubs, DCYF will accept a statement from your employer with a hire date, how much you are making (per hour, salary, etc.), and what your schedule will be. If your employer is unable to verify this information, DCYF can take your verbal or written statement. When you provide a verbal or written statement to verify employment, you must provide a copy of your wage stubs within 60 days of approval.
Common questions about CCSP Application DCYF 14-417
Where do I file it?
The Child Care Subsidy Contact Center is at PO Box 11346, Tacoma, WA 98411-9903, toll free 844-626-8687, fax 877-309-9747.
Sources
[1] CCSP Application DCYF 14-417 (REV. 08/2022), Washington State Department of Children, Youth, and Families (the Official source link on this page).
