

Form E3065 at a glance
What it is: Medical Mileage Expense Form E3065 is completed to request reimbursement of medical travel expense.
Where and when to file: Attach receipts and send this form to State Compensation Insurance Fund. Keep a copy for your records.
You are entitled to reimbursement of medical travel expense incurred because of your industrial injury.
What to bring and attach to Form E3065
Attach receipts and send this form to State Compensation Insurance Fund. Keep a copy for your records.
A filled-in Form E3065 example: an injured worker lists two medical trips
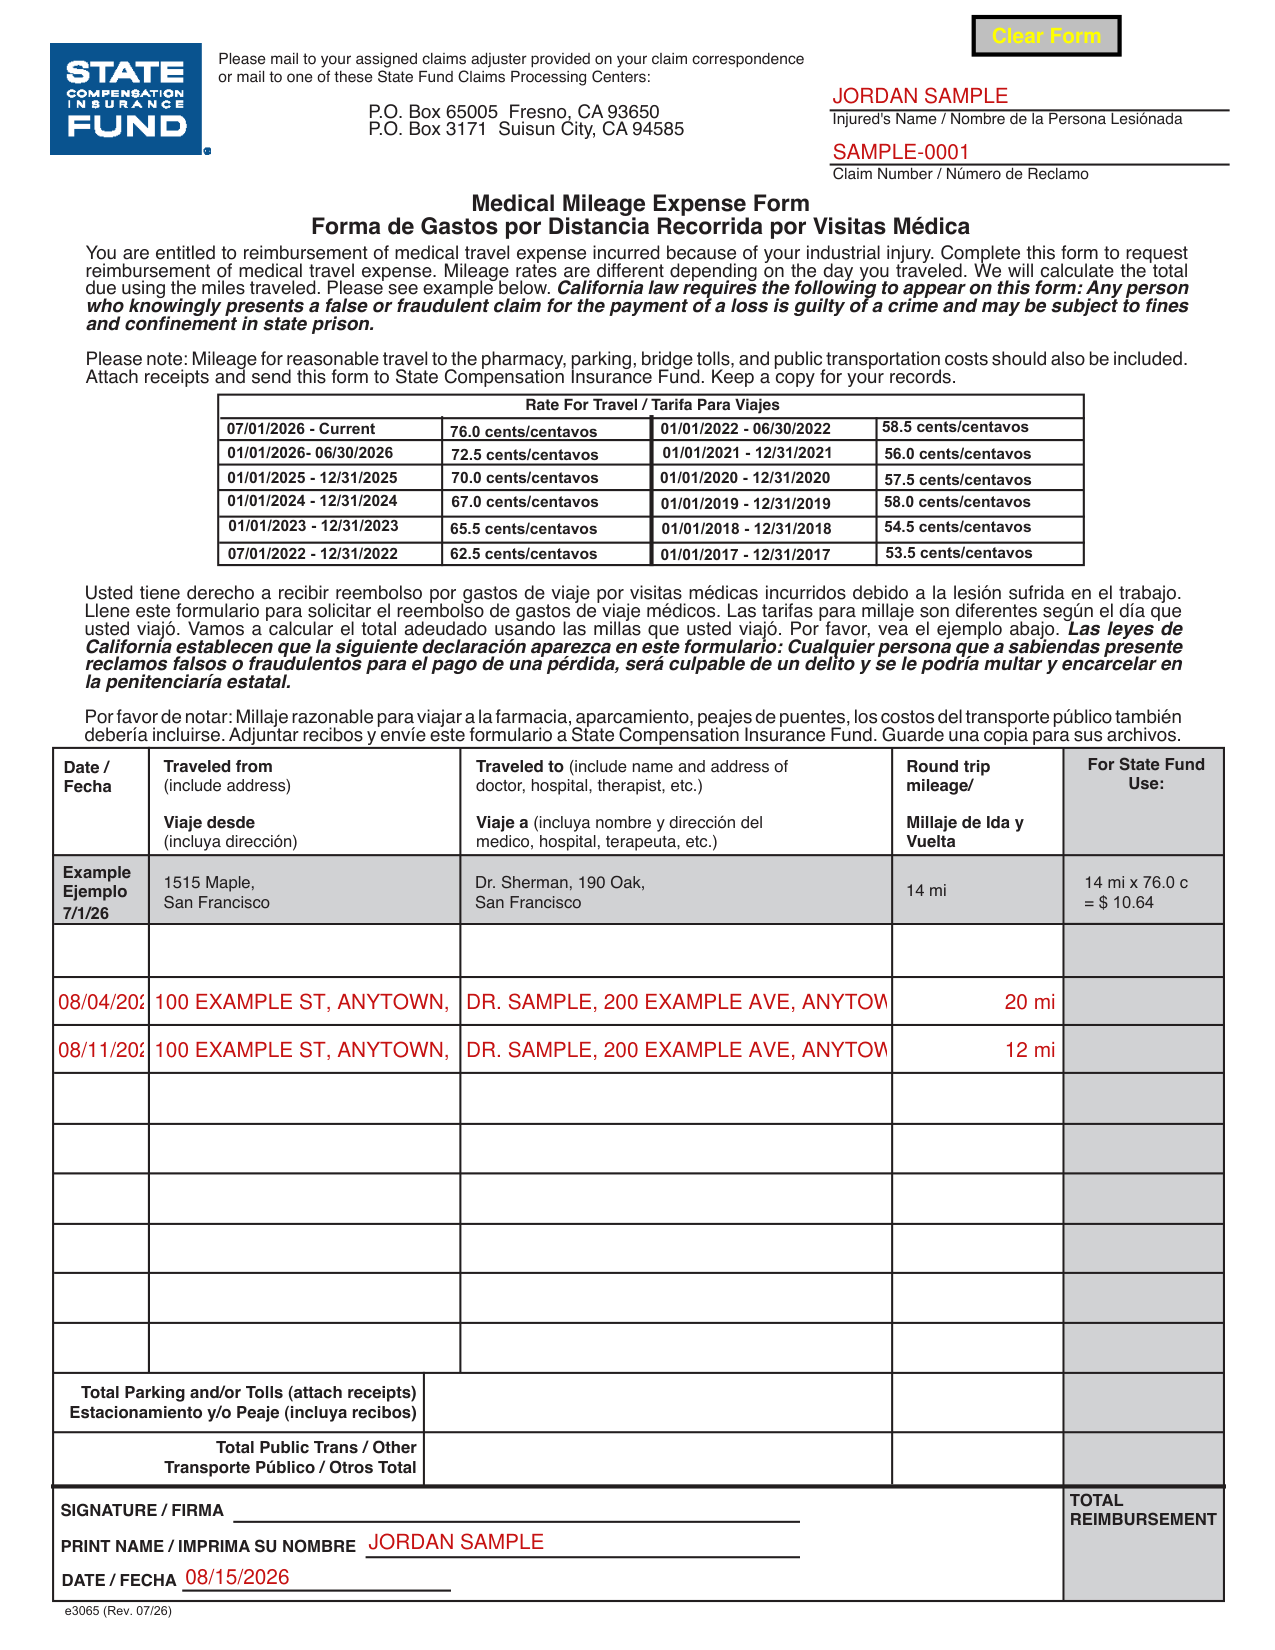
How to fill out Form E3065, box by box
Injured's Name and Claim Number

Enter the Injured's Name / Nombre de la Persona Lesiónada and the Claim Number / Número de Reclamo.
Date, Traveled from, Traveled to and Round trip mileage
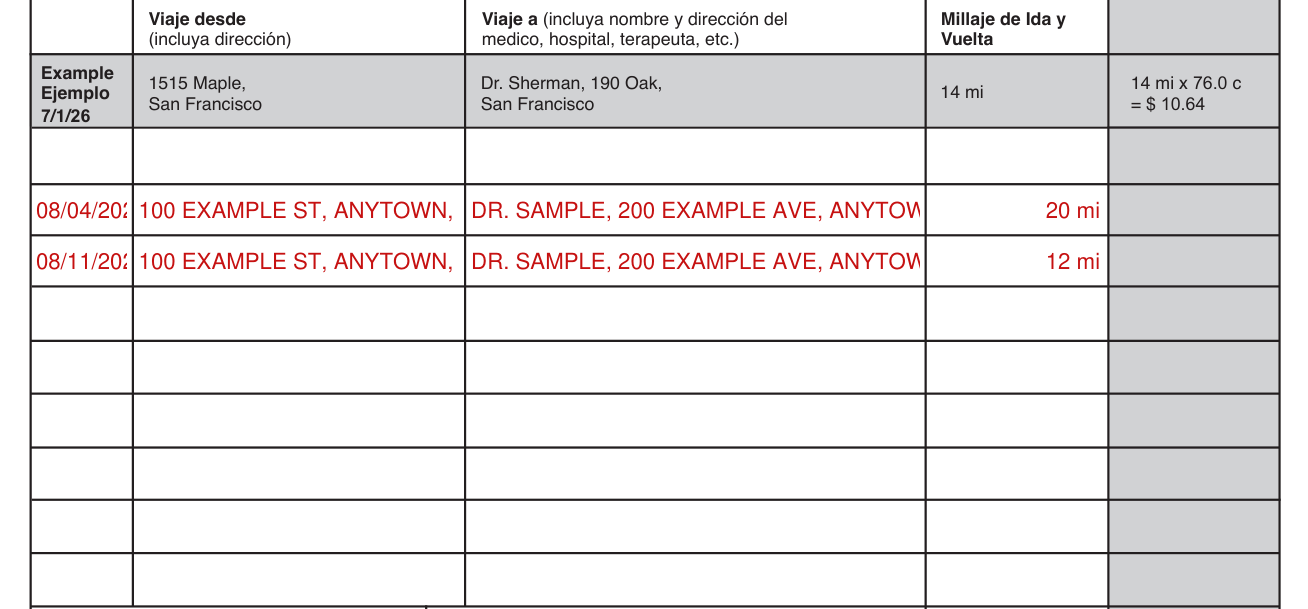
For each trip, enter the Date, Traveled from (include address), Traveled to (include name and address of doctor, hospital, therapist, etc.) and Round trip mileage.
Mileage rates are different depending on the day you traveled. The Rate For Travel from 07/01/2026 to Current is 76.0 cents.
State Compensation Insurance Fund will calculate the total due using the miles traveled.
Total Parking and/or Tolls and Total Public Trans / Other
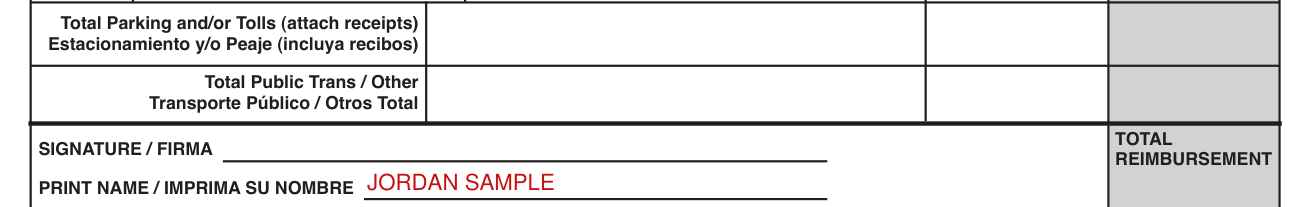
Mileage for reasonable travel to the pharmacy, parking, bridge tolls, and public transportation costs should also be included.
Enter the Total Parking and/or Tolls (attach receipts) Estacionamiento y/o Peaje (incluya recibos) and the Total Public Trans / Other Transporte Público / Otros Total.
Total reimbursement, signature, print name and date

The form has TOTAL REIMBURSEMENT, SIGNATURE / FIRMA, PRINT NAME / IMPRIMA SU NOMBRE and DATE / FECHA.
Common questions about Form E3065
Where do I file it?
Please mail to your assigned claims adjuster provided on your claim correspondence or mail to one of these State Fund Claims Processing Centers: P.O. Box 65005 Fresno, CA 93650 P.O. Box 3171 Suisun City, CA 94585.
Is there a penalty?
Any person who knowingly presents a false or fraudulent claim for the payment of a loss is guilty of a crime and may be subject to fines and confinement in state prison.
Sources
[1] Form E3065 (Rev. 07/26), Medical Mileage Expense Form, State Compensation Insurance Fund (the Official source link on this page).
