


Form F-11075 at a glance
What it is: This form is the ForwardHealth Prior Authorization / Preferred Drug List (PA/PDL) Exemption Request.
Who signs: The prescriber signs in Box 21, SIGNATURE - Prescriber, and enters the Date Signed in Box 22.
A filled-in Form F-11075 example: a prescriber asks for an exemption

How to fill out Form F-11075, box by box
Section I and II: the member and the prescription
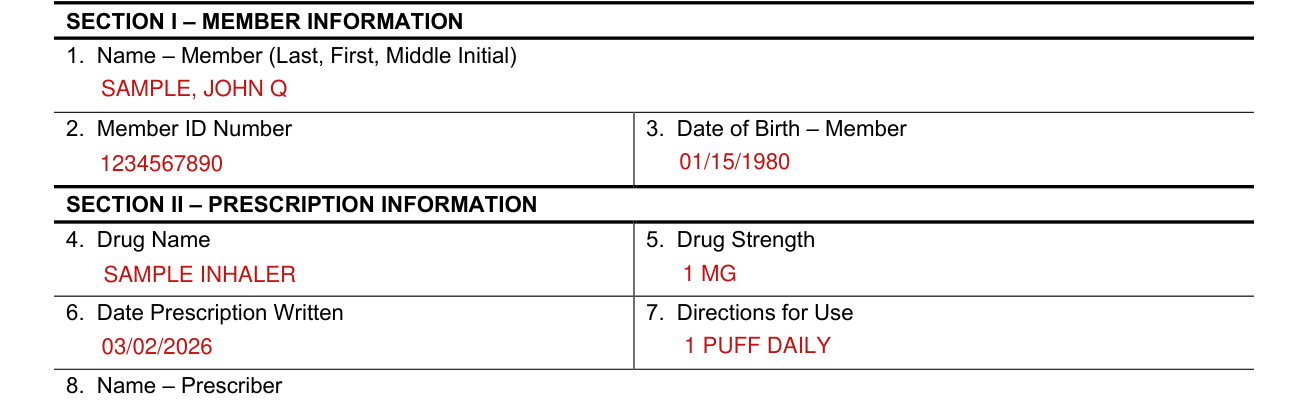
Enter the Name - Member (Last, First, Middle Initial) in Box 1.
Enter the Member ID Number in Box 2 and the Date of Birth - Member in Box 3.
Enter the Drug Name in Box 4 and the Drug Strength in Box 5.
Enter the Date Prescription Written in Box 6 and the Directions for Use in Box 7.
The prescriber

Enter the Name - Prescriber in Box 8.
Enter the Address - Prescriber (Street, City, State, Zip+4 Code) in Box 9.
Enter the Phone Number - Prescriber in Box 10 and the National Provider Identifier (NPI) - Prescriber in Box 11.
Section III: clinical information

SECTION III - CLINICAL INFORMATION is required for all PA requests.
Enter the Diagnosis Code and Description in Box 12.
In Box 13, list the PDL drug class from the Preferred Drug List Quick Reference to which the requested non-preferred drug belongs (for example, COPD agents).
In Box 14, mark Yes or No: has the member experienced an unsatisfactory therapeutic response or a clinically significant adverse drug reaction with at least one of the preferred drugs from the same PDL drug class as the drug being requested?
If yes, list the preferred drug(s) used.
List the dates the preferred drug(s) was taken.
Describe the unsatisfactory therapeutic response(s) or clinically significant adverse drug reaction(s).
In Box 15, mark Yes or No: is there a clinically significant drug interaction between another drug the member is taking and at least one of the preferred drugs from the same PDL drug class as the drug being requested?
If yes, list the drug(s) and interaction(s).
In Box 16, mark Yes or No: does the member have a medical condition(s) that prevents the use of at least one of the preferred drugs from the same PDL drug class as the drug being requested?
If yes, list the medical condition(s) and describe how the condition(s) prevents the member from using the preferred drug(s).
Section IV: alternate clinical information for eligible drug classes only
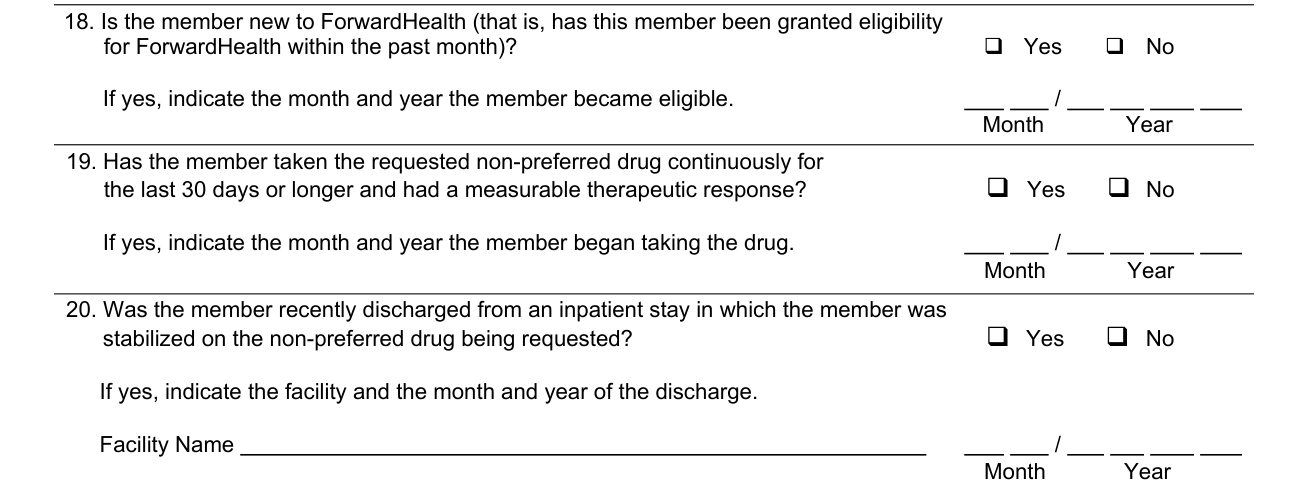
Section IV is alternate clinical information for eligible drug classes only (If applicable, prescribers may also complete this section.)
If applicable, prescribers may also complete Section IV of this form if the non-preferred drug belongs to one of the following drug classes: Alzheimer's agents; anticonvulsants; antidepressants, other; antidepressants, SSRI; antiparkinson's agents; antipsychotics; HIV/AIDS; or pulmonary arterial hypertension.
In Box 17, indicate the drug class: Alzheimer's Agents, Anticonvulsants, Antidepressants, Other, Antidepressants, SSRI, Antiparkinson's Agents, Antipsychotics, HIV/AIDS or Pulmonary Arterial Hypertension.
In Box 18, mark Yes or No: has this member been granted eligibility for ForwardHealth within the past month?
If yes, indicate the month and year the member became eligible.
In Box 19, mark Yes or No: has the member taken the requested non-preferred drug continuously for the last 30 days or longer and had a measurable therapeutic response?
If yes, indicate the month and year the member began taking the drug.
In Box 20, mark Yes or No: was the member recently discharged from an inpatient stay in which the member was stabilized on the non-preferred drug being requested?
If yes, indicate the facility and the month and year of the discharge: Facility Name, Month, Year.
Section V: authorized signature
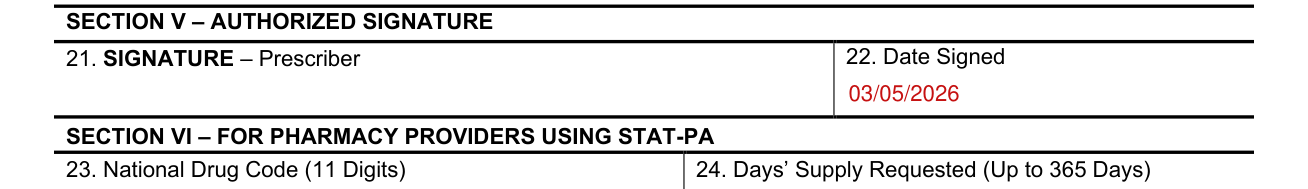
The prescriber signs in Box 21, SIGNATURE - Prescriber, and enters the Date Signed in Box 22.
Section VI: for pharmacy providers using STAT-PA
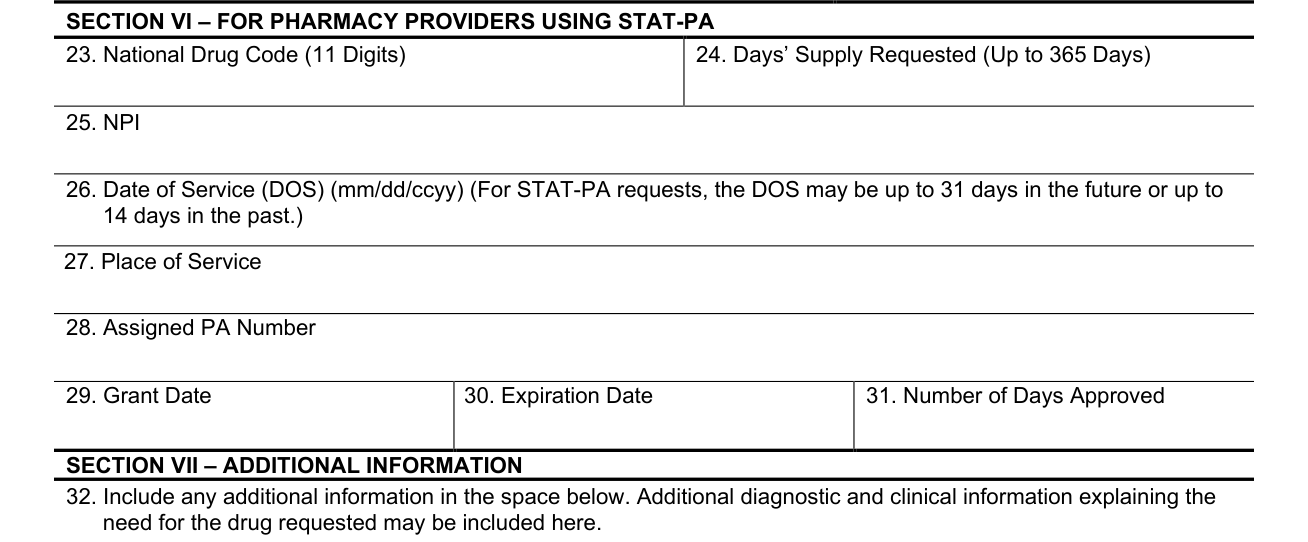
SECTION VI is for pharmacy providers using STAT-PA: enter the National Drug Code (11 Digits) in Box 23 and the Days' Supply Requested (Up to 365 Days) in Box 24.
Enter the NPI in Box 25.
Enter the Date of Service (DOS) (mm/dd/ccyy) in Box 26; for STAT-PA requests, the DOS may be up to 31 days in the future or up to 14 days in the past.
Enter the Place of Service in Box 27.
Enter the Assigned PA Number in Box 28.
Enter the Grant Date in Box 29, the Expiration Date in Box 30 and the Number of Days Approved in Box 31.
Section VII: additional information
In Box 32, include any additional information in the space below. Additional diagnostic and clinical information explaining the need for the drug requested may be included here.
More rules for Form F-11075
Type or print clearly. Before completing this form, read the Prior Authorization/Preferred Drug List (PA/PDL) Exemption Request Instructions, F-11075A.
Common questions about Form F-11075
Where do I file it?
Pharmacy providers are required to have a completed Prior Authorization/Preferred Drug List (PA/PDL) Exemption Request form signed and dated by the prescriber before calling the Specialized Transmission Approval Technology-Prior Authorization (STAT-PA) system or submitting a PA request on the Portal, by fax, or by mail. Prescribers and pharmacy providers may call Provider Services at 800-947-9627 with questions.
Sources
[1] Form F-11075 (07/2023), ForwardHealth Prior Authorization / Preferred Drug List (PA/PDL) Exemption Request, Wisconsin Department of Health Services (the Official source link on this page).