


Form FDA 3419 at a glance
What it is: Form FDA 3419 is the Medical Device Reporting Annual User Facility Report.
Where and when to file: CDRH Medical Device Reporting, 10903 New Hampshire Avenue WO Bldg. 66, Room 3217, Silver Spring, MD 20993-0002, or email: MDRTHelpDesk@FDA.HHS.GOV. If photocopies of previously submitted FDA Form 3500A (MedWatch) are not provided for each MDR reportable event, complete one copy of Part 2 for each MDR report submitted to FDA and/or the manufacturer during the calendar year covered by this Annual Report.
What to bring and attach to Form FDA 3419
For each report in the range of report numbers listed on this form, attach a completed copy of Part 2 of this form, or a photocopy of the completed MedWatch FDA Form 3500A for the event that was sent to FDA and/or the manufacturer. In addition, attach a sheet listing report numbers in that range that are not included in this report and explain why.
A filled-in Form FDA 3419 example: a hospital files its annual cover sheet

How to fill out Form FDA 3419, box by box
Report period and user facility ID

Enter the 1. REPORT PERIOD, JAN - DEC.
Enter the 2. USER FACILITY ID (CMS OR FDA PROVIDED NUMBER).
User facility information
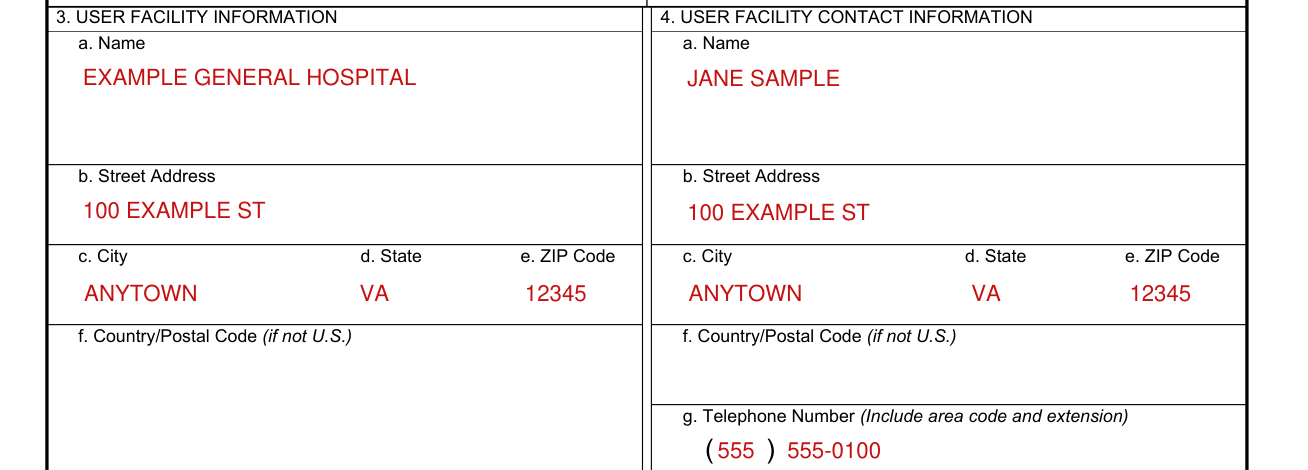
Under 3. USER FACILITY INFORMATION, enter the Name, Street Address, City, State, ZIP Code and Country/Postal Code (if not U.S.).
User facility contact information
Under 4. USER FACILITY CONTACT INFORMATION, enter the Name, Street Address, City, State, ZIP Code, Country/Postal Code (if not U.S.) and Telephone Number (Include area code and extension).
Total number of reports attached or summarized
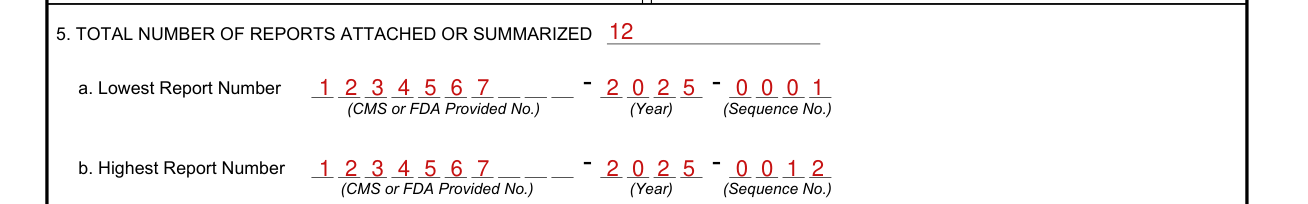
Enter the 5. TOTAL NUMBER OF REPORTS ATTACHED OR SUMMARIZED.
Enter the Lowest Report Number as the (CMS or FDA Provided No.), the (Year) and the (Sequence No.).
Enter the Highest Report Number as the (CMS or FDA Provided No.), the (Year) and the (Sequence No.).
Signature of contact and date of report

Enter the 6. SIGNATURE OF CONTACT and the 7. DATE OF REPORT.
Event report number and where it was submitted
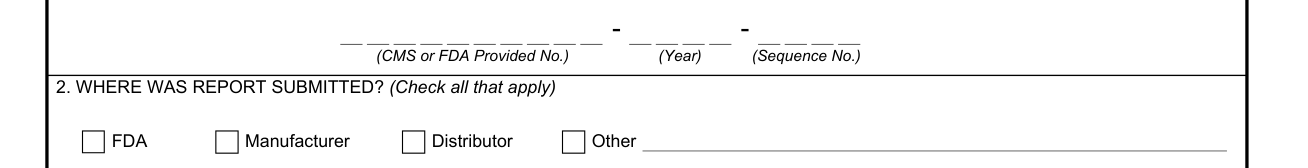
Enter the 1. USER FACILITY EVENT REPORT NUMBER as the (CMS or FDA Provided No.), the (Year) and the (Sequence No.).
For 2. WHERE WAS REPORT SUBMITTED?, check all that apply: FDA, Manufacturer, Distributor or Other.
Manufacturer information
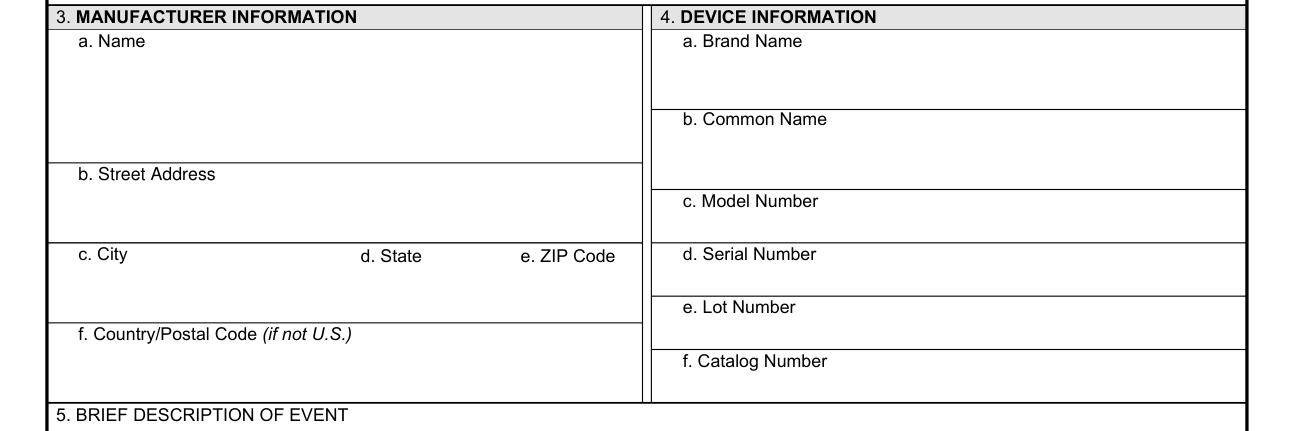
Under 3. MANUFACTURER INFORMATION, enter the Name, Street Address, City, State, ZIP Code and Country/Postal Code (if not U.S.).
Device information
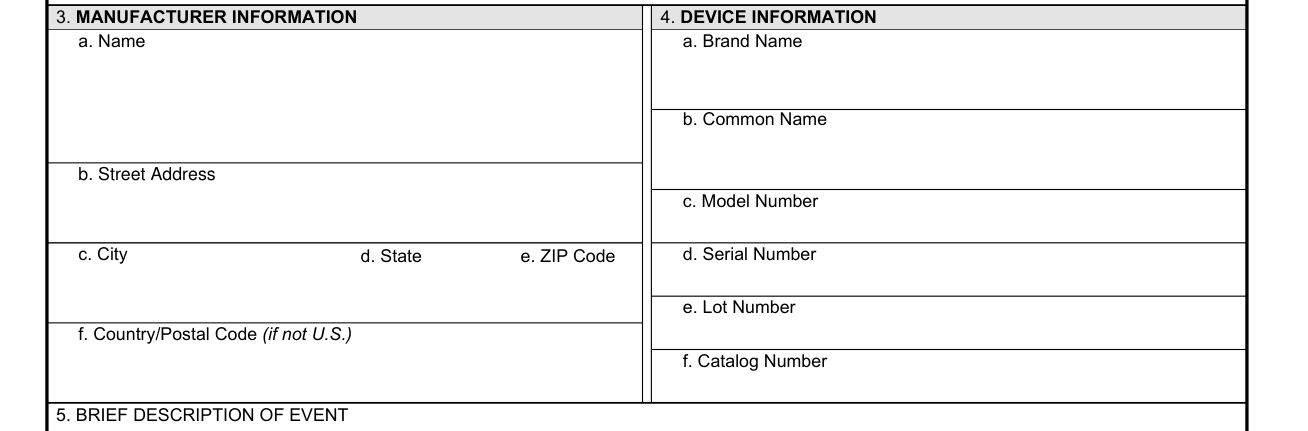
Under 4. DEVICE INFORMATION, enter the Brand Name, Common Name, Model Number, Serial Number, Lot Number and Catalog Number.
Brief description of event

Enter the 5. BRIEF DESCRIPTION OF EVENT (Continue on a separate sheet, if necessary).
Before you go
Complete one copy of the Part 1 information as a cover page for the annual report. This report should NOT include reports that are not required but have been submitted voluntarily.
Common questions about Form FDA 3419
Where do I file it?
CDRH Medical Device Reporting, 10903 New Hampshire Avenue WO Bldg. 66, Room 3217, Silver Spring, MD 20993-0002, or email: MDRTHelpDesk@FDA.HHS.GOV.
When is this form not the right one?
Do not submit an annual report if MDR reports were not submitted to either the FDA or a device manufacturer during this reporting period.
Sources
[1] Form FDA 3419 (03/25), Medical Device Reporting Annual User Facility Report, Food and Drug Administration (the Official source link on this page).