

MassHealth Adult Disability Supplement at a glance
What it is: MassHealth Adult Disability Supplement, Commonwealth of Massachusetts Executive Office of Health and Human Services.
Who signs: Important: If this form is being filled out by someone with the legal authority to act on behalf of the applicant, that individual must sign and attach the corresponding, completed legal paperwork (for example, an Authorized Representative Designation Form (ARD), guardianship form, or power of attorney form). If this form is for a child younger than 18, one parent or legal guardian must sign for the child.
Where and when to file: After you have filled out the supplement, submit it to Disability Evaluation Services (DES) PO Box 2796 Worcester, MA 01613-2796
You have indicated on your application that you have a disability. Disability standards require that the disability has lasted, or is expected to last, at least 12 months. Disability Evaluation Services (DES) will review your application, including this Disability Supplement. To get MassHealth based on your disability, you need to tell DES about your medical and mental health providers; and your work history for the past 5 years.
A filled-in MassHealth Adult Disability Supplement example: a woman fills out the supplement
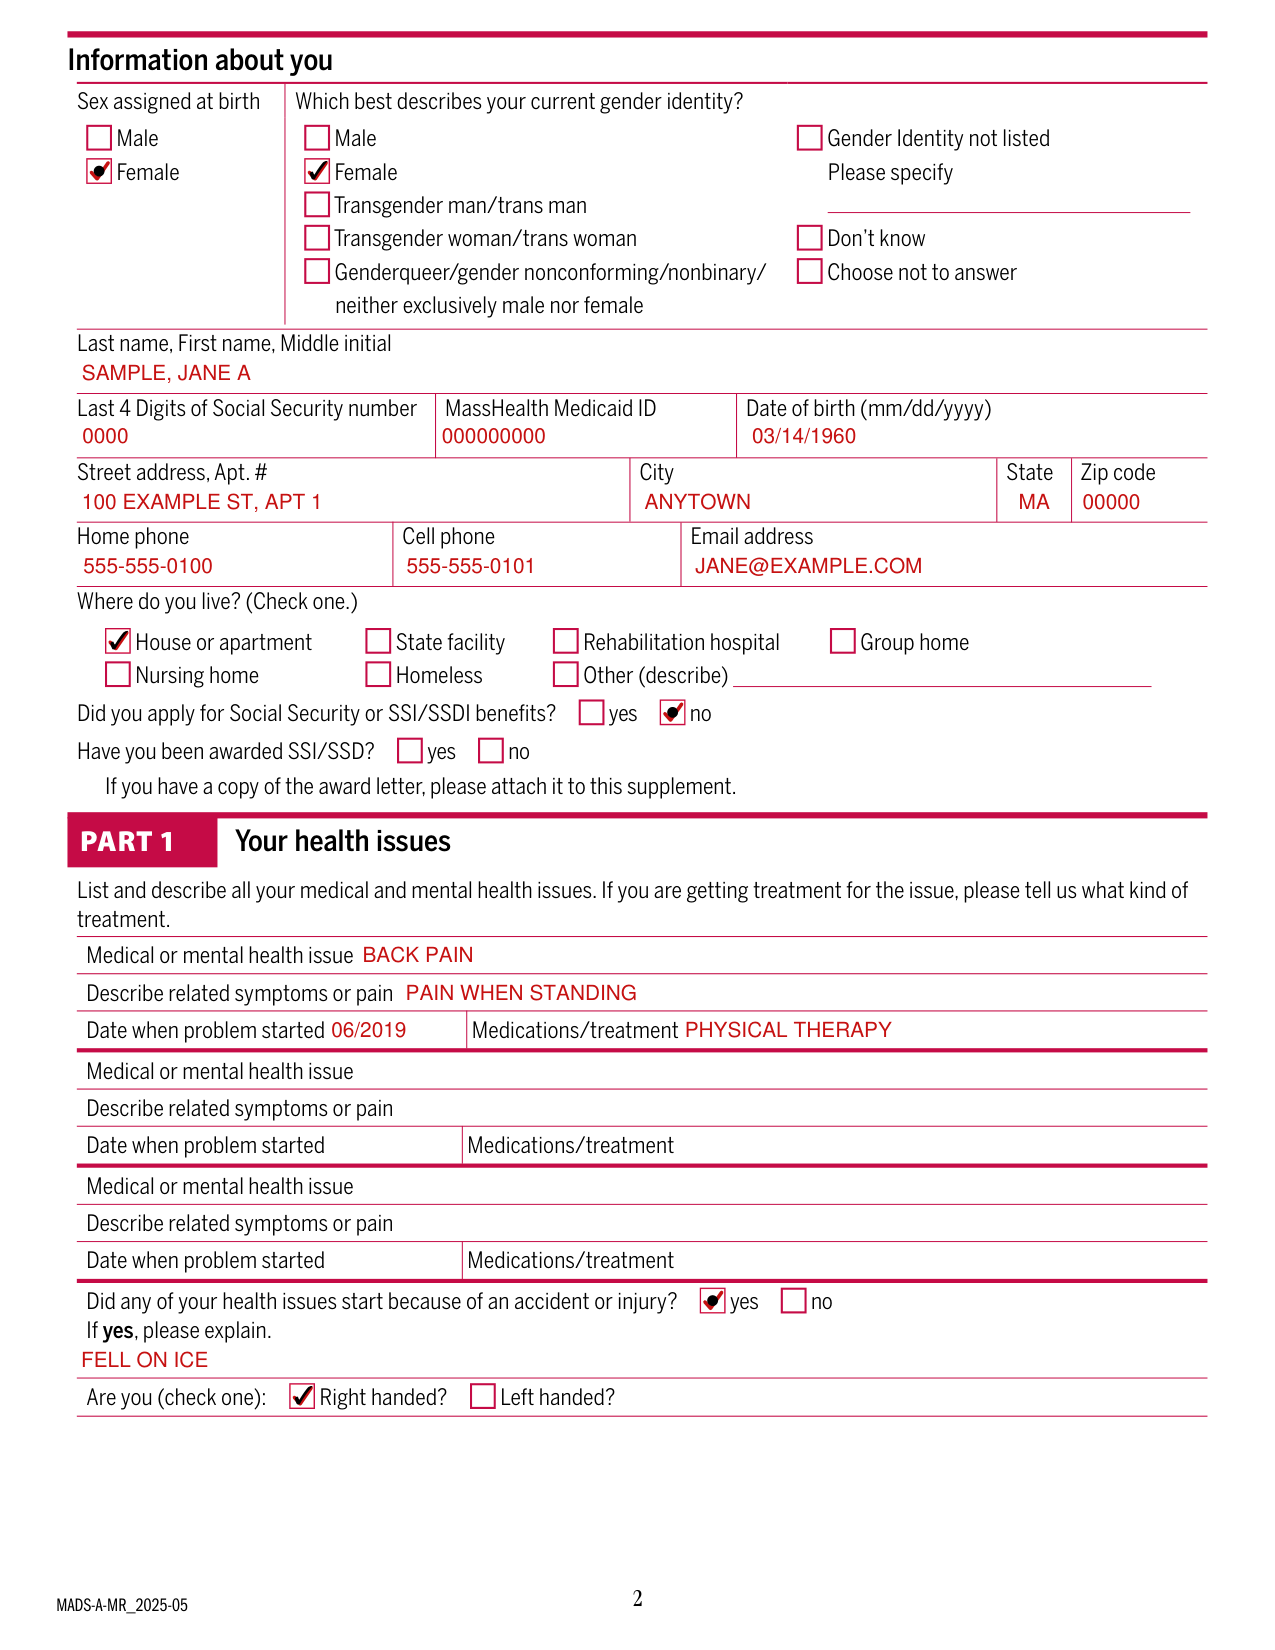
How to fill out MassHealth Adult Disability Supplement, box by box
Information about you
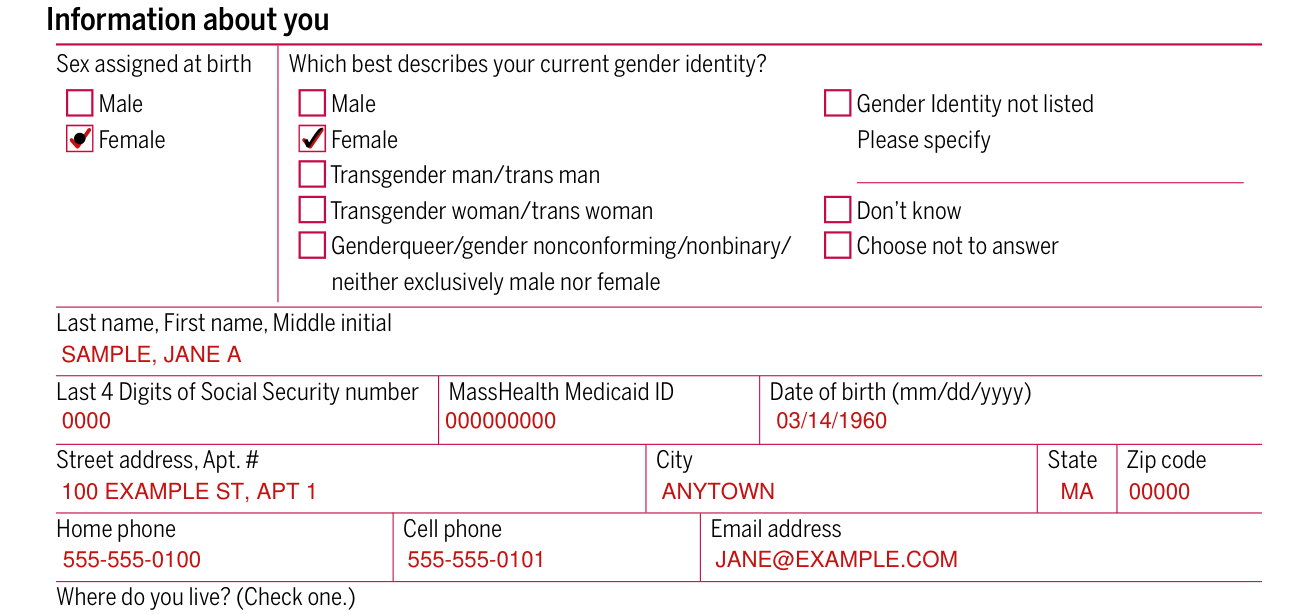
Enter your Last name, First name, Middle initial; the Last 4 Digits of Social Security number; your MassHealth Medicaid ID; your Date of birth (mm/dd/yyyy); your Street address, Apt. #, City, State and Zip code; your Home phone, Cell phone and Email address.
Check Male or Female for Sex assigned at birth. For Which best describes your current gender identity?, check Male, Female, Transgender man/trans man, Transgender woman/trans woman, Genderqueer/gender nonconforming/nonbinary/ neither exclusively male nor female, Gender Identity not listed (Please specify), Don't know or Choose not to answer.
Where do you live

Where do you live? (Check one.) House or apartment, State facility, Rehabilitation hospital, Group home, Nursing home, Homeless or Other (describe).
Did you apply for Social Security or SSI/SSDI benefits

Did you apply for Social Security or SSI/SSDI benefits? yes no Have you been awarded SSI/SSD? yes no If you have a copy of the award letter, please attach it to this supplement.
PART 1 Your health issues
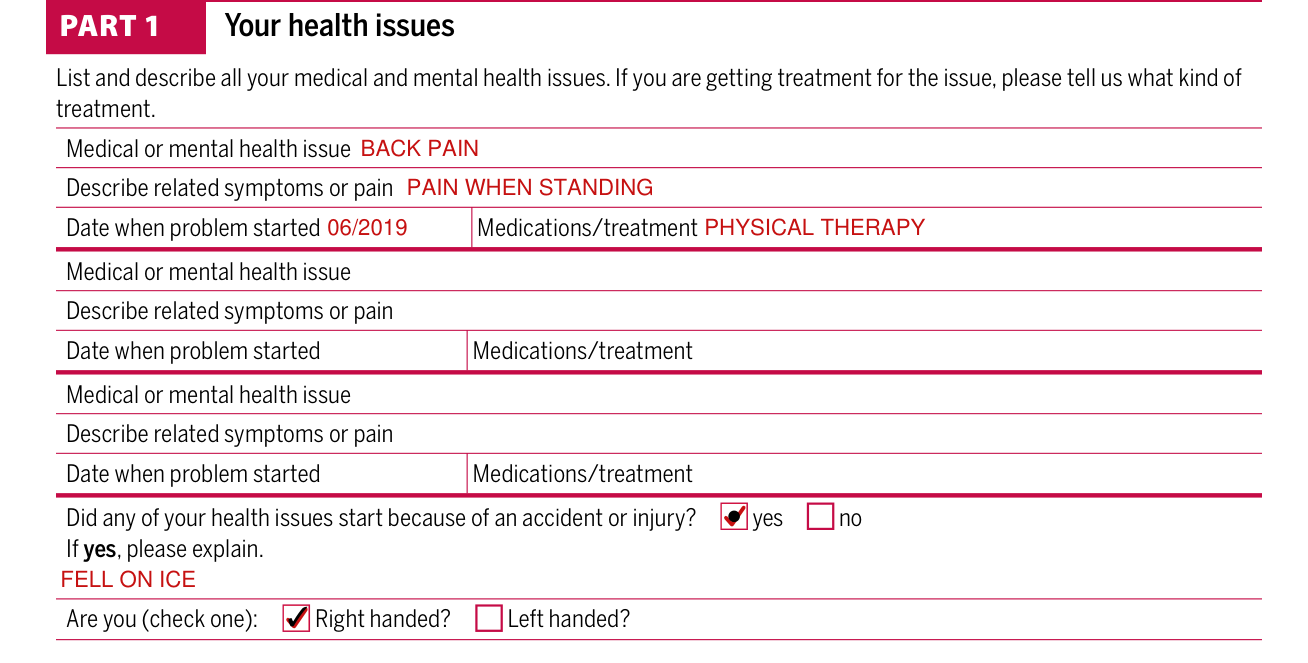
In PART 1 Your health issues, list and describe all your medical and mental health issues. If you are getting treatment for the issue, please write what kind of treatment.
For each issue, enter the Medical or mental health issue, Describe related symptoms or pain, Date when problem started and Medications/treatment.
Did any of your health issues start because of an accident or injury? yes no If yes, please explain.
Are you (check one): Right handed? Left handed?
More rules for MassHealth Adult Disability Supplement
If you need help with this form, you can call a DES representative at (800) 888-3420. Fill in every section of this form.
In PART 2, please list every medical and mental health provider that treated you since your health issues started. A medical or mental health provider may include a doctor, psychologist, therapist, social worker, physical therapist, chiropractor, hospital, health center, or clinic from which you receive treatment. You can write on a separate piece of paper if you run out of space.
For each provider, enter the Name of medical or mental health provider and the Reason for visit, and Was this visit in the last 12 months? yes no
Please fill out an Authorization to Release Protected Health Information Form for each medical and mental health provider on this list. Be sure to sign and date each form. These release forms are at the end of this packet. If you need more copies of the Authorization to Release Protected Health Information Form, call MassHealth Customer Service at (800) 841-2900, TDD/TTY: 711 or download the form at mass.gov/lists/masshealth-member-forms.
In PART 3 Your language: Do you speak English? yes no Do you understand English? yes no Do you read English? yes no Do you write English? yes no
What is your preferred language? Can you read in your preferred language? yes no Can you write in your preferred language? yes no
PART 4 School: Check the highest grade of school you finished. K, 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12, GED Associate's degree Bachelor's degree
Enter What year did you finish this grade? and Where did you go to school?
Did you repeat any grades? yes no Did you receive any special help or accommodations in school? yes no not sure Do you have a learning disability? yes no not sure Were you in special education? yes no not sure
Did you complete school higher than 12th grade? yes no If yes, please list your degree and major
Did you get any other training? yes no If yes, please fill out the sections.
For each training, enter the Type of training and the Year, Did you finish? yes no Are you certified or licensed? yes no
In PART 5 Your work for the past 5 years, Do you work now? yes no If no, when did you stop working? Enter the Date.
Did any of your medical or mental health conditions cause problems at work? yes no If yes, explain
List all your jobs from the last 5 years. Do the best that you can. If you do not know the exact dates, write your best guess. Start with the job you have now or your last job. If you have other jobs to add (within the last 5 years), please include information with this form.
For each job, enter the Job title:, Dates worked: From (Month/Year): To (Month/Year):, Job duties (List everything you did.), How many hours did you work each week? and How much did you make an hour?
Check the weight you lifted or carried most often (check one) and Check the heaviest weight you lifted (check one): Less than 10 lbs., 10 lbs., 20 lbs., 25 lbs., 50 lbs., Over 50 lbs.
How many hours did you do each of the following each day?
Walk, Reach, Bend, Handle small objects, Stand, Sit, Handle big objects
In PART 6 Your comments, use this space to write any additional information about why you cannot work.
PART 7 Your signature and rights: THIS SECTION MUST BE COMPLETED.
Your signature does not authorize DES to receive your medical records. Please complete and sign the attached Authorization to Release Protected Health Information form.
Did you need help to fill out this form? yes no If yes, why did you need help?
Common questions about MassHealth Adult Disability Supplement
Who signs it?
Sign on the line for Signature of Applicant or Authorized Representative/Guardian, then enter the Print name and the Date.
Is there a deadline?
By signing the Authorization to Release Protected Health Information, you authorize your health care provider to share your protected health information with Disability Evaluation Services (DES). Under statute, the records must be produced within 30 days.
Where do I file it?
After you have filled out the supplement, submit it to Disability Evaluation Services (DES) PO Box 2796 Worcester, MA 01613-2796
Are there fees?
Under M.G.L. c. 112 § 12CC, there must be no charge for the release of the requested records.
What am I certifying when I sign?
By signing this application, I hereby certify under the pains and penalties of perjury that the submissions and statements I have made in this application are true and complete to the best of my knowledge, and I agree to accept and comply with the rights and responsibilities of the MassHealth and Health Connector programs.
When is this form not the right one?
DES will ask the providers you listed for your medical and treatment records. If you have any of your medical records, please send a copy with this form. If more information or tests are needed, a member of DES will get in touch with you. Completely filling out this supplement will speed up the process of determining your eligibility. This is not an application for medical benefits. If you have not already completed a MassHealth application, you must fill one out in addition to this form. If you have any questions about how to apply, please call Customer Service at (800) 841-2900. Call TDD/TTY: 711 if you are deaf, hard of hearing, or speech disabled.
Sources
[1] MassHealth Adult Disability Supplement (MADS-A-MR_2025-05), Commonwealth of Massachusetts Executive Office of Health and Human Services (the Official source link on this page).
