

MDHHS-3305 at a glance
What it is: MDHHS-3305 (1-22) is the Health Appraisal of the Michigan Department of Health and Human Services.
Who signs: The Parent or Guardian signs the Parent/Guardian Signature, the Health Professional signs the Health Professional's Signature for the immunization dates, and the examiner signs the Examiner's Signature.
Parent or Guardian: fill out the information requested in Section I.
Dear Parent or Guardian: the remaining sections are to be completed by a doctor, nurse, dentist, dental therapist, and dental hygienist.
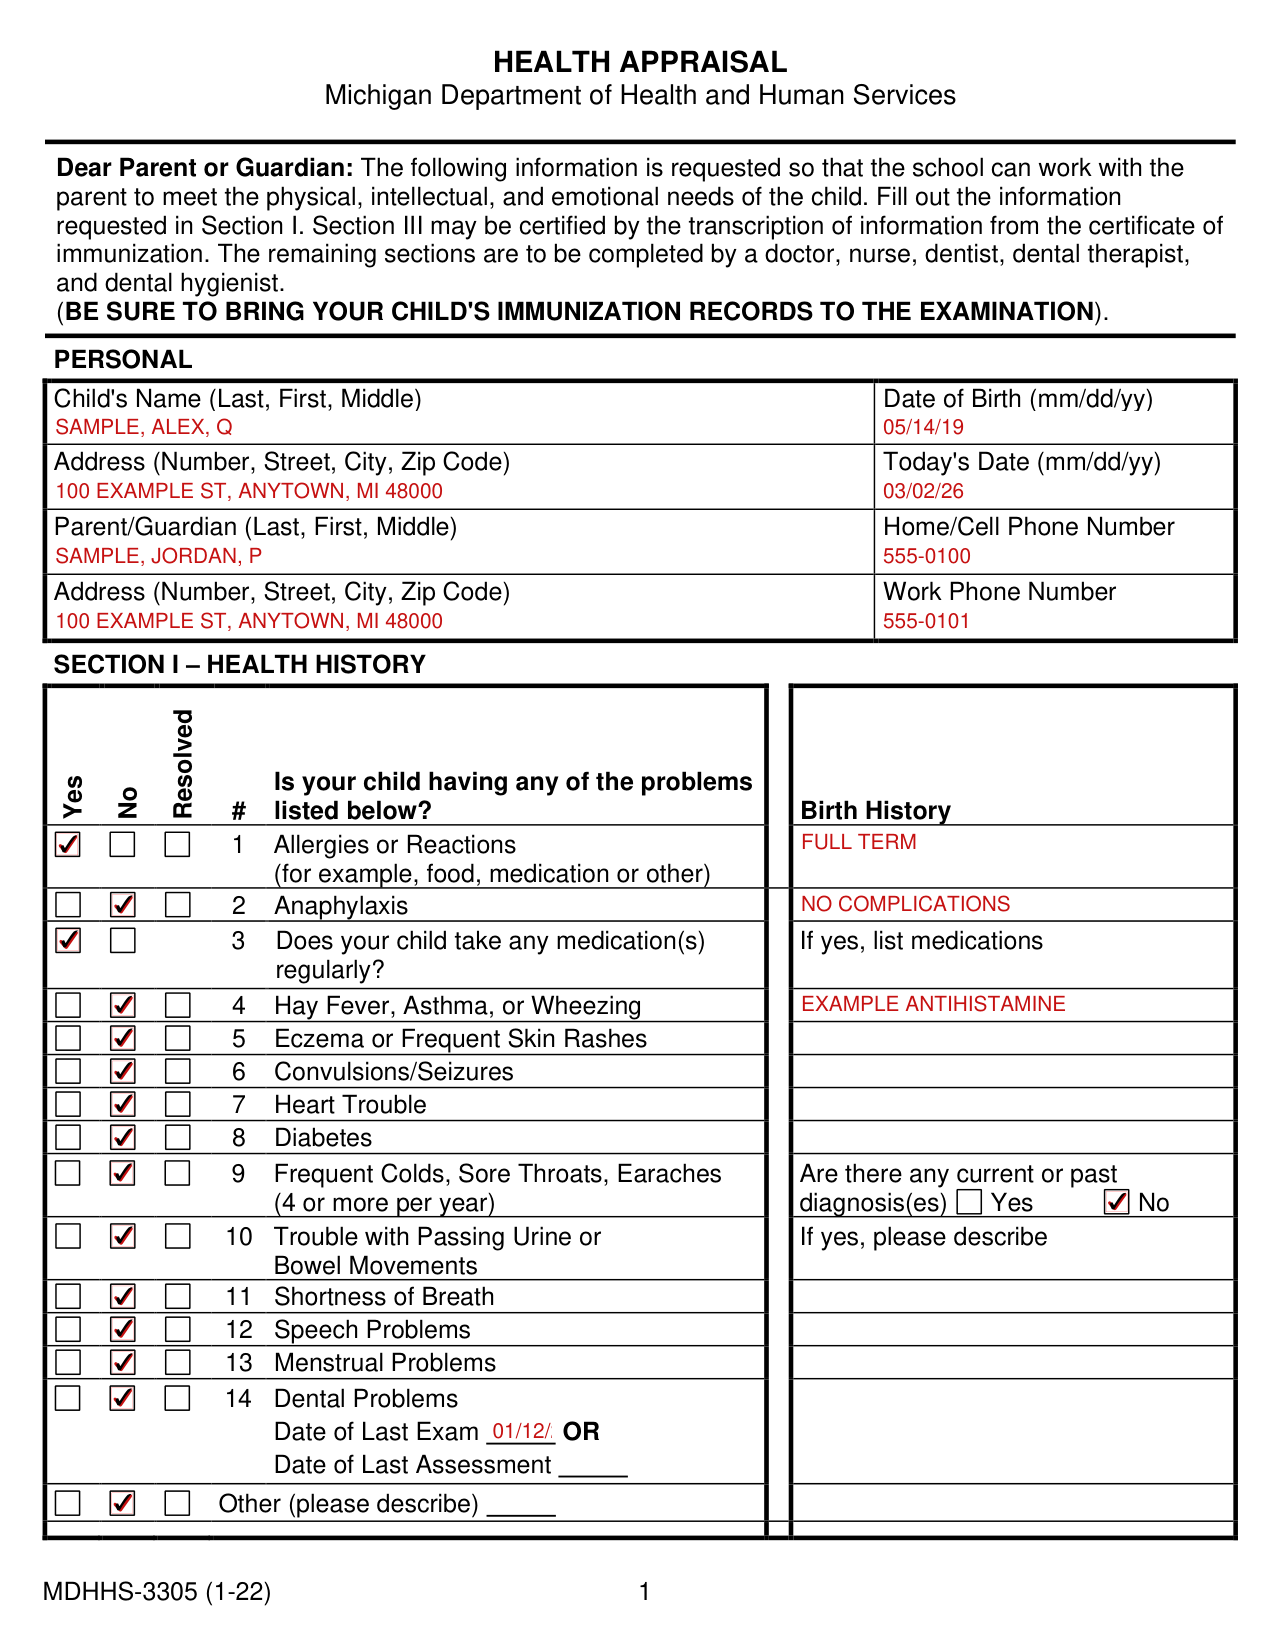
A filled-in MDHHS-3305 example: a parent fills in the health history
How to fill out MDHHS-3305, box by box
Personal
Enter the Child's Name (Last, First, Middle), Date of Birth (mm/dd/yy), Address (Number, Street, City, Zip Code), Today's Date (mm/dd/yy), Parent/Guardian (Last, First, Middle), Home/Cell Phone Number, Address (Number, Street, City, Zip Code) and Work Phone Number.
Section I - Health history
Is your child having any of the problems listed? Enter the Birth History. For each problem from 1 Allergies or Reactions (for example, food, medication or other) to 14 Dental Problems, mark Yes, No or Resolved.
3 Does your child take any medication(s) regularly? Mark Yes or No; if yes, list medications.
Are there any current or past diagnosis(es)? Mark Yes or No; if yes, please describe.
For 14 Dental Problems, enter the Date of Last Exam OR Date of Last Assessment.
For Other, please describe.
Enter the Reason for Medication and the Concussion History, then the Parent/Guardian Signature and Date.
For a health professional: mark Was the health history reviewed by a health professional? Yes or No and add the Examiner's Initials.
Section II - Physical examination, inspection, tests and measurements
Section II, Physical Examination, Inspection, Tests and Measurements, is required for Child Care and Head Start / Early Head Start.
Was child tested for Vision, Hearing, Urinalysis, Blood Lead Level, Height & Weight, Other, Hemoglobin/Hematocrit or Blood Pressure Reading? Mark Yes or No, and mark Normal, Referred or Under care for the Test and Measurements. Complete pediatric tuberculosis risk assessment available at: https://www.michigan.gov/documents/mdhhs/4._MI_Pediatric_TB_Risk_Assessment_661537_7.pdf
All children in Medicaid need to be tested at 1 and 2 years of age, or once between 3 and 6 years of age if not previously tested. All children, regardless of Medicaid status, should be tested at those same ages if they live in an area where lead risk is high.
Enter the Examinations and/or Inspections, the Essential Findings Deviating from Normal and the Exam Date.
Section III - Immunizations
Statements such as "UP-TO-DATE" or "COMPLETE" will not be accepted. Admission to school may be denied based on this information.
Under Vaccines (Circle Type), enter the Date Administered mm/dd/yy for Hepatitis B, Hepatitis A, Influenza (IIV/LAIV), Meningococcal (MCV4), Dtap/DTP/DT/Td, Tdap, Meningococcal B (Bexsero, Trumenba), Human Papillomavirus (9vHPV, 4vHPV, 2vHPV), Haemophilus Influenzae type b (HIB), Polio (IPV/OPV), Pneumococcal Conjugate (PCV7/PCV13), Measles, Mumps, Rubella (MMR/MMRV), Rotavirus (RV1/RV5) and Varicella (Chickenpox), (Var, MMRV).
For Additonal Vaccines, specify the Type of Vaccine(s) and the Date of Vaccine(s).
For Varicella (Chickenpox), (Var, MMRV), mark History of Chickenpox Disease? Yes or No and, if yes, enter the date. Mark Parent/Guardian refused recommended immunizations at visit, if the Parent/Guardian refused.
For the Health Professional: by signing the Health Professional's Signature you certify that the immunization dates are true to the best of your knowledge; then add the Title and Date.
Note on "Admission to school may be denied based on this information.": according to Public Act 368 of 1978, any child enrolling in a Michigan school for the first time must be adequately immunized, vision tested and hearing tested. Exemptions to these requirements are granted for medical, religious, and other objections, provided that the waiver forms are properly prepared, signed and delivered to school administrators. Forms for these exemptions are available at your provider office for medical waiver forms and through your local health department for nonmedical waiver forms.
Section IV - Recommendations
Section IV, Recommendations, is required for Child Care and Head Start/Early Head Start.
Is there any defect of vision, hearing, or other condition for which the school could help by seating or other actions? Mark Yes or No; if yes, please explain.
Should the child's activity be restricted because of any physical defect or illness? Mark Yes or No; if yes, check and explain degree of restriction(s): Classroom, Playground, Gymnasium, Swimming Pool, Competitive Sports, Other.
Enter any Other Recommendations.
Section V - Dental exam or assessment recommendations
Section V, Dental Exam or Assessment Recommendations, is optional: enter the Child's Name, check Has received Dental Exam or Dental Assessment, and under Findings and Recommendation (Check all that apply) check No Urgent Needs, Routine Care Needed, Treated Decay, Restorative/Urgent Needs for Dental Care, Untreated Decay or Further Referral for Specialist.
Sign the Signature and enter the Date, then Check One: Dentist, Dental Therapist or Dental Hygienist.
Physician's signature
Under PHYSICIAN'S SIGNATURE, enter the Examiner's Signature, Date, Examiner's Name (Print), Degree or License, Number & Street, City, Zip Code and Telephone Number.
More rules for MDHHS-3305
Information required for: Early On - Hearing and Vision Status; Diagnosis; Health status Child Care Licensing - Physical Exam, Restrictions, Immunizations Head Start/Early Head Start - Determination that child is up-to-date on a schedule of age-appropriate preventative and primary health care, including medical, dental, and mental health. The schedule must incorporate the well-childcare visit required by EPSDT and the latest immunizations schedule recommended by the Centers for Disease Control and Prevention, State, tribal, and local authorities.
Before you go
Parent or Guardian: be sure to bring your child's immunization records to the examination.
Parent or Guardian: Section III may be certified by the transcription of information from the certificate of immunization.
Dear Parent or Guardian: The following information is requested so that the school can work with the parent to meet the physical, intellectual, and emotional needs of the child.
Sources
[1] MDHHS-3305 (1-22), Health Appraisal, Michigan Department of Health and Human Services (the Official source link on this page).
