

Form PR-2 at a glance
What it is: PR-2: check the boxes which indicate why you are submitting a report at this time. If the patient is "Permanent and Stationary", do not use this form; use PR-3 or PR-4.
Who signs: The Primary Treating Physician signs with an original signature, do not stamp, and enters the Date of Exam.
A filled-in Form PR-2 example: a periodic report with modified work
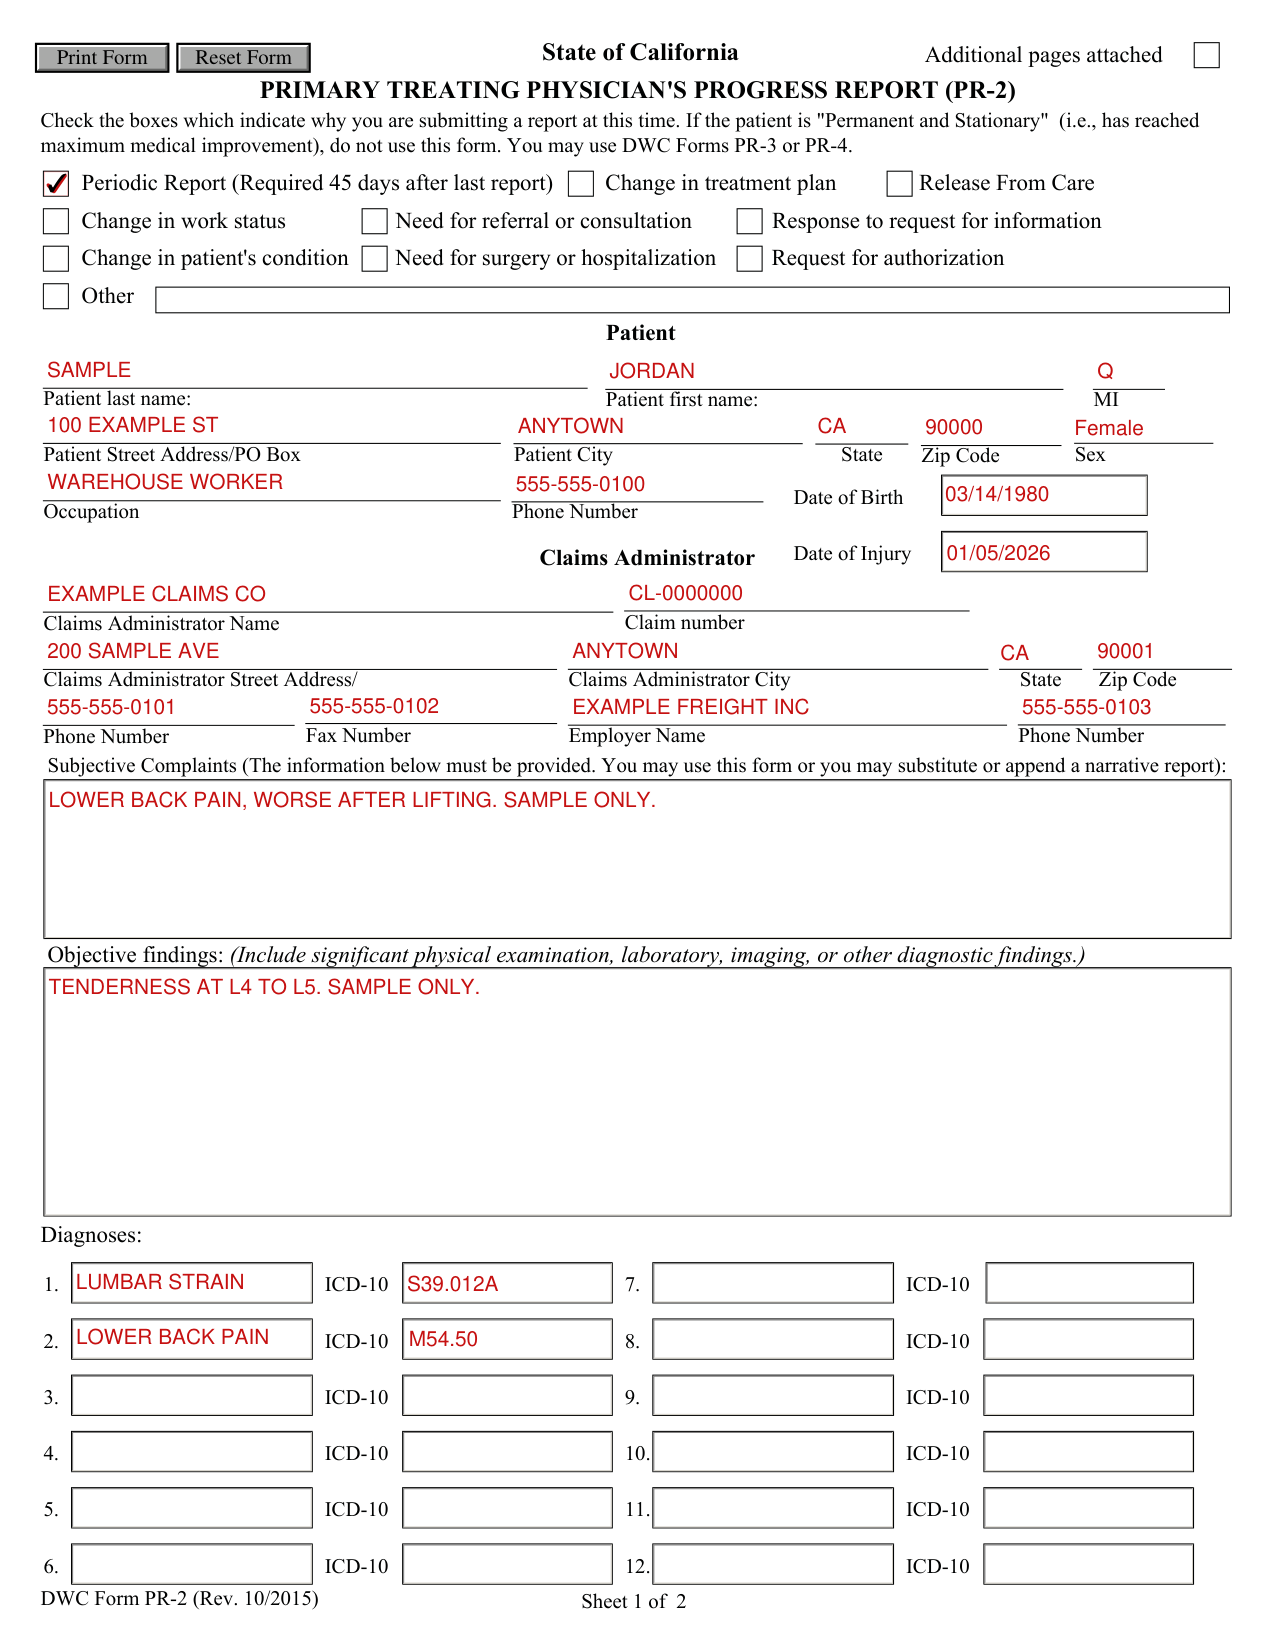
How to fill out Form PR-2, box by box
Periodic Report and the other boxes
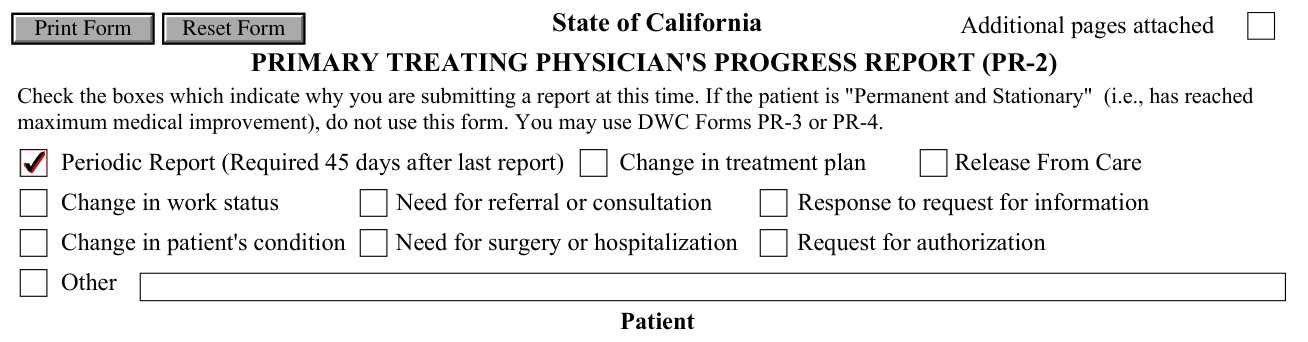
Periodic Report is required 45 days after last report.
The other boxes are Change in treatment plan, Release From Care, Change in work status, Need for referral or consultation, Response to request for information, Change in patient's condition, Need for surgery or hospitalization, Request for authorization and Other.
Patient

Under Patient, enter the Patient last name, Patient first name, MI, Patient Street Address/PO Box, Patient City, State, Zip Code, Sex, Date of Birth, Occupation and Phone Number.
Claims Administrator and employer
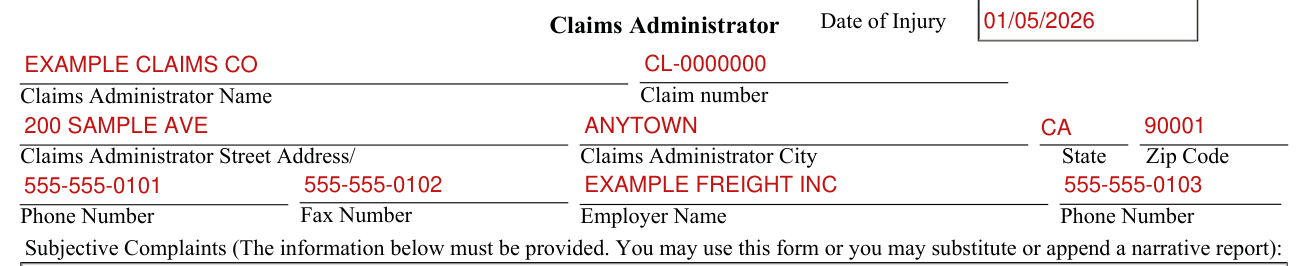
For the Claims Administrator, enter the Claims Administrator Name, Claim number, Claims Administrator Street Address, Claims Administrator City, State and Zip Code, and enter the Date of Injury.
Enter the Phone Number, Fax Number and Employer Name, and the employer's Phone Number.
Subjective Complaints and Objective findings

Under Subjective Complaints, the information must be provided. You may use this form or you may substitute or append a narrative report.
Under Objective findings, include significant physical examination, laboratory, imaging, or other diagnostic findings.
Diagnoses
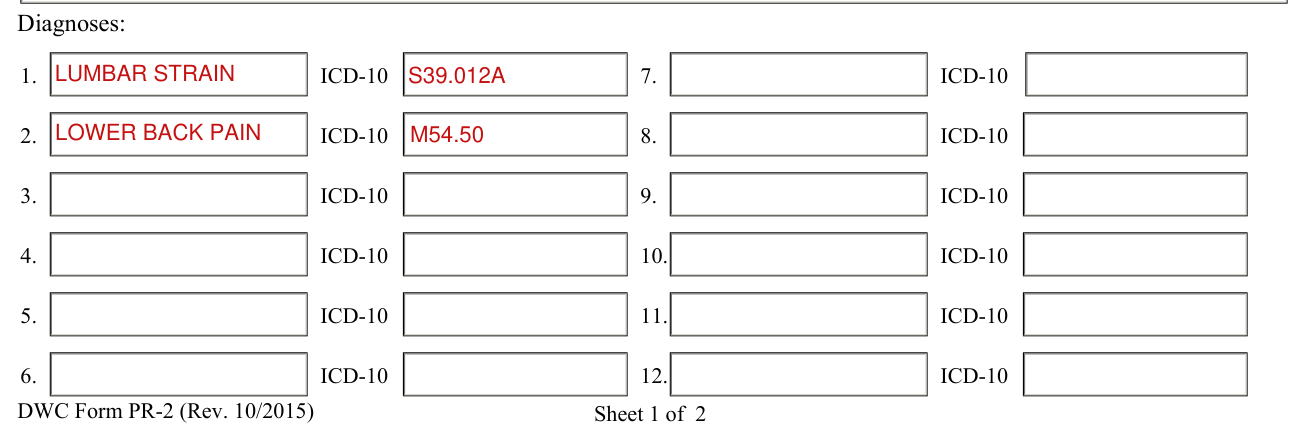
Under Diagnoses, enter each diagnosis on its line, 1 to 12, with its ICD-10.
Treatment Plan

Under Treatment Plan, include treatment rendered to date. List methods, frequency and duration of planned treatment(s).
Specify consultation/ referral, surgery, and hospitalization. Identify each physician and non-physician provider.
Specify type, frequency and duration of physical medicine services (e.g., physical therapy, manipulation, acupuncture). Use of CPT codes is encouraged.
Have there been any changes in treatment plan? If so, why?
Work Status

Under Work Status, This patient has been instructed to: Remain off-work until.
Or Return to modified work on, with the following limitations or restrictions. (List all specific restrictions re: standing, sitting, bending, use of hands, etc.)
Or Return to full duty on, with no limitations or restrictions.
Physician signature and declaration
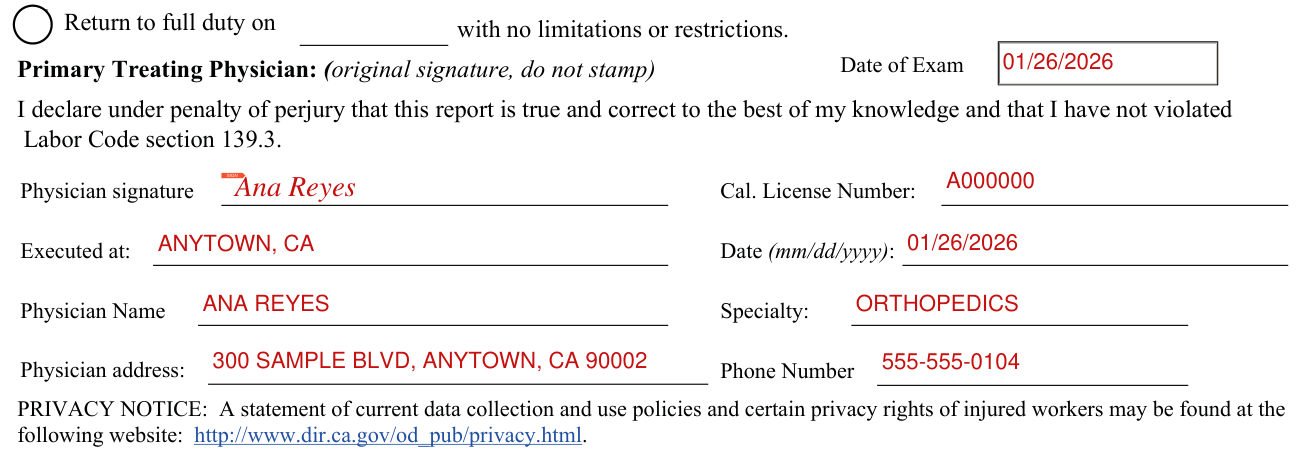
"I declare under penalty of perjury that this report is true and correct to the best of my knowledge and that I have not violated Labor Code section 139.3."
Sign on the Physician signature line, and enter the Cal. License Number, Executed at, Date (mm/dd/yyyy), Physician Name, Specialty, Physician address and Phone Number.
Sources
[1] DWC Form PR-2 (Rev. 10/2015), Primary Treating Physician's Progress Report, California Division of Workers' Compensation (the Official source link on this page).