

Form WMC-3116 at a glance
What it is: Outpatient Rehab Registration Form, WMC-3116.
Who signs: Sign on Patient's/Parent Signature and fill in the Date.
A filled-in Form WMC-3116 example: an adult patient registers
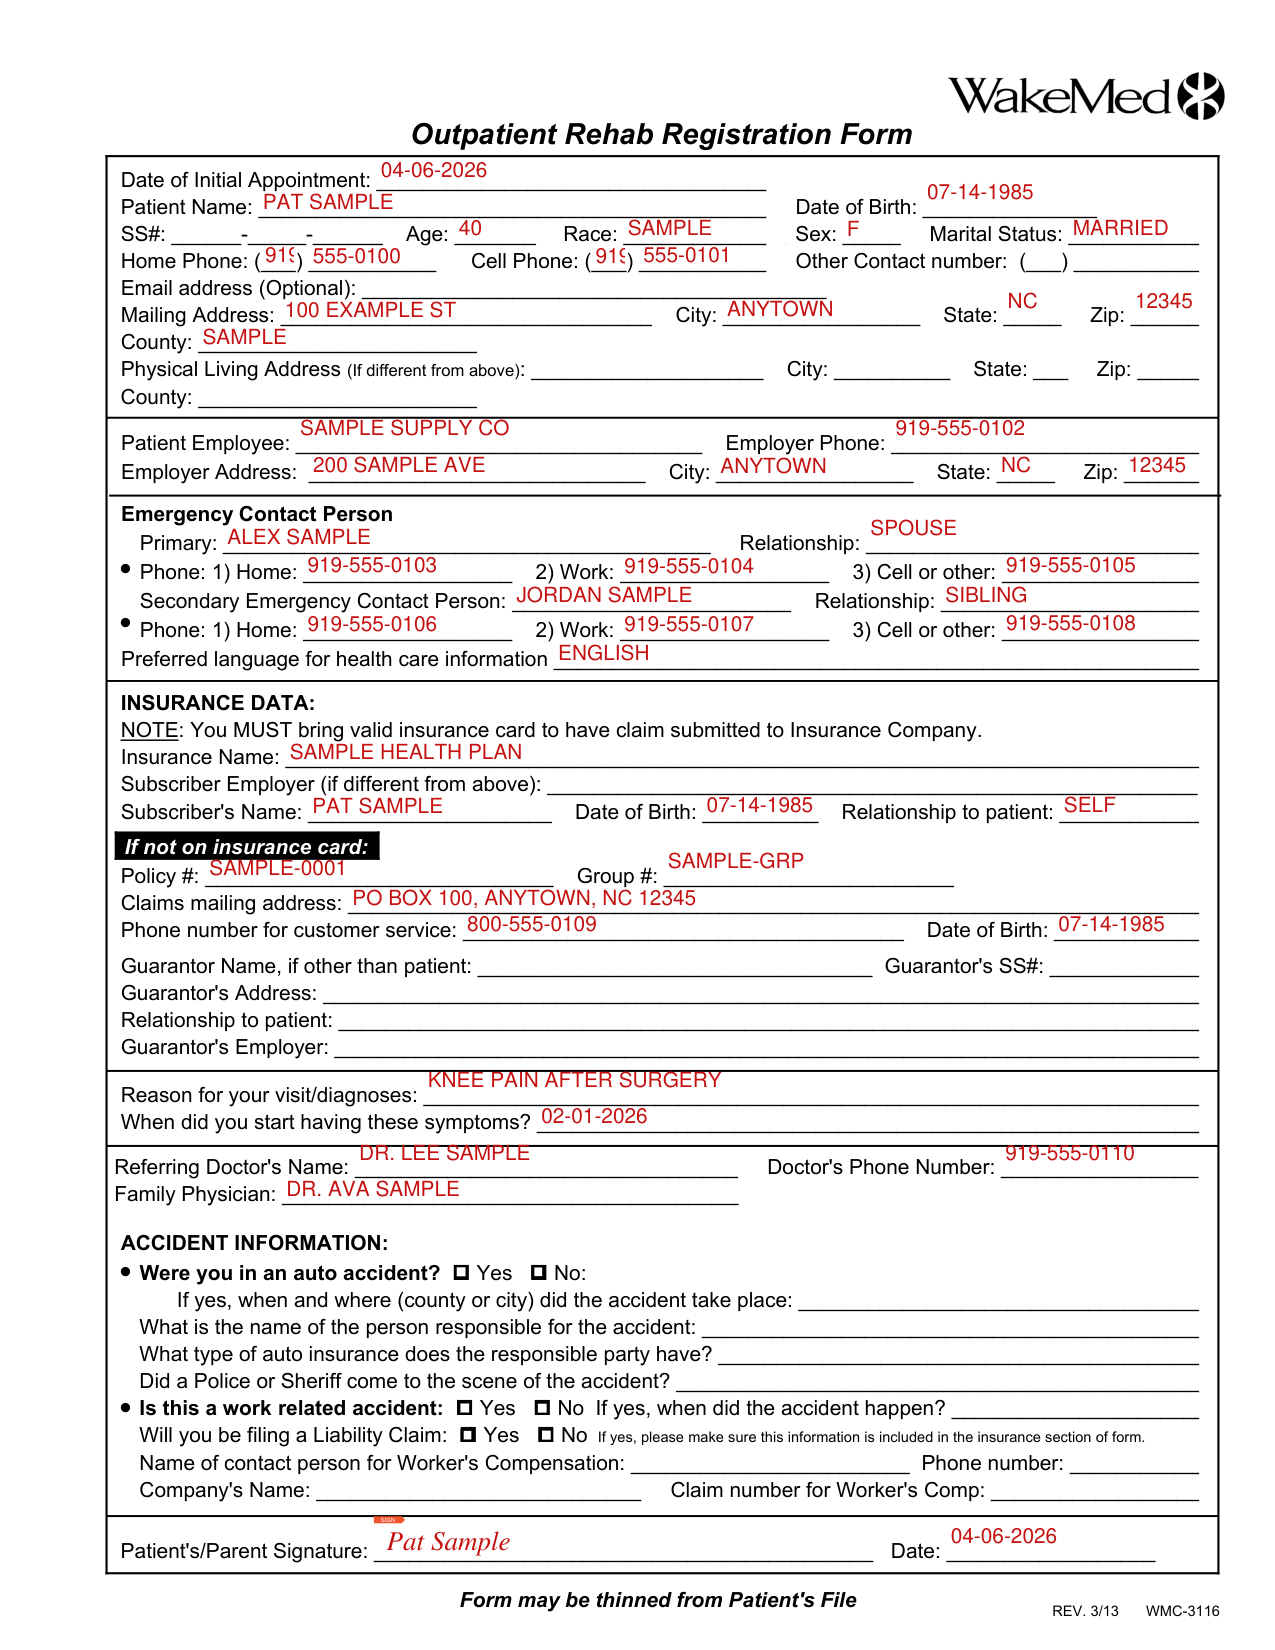
How to fill out Form WMC-3116, box by box
Patient

Fill in Date of Initial Appointment, Patient Name, Date of Birth, SS#, Age, Race, Sex and Marital Status.
Phone, email and addresses

Fill in Home Phone, Cell Phone, Other Contact number and Email address (Optional).
Fill in Mailing Address, City, State, Zip and County.
Fill in Physical Living Address (If different from Mailing Address), City, State, Zip and County.
Employer

Fill in Patient Employee, Employer Phone, Employer Address, City, State and Zip.
Emergency contacts
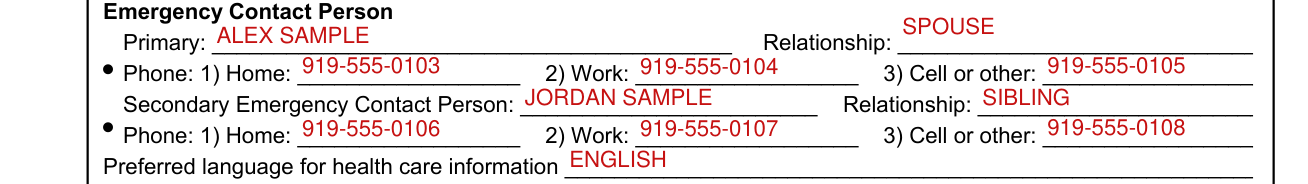
For Emergency Contact Person Primary and for Secondary Emergency Contact Person, write the person on that line and fill in Relationship and Phone: 1) Home, 2) Work, 3) Cell or other.
Fill in Preferred language for health care information.
Insurance data

You MUST bring valid insurance card to have claim submitted to Insurance Company.
Under INSURANCE DATA, fill in Insurance Name, Subscriber Employer "(if different from above)", Subscriber's Name, Date of Birth and Relationship to patient.
If not on insurance card

If not on insurance card: fill in Policy #, Group #, Claims mailing address, Phone number for customer service and Date of Birth.
Guarantor

Fill in Guarantor Name, if other than patient, Guarantor's SS#, Guarantor's Address, Relationship to patient and Guarantor's Employer.
Your visit and doctors

Fill in Reason for your visit/diagnoses and When did you start having these symptoms?
Fill in Referring Doctor's Name, Doctor's Phone Number and Family Physician.
Accident information

Under ACCIDENT INFORMATION, mark Yes or No for Were you in an auto accident?
If yes, fill in when and where (county or city) did the accident take place, What is the name of the person responsible for the accident, What type of auto insurance does the responsible party have? and Did a Police or Sheriff come to the scene of the accident?
Mark Yes or No for Is this a work related accident. If yes, fill in when did the accident happen?
Mark Yes or No for Will you be filing a Liability Claim. If yes, please make sure this information is included in the insurance section of form.
Fill in Name of contact person for Worker's Compensation, Phone number, Company's Name and Claim number for Worker's Comp.
Signing the form

Sign on Patient's/Parent Signature and fill in the Date.
More rules for Form WMC-3116
Checklist for first Outpatient Rehab Appointment: 1. Completed: WakeMed Rehab Outpatient Services Intake Profile Form, 2. Completed: Outpatient Rehab Registration Form, 3. Current Insurance Card, 4. Photo Identification (of patient if an adult or parent/legal guardian if patient is a minor).
5. If not already faxed by doctor's office, please bring your signed Physician/Doctor's Referral Form (Date on the form must be less than 30 days from date of 1st rehab appointment).
If there is anyone other than the patient that will be responsible for calling to make appointments, scheduling inquiries or to inquire on your progress, please let WakeMed know. A medical information release form is required if you are not the parent of a minor or legal guardian.
If you have a Health Care Power of Attorney form completed, please bring a copy of the official form and the information will be placed in your file.
For questions about the Rehab Registration Process, please call 919-350-4626.
Sources
[1] WakeMed Outpatient Rehab Registration Form WMC-3116, REV. 3/13 (the served file; no issuer file found) (the Official source link on this page).
