


Form WC-14 at a glance
What it is: WC-14 Notice of Claim, Georgia State Board of Workers' Compensation, REVISION 7/2022.
Where and when to file: E. CERTIFICATE OF SERVICE: check I hereby certify that I have today sent a copy of this form to all of the parties and have sent this form to the State Board of Workers' Compensation, 270 Peachtree St., NW, Atlanta, Georgia 30303-1299.
A filled-in Form WC-14 example: an employee files a notice of claim
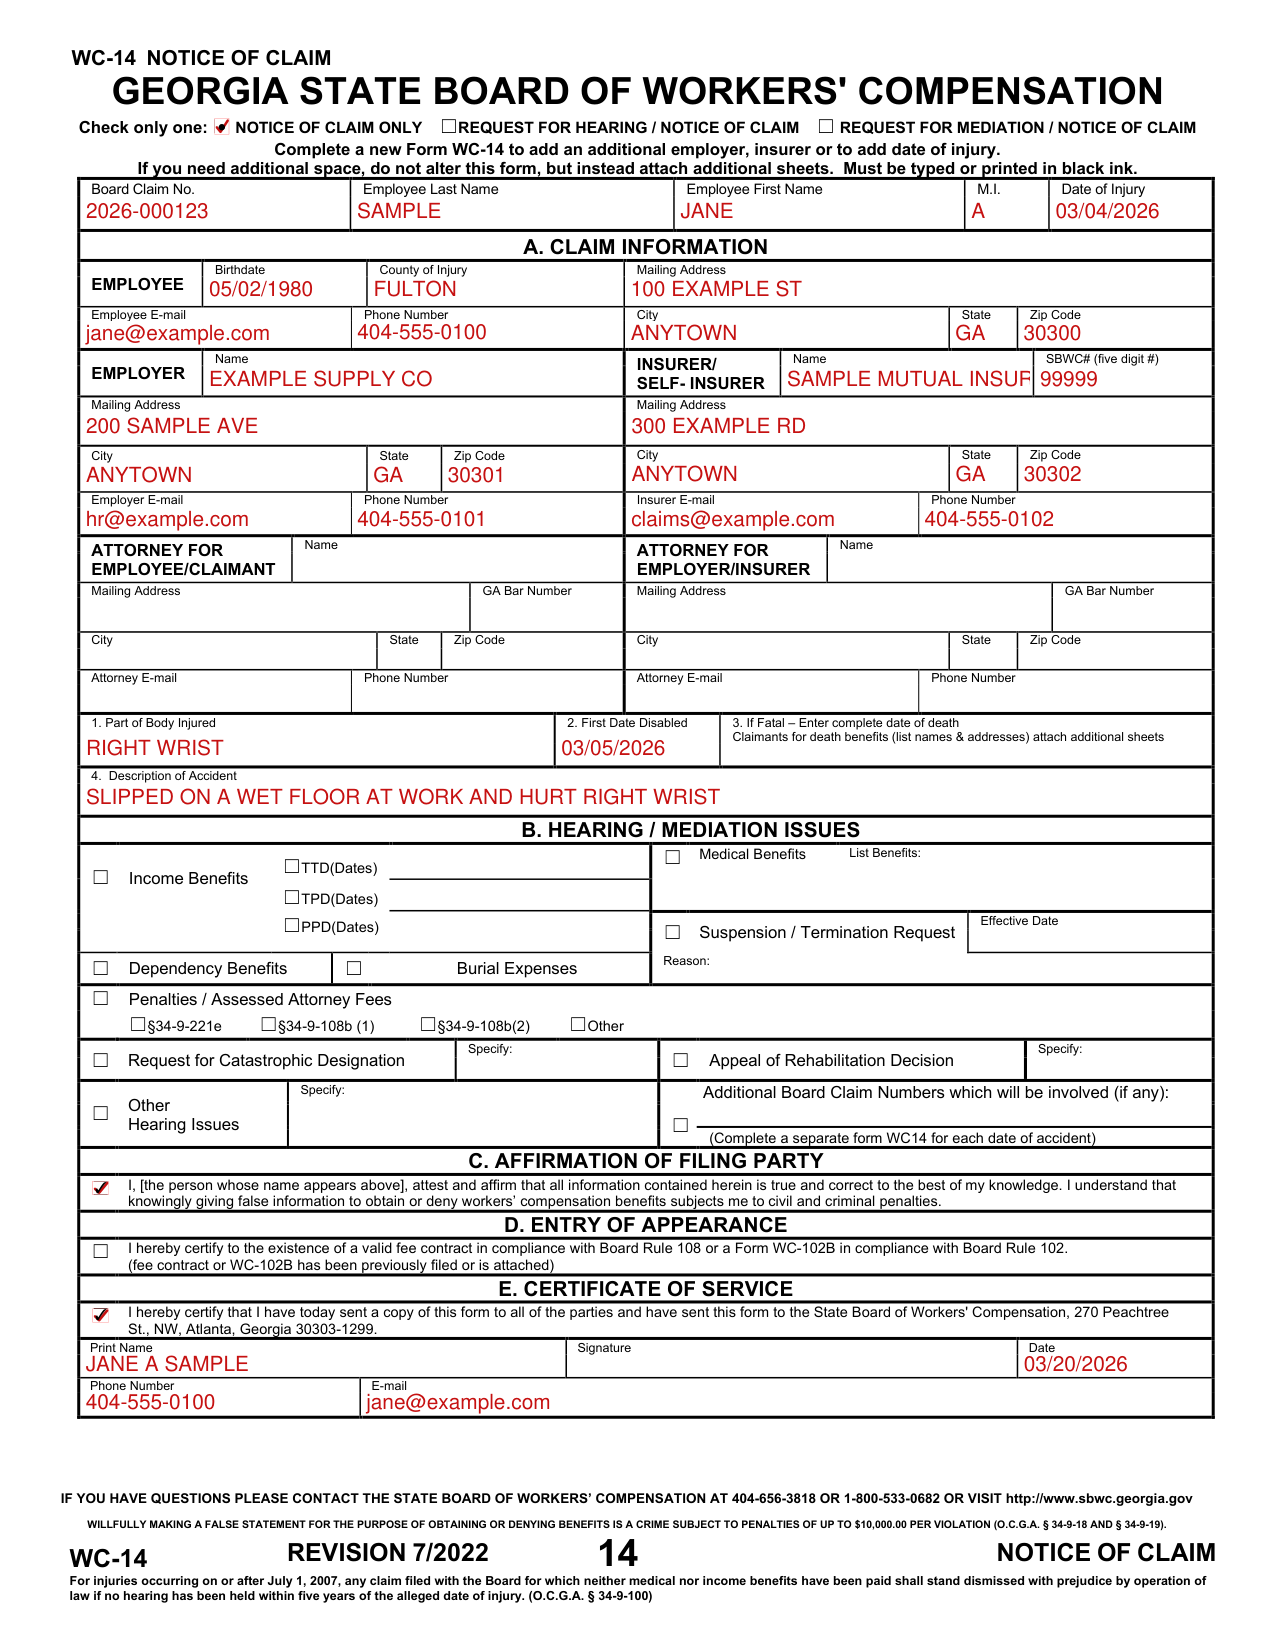
How to fill out Form WC-14, box by box
Check only one and the claim

Check only one: Notice of Claim Only, Request for Hearing / Notice of Claim, or Request for Mediation / Notice of Claim.
Complete a new Form WC-14 to add an additional employer, insurer or to add date of injury. If you need additional space, do not alter this form, but instead attach additional sheets. Must be typed or printed in black ink. Enter the Board Claim No., Employee Last Name, Employee First Name, M.I. and Date of Injury.
A. CLAIM INFORMATION: EMPLOYEE
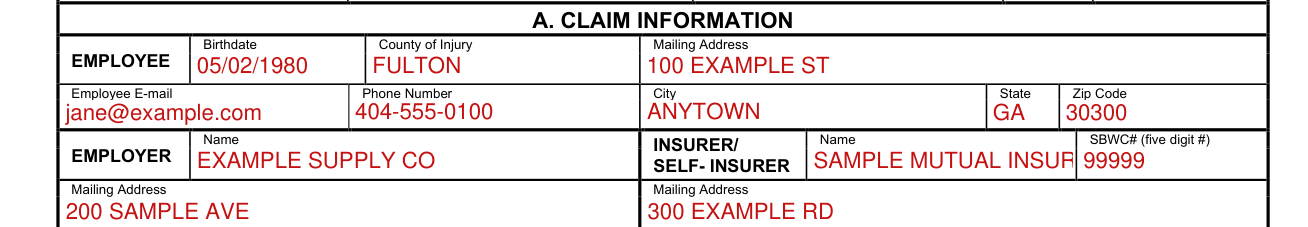
Under A. CLAIM INFORMATION, EMPLOYEE, enter Birthdate, County of Injury, Mailing Address, Employee E-mail, Phone Number, City, State and Zip Code.
EMPLOYER and INSURER/ SELF- INSURER
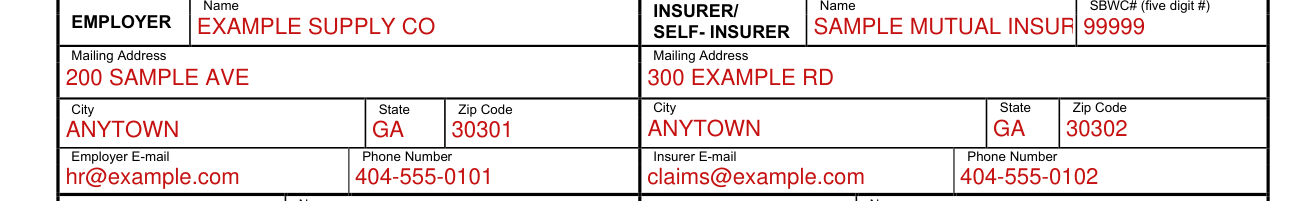
Under EMPLOYER, enter the Name, Mailing Address, City, State, Zip Code, Employer E-mail and Phone Number.
Under INSURER/ SELF-INSURER, enter the Name, SBWC# (five digit #), Mailing Address, City, State, Zip Code, Insurer E-mail and Phone Number.
ATTORNEY FOR EMPLOYEE/CLAIMANT and ATTORNEY FOR EMPLOYER/INSURER

Under ATTORNEY FOR EMPLOYEE/CLAIMANT and under ATTORNEY FOR EMPLOYER/INSURER, enter the Name, Mailing Address, GA Bar Number, City, State, Zip Code, Attorney E-mail and Phone Number.
1. Part of Body Injured, 2. First Date Disabled, 3. If Fatal and 4. Description of Accident

Enter 1. Part of Body Injured, 2. First Date Disabled, 3. If Fatal - Enter complete date of death and 4. Description of Accident.
Claimants for death benefits (list names & addresses): attach additional sheets.
B. HEARING / MEDIATION ISSUES
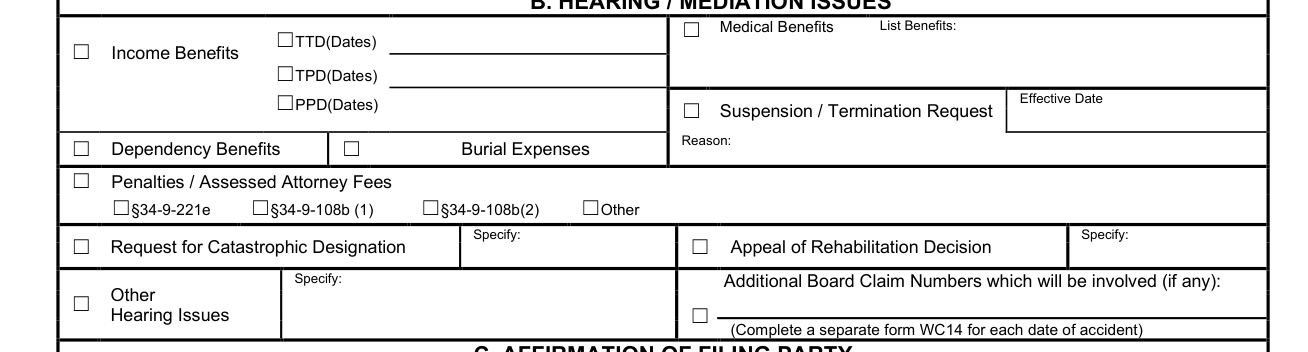
Under B. HEARING / MEDIATION ISSUES, check Income Benefits with TTD(Dates), TPD(Dates) or PPD(Dates), and Medical Benefits with List Benefits.
Check Suspension / Termination Request with its Effective Date and Reason.
Check Dependency Benefits or Burial Expenses.
Check Penalties / Assessed Attorney Fees with §34-9-221e, §34-9-108b (1), §34-9-108b(2) or Other.
Check Request for Catastrophic Designation with Specify, Appeal of Rehabilitation Decision with Specify, or Other Hearing Issues with Specify.
Additional Board Claim Numbers, C. AFFIRMATION OF FILING PARTY, D. ENTRY OF APPEARANCE and E. CERTIFICATE OF SERVICE
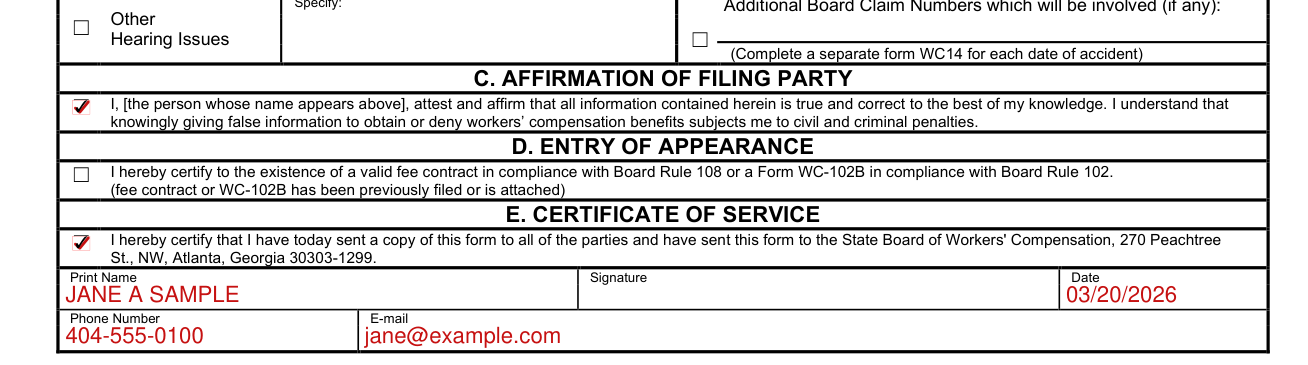
Additional Board Claim Numbers which will be involved (if any): (Complete a separate form WC14 for each date of accident). C. AFFIRMATION OF FILING PARTY: check I attest and affirm that all information contained herein is true and correct to the best of my knowledge. I understand that knowingly giving false information to obtain or deny workers' compensation benefits subjects me to civil and criminal penalties.
D. ENTRY OF APPEARANCE: check I hereby certify to the existence of a valid fee contract in compliance with Board Rule 108 or a Form WC-102B in compliance with Board Rule 102 (fee contract or WC-102B has been previously filed or is attached).
Enter Print Name, Signature, Date, Phone Number and E-mail.
Common questions about Form WC-14
What is a WC 14 form in Georgia?
WC-14 Notice of Claim, Georgia State Board of Workers' Compensation, REVISION 7/2022. If you have questions, contact the State Board of Workers' Compensation at 404-656-3818 or 1-800-533-0682 or visit http://www.sbwc.georgia.gov
Is there a penalty?
Willfully making a false statement for the purpose of obtaining or denying benefits is a crime subject to penalties of up to $10,000.00 per violation (O.C.G.A. § 34-9-18 and § 34-9-19). (checked October 22, 2026)
Sources
[1] Form WC-14 (Rev 7/2022), Georgia State Board of Workers' Compensation (the Official source link on this page).