

Gerber Life Insurance Claim Form at a glance
What it is: A signed claim form is required. A claim form needs to be completed for each accident.
Where and when to file: Send all correspondence to WebTPA, Inc., P.O. Box 2415 Grapevine, TX 76099-2415. The claim form must be sent within 90 days of the date you first received medical care.
A filled-in Gerber Life Insurance Claim Form example: a parent fills out Part 1-B for a son hurt at school

How to fill out Gerber Life Insurance Claim Form, box by box
Part 1-A, completed by the Organization/School

To be completed in full by the Organization/School: Part 1-A.
If Part 1-A and Part 1-B are not completed in full, this claim cannot be processed and will be returned.
Enter the Organization/School District Name and the Policy Number.
Enter the School/Team/League Name, the Phone No., the Address and the Email.
Enter the Type of Activity/Sport. If Athletics, designate P.E. Class, Intramural, Interscholastic Game, Jr. Varsity, Varsity, Youth, Adult, Practice or Other.
Enter the Date of Accident, the Accident Time and the Date of First Treatment.
Where and how did accident occur? Please be specific.
Enter the Part of body Injured. Then, Yes or No: At the time of the accident, was the claimant involved in a sponsored and supervised activity and were they a current student/member of the Organization/School District?
Enter Under whose supervision. Then, Yes or No: Was he/she a witness?
SIGN: enter the Authorized Signature, the Title and the Date. It must be signed by an Organization/School official unless injury did not occur during an Organization/School activity. Signature is required.
Part 1-B, completed by the claimant or the parent/legal guardian
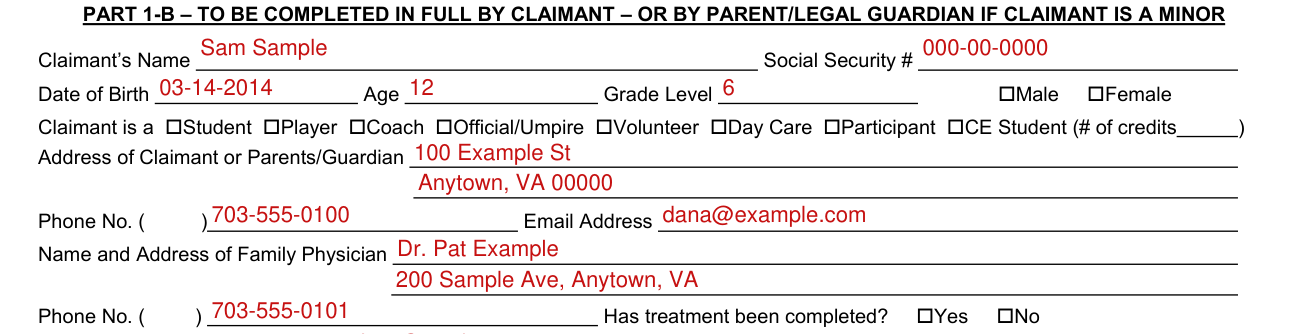
To be completed in full by the claimant, or by the parent/legal guardian if claimant is a minor: Part 1-B.
Enter the Claimant's Name, the Social Security #, the Date of Birth, the Age and the Grade Level, and mark Male or Female.
Mark what the claimant is: Student, Player, Coach, Official/Umpire, Volunteer, Day Care Participant or CE Student (# of credits).
Enter the Address of Claimant or Parents/Guardian, the Phone No. and the Email Address.
Enter the Name and Address of Family Physician and the Phone No. Then, Yes or No: Has treatment been completed?
Father/Guardian and Mother/Guardian
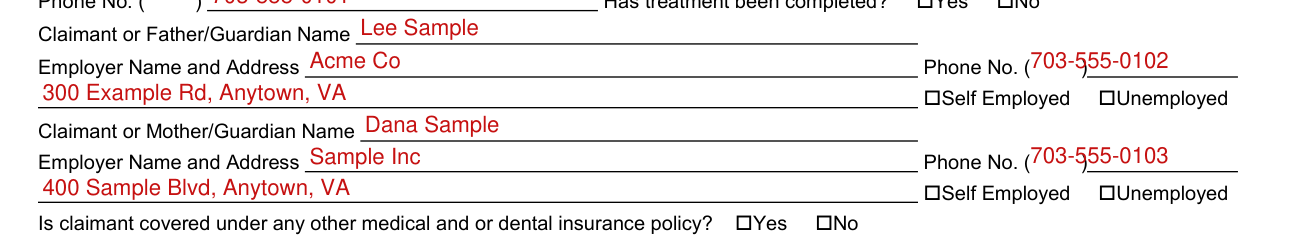
Enter the Claimant or Father/Guardian Name and the Claimant or Mother/Guardian Name, each with the Employer Name and Address and the Phone No. Mark Self Employed or Unemployed.
Other insurance coverage

Yes or No: Is claimant covered under any other medical and or dental insurance policy?
Yes or No: Is claimant covered under a government sponsored insurance such as Medicare/Medicaid?
Enter the Name of all companies providing claimant insurance coverage or prepaid health plans: Name of Company, Address and Policy #.
Yes or No: Are benefits due for this claim under these other insurance coverages?
Yes or No: Does your son or daughter have medical insurance coverage as an eligible dependent from a previous marriage as mandated in a divorce decree? If yes, please give name, address and phone number of responsible party.
Signing as Claimant, Parent or Guardian

AFFIDAVIT: I verify that the statement on other insurance is accurate and complete. I understand that the intentional furnishing of incorrect information via the U.S. Mail may be fraudulent and violate federal laws as well as state laws.
I agree that it is determined at a later date that there are other insurance benefits collectible on this claim I will reimburse Gerber Life Insurance Company to the extent for which Gerber Life Insurance Company would not have been liable.
Signature: Claimant, Parent or Guardian, and Date. Signature is required.
AUTHORIZATION TO RELEASE INFORMATION: I hereby authorize any employer, health plan, insurance company, hospital, physician, health care profession, clinic, laboratory, pharmacy, medical facility or other person that has provided treatment, payment, or services in connection with this claim to disclose, when requested to do so, all information with respect to any injury, policy coverage, medical history, consultations, prescription or treatment, and copies of all hospital or medical records and itemized bills to WebTPA, Inc. and Gerber Life Insurance Company, it's agents, employees and representatives.
I hereby authorize WebTPA, Inc. to discuss any information related to medical expenses incurred or treatments rendered in connection with this claim, with Special Markets Insurance Consultants, Inc. representatives and their assigned agents and to officials at the school or organization through which this policy is issued.
A photo static copy of this authorization shall be considered as effective and valid as the original.
Sign on the Signature line for the Claimant, Parent or Guardian, and add the Date.
More rules for Gerber Life Insurance Claim Form
If you have other insurance, submit your claim to your other insurer.
When you receive the explanation of benefits notice from your primary carrier, send it along with the corresponding itemized bills and with the fully completed claim form.
You must submit itemized bills; balance due statements will not be processed.
Itemized bills include HCFA-1500 (standard form used by Providers) and UB-04, or UB-92 (standard form used by Hospitals).
If you already paid the bill, include a paid receipt or a copy of your cancelled check. Otherwise payment will be made to the providers of service (Hospital, Physician or Others), unless a paid receipt statement accompanies the bill at the time the claim is submitted.
Any bills not filed with the claim form should be sent, within 90 days of the date you received medical care, to the Company identified with claimant's name, Organization or School name and date of Accident.
Please contact WebTPA, Inc. by calling 866-975-9468 if you would like to check the status of your claim or if you have any questions on how your claim was processed or the benefit paid.
If you change your address, please notify Webtpa, Inc. by sending notification to Webtpa so that there is no delay in processing any claims.
Keep copies of all claim forms, bills, and correspondence for your own records until your claim has been processed.
Claim Forms Not Completed In Full or Not Submitted; Balance Due, Balance Forward, or Past Due Statements Submitted for Bills; Explanation of Benefits from Primary Carrier Not Provided with the Bills.
The accident policy benefits are limited and may not provide 100% coverage. Completion of a claim form does not guarantee benefit payment.
Continue to the next page of the form, which must be completed in full.
Answer all questions in detail (including all signatures on the front and back of the form).
Common questions about Gerber Life Insurance Claim Form
Is there a deadline?
The claim form must be sent within 90 days of the date you first received medical care.
Where do I file it?
Send all correspondence to WebTPA, Inc., P.O. Box 2415 Grapevine, TX 76099-2415.
Is there a penalty?
Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance or statement of claim containing any materially false information, or conceals for the purpose of misleading, information concerning any fact material thereto, commits a fraudulent insurance act which is a crime and may subject such person to criminal and civil penalties.
Sources
[1] Gerber Life Insurance Claim Form (the served file; no issuer file found) (the Official source link on this page).
