

FSA/HRA Claim Form at a glance
What it is: FSA/HRA Claim Form: please indicate the appropriate Account: Flexible Spending Health Account (FSA) Health Reimbursement Account (HRA).
Where and when to file: Contact Information & Claims Submission: IAA - PO Box 5082 Mt. Laurel, NJ 08054, flexclaims@iaatpa.com, 800-238-0876 (Fax).
A filled-in FSA/HRA Claim Form example: an FSA claim for glasses
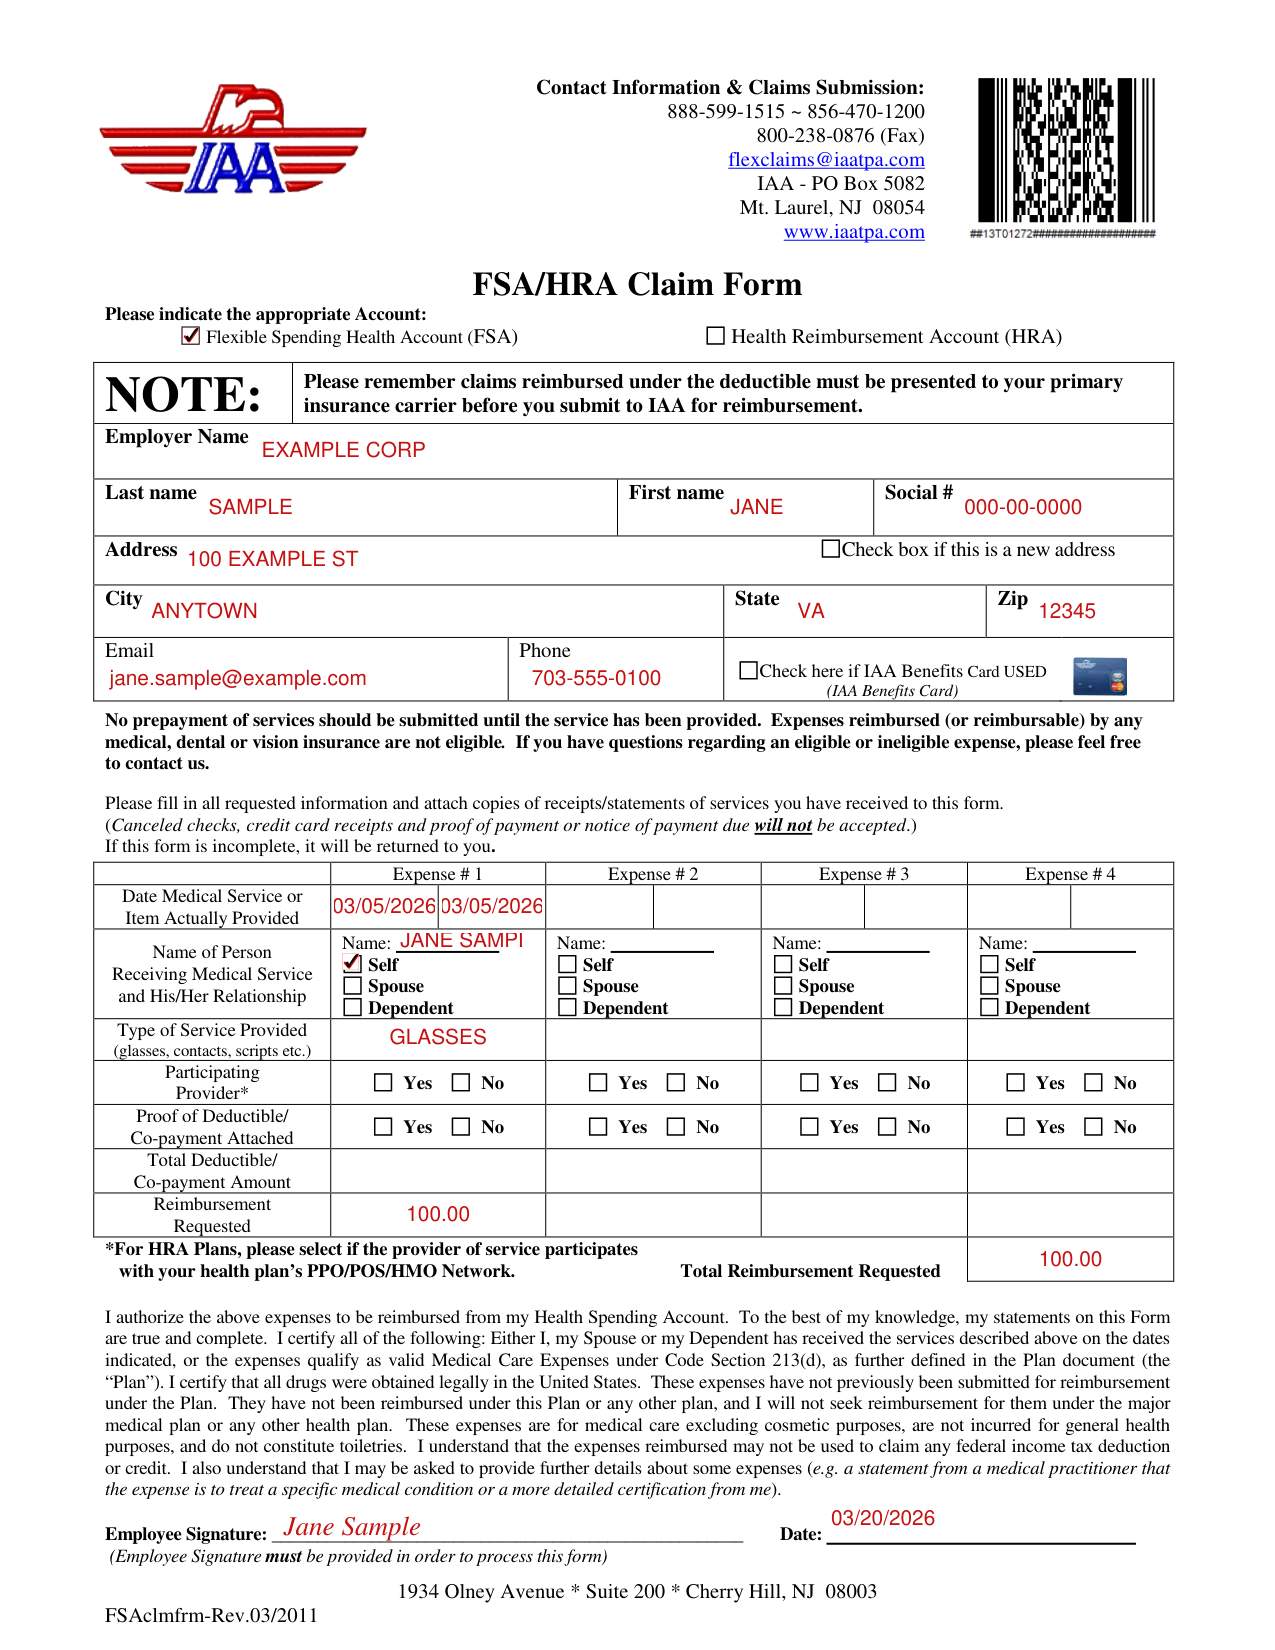
How to fill out FSA/HRA Claim Form, box by box
Which Account

FSA/HRA Claim Form: please indicate the appropriate Account: Flexible Spending Health Account (FSA) Health Reimbursement Account (HRA).
Please remember claims reimbursed under the deductible must be presented to your primary insurance carrier before you submit to IAA for reimbursement.
Employer Name, name and Address

Enter Employer Name, Last name, First name and Social #.
Enter Address, City, State, Zip, Email and Phone. Check box if this is a new address.
Check here if IAA Benefits Card USED.
Expense # 1 to Expense # 4
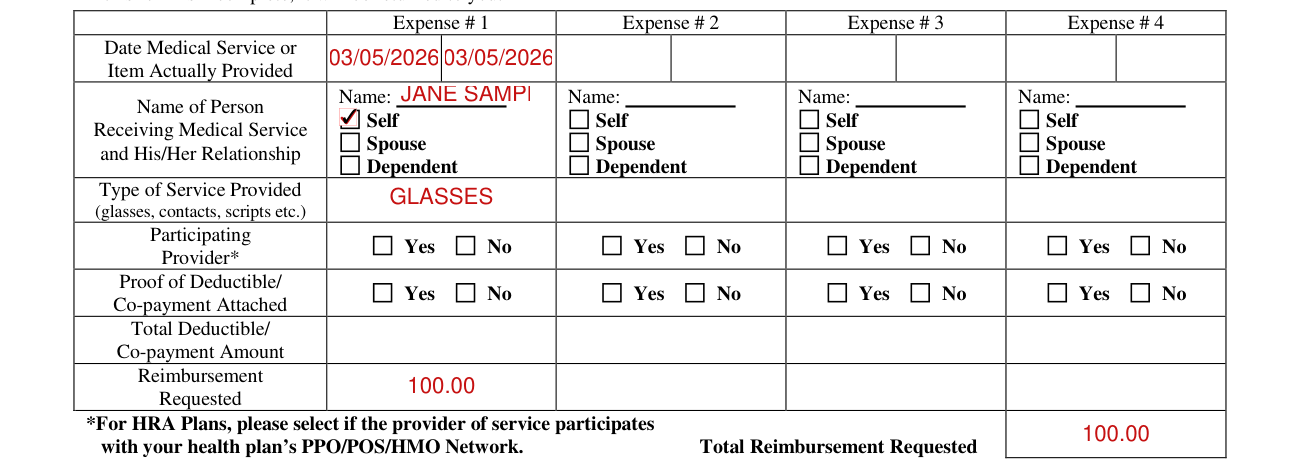
For Expense # 1, Expense # 2, Expense # 3 and Expense # 4, enter the Date and the Medical Service or Item Actually Provided.
Enter the Name of Person Receiving Medical Service and His/Her Relationship: Self, Spouse or Dependent. Enter the Type of Service Provided (glasses, contacts, scripts etc.).
Participating Provider* Yes No: *For HRA Plans, please select if the provider of service participates with your health plan's PPO/POS/HMO Network. Mark Proof of Deductible/ Co-payment Attached Yes or No. Enter the Total Deductible/ Co-payment Amount and the Reimbursement Requested, then the Total Reimbursement Requested.
Signing the claim

Employee Signature and Date: These expenses have not previously been submitted for reimbursement under the Plan. They qualify as valid Medical Care Expenses under Code Section 213(d), and I will not seek reimbursement for them under the major medical plan or any other health plan. I understand that the expenses reimbursed may not be used to claim any federal income tax deduction or credit. Employee Signature must be provided in order to process this form.
More rules for FSA/HRA Claim Form
Please fill in all requested information and attach copies of receipts/statements of services you have received to this form.
Expenses reimbursed (or reimbursable) by any medical, dental or vision insurance are not eligible.
No prepayment of services should be submitted until the service has been provided.
Canceled checks, credit card receipts and proof of payment or notice of payment due will not be accepted.
If this form is incomplete, it will be returned to you.
In order to satisfy IRS requirements documentation is needed to process your claim(s).
When submitting for reimbursement, please complete and provide necessary documentation. This will quicken the processing time of your claim(s).
Medical Payments All documentation should show date of service, procedure performed and should prove the claim was initially processed by your health care carrier.
Acceptable documentation includes: a copy of the Explanation of Benefits (EOB) from your health care carrier and/or an itemized bill indicating services received for that person have been applied to the applicable deductible.
Dental and Vision All documentation should show date of service, procedure performed or item(s) purchased and name of person receiving services/items. The submission should include: copy of statement, itemized bill, or detailed receipt.
Prescription Drugs (Rx) Provide a copy of the pharmacy receipt for the prescriptions(s). Usually, this is stapled to the bag containing your prescription(s). This will provide details, such as prescription name, price and fill date.
In some Plans, the prescription benefits are subject to a calendar year deductible, before co-pays are applied. These should be submitted as well.
Over-the-Counter Purchases (OTC) All documentation should include the itemized register receipt from the store of purchase.
If your register receipt prints abbreviated product names, please provide unabbreviated product name to quicken processing time.
All medication purchases incurred after 12/31/2010 must be accompanied by a doctor's prescription.
Common questions about FSA/HRA Claim Form
Where do I file it?
Contact Information & Claims Submission: IAA - PO Box 5082 Mt. Laurel, NJ 08054, flexclaims@iaatpa.com, 800-238-0876 (Fax).
Sources
[1] FSA/HRA Claim Form (FSAclmfrm-Rev.03/2011), IAA (the Official source link on this page).
