

Form H1836-A at a glance
What it is: Form H1836-A is the Medical Release/Physician's Statement.
Who signs: The physician enters the Name of Physician (please type or print), signs on Signature - Physician and enters the Date. The Client or Personal Representative signs and enters the Date.
The patient named in Section I has applied for benefits with HHSC. Federal and state regulations require that persons receiving benefits work or participate in activities to prepare them for work unless they are physically or mentally incapable of working. This patient claims that disability. Please complete the appropriate parts. After you complete the form, you may give it to the person or mail it to HHSC at the address in Section I.
A filled-in Form H1836-A example: staff start the form for a patient
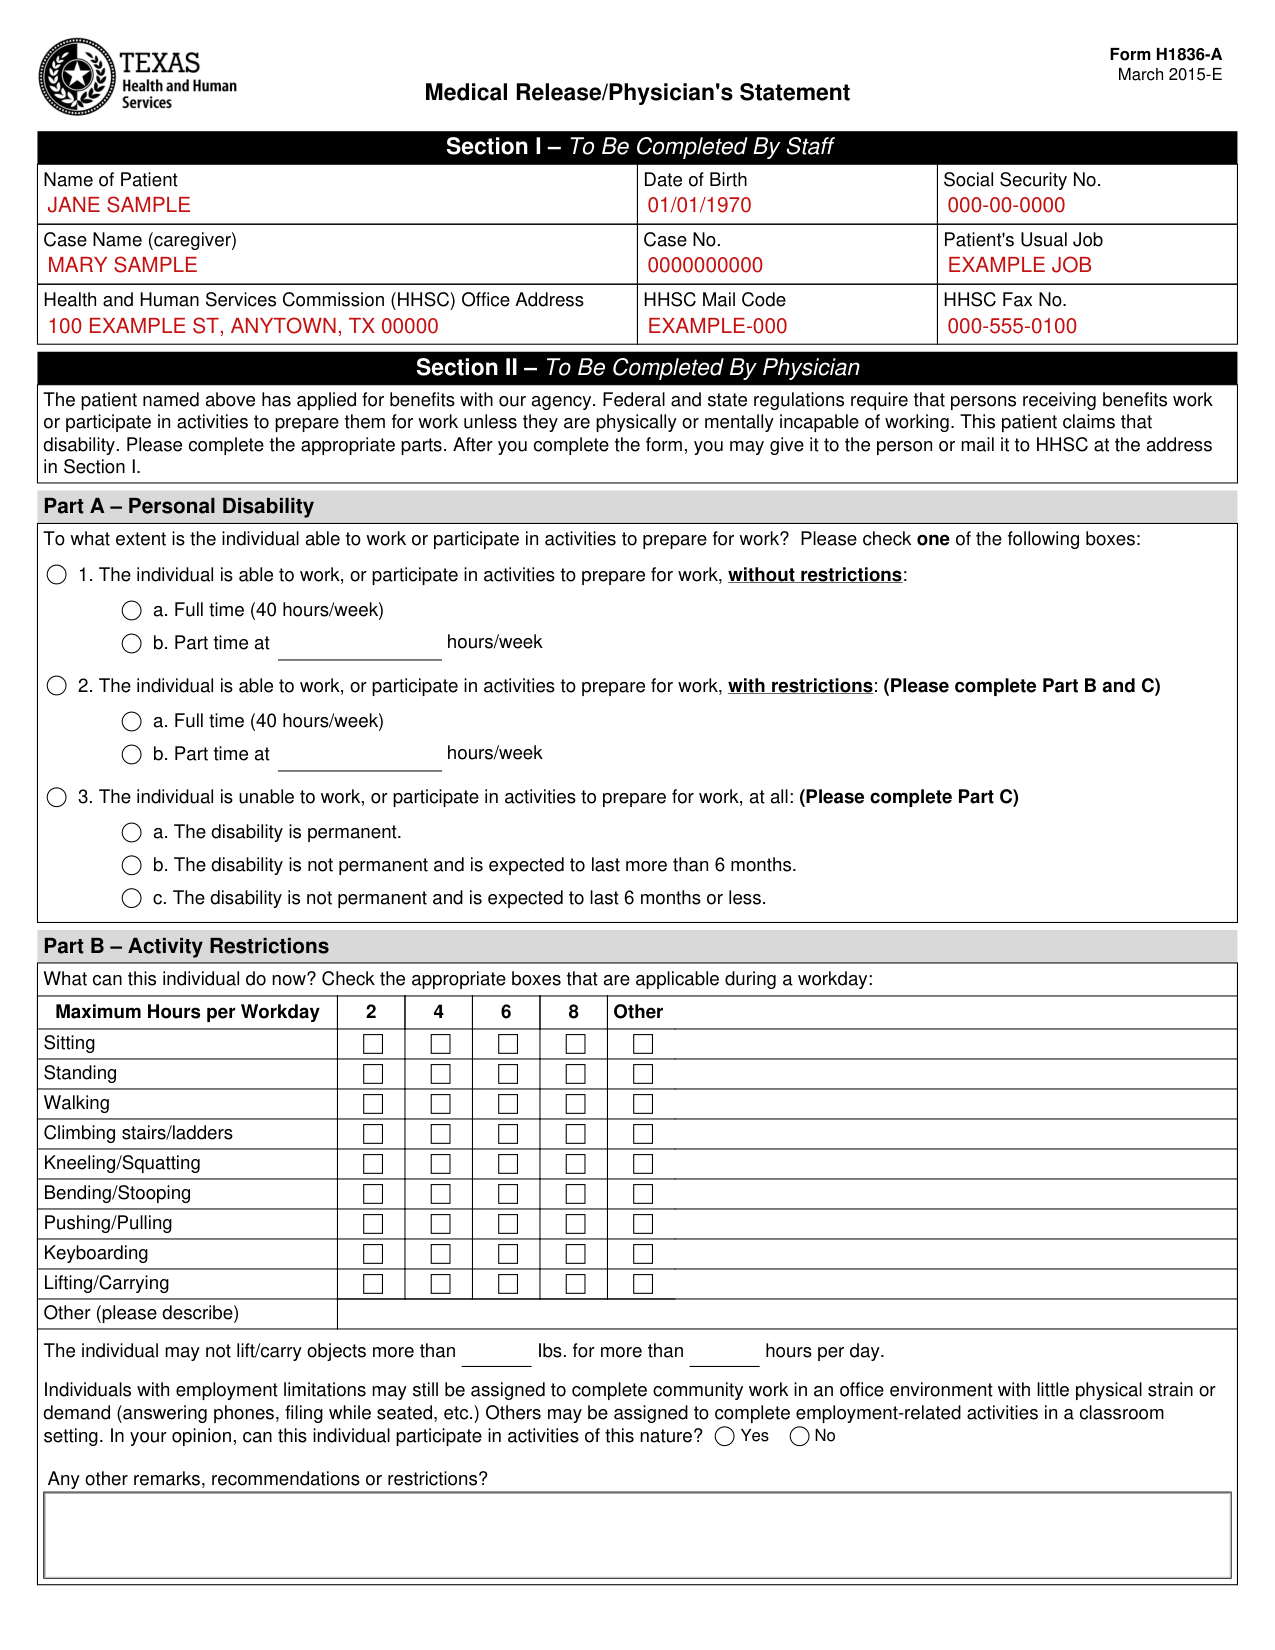
How to fill out Form H1836-A, box by box
Section I - To Be Completed By Staff
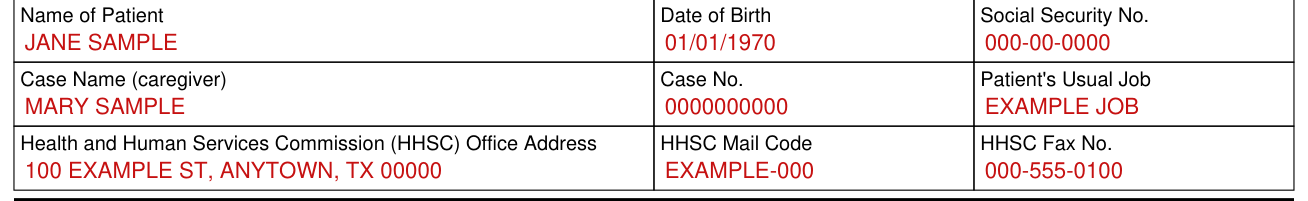
Section I - To Be Completed By Staff is where staff enter the Name of Patient, Date of Birth and Social Security No.
Enter the Case Name (caregiver), Case No. and Patient's Usual Job.
Enter the Health and Human Services Commission (HHSC) Office Address, HHSC Mail Code and HHSC Fax No.
Part A - Personal Disability
Part A - Personal Disability is where you check one of the following boxes for the extent to which the individual is able to work or participate in activities to prepare for work.
Box 1: the individual is able to work, or participate in activities to prepare for work, without restrictions, either a. Full time (40 hours/week) or b. Part time at hours/week.
Box 2: the individual is able to work, or participate in activities to prepare for work, with restrictions, either a. Full time (40 hours/week) or b. Part time at hours/week; complete Part B and C.
Box 3: the individual is unable to work, or participate in activities to prepare for work, at all; complete Part C and check a. The disability is permanent, b. The disability is not permanent and is expected to last more than 6 months, or c. The disability is not permanent and is expected to last 6 months or less.
Part B - Activity Restrictions
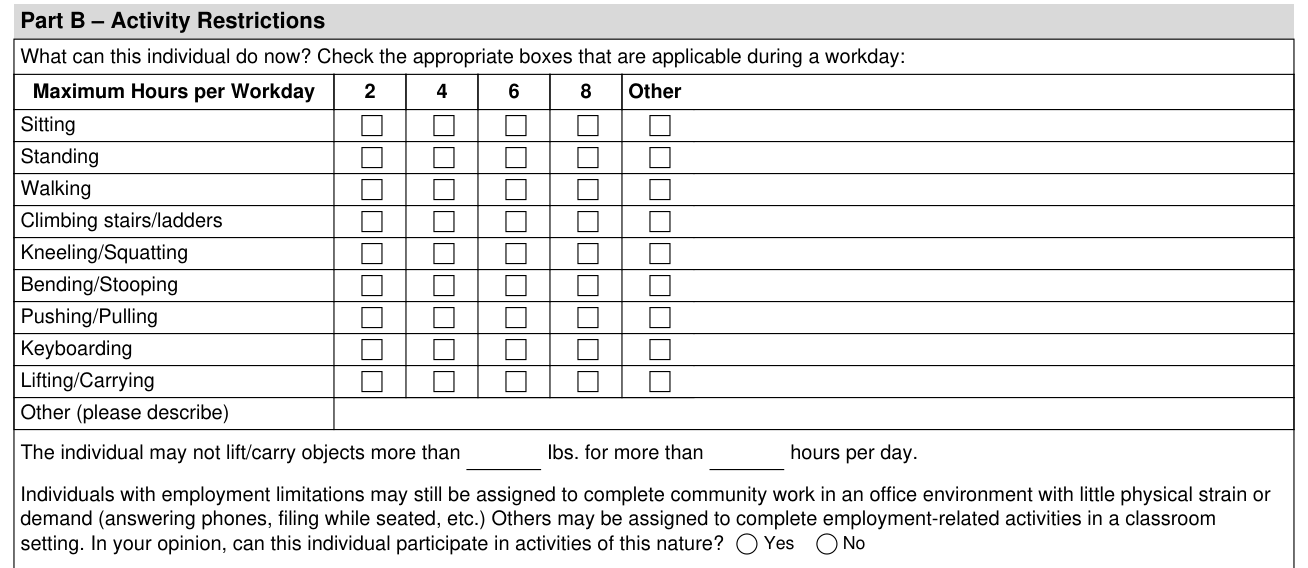
Part B - Activity Restrictions is where you check the appropriate boxes that are applicable during a workday, under Maximum Hours per Workday 2, 4, 6, 8 or Other.
Check the appropriate boxes that are applicable during a workday for Sitting, Standing, Walking, Climbing stairs/ladders, Kneeling/Squatting, Bending/Stooping, Pushing/Pulling, Keyboarding and Lifting/Carrying.
For Other, please describe.
The individual may not lift/carry objects more than lbs. for more than hours per day.
Check Yes or No: in your opinion, can this individual participate in activities of this nature, community work in an office environment with little physical strain or demand (answering phones, filing while seated, etc.) or employment-related activities in a classroom setting?
Enter any other remarks, recommendations or restrictions.
Part C - Diagnosis
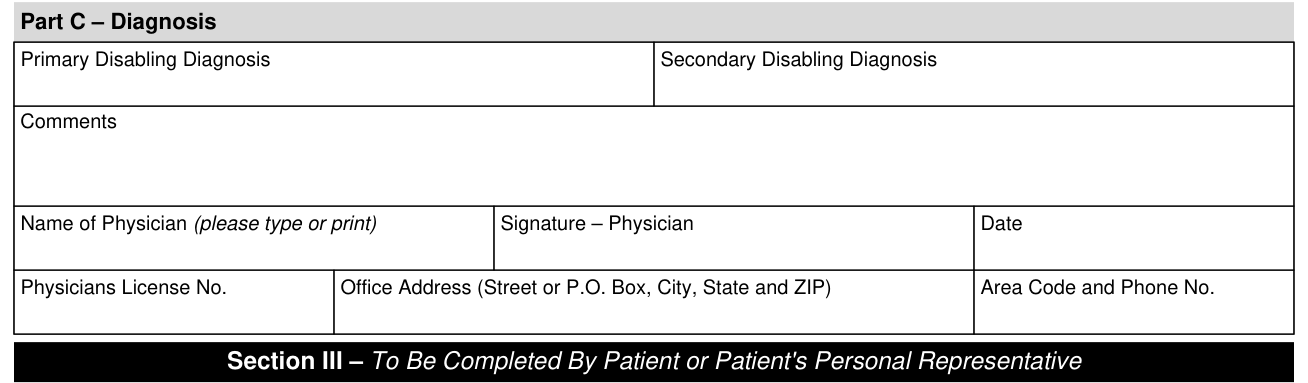
Part C - Diagnosis is where you enter the Primary Disabling Diagnosis and Secondary Disabling Diagnosis.
The physician enters the Physicians License No., Office Address (Street or P.O. Box, City, State and ZIP) and Area Code and Phone No.
Section III - To Be Completed By Patient or Patient's Personal Representative
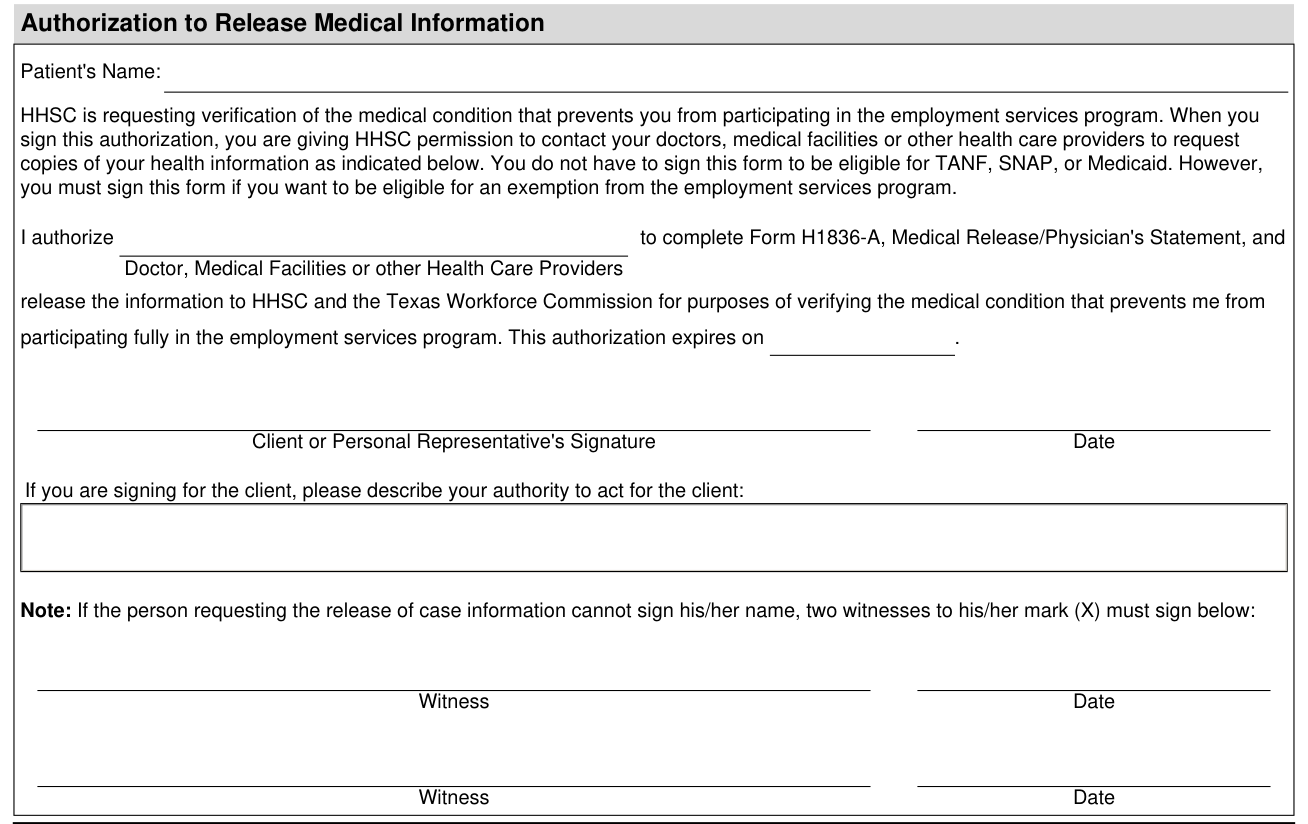
You do not have to sign this form to be eligible for TANF, SNAP, or Medicaid. However, you must sign this form if you want to be eligible for an exemption from the employment services program.
When you sign this authorization, you are giving HHSC permission to contact your doctors, medical facilities or other health care providers to request copies of your health information.
Enter the Patient's Name, and after I authorize enter the Doctor, Medical Facilities or other Health Care Providers to complete Form H1836-A, Medical Release/Physician's Statement.
By signing you authorize the release of the information to HHSC and the Texas Workforce Commission for purposes of verifying the medical condition that prevents you from participating fully in the employment services program. Enter when it expires on This authorization expires on.
If you are signing for the client, describe your authority to act for the client.
If the person requesting the release of case information cannot sign his/her name, two witnesses to his/her mark (X) must sign on the Witness and Date lines.
You can withdraw permission you have given your doctor or health care provider to use or disclose health information that identifies you, unless they have already taken action based on your permission. You must withdraw your permission in writing.
Sources
[1] Form H1836-A (March 2015-E), Medical Release/Physician's Statement, Texas Health and Human Services Commission (the Official source link on this page).
