

Harris Health Application for Financial Assistance at a glance
What it is: The Harris Health Application for Financial Assistance must be completed to obtain Harris Health financial assistance.
Where and when to file: Mail the application to Harris Health Financial Assistance Program, P.O. Box 300488, Houston, TX 77230.
Be sure you, your spouse, and ALL children between 18 and 26 years old who live with you sign and date the form.
You, your spouse and all children 18 to 26 years old who live in your house must sign and date to get a Harris Health Program with prescriptions.
I am a bona fide resident or am a dependent of a bona fide resident of Harris County for Harris Health Financial Assistance and a resident of Texas for grant programs. I physically live in Harris County, maintain living quarters in Harris County, Texas, and do not claim to be a resident of another county or state.
What to bring and attach to Harris Health Application for Financial Assistance
Provide copies of identification of you and, if applicable, your spouse: either a marriage license/IRS 1040, if married; a Declaration and Registration of Informal Marriage, if marriage is common law; or other proof of marriage and common law marriage.
Also provide one of the following forms of picture identification: State-issued driver license; State-issued ID card; Current student ID; Current employee job badge; U.S. Immigration documents; Passport with picture; Foreign consulate ID card; Agency letter; Current Enhanced+ Public Library Photo ID Card; or National Electoral Institute (INE) photo ID card.
Provide proof of gross income for the past 30 days for you, your spouse, and adult children between 18 and 26 and who are full time students living with you.
Provide all of the following, if applicable: Proof of cash income; Current check stubs; Proof of income from rental property; Workmen's compensation; Proof of dividends and royalties; Proof of alimony received; Proof of military pay and allowances; Child support documents; Social Security award letter; Retirement award letter; Current IRS 1040 tax return(all pages) if self-employed; Veteran Affairs letter or check; Agency letter; Unemployment benefits record; Income on SNAP form TF0001; Harris Health System-Statement of Self Employment Income Form if no tax return is filed; Harris Health System-Wage Verification Form (for cash and personal check wages only); and Harris Health System-Statement of Support Form, if no income.
For an address with your name or your spouse's name, provide one of the following documents dated within the last 60 days: Utility bill; Check stub; Mortgage coupon; Credit card statement; Business mail; Medicaid or Medicare letter; School record for children under 18; Certification documents or benefit checks from Social Security Administration or Texas Workforce Commission; Certification paper from Supplemental Nutrition Assistance Program (SNAP), or SNAP Form TF0001; Agency letter; Statement from a licensed child care provider; or Harris Health System-Residence Verification Form filled out by a non-related person not living in your house.
For documentation of dependent children living with you, provide one of the 11 documents the form lists, such as a birth certificate, a baptismal record, a divorce decree or child support document, or proof of full time school enrollment for students 18 to 26.
For immigration status for you, your spouse, and your dependent children, provide current or expired documents from the U.S. Citizenship and Immigration Services.
For health care coverage for you, your spouse, and your dependent children, provide current proof of Medicaid, CHIP, CHIP Perinatal, Medicare, or health insurance.
A filled-in Harris Health Application for Financial Assistance example: a divorced mother lists her household
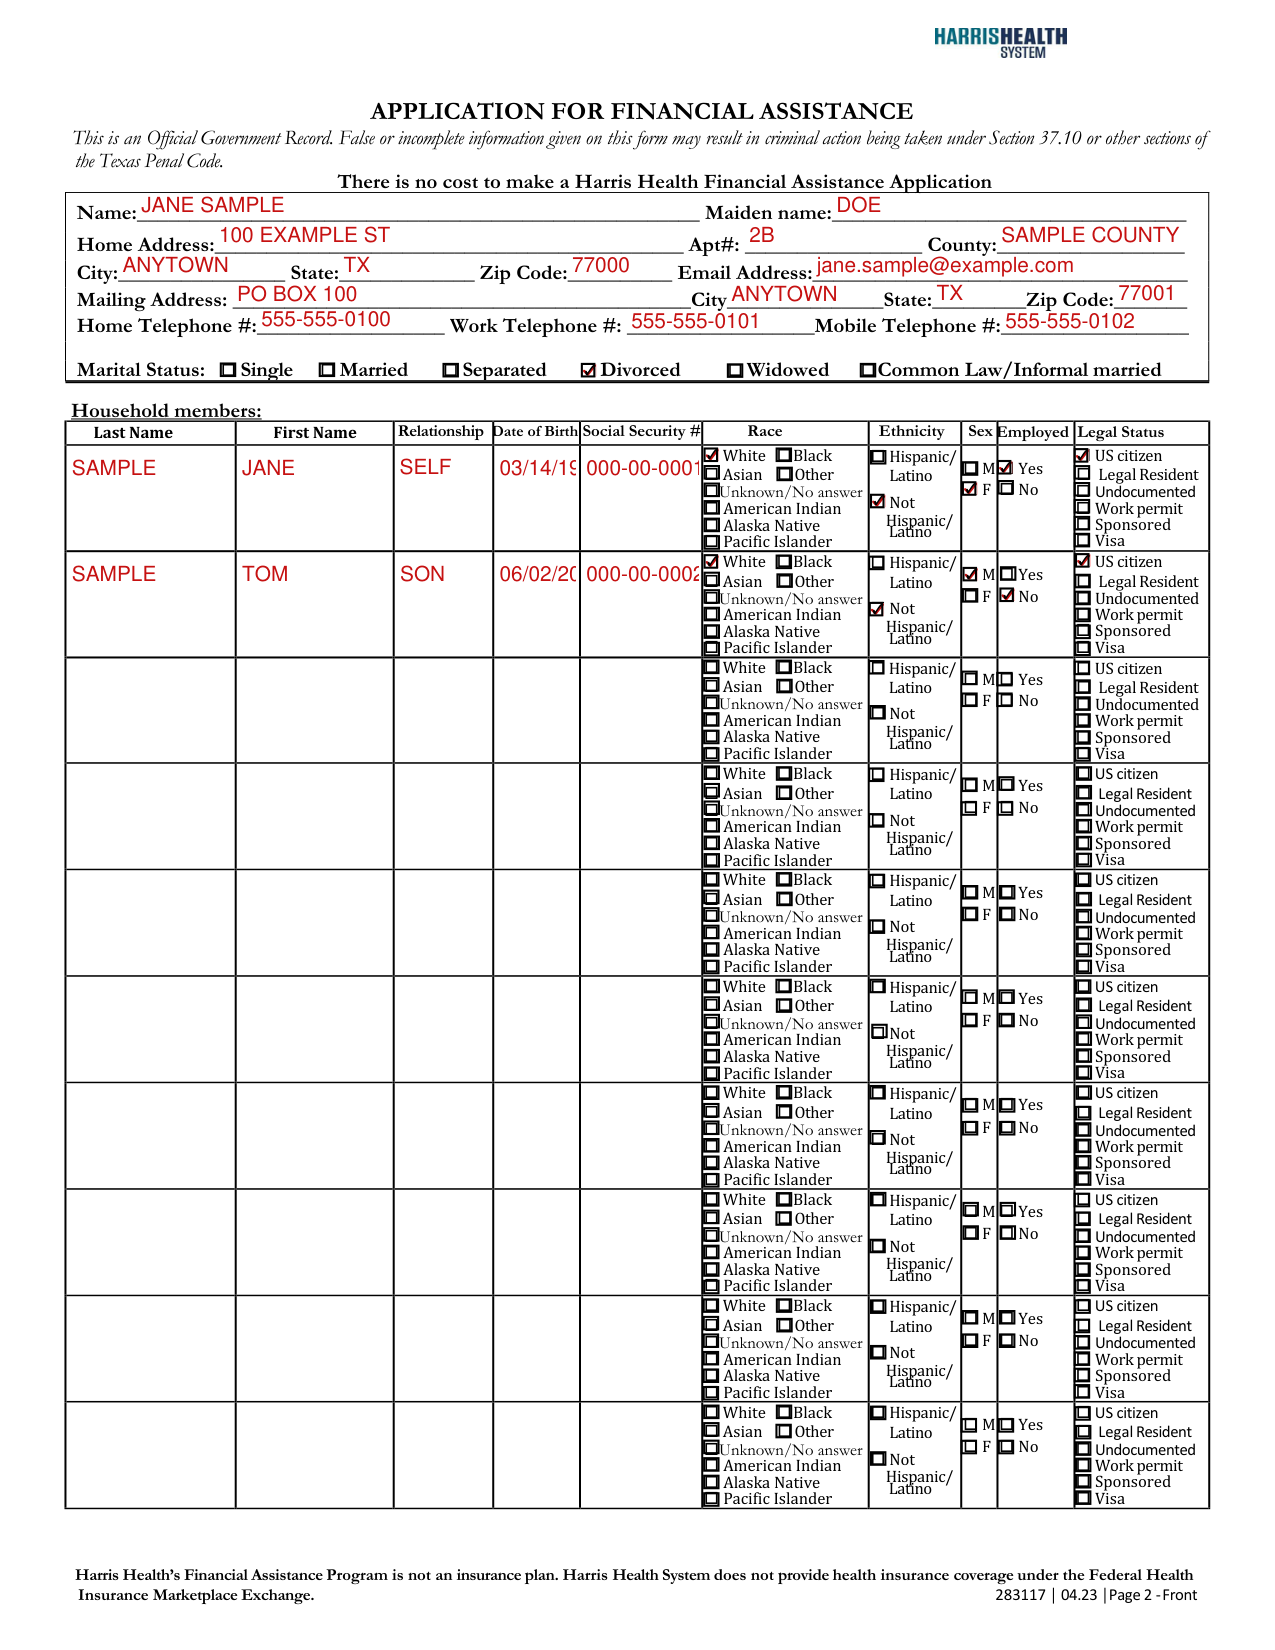
How to fill out Harris Health Application for Financial Assistance, box by box
Name and addresses

Fill in Name and Maiden name.
Fill in Home Address, Apt#, County, City, State, Zip Code and Email Address.
Fill in Mailing Address with City, State and Zip Code.
Fill in Home Telephone #, Work Telephone # and Mobile Telephone #.
Marital Status

Under Marital Status, mark Single, Married, Separated, Divorced, Widowed or Common Law/Informal married.
Household members
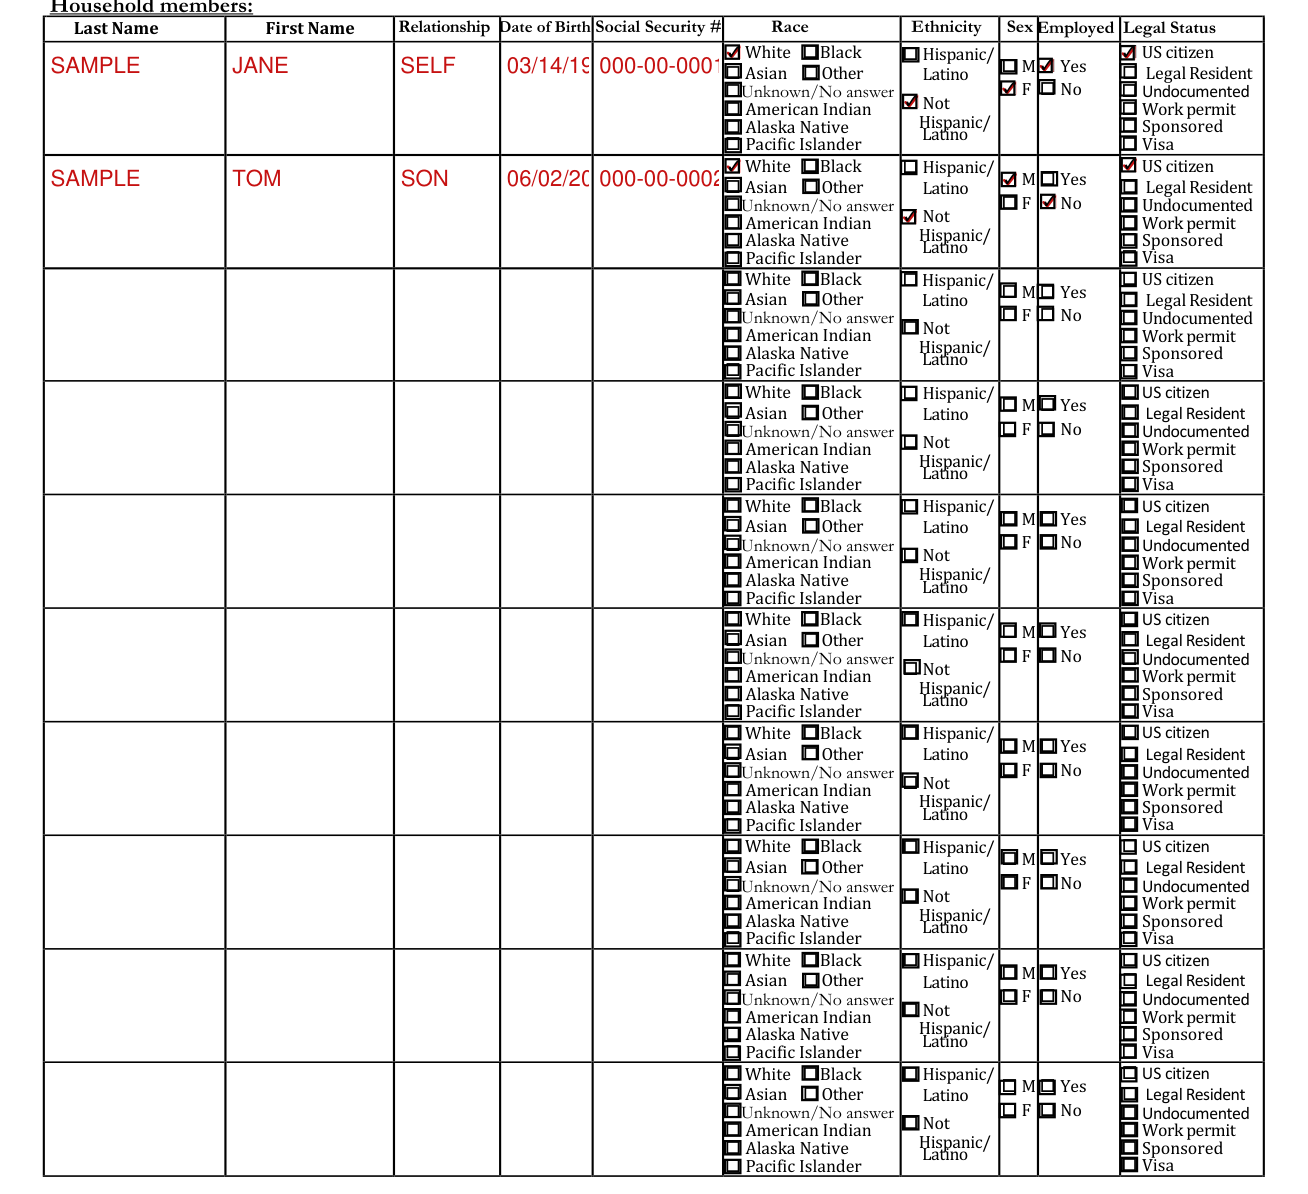
Under Household members, fill in Last Name, First Name, Relationship, Date of Birth and Social Security # for each member.
Under Race, mark White, Black, Asian, Other, Unknown/No answer, American Indian, Alaska Native or Pacific Islander.
Under Ethnicity, mark Hispanic/ Latino or Not Hispanic/ Latino.
Under Sex, mark M or F.
Under Employed, mark Yes or No.
Under Legal Status, mark U.S. citizen, Legal Resident, Undocumented, Work permit, Sponsored or Visa.
Household income
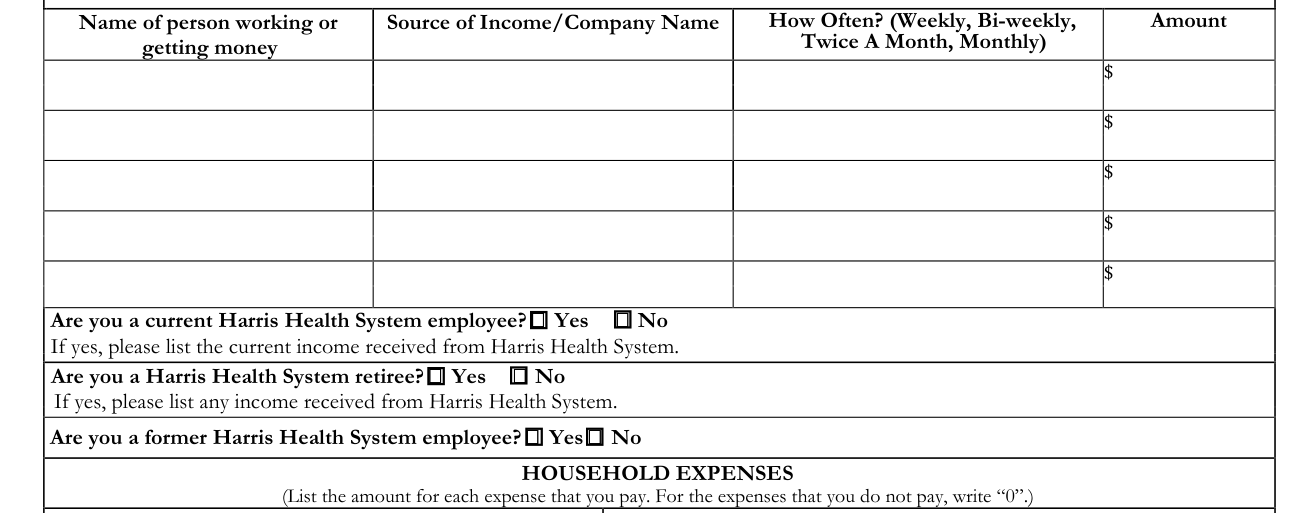
List all gross income for your family: Name of person working or getting money, Source of Income/Company Name, How Often? (Weekly, Bi-weekly, Twice A Month, Monthly) and Amount.
Are you a current Harris Health System employee? Mark Yes or No. If yes, please list the current income received from Harris Health System.
Are you a Harris Health System retiree? Mark Yes or No. If yes, please list any income received from Harris Health System.
Are you a former Harris Health System employee? Mark Yes or No.
Household expenses
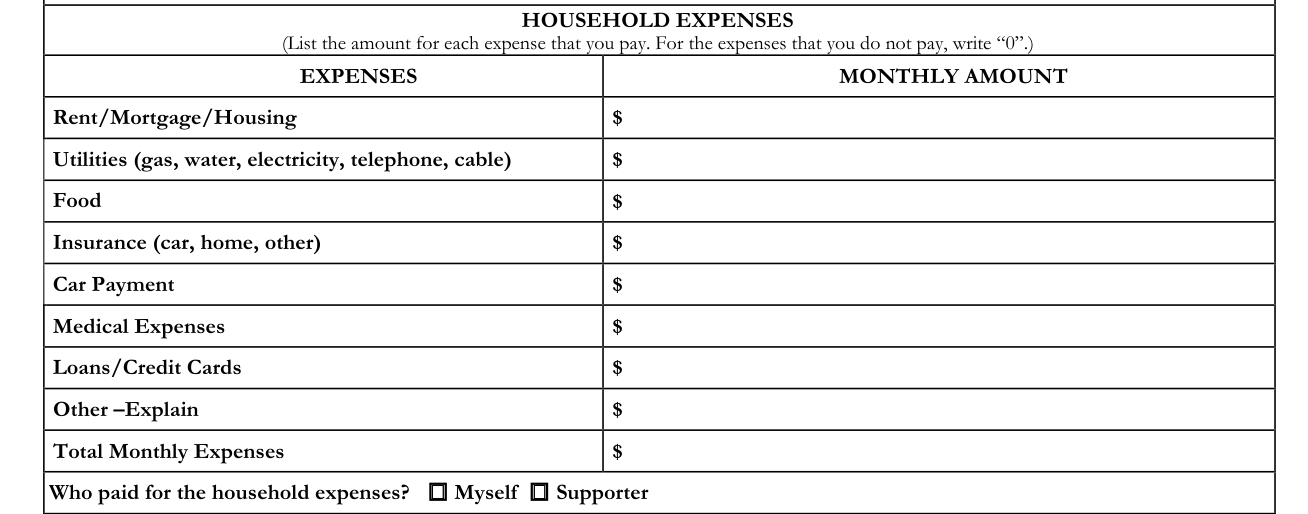
List the amount for each expense that you pay. For the expenses that you do not pay, write “0”.
List a Monthly Amount for Rent/Mortgage/Housing, Utilities (gas, water, electricity, telephone, cable), Food, Insurance (car, home, other), Car Payment, Medical Expenses, Loans/Credit Cards, Other -Explain and Total Monthly Expenses.
Who paid for the household expenses? Mark Myself or Supporter.
Veteran, pregnant, health insurance, Medicare, Social Security and medical need

Are you a veteran? Mark Yes or No.
Is anyone pregnant? Mark No, or Yes with who and the Expected Due Date.
Does anyone have health insurance? Mark No, or Yes with who, the Name of Insurance Company and Member #.
Do you or a member of your household receive Medicare because of disability or ALS or ESRD? Mark No, or Yes with who.
Have you or a member of your household applied for any Social Security benefits? Mark No, or Yes with who and When.
Is there a medical need? Mark No or Yes.
Signing

By signing this application for assistance, I affirm under penalty of perjury that the information on the application and its attachments is true and correct.
All household members over 18 must sign and date the application so to allow Harris Health System to check the Texas Workforce Commission employment records.
Mark Yes or No for “I have read the APPLICANT'S AFFIRMATION OF RIGHTS AND RESPONSIBILITIES”.
Sign and date Your signature.
Sign and date Signature of your spouse if married or common law.
Sign and date Signature of your child 18 to 26 years old who lives in your house.
Sign and date the Witness signature (if any line is signed with an “X”).
More rules for Harris Health Application for Financial Assistance
The Application for Financial Assistance is an Official Government Record.
False or incomplete information given on this form may result in criminal action being taken under Section 37.10 or other sections of the Texas Penal Code.
Deliberately omitting information or giving false or misleading information may cause Harris Health System to terminate services to me or a member of my household/family.
You must report any changes of name, address, marital status, legal status, income, household members, and health care coverage right away.
Failure to report these changes may mean you lose your assistance from Harris Health System and may be responsible to pay the costs of care from Harris Health System.
By signing, you certify under penalty of law that the information you have given to Harris Health System is true and complete to the best of your knowledge.
My signature authorizes the release of information to Harris Health System vendors, contractors, state and federal agencies, or patient assistance programs to review records for auditing purposes.
If your situation is different
You are a renewal applicant
For a Renewal Applicant (except a Medicare applicant): if your name, address, marital status, legal status, number of household member(s), and/or health care coverage has not changed since the expiration of your prior application, complete and submit this application along with your family gross income for the past 30 days only.
You have Medicare
If you have Medicare and are eligible for Harris Health Financial Assistance Program, you must fill out a Medicare Asset Form and show proof of your current resources and liabilities (all pages of bank statements, credit card, bills, loans, etc.).
Common questions about Harris Health Application for Financial Assistance
What is Harris Health Financial Assistance Program?
The Harris Health Application for Financial Assistance must be completed to obtain Harris Health financial assistance. Harris Health's Financial Assistance Program is not an insurance plan. Harris Health System does not provide health insurance coverage under the Federal Health Insurance Marketplace Exchange.
Is there a deadline?
I will report changes in my household/family situation, including changes in income, household/family members, and residency that affect eligibility during the certification period within 14 days of the change. To maintain program eligibility, I will be required to reapply for assistance at least every twelve months and potentially sooner if I am identified as eligible for any type of third-party assistance.
Where do I file it?
Mail the application to Harris Health Financial Assistance Program, P.O. Box 300488, Houston, TX 77230.
Are there fees?
There is no cost to make a Harris Health Financial Assistance Application.
Where to get help with Harris Health Application for Financial Assistance
If you have any questions, call the Eligibility Call Center at 713-566-6509.
Sources
[1] Application for Financial Assistance (283117, 04.23), Harris Health System (the Official source link on this page).
