

Health History Form at a glance
What it is: The American Dental Association Health History Form: answers are for the office records only and will be kept confidential subject to applicable laws, and the office does not use this information to discriminate.
Who signs: Sign on Signature of Patient/legal Guardian and enter the Date.
A filled-in Health History Form example: a patient fills out the top of page 1
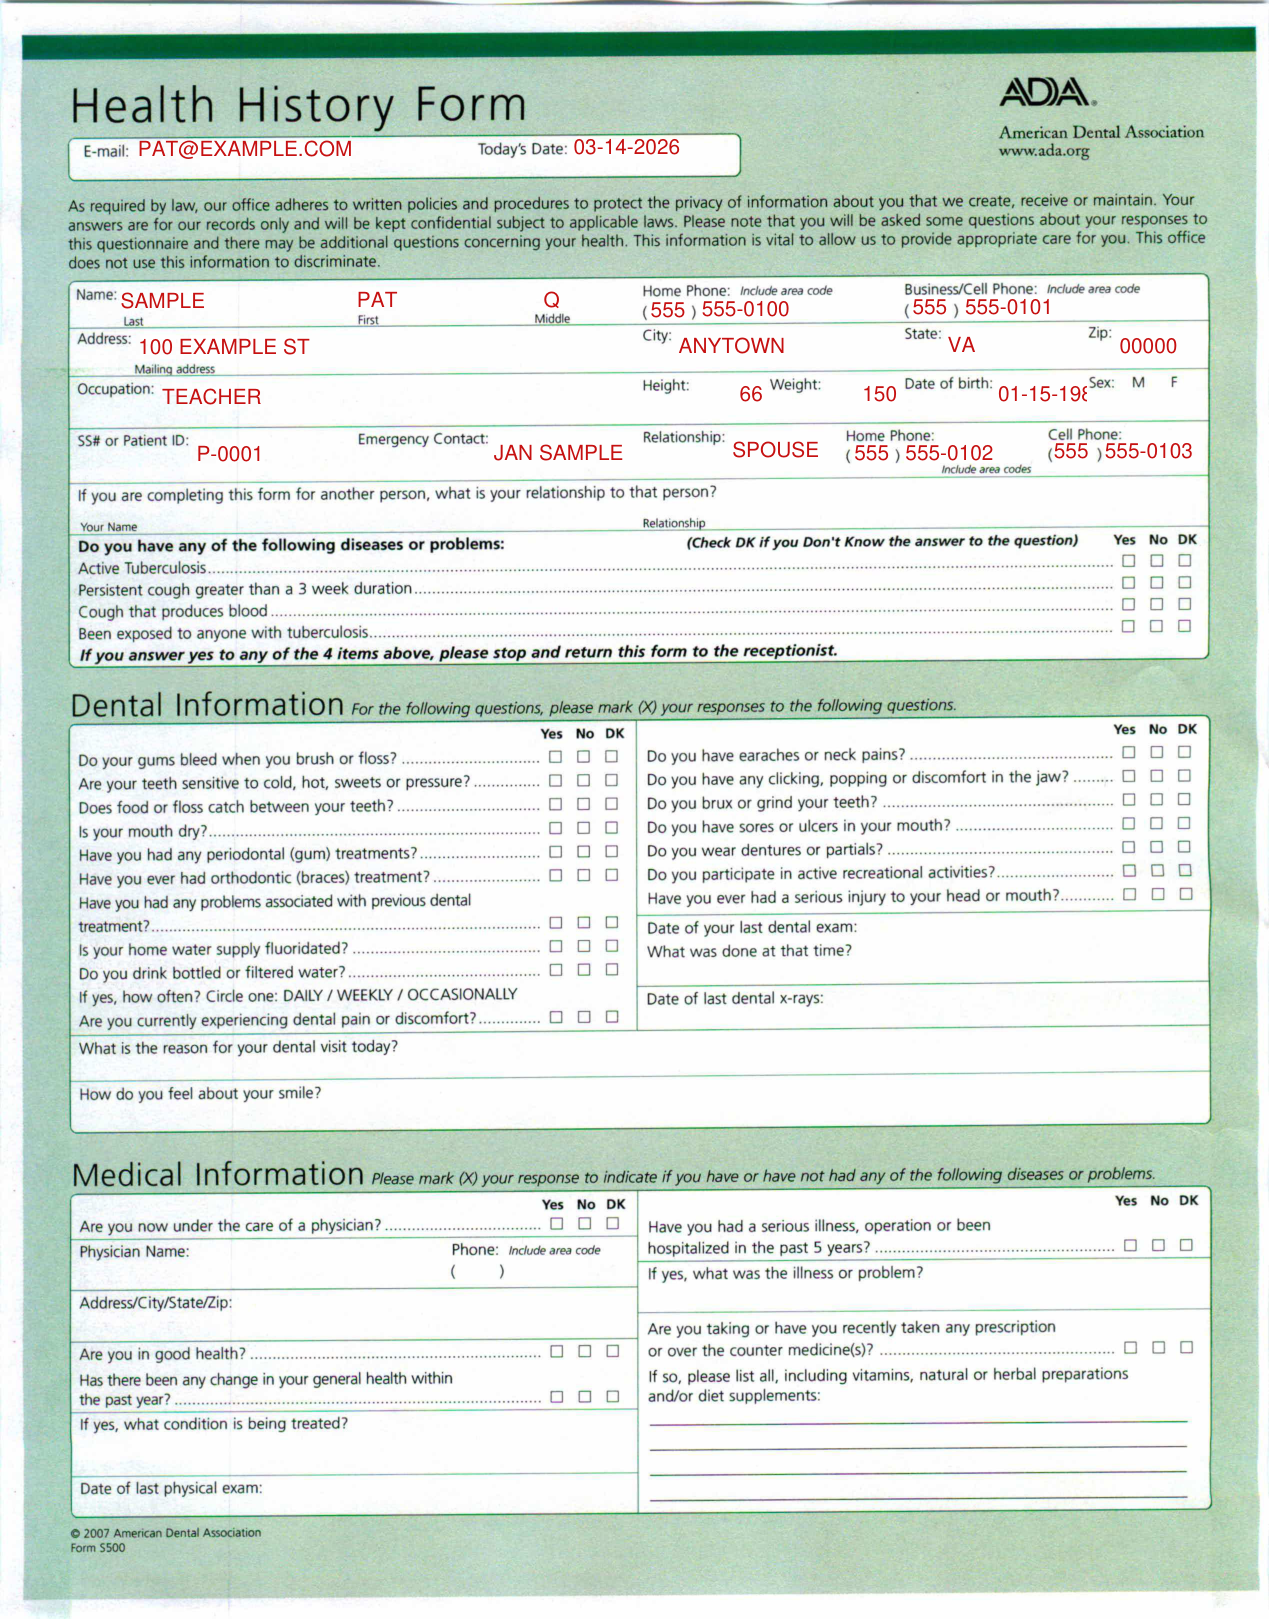
How to fill out Health History Form, box by box
Name, Address, Phone and E-mail
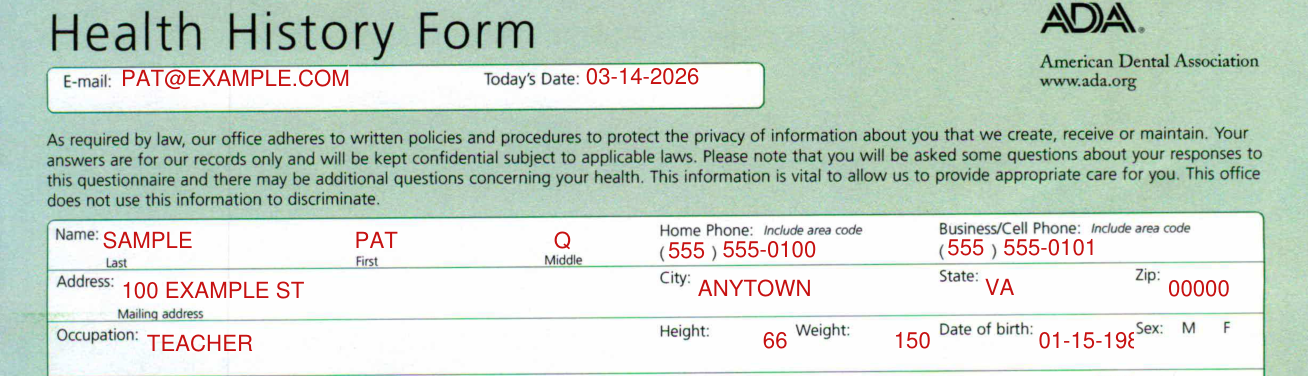
Enter your E-mail and Today's Date.
Enter your Name (last, First, Middle), Home Phone and Business/CellPhone. Include area code.
Enter your Address, City, State and Zip.
Occupation, Height, Weight and EmergencyContact

Enter your Occupation, Height, Weight and Date of birth, and mark Sex: M or F.
Enter SS#or Patient ID, EmergencyContact, Relationship, Home Phone and Cell Phone. Include area codes.
Your Name and Relationship

If you are completing this form for another person, enter Your Name and your Relationship to that person.
Active Tuberculosis

Check Yes, No or DK. Check DK if you Don't Know the answer to the question.
If you answer yes to any of the 4 items Active Tuberculosis, Persistent cough greater than a 3 week duration, Cough that produces blood or Been exposed to anyone with tuberculosis, please stop and return this form to the receptionist.
More rules for Health History Form
For the following questions, please mark (X) your responses to the following questions.
Check Yes, No or DK. Do your gums bleed when you brush or floss? Are your teeth sensitive to cold, hot, sweets or pressure? Does food or floss catch between your teeth? Is your mouth dry? Have you had any periodontal (gum) treatments? Have you ever had orthodontic (braces) treatment? Do you have earaches or neck pains? Do you have any clicking, popping or discomfort in the jaw? Do you brux or grind your teeth? Do you have sores or ulcers in your mouth? Do you wear dentures or partials? Do you participate in active recreational activities?
Have you had any problems associated with previous dental treatment? Have you ever had a serious injury to your head or mouth? Is your home water supply fluoridated? Do you drink bottled or filtered water? Are you currently experiencing dental pain or discomfort?
Enter Date of your last dental exam, What was done at that time, Date of last dental x-rays, What is the reason for your dental visit today and How do you feel about your smile.
If yes to Do you drink bottled or filtered water?, circle one: DAILY/ WEEKLY/ OCCASIONALLY.
Please mark (X) your response to indicate if you have or have not had any of the following diseases or problems.
Are you now under the care of a physician? Enter Physician Name and Phone. Include area code.
If yes to Have you had a serious illness, operation or been hospitalized in the past 5 years?, enter what was the illness or problem.
Are you taking or have you recently taken any prescription or over the counter medicine(s)? If so, please list all, including vitamins, natural or herbal preparations and/or diet supplements.
If yes to any change in your general health within the past year, enter what condition is being treated. Enter Date of last physical exam.
Do you use controlled substances (drugs)?
Have you had an orthopedic total joint (hip, knee, elbow, finger) replacement? If yes, have you had any complications?
Do you use tobacco (smoking, snuff, chew, bidis)? If so, how interested are you in stopping?
If you drink alcoholic beverages, enter how much alcohol did you drink in the last 24 hours and how much do you typically drink In a week.
WOMEN ONLY: mark Pregnant?, Taking birth control pills or hormonal replacement? and Nursing?, and enter Number of weeks.
To all yes responses about Allergies, specify type of reaction.
Check Yes, No or DK for Autoimmune disease, Rheumatoid arthritis, Asthma, Bronchitis, Emphysema. Check Yes, No or DK for Tuberculosis, Cardiovascular disease, Arteriosclerosis, Congestive heart failure, Damaged heart valves, Heart attack, Heart murmur. Check Yes, No or DK for Low blood pressure, High blood pressure, Mitral valve prolapse, Rheumatic fever, Rheumatic heart disease, Abnormal bleeding, Anemia, Blood transfusion, Hemophilia. Check Yes, No or DK for Arthritis, Chronic pain, Eating disorder, Malnutrition, Gastrointestinal disease, Ulcers, Thyroid problems, Stroke, Glaucoma, Epilepsy, Osteoporosis, Mental health disorders, Kidney problems, Chest pain upon exertion, Neurological disorders, Sexually transmitted disease, Excessive urination.
If yes to Neurological disorders, specify.
If yes to Blood transfusion, enter the date.
Has a physician or previous dentist recommended that you take antibiotics prior to your dental treatment? Enter Name of physician or dentist making recommendation and Phone.
Do you have any disease, condition, or problem not listed on this form that you think I should know about? Please explain.
Both Doctor and patient are encouraged to discuss any and all relevant patient health issues prior to treatment.
Common questions about Health History Form
Who signs it?
Sign on Signature of Patient/legal Guardian and enter the Date.
What am I certifying when I sign?
By signing you certify that you have read and understand the form and that the information given on this form is accurate.
Sources
[1] Health History Form, American Dental Association (the Official source link on this page).