

EFT/ERA Authorization Form at a glance
What it is: The EFT/ERA Authorization Form authorizes Healthfirst, called COMPANY, to initiate credit entries and, if necessary, adjustments for any credit entries to an account at the depository named.
Who signs: Add your Signature and the Date.
You need only fill out one EFT/ERA Authorization form per Tax ID as long as all the providers in the group have the same bank account.
A filled-in EFT/ERA Authorization Form example: a physician adds ERA and EFT

How to fill out EFT/ERA Authorization Form, box by box
Type of Transaction

Under Type of Transaction, choose Add ERA and EFT, Change ERA, Terminate ERA and EFT or Change EFT.
Provider/Physician Name and Provider Type
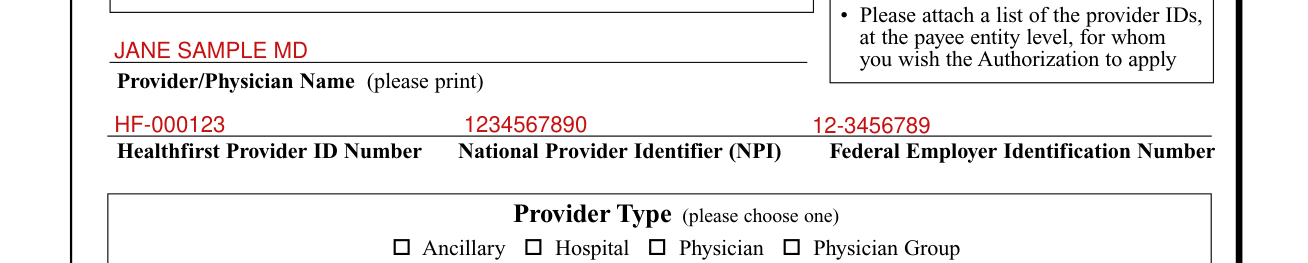
Print the Provider/Physician Name, then enter the Healthfirst Provider ID Number, National Provider Identifier (NPI) and Federal Employer Identification Number.
Physician Group Notes say to attach a list of the provider IDs, at the payee entity level, for whom you wish the Authorization to apply.
Under Provider Type, choose one: Ancillary, Hospital, Physician or Physician Group.
Account Type and Account Name

If you wish to participate in the EFT process, choose one Account Type: Checking, Savings, Demand Deposit or Money Market.
Enter the Account Name.
Depository/Bank Name
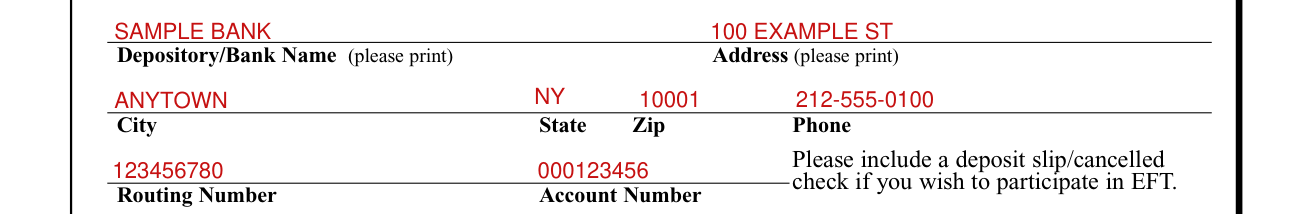
Print the Depository/Bank Name and Address, then enter the City, State, Zip and Phone.
Enter the Routing Number and the Account Number.
Please include a deposit slip/cancelled check if you wish to participate in EFT.
Clearing House

If you wish to participate in the ERA process, identify which Clearing House you (or your vendor) are currently using: Emdeon I-UB92, Emdeon P-HCFA 1500 or Other, with its Name. Please note that you or your vendor must use one of the clearing houses in order to participate in the ERA process.
Under Special ERA/Paper Remittance Note, mark I wish to receive ERA only if you wish to receive ERA only.
Signing the form

Under SIGN, print your Name and Title.
This authority is to remain in full force and effect until COMPANY has received written notification from me of its termination in such time and in such manner as to afford COMPANY and DEPOSITORY a reasonable opportunity to act on said notice of termination. Provider agrees that all ERA and/or EFT transactions will be conducted in accordance with company's policies and procedures (and may be changed from time to time) and may be suspended or discontinued at any time. Please note: At the conclusion of the grace period, paper remits will no longer be available.
Contact person

Provide the name of a contact person that can verify and provide any changes in the listed data: Contact Name, Title, Phone Number, Email Address, Address, City, State and Zip.
More rules for EFT/ERA Authorization Form
Please direct all questions to Phone: 888-801-1660.
Common questions about EFT/ERA Authorization Form
Where do I file it?
Completed forms can be submitted as follows: Mail: Provider Services, P.O. Box 5168, New York, NY 10274-5168; E-Mail: ERAEFTconfirmation@healthfirst.org; or Fax: 646-313-4635.
Sources
[1] Healthfirst EFT/ERA Authorization Form (Rev. 11/17), Healthfirst (the Official source link on this page).