

DHS-4695-ENG at a glance
What it is: The MINNESOTA HEALTH CARE PROGRAMS (MHCP) Authorization Form is filled out by the person requesting an authorization.
Who signs: Sign and date the form.
A filled-in DHS-4695-ENG example: a clinic requests a medical service
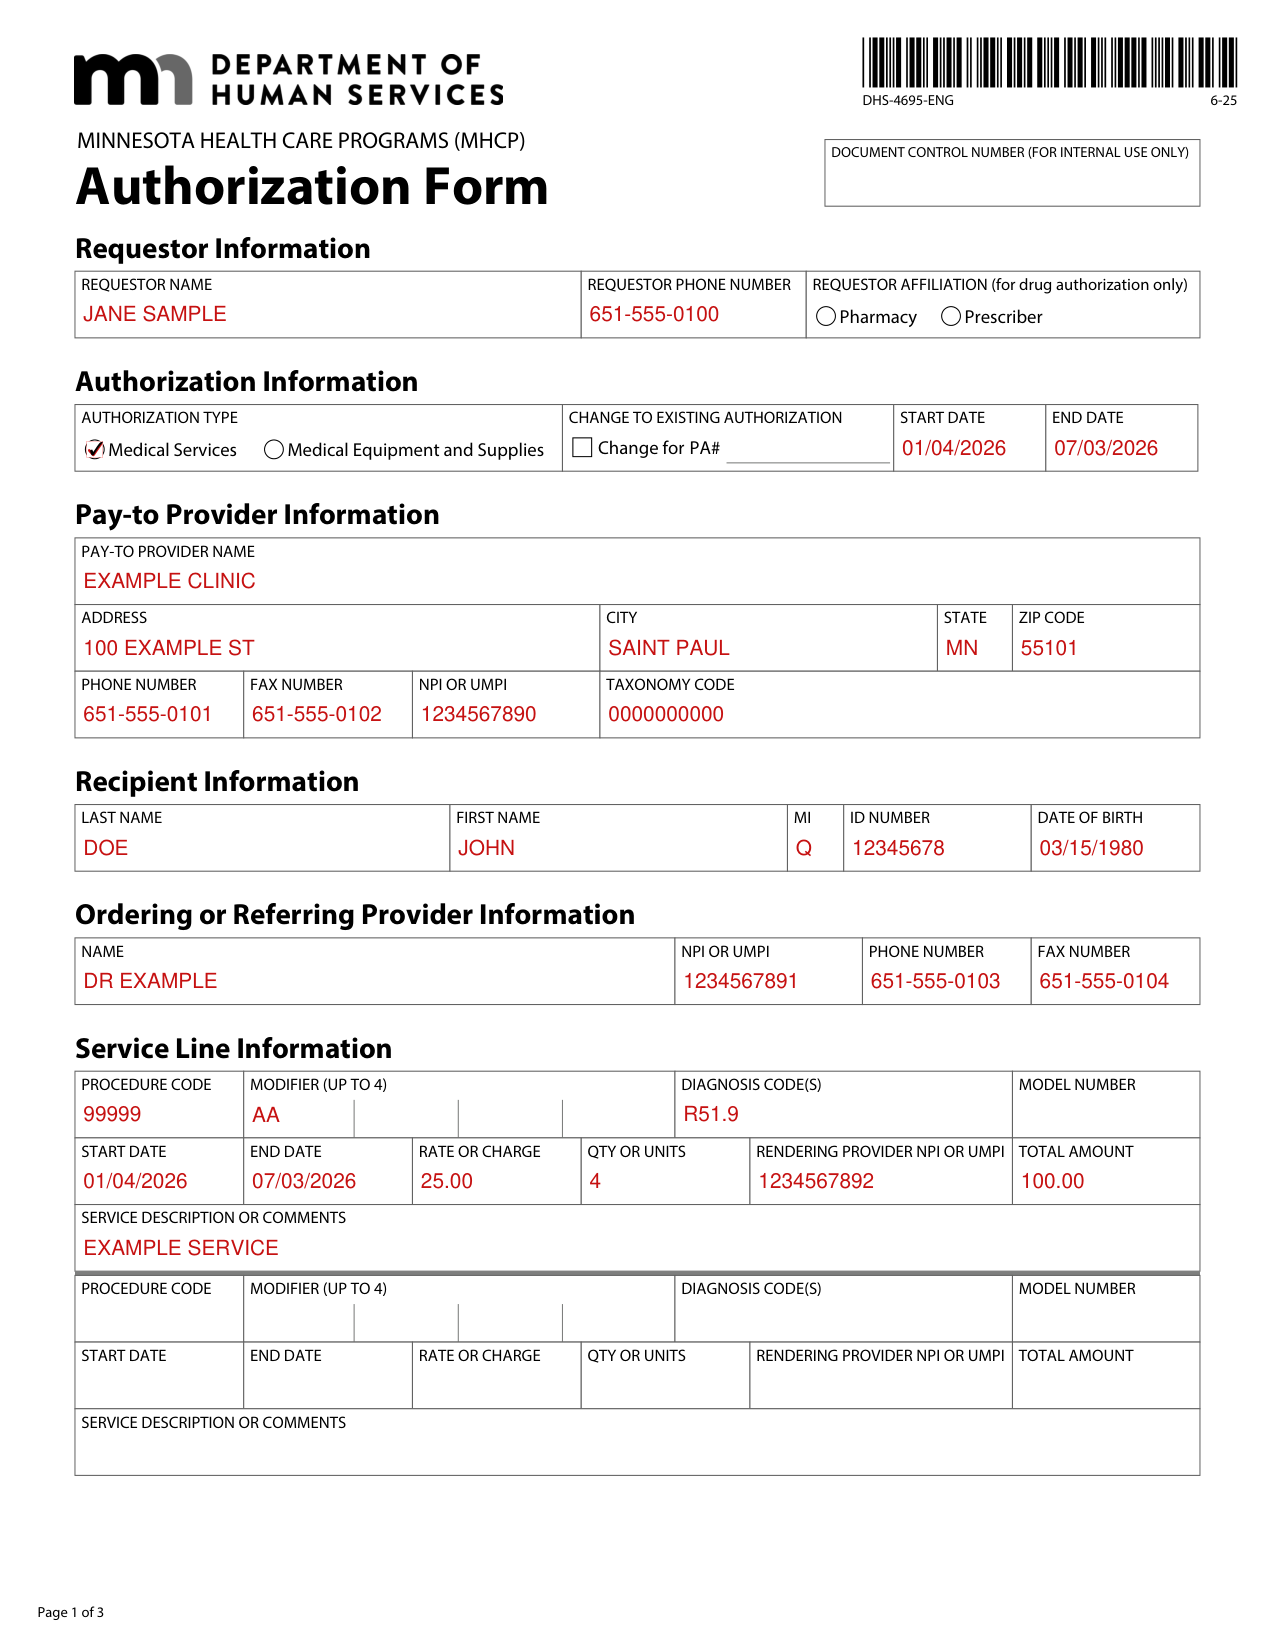
How to fill out DHS-4695-ENG, box by box
Requestor Information

Enter the first and last name of the person requesting this authorization, and the requestor's phone number.
For physician administered drug authorizations, select whether the requestor is affiliated with a pharmacy or prescriber.
Authorization Information

Place an “X” in the appropriate Authorization Type box.
If you are making a change to an existing authorization, mark the Change for PA # box and print the 11-digit authorization number you wish to update.
For the start date, enter the first date of service (MM/DD/YYYY) for this authorization request. If approved, this will be the effective date of the authorization. If service has already been provided, enter the date the service began.
For the end date, enter the last date of service (MM/DD/YYYY) for the authorization request. If service has already been provided and will not continue, enter the last date the service was provided.
Pay-to Provider Information
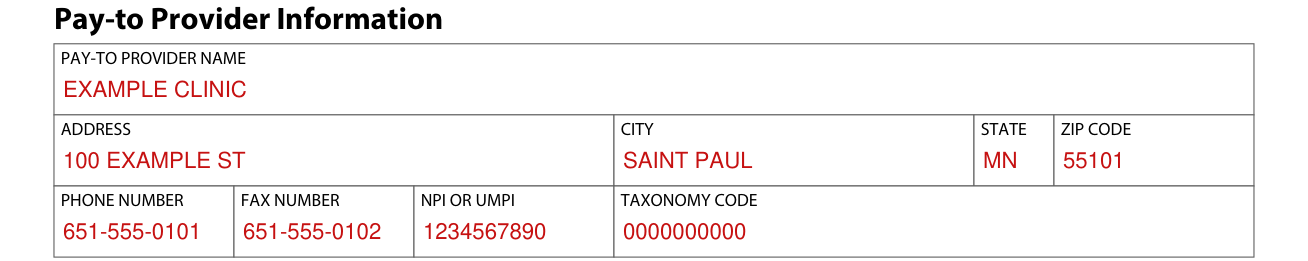
Enter the name of the pay-to provider for the service, and the provider's street address, city, state and zip code. For consolidated providers, enter the address for the location where the service was performed.
Enter the provider's phone number, fax number and NPI/UMPI.
For consolidated providers, enter the provider's taxonomy code, when applicable.
Recipient Information

Enter the recipient's last name, first name and middle initial (if known).
Enter the recipient's 8-digit MHCP ID number, and the recipient's birth date in MM/DD/YYYY format.
Ordering or Referring Provider Information

Under Ordering or Referring Provider Information, enter the name of the provider who ordered, referred or prescribed the service.
Enter the provider's 10-digit NPI or UMPI, phone number and fax number.
Service Line Information
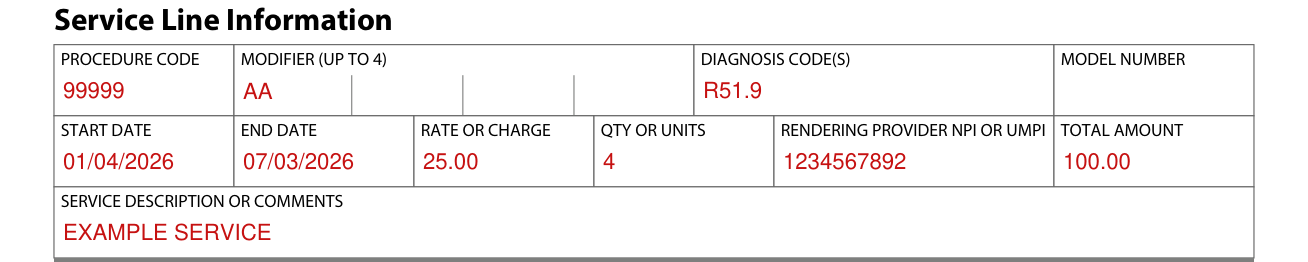
Enter the appropriate CPT/HCPCS code for the procedure/service you are requesting for authorization, any appropriate CPT/HCPCS modifier(s), and the recipient's ICD diagnosis code(s) relevant to the procedure/service.
If you are requesting authorization for a medical supply, enter the model number or UPC. If the medical supply does not have a model number or UPC, leave blank.
For the start date, enter the first date of service (MM/DD/YYYY) for the procedure listed. For the end date, enter the last date of service (MM/DD/YYYY).
Enter your usual and customary charge or requested rate of payment per unit, and the total number of procedure/service units.
For the rendering provider, enter the 10-digit NPI or UMPI of the rendering provider if different than the NPI/ UMPI listed under Provider Information.
Enter the total reimbursement amount (rate multiplied by qty/units) you are requesting for this service.
Enter comments and/or description of the service to be provided.
Signature

Sign and date the form.
More rules for DHS-4695-ENG
Complete one form per recipient.
Include supporting documentation as necessary.
Common questions about DHS-4695-ENG
Where do I file it?
For most Medical services and Equipment and Supplies, send all supporting documentation to Acentra at: Send to: Acentra Attention MN Medicaid 2810 N Parham Road, Suite 305 Henrico, VA 23294 Fax: 866-889-6512 Phone: 866-433-3658 For physician administered drugs (J-codes) ONLY, send all supporting documentation by fax or mail to: Prime Therapeutics Pharmacy LLC Attn: GV-4201 P.O. Box 64811 St. Paul, MN 55164-0811 Fax: 844-575-7887
Sources
[1] DHS-4695-ENG (6-25), MHCP Authorization Form, Minnesota Department of Human Services (the Official source link on this page).