

Medical Command Authorization Form at a glance
What it is: The Medical Command Authorization Form is an application for medical command; if approved, the authorization will be valid for the current calendar year, unless restricted or withdrawn by the ALS service medical director.
Who signs: Sign on Signature of Applicant and enter the Date.
A filled-in Medical Command Authorization Form example: an EMT-Paramedic applies for medical command authorization

How to fill out Medical Command Authorization Form, box by box
ALS Service Affiliate #, Calendar Year and your name
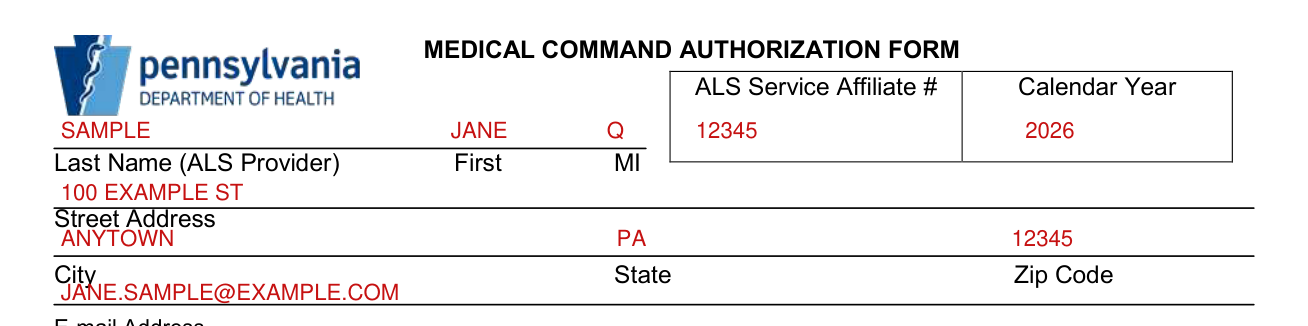
Enter the ALS Service Affiliate # and the Calendar Year.
Enter your Last Name (ALS Provider), First, MI, Street Address, City, State, Zip Code and E-mail Address.
Check One
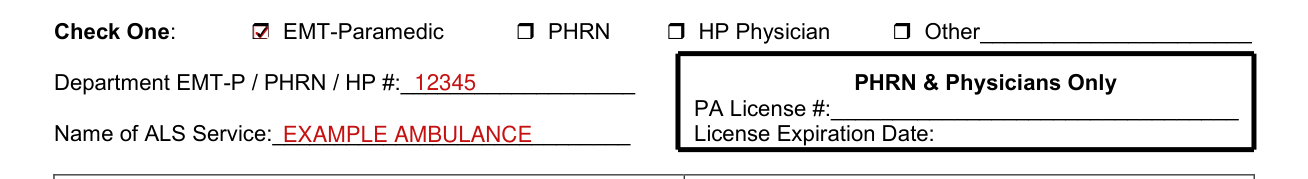
After Check One, mark EMT-Paramedic, PHRN, HP Physician or Other, then enter the Department EMT-P / PHRN / HP # and the Name of ALS Service.
PHRN & Physicians Only: enter the PA License # and the License Expiration Date.
1. List all ambulance services
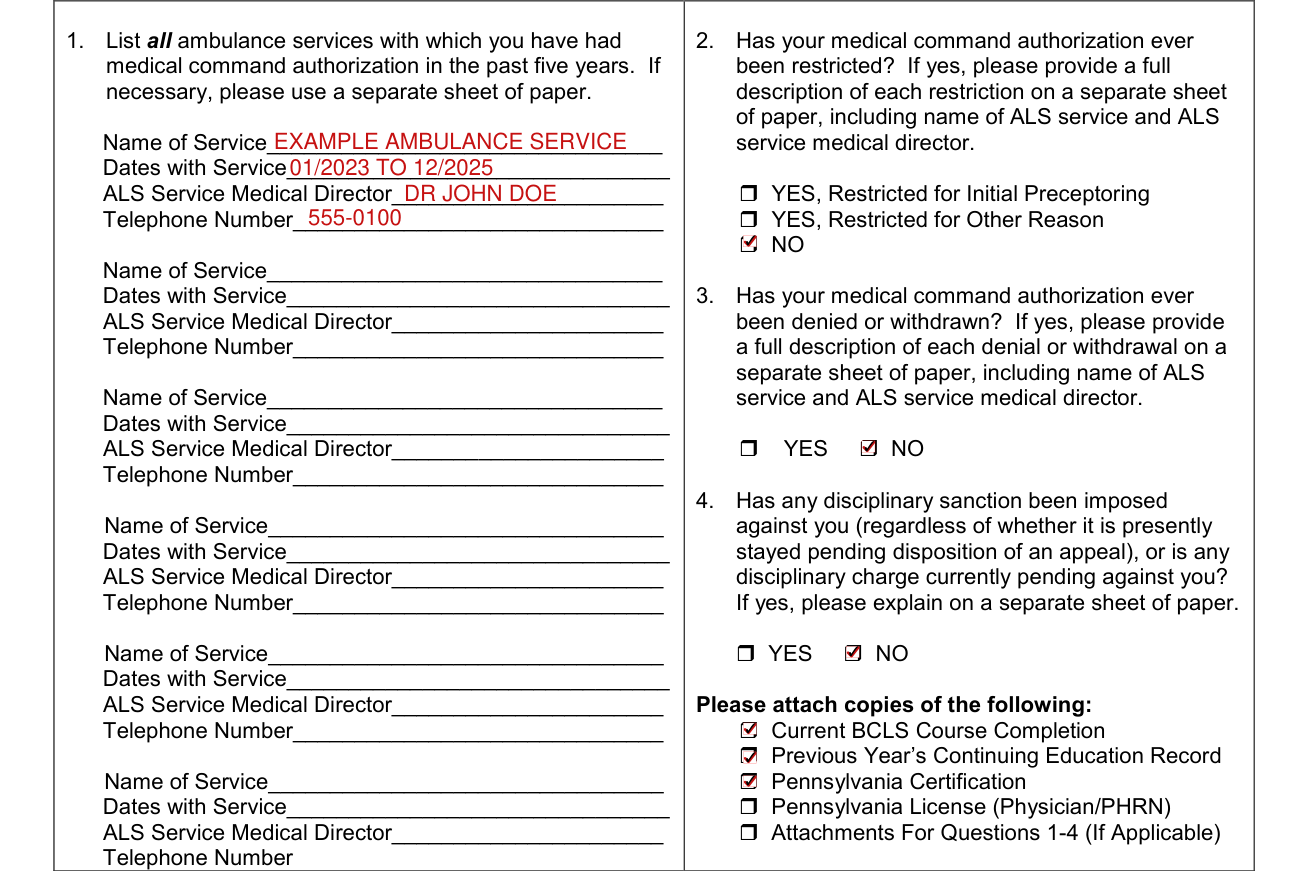
List all ambulance services with which you have had medical command authorization in the past five years; if necessary, use a separate sheet of paper.
For each service, enter the Name of Service, Dates with Service, ALS Service Medical Director and Telephone Number.
Questions 2, 3 and 4 and attachments
Question 2: has your medical command authorization ever been restricted? Mark YES, Restricted for Initial Preceptoring, YES, Restricted for Other Reason, or NO.
If your medical command authorization has ever been restricted, provide a full description of each restriction on a separate sheet of paper, including name of ALS service and ALS service medical director.
Question 3: has your medical command authorization ever been denied or withdrawn? Mark YES or NO.
If your medical command authorization has ever been denied or withdrawn, provide a full description of each denial or withdrawal on a separate sheet of paper, including name of ALS service and ALS service medical director.
Question 4: has any disciplinary sanction been imposed against you (regardless of whether it is presently stayed pending disposition of an appeal), or is any disciplinary charge currently pending against you? Mark YES or NO.
If any disciplinary sanction has been imposed against you or any disciplinary charge is currently pending against you, explain on a separate sheet of paper.
Attach copies of Current BCLS Course Completion, Previous Year's Continuing Education Record, Pennsylvania Certification, Pennsylvania License (Physician/PHRN) and Attachments For Questions 1-4 (If Applicable).
Signature of Applicant and Date

Sign on Signature of Applicant and enter the Date.
By signing, you certify that the information provided in this application is true and correct to the best of your knowledge, information, and belief.
You grant the ALS service/ medical director permission to investigate all information on this application, and you grant third parties permission to release information about your professional competence to the ALS service/ medical director.
If granted, medical command authorization applies only to the ALS service listed on this application and only permits practice in accordance with the Statewide and regional medical treatment protocols.
If your situation is different
ALS Service Medical Director Checklist
For an Initial Determination (applicant has never had medical command authorization within PA), the ALS service medical director must check each of the following: Verify continuing education requirements met, Verify certification through regional EMS council, and verify through regional EMS council that no disciplinary sanction is currently imposed against the individual that prevents the individual from receiving medical command authorization.
Under Verification of competence to perform each of the services within the individual's scope of practice, check at least one of the following: Direct observation, or Consult suitable physician, PHRN, or EMT-P who has directly observed performance of services, with the Name.
For an Annual Review or Other Review with this ALS Service (applicant has had previous medical command authorization within PA), verify continuing education requirements met and verification of competence to perform each of the services within the individual's scope of practice.
Check at least one of these, each with a Name. Direct observation. Consult suitable physician(s), PHRN(s), or EMT-P(s) who directly observed performance of services. Perform medical audit of records of service. Consult emergency department physician(s) who has received patients treated by applicant. Consult medical command physician(s) who has given command. Consult ALS service medical director(s) who has granted, restricted, or denied command.
Decision Rendered
Under Decision Rendered (Choose Only One Column), choose one of the columns Initial (with any ALS service), Initial (with this ALS service) or Review (annual or other), with Grant, Renew, Renew and Require Con. Ed., Restrict for Preceptoring, Restrict for Other, Deny and Withdraw.
The ALS service medical director signs to say: I have evaluated the individual's qualifications based upon the individual's ability to competently perform each of the services set forth within the scope of practice authorized by the individual's certification or recognition; the ALS Provider signs too, each with Printed, Signature and Date.
Sources
[1] Medical Command Authorization Form (MedCommAuthform 04/24/2013) (the Official source link on this page).