

SOC 829 at a glance
What it is: In-Home Supportive Services (IHSS) / Waiver Personal Care Services (WPCS) Provider Direct Deposit Enrollment/Change/Cancellation Form.
Who signs: Your signature authorizing direct deposit must be an ORIGINAL SIGNATURE, photocopies will not be accepted.
Where and when to file: Please send your COMPLETED Enrollment/Change/Cancellation Form to: PROVIDER FORMS PROCESSING CENTER P.O. BOX 1697 West Sacramento, CA 95691-6697. It takes 30 days for you to start receiving Direct Deposit after you submit your request. Your request for Direct Deposit does not change the way you submit your timesheets, so make sure you continue to submit your timesheets as you wait for your Direct Deposit to begin.
What to bring and attach to SOC 829
You will need the name of your Bank, the Bank Routing Number and your Checking or Savings Account Number.
A filled-in SOC 829 example: a provider enrolls in direct deposit

How to fill out SOC 829, box by box
Check the Box

Check the Box: NEW to enroll in direct deposit; CHANGE to change your bank account; and CANCEL to cancel direct deposit.
By checking NEW, you authorize the State controller's Office to directly deposit your pay warrants to your personal bank account. By checking CHANGE, you authorize the State controller's Office to change your Direct Deposit to your new personal bank account. By checking CANCEL, you cancel your Direct Deposit authorization.
Provider name and street, city, state and zip code
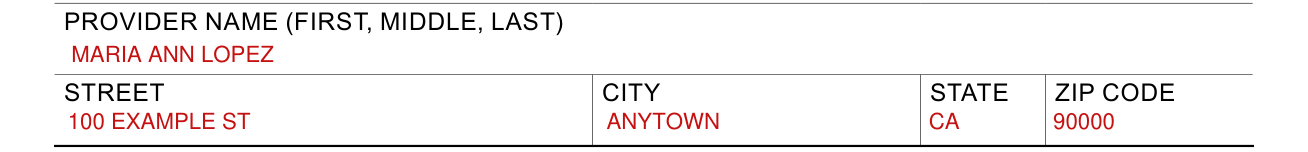
Enter the PROVIDER NAME (FIRST, MIDDLE, LAST), then the STREET, CITY, STATE and ZIP CODE.
Case number and provider number

Provide your Case and Provider number; you will find them on your IHSS statement of earnings (pay stub).
Type of account

Check the box to say whether you want your paycheck deposited in your checking or savings account (CHECK ONLY ONE TYPE).
If you prefer to have your money deposited into your savings account, contact your bank for assistance.
Banking information

Enter the ROUTING NUMBER; it MUST BE 9 NUMBERS.
Enter the ACCOUNT # and the BANK NAME.
You may find the bank information you will need to complete the enrollment form on your personal checks or your bank may assist you. If you need help identifying this information please ask your Bank for assistance.
Signature of payee (provider) and date

Sign as the PAYEE (PROVIDER) and enter the DATE.
Your signature authorizing direct deposit must be an ORIGINAL SIGNATURE, photocopies will not be accepted.
By signing you acknowledge that you will not send 100% of funds deposited to your bank to another bank outside the U.S.
More rules for SOC 829
All information requested on the form must be provided. Incomplete forms will be returned. To enroll in Direct Deposit you must complete all fields on an Enrollment/change/Cancellation form.
Multiple recipients, changing or canceling
You work for multiple recipients
If you work for multiple recipients, you must complete a separate Provider Enrollment/Change/Cancellation form for EACH Recipient with whom you are employed. When you begin work for a new recipient you will need to complete a new form.
You wish to change or cancel your Direct Deposit
Your Direct Deposit will continue to be deposited into the bank account you have chosen until you request a change. If you wish to change or cancel your Direct Deposit authorization for any recipient for whom you work, you must submit an Enrollment/Change/Cancellation form with a check next to the box for Change or Cancel.
Common questions about SOC 829
Where do I file it?
Please send your COMPLETED Enrollment/Change/Cancellation Form to: PROVIDER FORMS PROCESSING CENTER P.O. BOX 1697 West Sacramento, CA 95691-6697.
When is this form not the right one?
You are not eligible for Direct Deposit if you are planning to send 100% of funds deposited to your bank to another bank outside the U.S.
Where to get help with SOC 829
You may contact the Direct Deposit Help desk toll free at (866) 376-7066.
Sources
[1] Form SOC 829 (10/18), IHSS / WPCS Provider Direct Deposit Enrollment/Change/Cancellation Form, California Department of Social Services (the Official source link on this page).
