

In-Home Supportive Services Referral Form (Form 3012) at a glance
What it is: This is the In-Home Supportive Services Referral Form of the San Francisco Department of Disability and Aging Services.
Where and when to file: Mail to the Department of Disability and Aging Services, P.O BOX 7988, San Francisco, CA 94120.
In order to receive IHSS, the applicant must be on full-scope Medi-Cal and may still have a share of cost (based on income). DAS staff can assist the applicant in applying for Medi-Cal coverage.
What to bring and attach to In-Home Supportive Services Referral Form (Form 3012)
Please answer all questions and print clearly. The applicant's authorization for release of information is required. A completed Health Certification Form (SOC 873) is required to complete the IHSS application process. It can be submitted via fax to 415-355-2463 or emailed to ihss@sfgov.org. For questions, please call (415) 355-6700 extension 3.
A filled-in In-Home Supportive Services Referral Form (Form 3012) example: a social worker refers an applicant
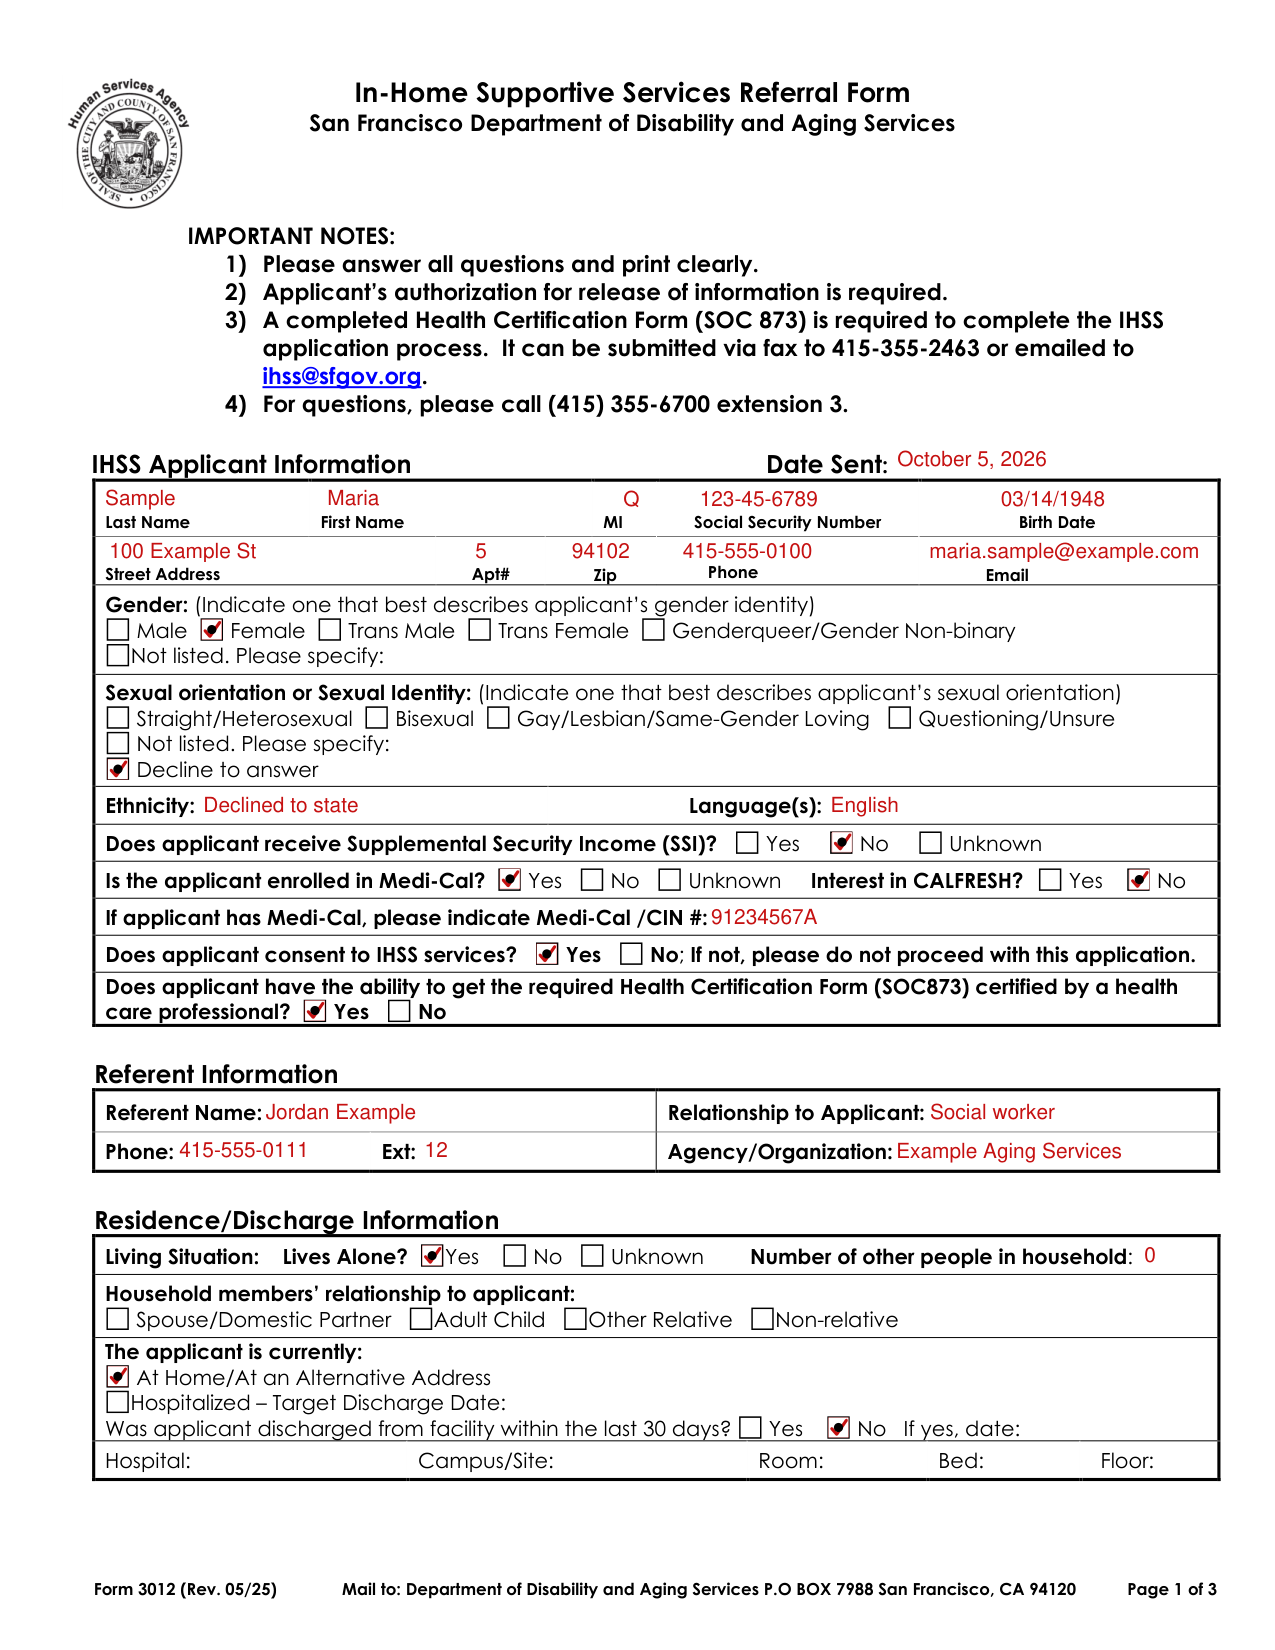
How to fill out In-Home Supportive Services Referral Form (Form 3012), box by box
IHSS Applicant Information
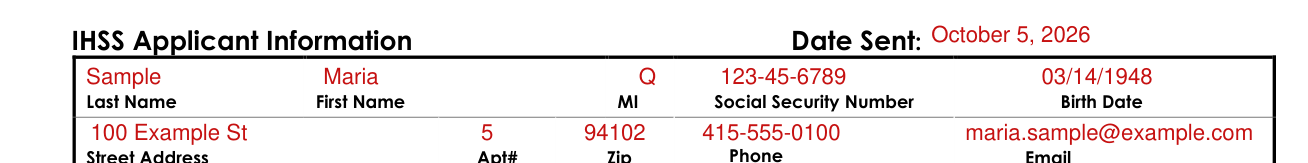
Enter the Date Sent under IHSS Applicant Information.
Enter the Last Name, First Name, MI, Social Security Number and Birth Date.
Enter the Street Address, Apt#, Zip, Phone and Email.
Gender, Sexual orientation or Sexual Identity, Ethnicity and Language(s)

Gender: indicate one that best describes the applicant's gender identity: Male, Female, Trans Male, Trans Female, Genderqueer/Gender Non-binary or Not listed. Please specify.
Sexual orientation or Sexual Identity: indicate one that best describes the applicant's sexual orientation: Straight/Heterosexual, Bisexual, Gay/Lesbian/Same-Gender Loving, Questioning/Unsure, Not listed. Please specify, or Decline to answer.
Enter the Ethnicity and Language(s).
Supplemental Security Income (SSI), Medi-Cal and CALFRESH

Does applicant receive Supplemental Security Income (SSI)? Mark Yes, No or Unknown.
Is the applicant enrolled in Medi-Cal? Mark Yes, No or Unknown. Interest in CALFRESH? Mark Yes or No.
If applicant has Medi-Cal, please indicate the Medi-Cal /CIN #.
Applicant consent to IHSS services and the Health Certification Form (SOC873)

Does applicant consent to IHSS services? Mark Yes or No. If not, please do not proceed with this application.
Does the applicant have the ability to get the required Health Certification Form (SOC873) certified by a health care professional? Mark Yes or No.
Referent Information
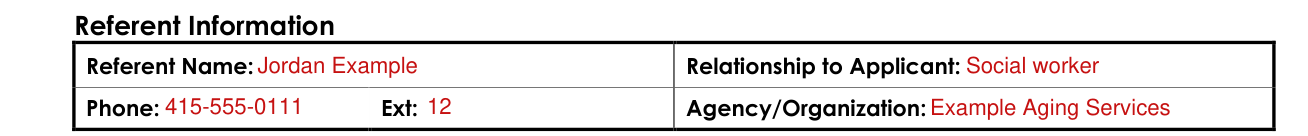
Under Referent Information, enter the Referent Name and the Relationship to Applicant.
Enter the Phone, Ext and Agency/Organization.
Living Situation
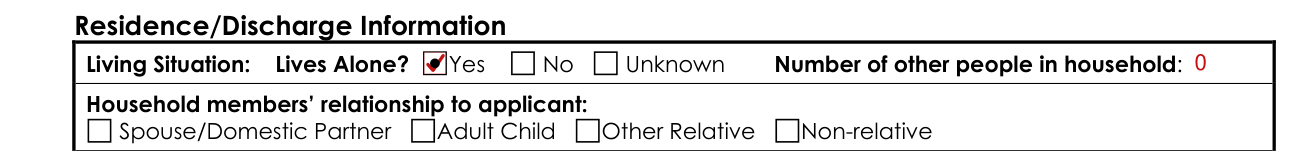
Living Situation: Lives Alone? Mark Yes, No or Unknown. Enter the Number of other people in household.
Household members' relationship to applicant: mark Spouse/Domestic Partner, Adult Child, Other Relative or Non-relative.
The applicant is currently

The applicant is currently: mark At Home/At an Alternative Address or Hospitalized, with a Target Discharge Date. Was applicant discharged from facility within the last 30 days? Mark Yes or No. If yes, enter the date.
Enter the Hospital, Campus/Site, Room, Bed and Floor.
Spouse/Other IHSS Recipient
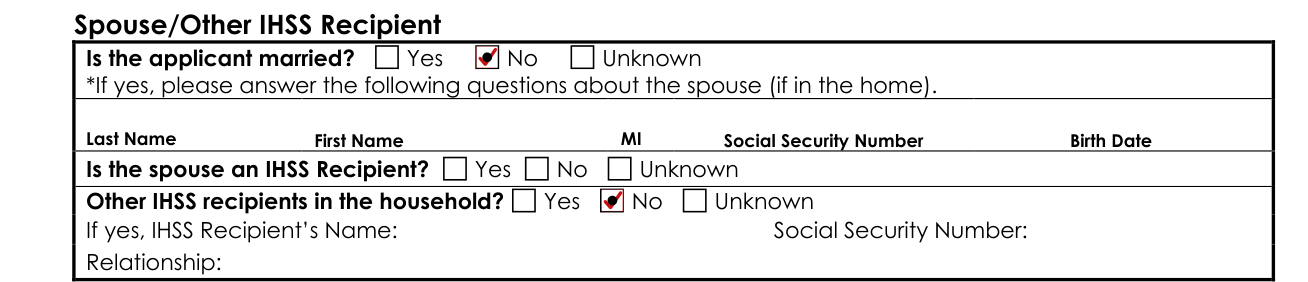
Spouse/Other IHSS Recipient: Is the applicant married? Mark Yes, No or Unknown. If yes, please answer the following questions about the spouse (if in the home).
Enter the spouse's Last Name, First Name, MI, Social Security Number and Birth Date. Is the spouse an IHSS Recipient? Mark Yes, No or Unknown. Other IHSS recipients in the household? Mark Yes, No or Unknown. If yes, enter the IHSS Recipient's Name, Social Security Number and Relationship.
Back Up Provider Services (BUPS)

Back Up Provider Services (BUPS): Is BUPS (emergency home care) requested? Mark Yes or No. DAS is unable to authorize emergency home care services without a completed Health Care Certification form SOC 873. Please fax the SOC 873 to DAS Intake at (415)355-2463. If yes, enter why emergency home care is needed.
Enter how the applicant's needs will be met until IHSS eligibility and services are established.
Physician/Clinic Information

Under Physician/Clinic Information, enter the Name (Last Name and First Name) and the Specialty.
Address: enter the Street Address, City, State and Zip.
Enter the Phone Number, Fax and Email.
Medical and Mental Health Information
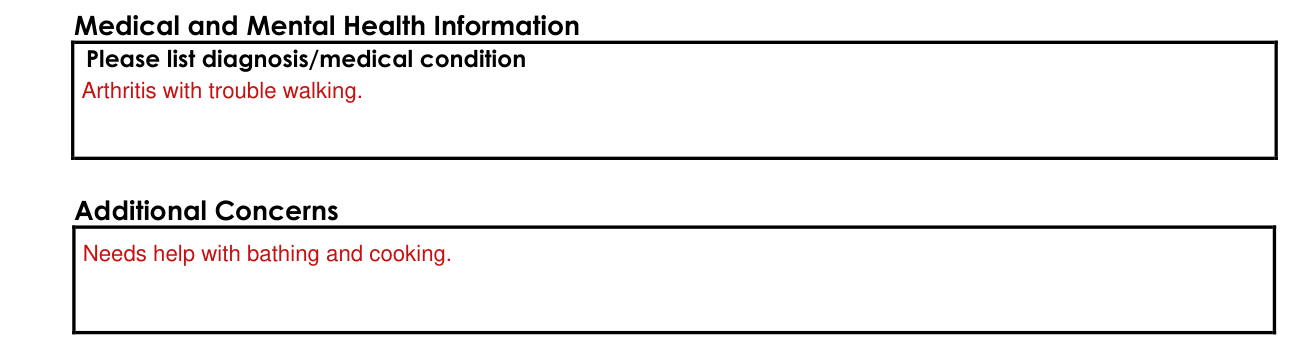
Medical and Mental Health Information: please list the diagnosis/medical condition.
Enter the Additional Concerns.
Emergency Contact Information
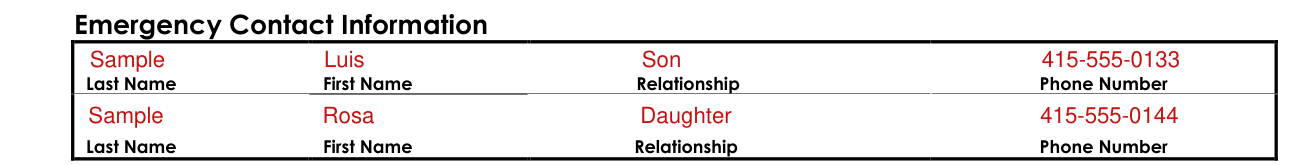
Under Emergency Contact Information, enter the Last Name, First Name, Relationship and Phone Number on each line.
Risks

Risks: Does the applicant currently exhibit or have history of Violent Behavior or Financial management/Eviction? Mark Active, Not Active, Past History or Unknown for each. Explain (If Active or Past History).
Other Circumstances

Other Circumstances: mark Yes, No or Unknown for each, and explain (If answer is YES). Is applicant at risk of abuse or have a history of being abused? Does applicant currently have or have history of suicidal ideation?
Please indicate any potential dangers to the worker visiting the applicant (e.g. aggressive pet, weapons, property hazards, potentially abusive person on site, etc.).
Support System and Other Services

Support System: how are the applicant's service needs currently being met? Please be as specific as possible and include information about current caregiver(s) and areas of need.
Other Services: please list other services the applicant is currently receiving.
Common questions about In-Home Supportive Services Referral Form (Form 3012)
Where do I file it?
Mail to the Department of Disability and Aging Services, P.O BOX 7988, San Francisco, CA 94120.
Sources
[1] In-Home Supportive Services Referral Form, Form 3012 (Rev. 05/25), San Francisco Department of Disability and Aging Services (the Official source link on this page).
