


Reimbursement Request Form at a glance
What it is: Reimbursement Request Form: fill up this form and attach the required documents.
Where and when to file: Filing of Claims have corresponding TATs depending on contractual stipulations, although the standard allowable period for acceptance and processing is within thirty (30) days from the point of the procedure or consultation.
What to bring and attach to Reimbursement Request Form
BASIC REQUIREMENTS: a duly filled up reimbursement request form.
BASIC REQUIREMENTS: a Detailed Charge Invoice from the hospital/clinic.
BASIC REQUIREMENTS: an Invoice.
BASIC REQUIREMENTS: a Medical Certificate with diagnosis.
A filled-in Reimbursement Request Form example: a clinic visit paid by bank crediting
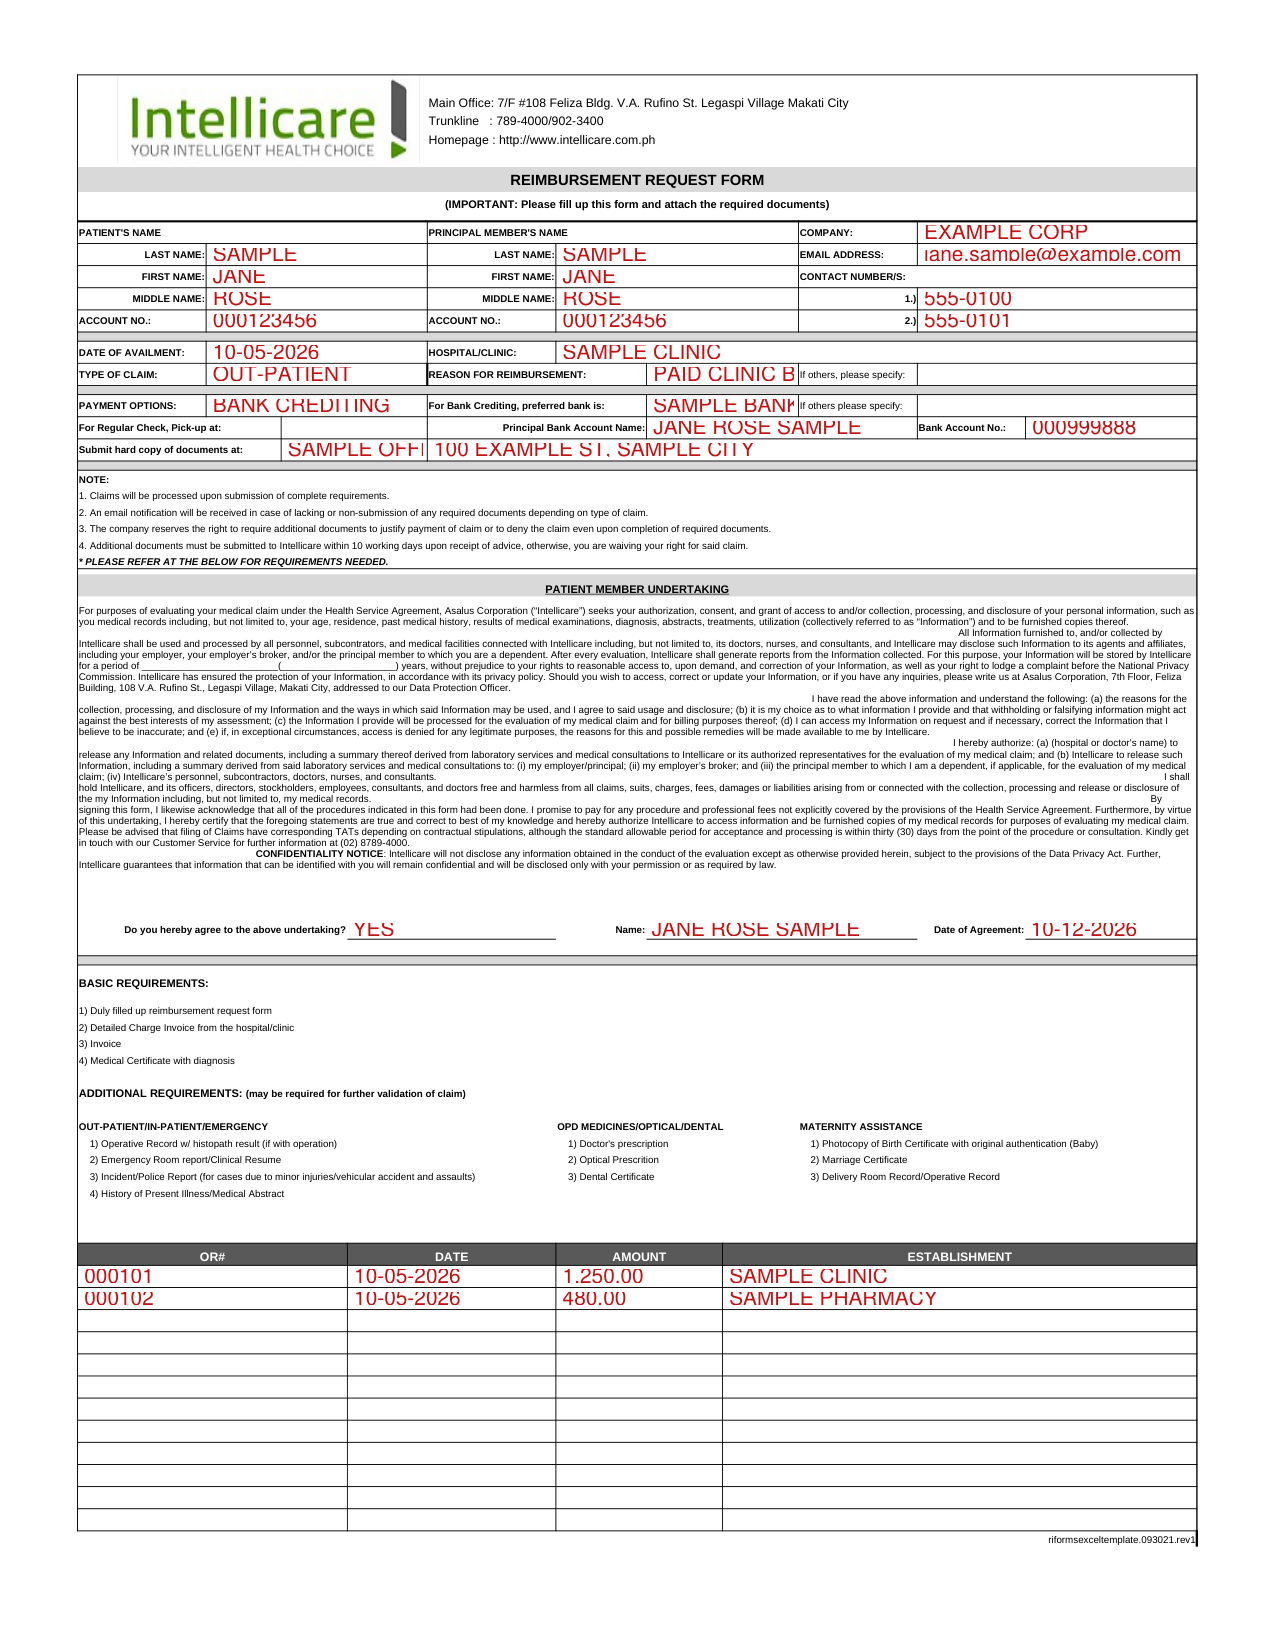
How to fill out Reimbursement Request Form, box by box
Patient, principal member and contact
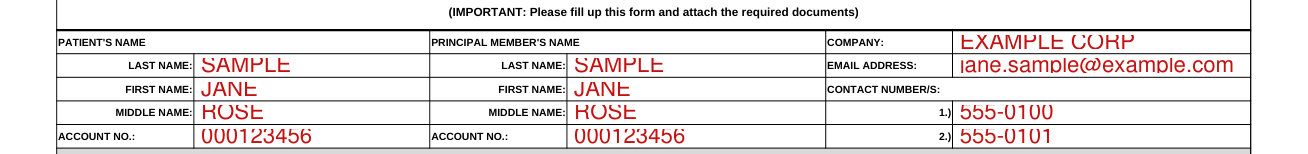
Under Patient's Name and Principal Member's Name, enter the Last Name, First Name, Middle Name and Account No. of each. Enter the Company, the Email Address and the Contact Number/s, 1.) and 2.).
Type of claim and reason for reimbursement

Enter the DATE OF AVAILMENT, the HOSPITAL/CLINIC, the TYPE OF CLAIM and the REASON FOR REIMBURSEMENT. If others, please specify.
Payment options

Under PAYMENT OPTIONS, fill in: For Bank Crediting, preferred bank is (If others please specify); For Regular Check, Pick-up at; Principal Bank Account Name; Bank Account No.
Submit hard copy of documents at

Fill in where to submit the hard copy of documents.
OR# DATE AMOUNT ESTABLISHMENT
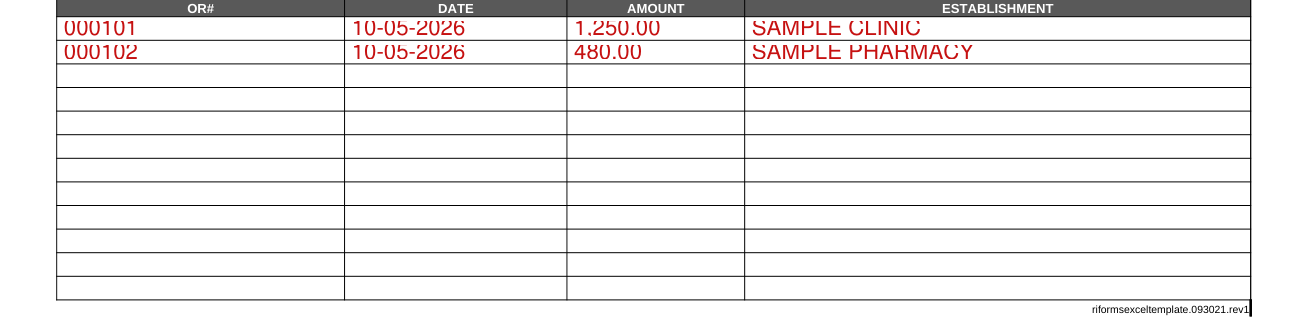
For each row, enter the OR#, the DATE, the AMOUNT and the ESTABLISHMENT.
Patient Member Undertaking

Under PATIENT MEMBER UNDERTAKING, fill in Name and Date of Agreement.
By signing this form, you acknowledge that all of the procedures indicated in this form had been done.
By signing this form, you promise to pay for any procedure and professional fees not explicitly covered by the provisions of the Health Service Agreement.
The undertaking certifies that the statements are true and correct to best of knowledge.
More rules for Reimbursement Request Form
NOTE: Claims will be processed upon submission of complete requirements.
NOTE: An email notification will be received in case of lacking or non-submission of any required documents depending on type of claim.
NOTE: The company reserves the right to require additional documents to justify payment of claim or to deny the claim even upon completion of required documents.
Additional requirements
OUT-PATIENT/IN-PATIENT/EMERGENCY
ADDITIONAL REQUIREMENTS (may be required for further validation of claim) for OUT-PATIENT/IN-PATIENT/EMERGENCY: 1) Operative Record w/ histopath result (if with operation); 2) Emergency Room report/Clinical Resume; 3) Incident/Police Report (for cases due to minor injuries/vehicular accident and assaults); 4) History of Present Illness/Medical Abstract.
OPD MEDICINES/OPTICAL/DENTAL
ADDITIONAL REQUIREMENTS (may be required for further validation of claim) for OPD MEDICINES/OPTICAL/DENTAL: 1) Doctor's prescription; 2) Optical Prescription; 3) Dental Certificate.
MATERNITY ASSISTANCE
ADDITIONAL REQUIREMENTS (may be required for further validation of claim) for MATERNITY ASSISTANCE: 1) Photocopy of Birth Certificate with original authentication (Baby); 2) Marriage Certificate; 3) Delivery Room Record/Operative Record.
Where to get help with Reimbursement Request Form
Get in touch with Customer Service at (02) 8789-4000 for further information.
Sources
[1] Reimbursement Request Form, Intellicare (the Official source link on this page).