
Kaiser Referral Request Form – Fill Out and Use This PDF
Updated:
The Kaiser Referral Request form is a critical document within Kaiser Permanente Colorado's system for managing the referral process for their patients to specialists or additional services. It serves as a bridge, ensuring that all necessary prior authorization requirements are met and that the transition of care is seamless and efficient. Whether the need is routine or urgent, with services expected within 72 hours, this form facilitates communication between primary care providers and specialists, streamlining patient care. Ready to submit a referral? Click the button below to fill out your form.
Get Form Now
Download PDF
Kaiser Referral Request Form PDF Details
Navigating healthcare protocols can often feel like a maze, but tools like the Kaiser Permanente Colorado Prior Authorization Request Form are designed to streamline processes for both healthcare providers and patients. This form, crucial for facilitating various healthcare services within Kaiser Permanente's network, especially in Colorado, carries significant importance. Required for both routine and urgent referrals, it ensures that patients receive the necessary pre-approval for medical procedures or consultations they may need. With dedicated fax numbers for different regions, such as Southern Colorado and Denver/Northern Colorado, and a specific line for preauthorization questions, the form outlines a structured pathway for submitting requests. Essential details such as the patient's Kaiser Permanente number, personal information, the referring and requested physicians' details, preliminary diagnosis, ICD codes, and the demanded service or procedure with the expected date are all integrated into the form to expedite the authorization process. This meticulous compilation of data underlines the importance of including relevant clinical information to support the request, highlighting the balance between bureaucratic requirement and clinical need. Furthermore, it reminds users to avoid abbreviations or acronyms, ensuring clarity and preventing misunderstandings that could delay patient care. Established in April 2013, this form represents a critical interface between healthcare bureaucracy and patient care, underpinning the logistical framework necessary for efficient healthcare delivery within the Kaiser Permanente ecosystem.
Question
Answer
Form Name
Kaiser Referral Request Form
Form Length
1 pages
Fillable?
Yes
Fillable fields
20
Avg. time to fill out
4 min 19 sec
Other names
kaiser colorado prior authorization form, kaiser authorization request form, kaiser authorization colorado, kaiser permanente pharmacy prior auth form
12
How to Fill Out Referral Request Form
Referral Request Form at a glance
What it is: Referral form to fax to Kaiser Moanalua (MOA) or Kaiser Authorization Dept.
Where and when to file: For STAT Care after hours or on weekends, call Kaiser MOA Operator (808) 432-0000 and have Specialist On-Call paged. If verbal authorization is obtained, submit this form the next Business Day.
A filled-in Referral Request Form example: a clinician faxes a routine referral

Pat Sample, a clinician, faxes the Kaiser referral request form. Pat requests a routine specialty consult for a patient, with clinical notes faxed along. The picture shows page 1, and every value in it is made up. The fax goes to Kaiser Moanalua (MOA), so Kaiser Authorization Dept stays empty. It is a Clinician Request, so Patient Request stays empty. The notes are faxed, so EPIC EMR Notes stays empty. The care is routine, so Urgent Episode Related Services stays empty. The PDF has no fillable box for Patient Name, Date of Birth, Kaiser Medical Record # or the Physician/Facility under REFERRING FROM, so the picture leaves them empty; after printing, the reader writes them in by hand.
How to fill out Referral Request Form, box by box
Fax completed form to
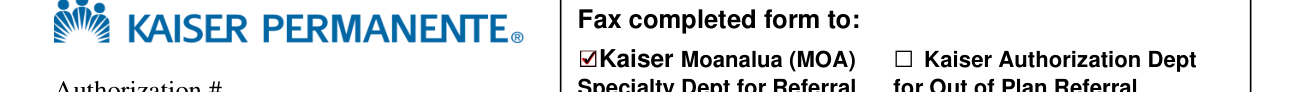
Fax completed form to Kaiser Moanalua (MOA) for the Specialty Dept for Referral, Phone (808) 432-8359, Fax (808) 432-7380, or to Kaiser Authorization Dept for Out of Plan Referral, Phone (808) 432-5687, Fax (808) 432-5691, Alt Fax (808) 432-5667.
Request (Select 1), notes and care

Select 1 of Clinician Request or Patient Request. Select 1 of Fax Clinical Notes with this Request or EPIC EMR Notes in “Care Everywhere”. Select 1 of Routine Care or Urgent Episode Related Services.
Member information
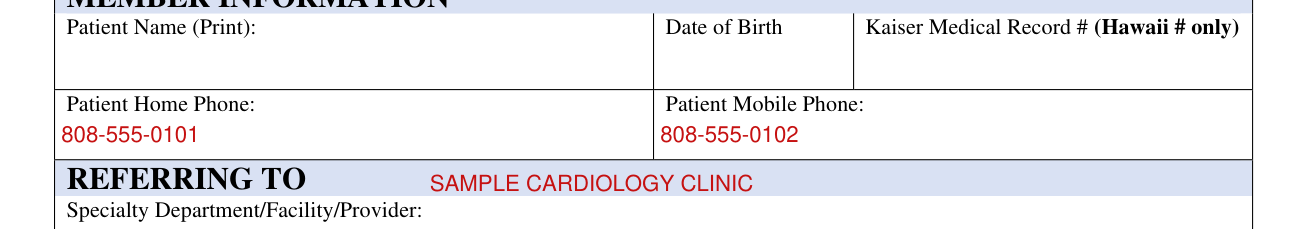
Under MEMBER INFORMATION, print the Patient Name, then fill in the Date of Birth, the Kaiser Medical Record # (Hawaii # only), the Patient Home Phone and the Patient Mobile Phone.
Referring to
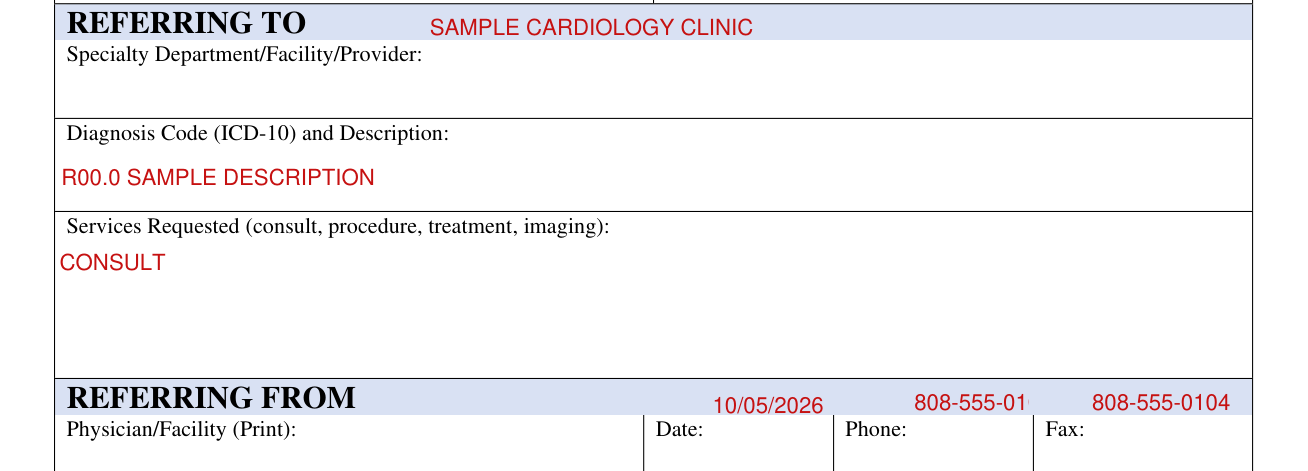
Under REFERRING TO, fill in the Specialty Department/Facility/Provider, the Diagnosis Code (ICD-10) and Description, and the Services Requested (consult, procedure, treatment, imaging).
Referring from

Under REFERRING FROM, print the Physician/Facility, then fill in the Date, Phone and Fax.
More rules for Referral Request Form
Send Invoices / Bills to Kaiser Foundation Health Plan, Inc. Phone Number: 1-877-875-3805 Hawaii Claims Administration P. O. Box 378021 Denver, CO 80237.
This does not guarantee payment. For information on the extent of this patient's coverage and current-membership status, contact Customer Service at 808-432-5955 (on Oahu) or 1-800-966-5955 (Outer Islands).
Sources
[1] Kaiser Referral Request Form (Rev 03/04/2022; the served file, no issuer file found) (the Official source link on this page).
Kaiser Referral Request Form isn’t the one you’re looking for?