

Form HI-22 at a glance
What it is: HI-22 is the Los Angeles Unified School District Benefits Administration application for continuation of health benefits.
Who signs: Sign on the Applicant's Signature line and enter the Date.
To receive coverage as a retired employee, you must meet the following requirements: Employee must be eligible or enrolled in District-sponsored health benefits and be in paid status on the selected retirement date.
You must resign to retire from District service and be eligible to receive an allowance from your retirement system (Calstrs or Calpers) for either age or disability retirement the day after your District resignation. Your District resignation date and Calstrs/Calpers retirement date must be consecutive dates (may include weekend days).
You must receive a monthly retirement payment from your retirement system.
What to bring and attach to Form HI-22
If you and/or your spouse is age 65 or older, you must attach a copy of your Medicare card.
A filled-in Form HI-22 example: a service retirement with a spouse
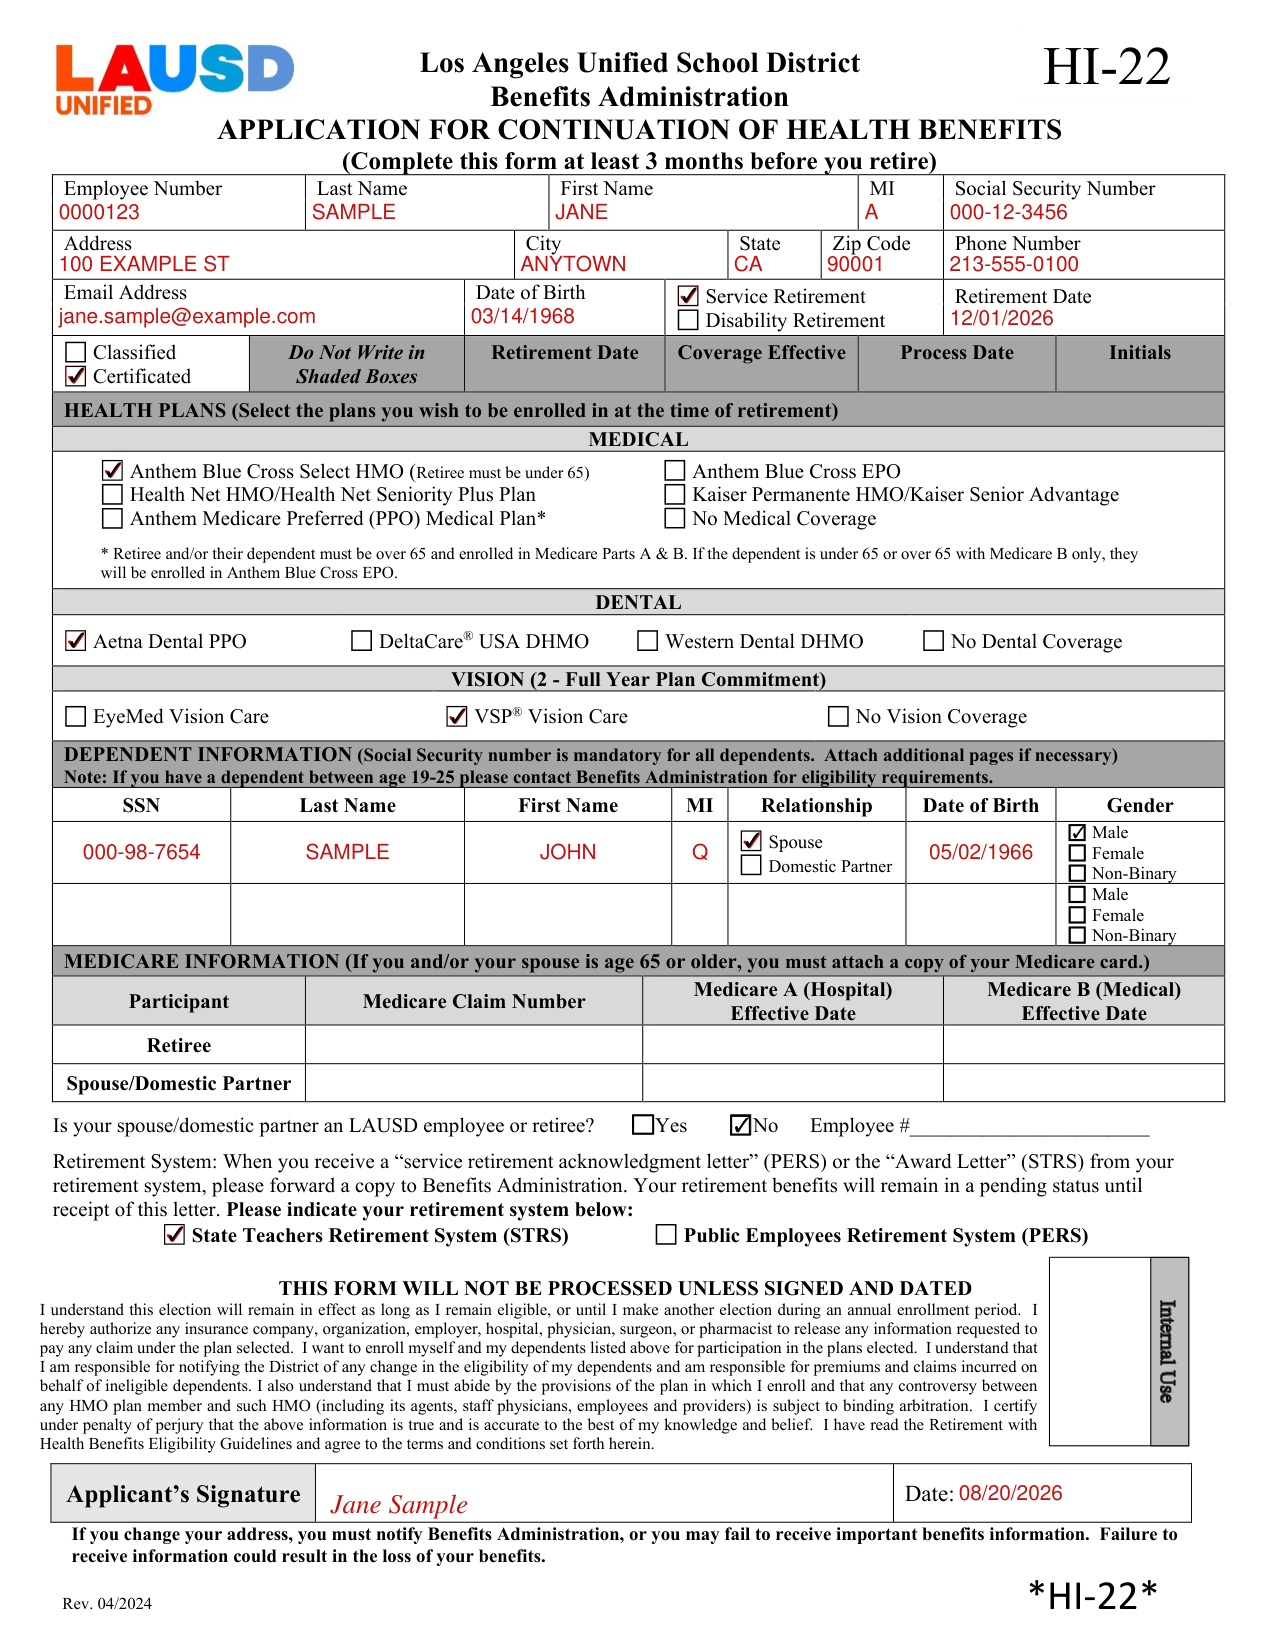
How to fill out Form HI-22, box by box
Employee Number, name, address and Date of Birth
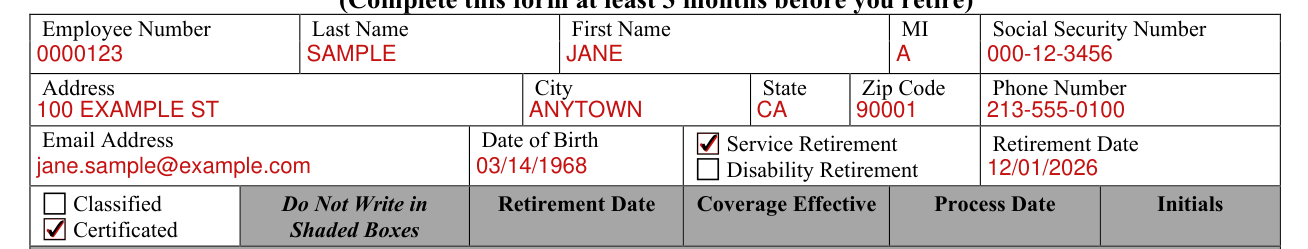
Enter the Employee Number, Last Name, First Name, MI, Social Security Number, Address, City, State, Zip Code, Phone Number, Email Address and Date of Birth.
Service Retirement, Disability Retirement and Retirement Date
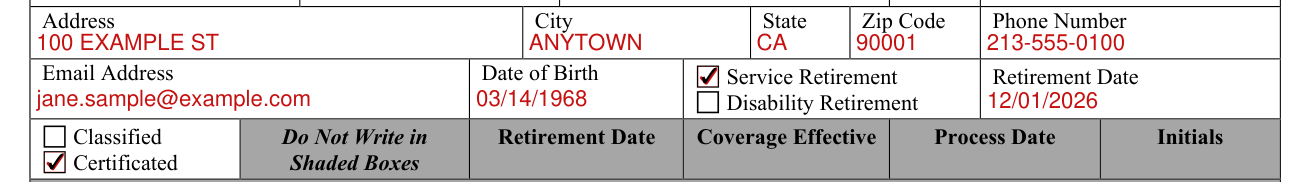
Check Service Retirement or Disability Retirement and enter the Retirement Date.
Classified or Certificated

Check Classified or Certificated.
Health plans: medical, dental and vision
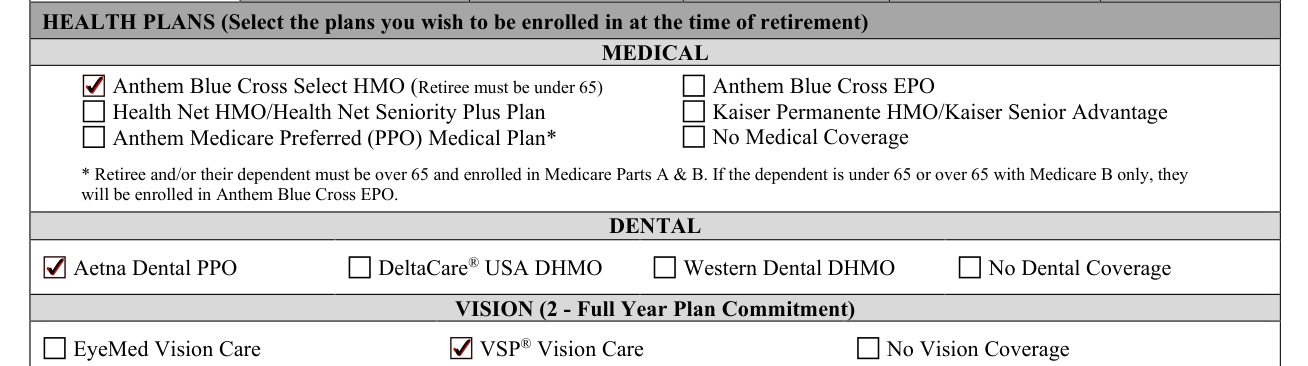
Select the plans you wish to be enrolled in at the time of retirement.
MEDICAL: Anthem Blue Cross Select HMO (Retiree must be under 65), Health Net HMO/Health Net Seniority Plus Plan, Anthem Medicare Preferred (PPO) Medical Plan*, Anthem Blue Cross EPO, Kaiser Permanente HMO/Kaiser Senior Advantage or No Medical Coverage.
* Retiree and/or their dependent must be over 65 and enrolled in Medicare Parts A & B. If the dependent is under 65 or over 65 with Medicare B only, they will be enrolled in Anthem Blue Cross EPO.
DENTAL: Aetna Dental PPO, DeltaCare® USA DHMO, Western Dental DHMO or No Dental Coverage.
VISION (2 - Full Year Plan Commitment): EyeMed Vision Care, VSP® Vision Care or No Vision Coverage.
Dependent information
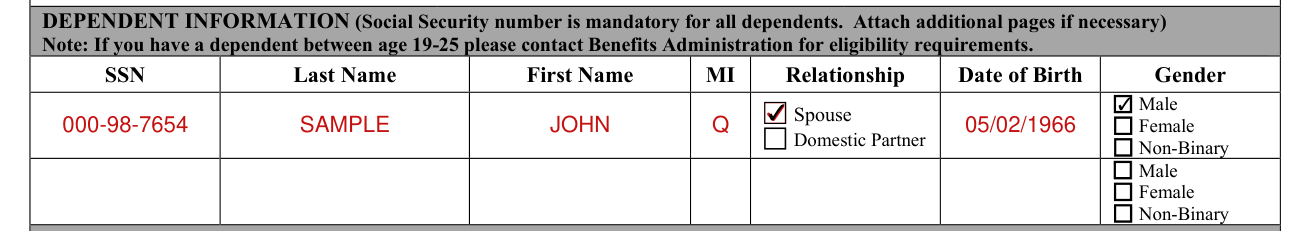
Social Security number is mandatory for all dependents. Attach additional pages if necessary. If you have a dependent between age 19-25 please contact Benefits Administration for eligibility requirements.
Enter the SSN, Last Name, First Name, MI, Relationship (Spouse or Domestic Partner), Date of Birth and Gender (Male, Female or Non-Binary).
Medicare information

Enter the Participant Medicare Claim Number, the Medicare A (Hospital) Effective Date and the Medicare B (Medical) Effective Date for the Retiree and for the Spouse/Domestic Partner.
LAUSD employee or retiree

Check Yes or No for Is your spouse/domestic partner an LAUSD employee or retiree? and enter the Employee #.
Retirement System

When you receive a “service retirement acknowledgment letter” (PERS) or the “Award Letter” (STRS) from your retirement system, please forward a copy to Benefits Administration. Your retirement benefits will remain in a pending status until receipt of this letter. Please indicate your retirement system: State Teachers Retirement System (STRS) or Public Employees Retirement System (PERS).
Applicant's Signature and Date

Sign on the Applicant's Signature line and enter the Date.
THIS FORM WILL NOT BE PROCESSED UNLESS SIGNED AND DATED I understand this election will remain in effect as long as I remain eligible, or until I make another election during an annual enrollment period. I hereby authorize any insurance company, organization, employer, hospital, physician, surgeon, or pharmacist to release any information requested to pay any claim under the plan selected. I want to enroll myself and my dependents listed in Dependent information for participation in the plans elected. I understand that I am responsible for notifying the District of any change in the eligibility of my dependents and am responsible for premiums and claims incurred on behalf of ineligible dependents. I also understand that I must abide by the provisions of the plan in which I enroll and that any controversy between any HMO plan member and such HMO (including its agents, staff physicians, employees and providers) is subject to binding arbitration. Signing certifies under penalty of perjury that the information on this form is true and accurate to the best of my knowledge and belief. I have read the Retirement with Health Benefits Eligibility Guidelines and agree to the terms and conditions set forth herein.
If your situation is different
Years of qualifying service and age for employees hired
You must meet the following requirements. For employees hired prior to March 11, 1984, five (5) consecutive years of qualifying service immediately prior to retirement shall be required in order to qualify for retiree health benefits for the life of the retiree.
Hired on or after March 11, 1984, but prior to July 1, 1987: ten (10) consecutive years of qualifying service immediately prior to retirement shall be required in order to qualify for retiree health benefits for the life of the retiree.
Hired on or after July 1, 1987, but prior to June 1, 1992: fifteen (15) consecutive years of qualifying service immediately prior to retirement shall be required, or ten (10) consecutive years immediately prior to retirement plus an additional ten (10) years which are not consecutive.
Hired on or after June 1, 1992: years of qualifying service and age must total at least eighty (80) in order to qualify for retiree health benefits. For employees who have a break in service, this must include at least ten (10) consecutive years immediately prior to retirement.
Hired on or after March 1, 2007: a minimum of fifteen (15) consecutive years of service with the District immediately prior to retirement, in concert with the “Rule of 80” eligibility requirement (section 4.0 (d) of the agreement), to receive employee and dependents' health and welfare benefits (medical dental and vision) upon retirement as provided for in this agreement.
Hired on or after April 1, 2009: years of qualifying service and age must total at least eighty-five (85) in order to qualify for retiree health benefits. This must include a minimum of twenty-five (25) consecutive years of service with the District immediately prior to retirement.
For School Police (sworn personnel), if you were hired on or after April 1, 2009, the employee's age plus the number of consecutive qualifying years of service, when added together, must equal 80 and you must have twenty (20) consecutive years of qualifying service immediately prior to retirement.
For AALA and SEIU employees hired on or after July 1, 2018, years of qualifying service and age must total at least eighty-seven (87) in order to qualify for retiree health benefits. This must include a minimum of thirty (30) consecutive years of service with the District immediately prior to retirement.
For CSEA employees hired on or after September 1, 2018, years of qualifying service and age must total at least eighty-seven (87) in order to qualify for retiree health benefits, and this must include a minimum of thirty (30) consecutive years of service with the District immediately prior to retirement.
You or your dependent is age 65 or older
Medicare requirement (Effective January 1, 2010): If you and/or your dependent reach/are age 65 or older, you must enroll and remain enrolled in Medicare Part B.
If you do not enroll in Medicare Part B, you will lose your medical and prescription benefits until proof of enrollment is submitted.
If you and/or your dependent are eligible for Medicare Part A premium-free from the Centers of Medicare and Medicaid Services (CMS), you must enroll and remain enrolled in Medicare Part A.
If you are not eligible for Medicare Part A premium-free from CMS, you must verify ineligibility by providing LAUSD Benefits Administration with an ineligibility letter from CMS.
You separated, resigned without retiring, or were dismissed
You are not eligible for retirement health benefits if you separated, resigned without retiring, or were dismissed from District Service.
You take deferred retirement or a lump sum distribution
If you take deferred retirement (that is, leaving funds on deposit with the retirement system for withdrawal at a later date) or a lump sum distribution, you are not eligible for these retirement benefits.
Common questions about Form HI-22
Is there a deadline?
Complete this form at least 3 months before you retire.
Where do I file it?
Complete and return this form along with copies of the required documents via fax, email, or mail: Fax: (213) 241-4247 Email: benefits@lausd.net Los Angeles Unified School District - Benefits Administration P.O. Box 513307 Los Angeles, CA 90051-1307 Phone: (213) 241-4262 Website: lausd.org/benefits
Sources
[1] Form HI-22 (Rev. 04/2024), Application for Continuation of Health Benefits, Los Angeles Unified School District Benefits Administration (the Official source link on this page).
